ALDH3B2 / Aldehyde dehydrogenase family 3 member B2 · IHC design guide

Design Immunohistochemistry for ALDH3B2

Plan paraffin-section ALDH3B2 IHC using high staining in breast adipocytes as a reference (HPA tissue IHC). This guide covers fixation consistency, antibody dilution and cytoplasmic scoring, with the staining–RNA discrepancy in view (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ALDH3B2 (IHC for ALDH3B2): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A05723, validated IHC image, and IHC protocol steps
Printable ALDH3B2 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A05723, controls and protocol steps. Open the full ALDH3B2 IHC guide →

ALDH3B2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern High in breast adipocytes; cytoplasmic in several tissues (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Breast
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A05723)
Caveat Staining has low consistency with RNA data (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope No isoforms; propeptide 383–385, chain 1–382 (UniProt)
Section 1

Recommended ALDH3B2 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with published ALDH3B2 tissue staining protocols (PMC6776190; PMC8671409).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver carcinoma tissue; fixative not specified (datasheet A05723)
FixationImage fixative and duration unreported (datasheet A05723); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ALDH3B2, 1:50-1:200 (datasheet A05723)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultALDH3B2-positive staining in adipocytes of breast (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues including breast. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 at 95–98 °C for 20 min (page retrieval rule). EDTA pH 8.0 was used for the tissue microarray (PMC8671409).
Section 2

What Is the Expected ALDH3B2 Staining Pattern?

In paraffin-section IHC, expect cytoplasmic staining, with high signal in breast adipocytes (HPA: tissue IHC). ALDH3B2 is associated with lipid droplets and has no transmembrane segment (UniProt P48448: localisation and topology). Treat this as a provisional pattern: HPA rates its tissue IHC antibody Approved but reports low consistency with RNA expression and pending external verification (HPA: reliability description).

What am I looking at on my slide?
Strong cytoplasmic chromogen in breast adipocytes, with little signal in adjacent structures.This matches the clearest supplied positive reference: breast adipocytes are scored High, and the tissue profile is cytoplasmic (HPA: tissue IHC). Record the cell type and compartment as well as intensity; a brown deposit alone does not establish target-specific staining.
Signal is confined to nuclei, extracellular material, or cell borders instead of adipocyte cytoplasm.That distribution departs from the reported tissue IHC pattern (HPA: cytoplasmic expression; High in breast adipocytes). Check section morphology, chromogen deposits, and controls before calling it ALDH3B2. HPA separately lists an ICC-IF membrane summary without images, so that summary cannot validate membrane-only paraffin IHC (HPA: subcellular record).
Strong staining appears in adrenal glandular cells or bronchial respiratory epithelial cells.Those specific cell populations are scored Not detected (HPA: tissue IHC). Investigate antibody cross-reactivity or endogenous detection activity with appropriate controls. Do not generalise the finding to every cell in either tissue, or assume that all staining outside breast is false: HPA describes cytoplasmic expression in several tissues (HPA: tissue profile).
Colour spreads across stroma, empty spaces, and several cell types without defined cytoplasm.This is difficult to score as cellular ALDH3B2 because the supplied tissue pattern is cytoplasmic (HPA: tissue IHC). Consider uneven reagent coverage, incomplete blocking, excess chromogen development, or endogenous enzyme activity as general IHC possibilities; compare a matched negative control and review the section before assigning specificity.
Breast adipocytes show no convincing cytoplasmic signal.A negative result conflicts with the supplied High reference (HPA: breast adipocytes), but one section does not prove biological absence. First verify preserved morphology, an active detection system, a suitable positive control, and the antibody's stated IHC use. HPA notes low staining-versus-RNA consistency and pending external verification, so avoid using this reference as an absolute pass criterion (HPA: reliability description).
💡Expected ALDH3B2 appearanceA credible positive is High cytoplasmic staining in breast adipocytes (HPA: tissue IHC), consistent with lipid-droplet association (UniProt P48448: localisation); isolated nuclear, extracellular, or widespread structure-free colour warrants investigation as a possible false positive.
How each factor affects the staining
Tissue and cell contextBreast adipocytes are High, while adipocytes in adipose tissue are Not detected (HPA: tissue IHC). Identify the sampled tissue before using an adipocyte result as a positive or negative control; the two HPA observations do not support a universal adipocyte expectation.
Subcellular interpretationUniProt places ALDH3B2 at lipid droplets and annotates no transmembrane segment (UniProt P48448). HPA describes cytoplasmic tissue staining, whereas its ICC-IF entry says Membrane but supplies no image-bearing cell lines (HPA: tissue IHC and subcellular record). Keep those assay-specific observations distinct.
Protein processing and epitope uncertaintyUniProt lists a 1–382 chain and a 383–385 propeptide, with no annotated glycosylation sites or isoforms (UniProt P48448). The supplied record does not locate the antibody epitope. These annotations cannot predict whether retrieval will expose it or whether a particular processing state will stain.
Evidence strength and IF/ICC questionWhat should IF/ICC show? HPA provides a Membrane summary but no ICC-IF image-bearing cell lines, and the listed antibody has IHC Approved with no ICC status (HPA: subcellular and antibody records). Use the cytoplasmic paraffin IHC result as the IHC reference; this evidence does not establish an IF/ICC protocol or a confirmed IF pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in breast adipocytes.The result disagrees with the High tissue reference (HPA: breast adipocytes); failed detection or unsuitable assay conditions remain possible.Confirm adipocyte morphology and run a matched positive control and detection-system control. Check the IHC-validated antibody's own instructions before adjusting general IHC steps; no ALDH3B2-specific retrieval or dilution is supplied.
All sections, including expected negative cells, stain.The pattern may reflect background or endogenous detection activity; adrenal glandular cells are Not detected in the supplied reference (HPA: tissue IHC).Review a no-primary control and the detection chemistry. Apply an appropriate endogenous-activity block if the control indicates it, then reassess cell-localised staining against the HPA reference.
Nuclei or extracellular spaces dominate the image.This diverges from cytoplasmic tissue expression (HPA: tissue profile). Deposits, tissue artefact, or nonspecific binding are possible general IHC explanations.Inspect morphology and the negative control; repeat with clean sections and controlled chromogen development if needed. Score only interpretable cellular signal.
Breast adipocytes stain, but adipocytes in adipose tissue do not.The difference matches the supplied tissue-specific observations: High in breast adipocytes and Not detected in adipose-tissue adipocytes (HPA: tissue IHC).Document tissue identity and compare equivalent cell populations within each section. Do not increase signal development solely to force the adipose-tissue sample positive.
A sharply outlined membrane pattern replaces cytoplasmic IHC staining.HPA's tissue IHC profile is cytoplasmic; its separate ICC-IF Membrane summary lacks image-bearing cell lines (HPA: tissue and subcellular records).Check whether the outline follows cells, tissue edges, or chromogen pooling; review controls before interpreting it. Report any reproducible discrepancy as assay-specific.
Staining is weak or inconsistent between sections.HPA reports low consistency between antibody staining and RNA expression and pending external verification (HPA: reliability description); the record does not identify a target-specific fixation effect.Compare matched sections, tissue preservation, control performance, and documented IHC conditions. Optimise retrieval or antibody concentration only as general IHC variables, without claiming an ALDH3B2-specific fixation sensitivity.

Sample controls for ALDH3B2 IHC & IF

🧪Run breast first and look for staining in adipocytes (HPA: High in breast adipocytes). Run adipose tissue as the negative comparator (HPA: Not detected in adipose-tissue adipocytes); on the breast slide, use non-adipocyte cells as internal background references only after confirming that they lack signal.
Positive control tissue: Breast (Adipocytes, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for ALDH3B2; derive a cell-line control from the positive tissue's cell type (Adipocytes) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control, host-species- and Ig-class-matched control IgG, and ALDH3B2 knockout material if available. Check endogenous peroxidase and biotin background in the breast section because the selected image uses avidin–peroxidase detection (selected SKU caption: avidin–peroxidase).
⚠️Feasibility: A target-specific fixation window and the fixative used for the selected paraffin-section image are unreported (selected SKU caption: fixative not stated). Retrieval dependence is also unreported, so optimize retrieval empirically; the supplied evidence does not establish that frozen sections or IF/ICC are easier. In lipid-rich breast adipocytes, processing-related empty lipid spaces can complicate interpretation of staining near the droplet boundary (UniProt P48448: lipid-droplet localisation; HPA: High in breast adipocytes).

HPA tissue IHC evidence for ALDH3B2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Breast Adipocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced ALDH3B2 IHC Tips

Troubleshoot ALDH3B2 staining in paraffin sections by checking retrieval, compartment, cell identity and controls before comparing signal intensity (UniProt P48448; HPA tissue IHC).

What retrieval should I try when ALDH3B2 staining is weak in paraffin sections?
Use citrate buffer at pH 6.0 for HIER at 95–98 °C for 20 min (page retrieval rule: cytoplasmic / membrane antigen). Keep section thickness, heating time and cooling conditions consistent across the comparison set, then inspect tissue integrity before increasing detection strength (standard IHC practice). The catalog image shows staining in paraffin-embedded human liver carcinoma at 1:50, but its caption does not report retrieval conditions (A05723 caption). If signal remains weak, compare a longer citrate incubation on serial sections while retaining the same controls and scoring criteria (standard IHC practice). Record any increase in diffuse background alongside the change in expected cytoplasmic signal (HPA tissue IHC; standard IHC practice).
Could fixation explain inconsistent ALDH3B2 staining between paraffin blocks?
ALDH3B2-specific fixation sensitivity is unknown because the selected tissue caption identifies paraffin embedding but gives no fixative (A05723 caption). For a controlled comparison, process matched samples with the same 10% neutral buffered formalin workflow and record fixation start, duration and specimen thickness (standard IHC practice). Compare serial sections stained in one run at the same antibody dilution; the catalog image used 1:50 (A05723 caption). If blocks differ, interpret a weaker result cautiously until retrieval, section quality and positive-control staining have been checked together (standard IHC practice). Neither the reported tissue pattern nor the protein annotation establishes a fixation effect for this target (HPA tissue IHC; UniProt P48448).
How should I judge cytoplasmic versus membrane ALDH3B2 staining?
Score the distribution within intact cells as well as its intensity: the catalog image describes cytoplasmic and membrane staining in paraffin-embedded human liver carcinoma (A05723 caption). UniProt places ALDH3B2 at lipid droplets and annotates no transmembrane segment, so a punctate cytoplasmic pattern can fit its reported biology (UniProt P48448 localisation and topology). HPA reports cytoplasmic expression across several tissues, while its subcellular summary says membrane without available main-location detail (HPA tissue IHC; HPA subcellular). Review matched 1:50 catalog-style staining and a no-primary control before calling a sharp surface outline specific (A05723 caption; standard IHC practice). Document diffuse, punctate and peripheral signal separately instead of merging them into one positive score (standard IHC practice).
What epitope issues matter when ALDH3B2 staining changes after retrieval?
Check the antibody's stated immunogen and epitope information before interpreting a changed pattern; those details are absent from the supplied caption (A05723 caption). The record lists 0 isoforms and a processed chain spanning residues 1–382, with a 383–385 propeptide (UniProt P48448 processing and isoforms). A cysteine methyl ester is annotated at residue 382, but its effect on this antibody's binding is unknown (UniProt P48448 modified residues; A05723 caption). Compare serial sections under the recommended citrate pH 6.0, 20 min retrieval and the same dilution before assigning the change to epitope exposure (page retrieval rule; standard IHC practice). If epitope details become available, check whether they overlap the processed region or modified residue (UniProt P48448; standard IHC practice).
How can I assess ALDH3B2 by IF alongside a cell identity marker?
Treat IF/ICC as an independently optimised assay: the supplied antibody image documents paraffin-section chromogenic IHC, and no ICC/IF images are listed here (A05723 caption; HPA subcellular). Multiplex ALDH3B2 with a marker for the cell population under study, then assess whether the two signals occupy the expected cells in separate channels (standard IF practice). Choose a fluorophore channel after measuring tissue autofluorescence with an unstained control, and use single-stain controls to check spectral bleed-through (standard IF practice). For an intracellular epitope, titrate detergent permeabilisation from 0.1% while checking membrane-marker retention; the exact antibody epitope is unspecified, and ALDH3B2 has no annotated transmembrane segment (A05723 caption; UniProt P48448 topology; standard IF practice). Interpret puncta with reference to its lipid-droplet annotation, without treating IF localisation as established by the IHC image (UniProt P48448 localisation; A05723 caption).
How do I troubleshoot widespread brown signal in ALDH3B2 IHC?
Run a no-primary section through the same secondary and avidin–peroxidase detection steps used in the catalog image; its negative control substituted PBS for primary antibody (A05723 caption). Quench endogenous peroxidase with 3% hydrogen peroxide for 10 min, then check whether staining persists in the no-primary section (standard chromogenic IHC practice). If it does, review secondary binding, avidin-related background and blocking conditions before changing the ALDH3B2 antibody concentration (standard IHC practice). If only primary-treated sections stain diffusely, compare serial sections at and below the illustrated 1:50 dilution while holding development time constant (A05723 caption; standard IHC practice). Judge residual staining against intact cytoplasmic patterns, rather than brown deposits at folds or damaged edges (HPA tissue IHC; standard IHC practice).
What is a defensible way to quantify ALDH3B2 IHC across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because HPA reports cytoplasmic staining while the catalog caption also describes membrane staining (HPA tissue IHC; A05723 caption). An H-score can combine the percentage of cells at intensities 0–3, yielding 0–300; retain separate cytoplasmic and peripheral scores where both occur (standard IHC practice). Alternatively, report percentage positive cells or positive-cell density per mm² within an annotated viable-tissue region (standard IHC practice). Normalise counts to the number of eligible cells or viable area, and compare sections stained in the same batch with fixed thresholds and exposure conditions (standard IHC practice). Include a no-primary control and record whether staining is cell-associated before accepting faint positives (A05723 caption; standard IHC practice).
When should an ALDH3B2-positive area be considered an artefact?
Favour signal in intact cell cytoplasm, with any peripheral component assessed separately; those patterns are described in tissue evidence, and UniProt associates the protein with lipid droplets (HPA tissue IHC; A05723 caption; UniProt P48448 localisation). Question isolated nuclear staining, acellular deposits and signal concentrated at section edges or necrotic regions, then compare adjacent intact areas (standard IHC practice). Check the no-primary section for endogenous enzyme or detection-system signal before calling brown deposits target-specific (A05723 caption; standard chromogenic IHC practice). Cell identity matters: HPA reports high staining in breast adipocytes but no detection in adipose-tissue adipocytes, indicating context-dependent observations (HPA tissue IHC). Treat unexpected cell populations cautiously because HPA also describes low agreement between staining and RNA expression and pending external verification (HPA reliability description).
Boster reagents

Best ALDH3B2 / Aldehyde dehydrogenase family 3 member B2 IHC Antibodies

A05723 has an IHC image from paraffin-embedded human liver carcinoma (A05723 image caption). A05723-1 lists IF/ICC applications but supplies no IF image (A05723-1 catalog). Both list human, mouse and rat reactivity (catalog).

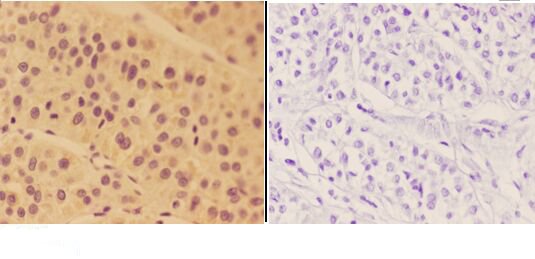
Real IHC data Immunohistochemistry (IHC) analyzes of ALDH3B2 pAb in paraffin-embedded human liver carcinoma tissue at 1:50,showing cytoplasm and membrane staining.Negative control (the right)Using PBS instead of primary antibody, secondary antibody is Goat Anti-Rabbit IgG-biotin followed by avidin-peroxidase.
Anti-ALDH3B2 Antibody
Cat # A05723

The rendered card is A05723, with an IHC image from a paraffin-embedded human liver carcinoma section stained at 1:50 (A05723 image caption). Its catalog lists IHC and human, mouse and rat reactivity; its image shows cytoplasmic and membrane staining (A05723 catalog; A05723 image caption).

Which to pick: For tissue IHC, choose A05723: this rabbit polyclonal has an IHC image from a human paraffin section and a listed dilution of 1:50–1:200 (A05723 catalog; A05723 image caption). For IF/ICC, choose A05723-1, a rabbit polyclonal that lists both applications at 1:50; no IF image is supplied (A05723-1 catalog). Both list human, mouse and rat reactivity, but the supplied tissue image documents human tissue only; its fixative is unreported (A05723 and A05723-1 catalogs; A05723 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P48448 (AL3B2_HUMAN, Aldehyde dehydrogenase family 3 member B2).
  2. Human Protein Atlas. ALDH3B2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. ALDH3B2 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. ALDH3B2 antibody validation summary (1 antibodies).
  5. Identification of new cancer stem cell markers and signaling pathways in HER‑2‑positive breast cancer by transcriptome sequencing. International journal of oncology 2019 — PMC6776190.
  6. Aldehyde dehydrogenase 3B2 promotes the proliferation and invasion of cholangiocarcinoma by increasing Integrin Beta 1 expression. Cell death & disease 2021 — PMC8671409.
  7. PubMed PMID:7484374 — UniProt-cited evidence.
  8. PubMed PMID:8890755 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.