This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section APLNR IHC using the reported cytoplasmic tissue pattern and medium staining in heart cardiomyocytes (HPA tissue IHC). Start the catalog antibody at 1:100–1:300 (datasheet) and include a no-primary control (standard IHC practice).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic in tissue (HPA tissue IHC); cell membrane (UniProt) | |
| Staining pattern | Cytoplasmic staining in several tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Caudate+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A05042) | |
| Caveat | Staining has low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | APLN/APELA drive internalization (UniProt) | |
| Isoform / epitope | No isoforms annotated; extracellular versus cytoplasmic epitope matters (UniProt) |
The catalog antibody’s IHC protocol is accompanied by published APLNR IHC methods for kidney, cuprizone model sections, and renal carcinoma tissue (PMC11351430; PMC11641372; PMC6461937; PMC13208026).
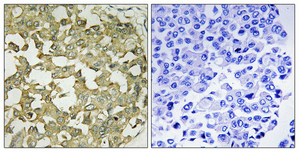
| Sample | Paraffin-embedded Human breast cancer tissue; fixative not specified (datasheet A05042) |
| Fixation | Image fixative and duration unreported (datasheet A05042); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-APLNR, 1:100-1:300 (datasheet A05042) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | APLNR-positive staining in neuronal cells of caudate (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in several tissues. No signal in the no-primary control. |
APLNR is a seven-pass cell-membrane receptor (UniProt P35414 topology). In paraffin-section IHC, look for staining in the appropriate cells, including cardiomyocytes and selected neuronal or glial cells with medium staining reported by HPA (HPA tissue IHC). Cytoplasmic staining can be plausible: HPA describes cytoplasmic expression in several tissues, and UniProt reports receptor internalization and recycling. Interpret cautiously because HPA rates the tissue IHC antibody Approved but reports low consistency with RNA expression (HPA tissue IHC).
| Membrane-associated staining in cardiomyocytes, caudate neuronal cells, or cortical glial cells. | This fits the receptor's cell-membrane location (UniProt P35414) and HPA's medium IHC staining in those named cells (HPA tissue IHC). A visible membrane outline supports the expected compartment; judge it alongside cell identity and controls because HPA reports low consistency between antibody staining and RNA expression (HPA tissue IHC). |
| Cytoplasmic puncta or a cytoplasmic signal accompany staining in an expected cell type. | Cytoplasmic staining is reported across several tissues (HPA tissue IHC). Ligand exposure can move APLNR into an endosomal recycling compartment (UniProt P35414 subcellular location), so cytoplasmic signal alone is not proof of an artefact. Predominantly nuclear staining has no support in the supplied APLNR localization records (UniProt P35414; HPA tissue IHC). |
| Strong staining appears in a cell population other than the reported positive population. | Check cell identity before assigning the signal to APLNR. For example, HPA reports medium staining in cortical glial cells and caudate neuronal cells, but no detection in lymph-node germinal-center cells (HPA tissue IHC). Unexpected staining raises the possibility of cross-reactivity or endogenous chromogenic activity; a no-primary control can help distinguish detection background (general IHC practice). |
| Chromogen is diffuse across tissue, including cells expected to be unstained. | A widespread haze does not establish receptor localization. Compare a no-primary control and inspect tissue-edge or damaged areas for nonspecific deposition (general IHC practice). HPA's cytoplasmic-expression summary does not make uniform staining of every cell an expected APLNR result (HPA tissue IHC). |
| No signal is visible in heart-muscle cardiomyocytes or cerebral-cortex glial cells. | Both are reported as medium-staining populations, so absence of signal warrants checking the run (HPA tissue IHC). Verify the positive-control section, antibody and detection steps, and section integrity (general IHC practice). HPA's Approved rating and low RNA–staining consistency mean a negative result in one specimen cannot, by itself, establish absent APLNR protein (HPA tissue IHC). |
| Seven-pass topology and trafficking (UniProt P35414). | APLNR spans the membrane seven times, with extracellular and cytoplasmic regions (UniProt P35414 topology). Apelin or APELA exposure can drive internalization into a recycling compartment (UniProt P35414 subcellular location); assess membrane and cytoplasmic signal together rather than requiring a continuous membrane rim. |
| Choice of cells for interpretation (HPA tissue IHC). | HPA reports medium staining in heart-muscle cardiomyocytes, hippocampal glial cells, and several other named populations (HPA tissue IHC). It reports no detection in colon glandular cells and lymph-node germinal-center cells under its IHC conditions (HPA tissue IHC). Those observations guide comparisons; they do not prove every specimen of a tissue will behave identically. |
| Strength of IHC evidence (HPA tissue IHC; HPA antibody record). | The listed mouse monoclonal antibody CAB025842 is IHC Approved, while the tissue profile notes low consistency between staining and RNA expression (HPA antibody record; HPA tissue IHC). Treat a matching pattern as supportive evidence and investigate unexpected cell types or compartments before assigning biological meaning. |
| What does IF/ICC evidence add? (HPA subcellular record). | HPA summarizes APLNR as membrane-localized for ICC-IF, but lists no main location or cell-line images (HPA subcellular record). That summary supports a localization expectation; it supplies no image-backed IF/ICC pattern here. IF/ICC methods belong in their own guide. |
| Fixation and retrieval evidence (UniProt P35414; HPA tissue IHC). | Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation. |
| Situation | Likely cause | Next action |
|---|---|---|
| No staining in a positive-control heart-muscle section (HPA tissue IHC: medium in cardiomyocytes). | The staining run may have failed, or the sampled cells may be difficult to identify; one absent signal does not establish absent receptor. | Confirm cardiomyocyte morphology, section integrity, antibody application, chromogenic detection, and a working positive control (general IHC practice). Record HPA's low RNA–staining consistency when interpreting the result (HPA tissue IHC). |
| Signal is confined to nuclei in an otherwise interpretable section. | Nuclear localization is unsupported by the supplied membrane and cytoplasmic APLNR records (UniProt P35414; HPA tissue IHC). | Review a no-primary control, counterstain, and nonspecific chromogen deposition (general IHC practice). Do not score nuclear-only staining as a convincing APLNR-positive pattern. |
| Every cell has similar cytoplasmic color, obscuring the reported positive populations. | Diffuse background can conceal cell-restricted staining (general IHC practice); HPA reports cytoplasmic expression in several tissues, not a uniform all-cell pattern (HPA tissue IHC). | Compare no-primary and positive-control sections, then reassess blocking, antibody concentration, washes, and detection development as general IHC variables. |
| A cell population reported as undetected stains strongly, such as colon glandular cells (HPA tissue IHC). | Possible explanations include misidentified cells, cross-reactivity, or endogenous chromogenic activity (general IHC practice). HPA's undetected call describes its tested conditions, not an absolute biological negative. | Check cell identity and the no-primary control; assess endogenous enzyme activity if relevant to the detection system (general IHC practice). Compare the result with a named medium-staining HPA population (HPA tissue IHC). |
| Cytoplasmic staining lacks a crisp membrane rim in an otherwise expected cell population. | HPA reports cytoplasmic tissue staining, and UniProt describes internalization and recycling after ligand exposure (HPA tissue IHC; UniProt P35414). The supplied evidence does not establish ligand exposure in this particular section. | Score the cell type and distribution, compare controls, and describe the observed compartment precisely. Avoid assigning trafficking as the cause without independent evidence. |
| ICC-IF expectations are being used to judge a chromogenic paraffin section. | HPA's ICC-IF entry says Membrane but provides no cell-line images, whereas its tissue IHC profile describes cytoplasmic expression (HPA subcellular record; HPA tissue IHC). | Use the tissue IHC observations and their reliability caveat for this section (HPA tissue IHC). Treat the ICC-IF summary as limited localization context and consult the separate IF/ICC guide for that application. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Cerebral cortex | Glial cells | Medium | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | Medium | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | Medium | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
APLNR is a seven-pass membrane receptor that can recycle through endosomes after ligand exposure (UniProt P35414). These questions focus on chromogenic IHC of paraffin sections.
A05042 has real IHC data from paraffin-embedded human breast cancer and catalog-listed IF; its stated reactivity covers human, mouse, and rat (A05042 IHC image caption; catalog applications/reactivity).
A05042 is the sole card and shows IHC on paraffin-embedded human breast cancer at 1:100 (A05042 IHC image caption). Its catalog lists IF and human, mouse, and rat reactivity, but provides no IF figure (A05042 catalog applications/reactivity; IF image alts).
Which to pick: For tissue IHC, choose A05042: its own figure documents paraffin-embedded human breast cancer at 1:100; the fixative is unreported (A05042 IHC image caption). For IF, A05042 is listed at 1:200–1:1000, but no IF figure or ICC validation is supplied (A05042 catalog applications/dilutions; IF image alts). For cross-species work, A05042 lists human, mouse, and rat reactivity, while its supplied tissue figure covers human only; clonality is unreported (A05042 catalog reactivity/clone; IHC image caption).