This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan CAMLG paraffin IHC using its cytoplasmic tissue staining pattern (HPA tissue IHC) and ER membrane location (UniProt). The catalog antibody has an IHC dilution range of 2–5 μg/ml (datasheet A08322-2); cerebral cortex neurons stain strongly, while adipocytes have no detected staining (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue stain (HPA tissue IHC); ER membrane protein (UniProt) | |
| Staining pattern | Cytoplasmic in neurons and fallopian glandular cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A08322-2) | |
| Positive control | Cerebral cortex+4 more · see all | |
| Negative control | Adipose tissue+3 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining has medium consistency with tissue RNA data (HPA tissue IHC) | |
| Regulation | Highest in brain, testis and ovary (UniProt) | |
| Isoform / epitope | No annotated isoforms; cytoplasmic vs lumenal epitope matters (UniProt) |
The catalog antibody’s IHC-P protocol uses EDTA pH 8.0 retrieval (datasheet A08322-2). The published CAMLG brain-section protocol below uses heated citric acid retrieval (PMC12093335: methods).
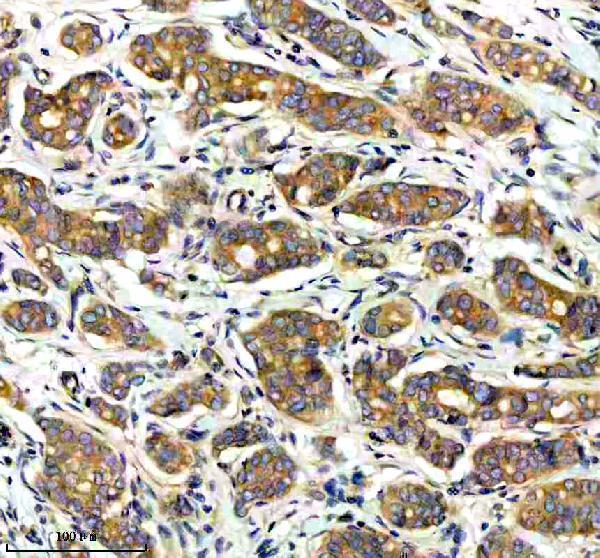
| Sample | Paraffin-embedded human breast cancer tissue; fixative not specified (datasheet A08322-2) |
| Fixation | Image fixative and duration unreported (datasheet A08322-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A08322-2); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A08322-2) |
| Primary antibody | Rabbit anti-CAMLG, 2-5 μg/ml (datasheet A08322-2) |
| Primary incubation | Overnight at 4 °C (datasheet A08322-2) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A08322-2) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CAMLG-positive staining in neuronal cells of cerebral cortex (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control. |
CAMLG is an endoplasmic reticulum membrane protein with 3 transmembrane segments (UniProt P49069 topology). In paraffin-section IHC, expect predominantly cytoplasmic staining, especially in cerebral cortex neuronal cells and fallopian tube glandular cells (HPA: general cytoplasmic expression; High in both cell populations). Interpret the pattern with caution: HPA rates its tissue IHC evidence Approved, with medium consistency between staining and RNA expression (HPA: tissue IHC reliability).
| Cytoplasmic chromogen in cortex neurons or fallopian tube glandular cells, stronger than nearby background. | This matches the reported High staining in those cells and the general cytoplasmic IHC profile (HPA: tissue IHC). An ER membrane protein can appear as cytoplasmic staining at light-microscope resolution (UniProt P49069: ER membrane). Assess intensity and distribution in the named cells, rather than treating every stained cell as equally informative. |
| Predominantly nuclear or sharply plasma-membrane staining, with little cytoplasmic signal. | That distribution conflicts with the reported tissue IHC profile and ER membrane annotation (HPA: general cytoplasmic expression; UniProt P49069: ER membrane). Consider nonspecific staining or an interpretation artefact; inspect morphology and controls before calling it CAMLG. HPA's uncertain nuclear ICC-IF observations do not establish a nuclear IHC pattern (HPA: subcellular ICC-IF). |
| Strong signal in adipocytes, marrow hematopoietic cells, skeletal myocytes, or soft-tissue fibroblasts. | HPA reports CAMLG as Not detected in those particular cell populations (HPA: tissue IHC). Investigate antibody cross-reactivity or endogenous detection activity, especially if the positive control stains as expected. These are comparison cells, not universal biological negatives: UniProt describes CAMLG expression as ubiquitous (UniProt P49069: tissue specificity). |
| Diffuse chromogen across cells and extracellular spaces, obscuring cell boundaries. | The distribution cannot be scored confidently against HPA's cell-specific, general cytoplasmic profile (HPA: tissue IHC). In routine IHC, incomplete blocking, excess antibody, or detection background can produce diffuse signal (general IHC practice). Compare a no-primary control and review the detection steps before interpreting weak cellular staining. |
| No detectable staining in cortex neurons or fallopian tube glandular cells. | This misses the strongest supplied tissue examples (HPA: High in both cell populations). First check section integrity and a working positive control; then review retrieval, antibody concentration, and detection as general IHC variables. A failed positive control prevents a reliable negative call for the test section (general IHC practice). |
| Cell population and tissue | HPA reports High staining in cortex neuronal cells and fallopian tube glandular cells, Medium staining in several other listed populations, and Not detected in specified adipocytes, marrow cells, myocytes, and fibroblasts (HPA: tissue IHC). Score the named cell population rather than assigning one intensity to the whole section. |
| Membrane topology and epitope access | CAMLG has 3 transmembrane segments and both cytoplasmic and lumenal regions (UniProt P49069 topology). An antibody's epitope location is not supplied, so topology alone cannot justify a particular retrieval method or predict how processing will affect staining. |
| IHC evidence and antibody choice | HPA lists HPA052636 and HPA056472 as IHC Approved, and rates the tissue profile Approved with medium staining–RNA consistency (HPA: antibodies; tissue IHC reliability). Approved supports use as a starting point, while the observed pattern and controls still determine whether an individual run is interpretable. |
| Low and absent HPA observations | HPA reports Low staining in selected glandular cells, cholangiocytes, and splenic red-pulp cells, while some other listed populations are Not detected (HPA: tissue IHC). Weak or absent staining in one population should be compared with its own HPA entry; UniProt's ubiquitous tissue description does not imply detectable IHC in every cell (UniProt P49069: tissue specificity). |
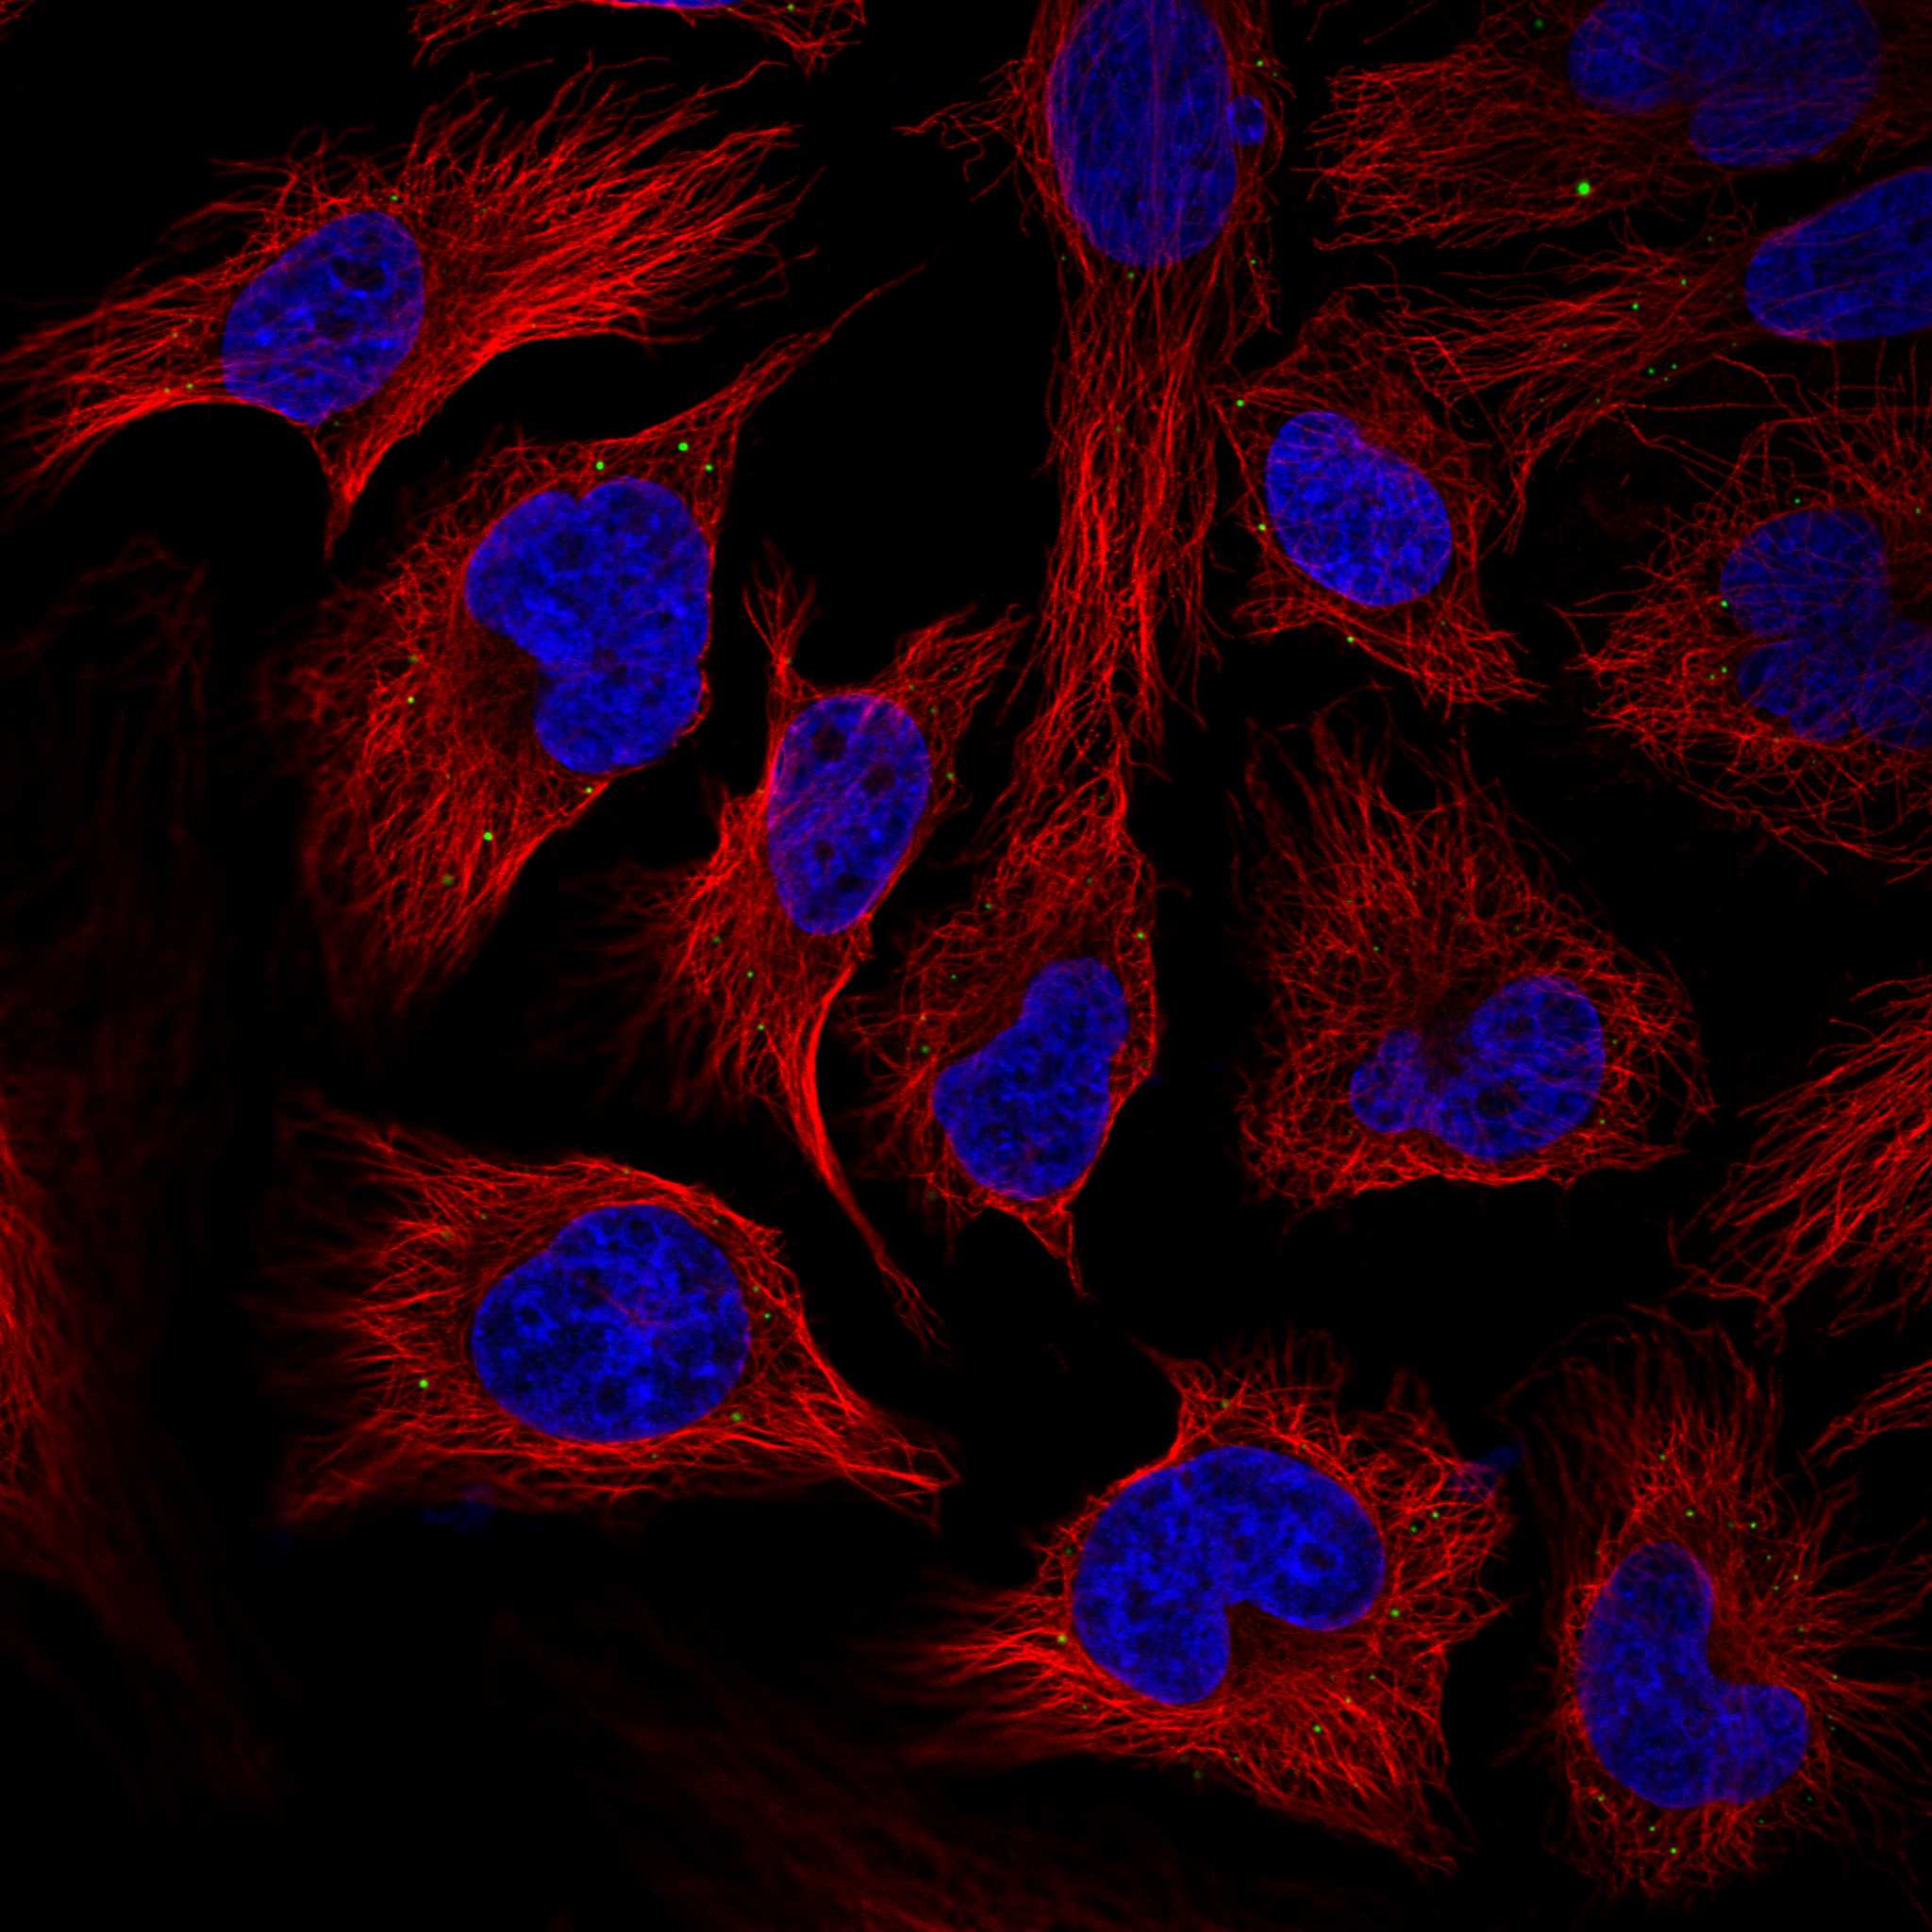
| ICC-IF localisation evidence | HPA calls vesicles the main ICC-IF location and nucleoplasm and nucleoli additional locations, all uncertain (HPA: subcellular ICC-IF). These observations may guide a separate IF assessment, but they do not override the general cytoplasmic tissue IHC profile or establish a nuclear paraffin-IHC positive call (HPA: tissue IHC). |
| Situation | Likely cause | Next action |
|---|---|---|
| Known-positive cortex neurons or fallopian tube glandular cells are blank. | The run may have insufficient detectable signal; HPA reports High staining in these cells (HPA: tissue IHC). | Confirm the positive-control section and detection reagents worked, then review retrieval and antibody concentration as general IHC checks. Do not interpret test-section absence while the control fails (general IHC practice). |
| A broad brown haze makes cytoplasmic staining hard to score. | Background from blocking, antibody concentration, or detection can obscure the reported cytoplasmic pattern (general IHC practice; HPA: tissue IHC profile). | Inspect a no-primary control and review blocking, washes, antibody concentration, and development time (general IHC practice). Score CAMLG only where cellular signal can be distinguished from background. |
| Nuclear staining dominates the paraffin section. | Predominant nuclear signal conflicts with the ER membrane annotation and general cytoplasmic tissue profile (UniProt P49069; HPA: tissue IHC). | Review morphology and controls, and compare the signal with cytoplasmic staining in a positive tissue. HPA's nuclear ICC-IF locations are uncertain and do not validate a nuclear IHC call (HPA: subcellular ICC-IF). |
| A purported negative comparator stains strongly. | HPA's Not detected calls apply to named cell populations, while UniProt describes broad tissue expression (HPA: tissue IHC; UniProt P49069: tissue specificity). | Verify which cells actually stain. If the signal is in an HPA Not detected population, check a no-primary control for endogenous detection activity and consider antibody cross-reactivity (general IHC practice). |
| Results differ between IHC antibodies or sections. | Both listed antibodies are IHC Approved, but HPA reports only medium consistency between antibody staining and RNA expression for the tissue profile (HPA: antibodies; tissue IHC reliability). | Compare the same named cell populations and matched controls across sections. Treat disagreement as unresolved until the staining distribution and controls support an interpretation (general IHC practice). |
| Q: Should an IF/ICC image show the same pattern as paraffin IHC? | HPA reports vesicular ICC-IF staining with additional nuclear locations, each uncertain, alongside a general cytoplasmic tissue IHC profile (HPA: subcellular ICC-IF; tissue IHC). | A: Evaluate IF/ICC localisation on its own guide page and retain the uncertainty labels. Do not use those ICC-IF observations to redefine a positive chromogenic IHC result (HPA: subcellular ICC-IF; tissue IHC). |



Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Skeletal muscle | Myocytes | Not detected | Protein (IHC) | HPA → |
| Soft tissue | Fibroblasts | Not detected | Protein (IHC) | HPA → |
Troubleshoot CAMLG staining in paraffin sections using the catalog antibody’s IHC evidence, expected cellular pattern, and matched controls.
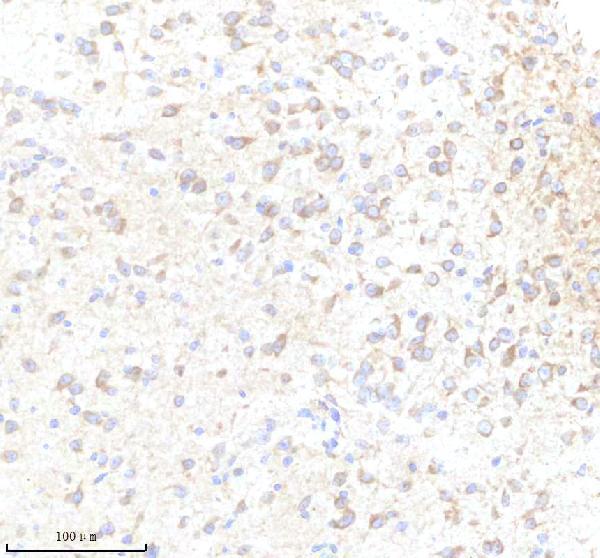
A08322-2 has IHC images from paraffin sections of human breast cancer, mouse brain, and rat brain (catalog image captions). No IF/ICC data are supplied (catalog applications and images).
A08322-2 is the only listed SKU; its application list includes IHC and its stated reactivity covers Human, Mouse, and Rat (catalog applications/reactivity). Its IHC images show human breast cancer, mouse brain, and rat brain paraffin sections (catalog image captions).
Which to pick: Choose A08322-2 for paraffin-section tissue IHC; its own captions document staining at 2 μg/ml in the pictured tissues (catalog image captions). For cross-species work, A08322-2 is a rabbit antibody with Human, Mouse, and Rat reactivity (catalog host/reactivity). No listed SKU has IF/ICC validation (catalog applications and images), and the IHC captions do not report the fixative (catalog image captions).