This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan CHAC1 paraffin-section IHC using the catalog antibody’s documented pancreas staining workflow (datasheet A09017-2). Compare cytoplasmic staining with HPA tissue IHC, including pancreatic endocrine cells and kidney tubule cells, while accounting for its low consistency with RNA expression (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | General cytoplasmic staining (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining across multiple tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A09017-2) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A09017-2) | |
| Caveat | Staining has low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | UPR-linked; intensity effect unproven (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope overlap is unknown (UniProt) |
The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet A09017-2). The published IHC protocols below provide conditions reported for gastric mucosa, kidney carcinoma, and lung adenocarcinoma samples (PMC6618068; PMC8034464; PMC11455913).
| Sample | Paraffin-embedded human pancreas tissue; fixative not specified (datasheet A09017-2) |
| Fixation | Image fixative and duration unreported (datasheet A09017-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A09017-2); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A09017-2) |
| Primary antibody | Rabbit anti-CHAC1, 1:50 recommended; image 2 μg/ml (datasheet A09017-2) |
| Primary incubation | Overnight at 4 °C (datasheet A09017-2) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A09017-2) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CHAC1-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control. |
CHAC1 is a soluble protein annotated in the cytosol and trans-Golgi network, with no transmembrane segment (UniProt Q9BUX1). In paraffin-section IHC, expect predominantly cytoplasmic staining in selected glandular, neuronal, renal tubular and pancreatic endocrine cells (HPA: general cytoplasmic expression; listed cells High). Treat intensity as a tissue-level guide: HPA rates its IHC evidence Approved but reports low consistency between antibody staining and RNA expression (HPA: reliability description).
| Cytoplasmic staining in appendix or gallbladder glandular cells, with less color in neighboring structures. | This matches the reported cell distribution and general cytoplasmic profile (HPA: Appendix and Gallbladder glandular cells High; general cytoplasmic expression). Compare cells within the same section before judging absolute color intensity; local tissue handling and chromogen development can affect that comparison (general IHC practice). |
| Cytoplasmic signal in kidney tubules, pancreatic endocrine cells, or Purkinje cells. | These are supported positive patterns (HPA: kidney cells in tubules High; pancreatic endocrine cells High; cerebellar Purkinje cells High). Record which cell population stains. A whole-tissue average can obscure a strong signal restricted to the listed cells (general IHC interpretation). |
| Predominantly nuclear or extracellular deposit instead of a cell-associated cytoplasmic pattern. | Neither compartment is the reported IHC pattern (HPA: general cytoplasmic expression; UniProt Q9BUX1: cytosol and trans-Golgi network). Review morphology, counterstain and the negative control before assigning this deposit to CHAC1; misplaced chromogen alone does not establish a second localization (general IHC practice). |
| Strong staining centered on an unlisted cell population while the expected cells are weak. | Consider cross-reactivity or endogenous detection activity, especially if the control shows the same distribution (general IHC practice). HPA lists specific High cell populations and reports low antibody–RNA consistency; its list cannot establish that every unlisted cell is truly negative (HPA: tissue IHC profile and reliability description). |
| Diffuse color across cells and stroma, or no signal in an HPA High cell population. | Diffuse deposit limits localization and suggests a background problem (general IHC practice). An absent signal merits a run-control check before a biological conclusion; HPA High describes observed staining, not guaranteed positivity in every specimen (HPA: tissue IHC profile; Approved with low antibody–RNA consistency). |
| Cell selection for interpretation | HPA reports High staining in selected glandular, neuronal, tubular and pancreatic endocrine cells; interpret those populations rather than labeling an entire organ uniformly positive (HPA: tissue IHC profile). |
| IHC evidence strength | The tissue profile is Approved, with low consistency between antibody staining and RNA expression; use the images as pattern guidance and avoid treating RNA abundance as a staining-intensity prediction (HPA: reliability description). |
| RNA versus protein example | Skeletal muscle has tissue-enhanced RNA specificity yet Low staining in myocytes. Choose a cell-level IHC control from the High staining list instead of inferring protein staining from RNA alone (HPA: RNA specificity; skeletal muscle myocytes Low). |
| Topology and processing | CHAC1 has no transmembrane segment, signal peptide, annotated propeptide or glycosylation site; UniProt lists the chain as residues 1–222. These annotations support a cell-associated interpretation but do not identify an antibody epitope or predict antigen-retrieval behavior (UniProt Q9BUX1). |
| IF/ICC Q&A: should mitochondria be expected in IHC? | HPA approves a mitochondrial ICC-IF location, whereas its tissue IHC profile is generally cytoplasmic and UniProt lists cytosol and trans-Golgi network. Report this assay-dependent difference; mitochondrial ICC-IF images do not establish mitochondrial resolution in chromogenic tissue IHC (HPA: subcellular and tissue profiles; UniProt Q9BUX1). |
| Situation | Likely cause | Next action |
|---|---|---|
| No visible staining in kidney tubules or appendix glandular cells. | The run may have a detection or tissue-handling failure; an absent signal alone cannot distinguish technical failure from specimen variation (general IHC practice; HPA: these cell populations High). | Check a same-run positive-control section, reagent sequence and chromogen development. If the run control works, review morphology and the specific cell population before recording a negative result (general IHC practice). |
| Color covers stroma and cells without clear borders. | Background may arise from nonspecific reagent binding or excessive chromogen development (general IHC practice). | Inspect the reagent-omission control, blocking and wash steps; compare background with a positive cell population on the same run (general IHC practice; HPA: general cytoplasmic expression). |
| Nuclear color dominates the expected cytoplasmic signal. | The distribution conflicts with reported tissue IHC and UniProt localization; counterstain or nonspecific deposit may complicate reading (HPA: general cytoplasmic expression; UniProt Q9BUX1). | Compare the chromogen color with the nuclear counterstain and controls. Score CHAC1 only where a distinct cell-associated pattern is credible (general IHC practice). |
| Unlisted cells stain more strongly than the expected population. | Cross-reactivity or endogenous detection activity is possible, while an unlisted cell is not automatically CHAC1-negative (general IHC practice; HPA: listed High populations). | Check a detection-reagent control and examine a second HPA High cell population. Describe the unexpected distribution separately rather than calling it validated CHAC1 staining (general IHC practice; HPA: tissue IHC profile). |
| Skeletal muscle looks weak despite tissue-enhanced RNA. | The observations concern different measurements: HPA reports Low staining in myocytes and tissue-enhanced skeletal-muscle RNA (HPA: tissue IHC and RNA specificity). | Do not use skeletal muscle as the sole positive IHC control. Compare the run with an HPA High cell population and document the RNA–staining discrepancy (HPA: tissue IHC profile and reliability description). |
| An IF image looks mitochondrial, but chromogenic IHC looks broadly cytoplasmic. | The assays have different reported patterns and spatial resolution; HPA approves mitochondrial ICC-IF localization and describes general cytoplasmic tissue IHC (HPA: subcellular and tissue profiles). | Use the tissue IHC profile to score paraffin sections. Keep the ICC-IF observation assay-specific and avoid claiming mitochondrial IHC localization from diffuse chromogen (HPA: subcellular and tissue profiles; general IHC interpretation). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | High | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: CHAC1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Use the catalog antibody’s paraffin-section result as a starting point, then validate cell type, compartment and background in each IHC experiment.
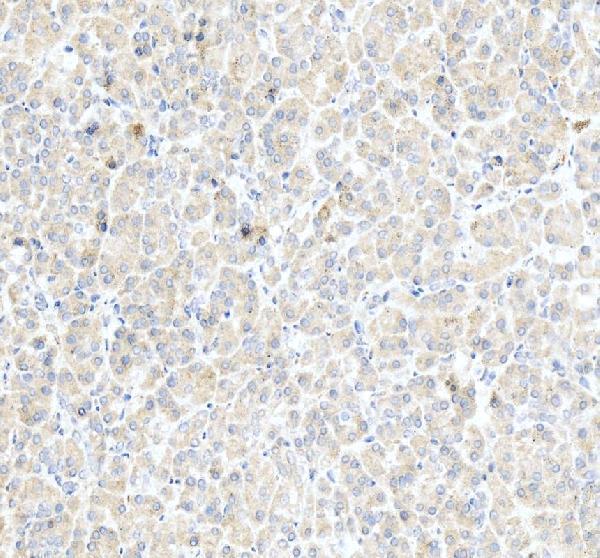
A09017-2 has real IHC data from a paraffin-embedded human pancreas section (IHC image caption); its listed reactivity is Human, Mouse and Rat (catalog). No IF data are supplied (catalog).
A09017-2 will render with an IHC figure from a paraffin-embedded human pancreas section (IHC image caption). Its listed applications are ELISA, IHC and WB, and its listed reactivity is Human, Mouse and Rat; no IF validation is supplied (catalog).
Which to pick: For tissue IHC, choose A09017-2: it is a polyclonal antibody listed for IHC (catalog), with a paraffin-section image using EDTA retrieval at pH 8.0 (IHC image caption); the fixative is unreported (IHC image caption). For IF/ICC, A09017-2 has no listed application or image data, so its suitability is unverified (catalog). For cross-species IHC, A09017-2 lists Mouse and Rat reactivity, but its supplied IHC figure shows only human pancreas (catalog; IHC image caption).