CMTM8 / CKLF-like MARVEL transmembrane domain-containing protein 8 · IHC design guide

Design Immunohistochemistry for CMTM8

Plan CMTM8 IHC in paraffin sections using hepatocytes and pancreatic exocrine cells as expected cytoplasmic staining references (HPA tissue IHC). The catalog antibody’s IHC dilution range is 1:100–1:300 (datasheet).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for CMTM8 (IHC for CMTM8): expected localisation Cytoplasmic tissue staining; membrane also annotated (HPA tissue IHC; UniProt), antibody A11789, validated IHC image, and IHC protocol steps
Printable CMTM8 IHC protocol sheet — expected localisation Cytoplasmic tissue staining; membrane also annotated (HPA tissue IHC; UniProt), antibody A11789, controls and protocol steps. Open the full CMTM8 IHC guide →

CMTM8 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining; membrane also annotated (HPA tissue IHC; UniProt)
Staining pattern Cytoplasmic in hepatocytes and pancreatic exocrine cells (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Epididymis+4 more · see all
Negative control ⓘ Appendix+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Pancreas-enhanced RNA (HPA tissue RNA)
Isoform / epitope 2 isoforms; check extracellular vs cytoplasmic epitope (UniProt)
Section 1

Recommended CMTM8 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet) is accompanied by 4 published CMTM8 tissue IHC protocols (PMC9468640; PMC4722886; PMC9013447; PMC7859753).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded Human Tonsils tissue; fixative not specified (datasheet A11789)
FixationImage fixative and duration unreported (datasheet A11789); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-CMTM8, 1:100-1:300 (datasheet A11789)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultCMTM8-positive staining in glandular cells of epididymis (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in several tissues, including liver and pancreas. No signal in the no-primary control.
💡Decision noteStart with Tris-EDTA pH 9.0 HIER at 95–98 °C for 20 min (page retrieval); evaluate the published retrieval methods when optimizing staining.
Section 2

What Is the Expected CMTM8 Staining Pattern?

CMTM8 is annotated in membranes, cytoplasm and nucleus, with four transmembrane segments (UniProt Q8IZV2 topology). In tissue IHC, expect mainly cytoplasmic staining in hepatocytes and pancreatic exocrine glandular cells, with medium staining also reported in several other cell types (HPA tissue IHC). HPA rates its tissue IHC reliability Approved, with medium consistency between staining and RNA data and external verification pending (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining in hepatocytes or pancreatic exocrine glandular cells.This fits the reported tissue pattern; both cell types show medium staining (HPA tissue IHC). Judge signal in the named cells rather than treating every cell in a positive tissue as positive (standard IHC practice).
Predominantly nuclear staining in tissue IHC, with little cytoplasmic signal.Check for an assay artefact before calling this the expected tissue pattern: HPA describes tissue staining as cytoplasmic, although it reports nucleoplasmic localization in ICC-IF and UniProt also annotates nucleus (HPA tissue IHC; HPA subcellular ICC-IF; UniProt Q8IZV2).
Strong staining in appendix glandular cells or lymph-node germinal center cells.These cell types are reported as not detected (HPA tissue IHC). Check for antibody cross-reactivity or endogenous detection activity with appropriate negative controls (standard IHC practice); the observation alone does not establish either cause.
Diffuse color across cells, stroma or the whole section, without a defined cellular pattern.Treat this as background until controls support a specific signal (standard IHC practice). It does not reproduce the reported cytoplasmic staining in selected tissue cell types (HPA tissue IHC).
No signal in hepatocytes or pancreatic exocrine glandular cells.Both are reported at medium intensity (HPA tissue IHC), so review the assay and a known-positive control (standard IHC practice). A blank section alone cannot establish that the sample lacks CMTM8.
💡Expected CMTM8 appearanceA convincing tissue IHC positive is defined cytoplasmic staining of medium intensity in hepatocytes or pancreatic exocrine glandular cells (HPA tissue IHC); uniform haze or strong staining in HPA not-detected cell types warrants a control check (HPA tissue IHC; standard IHC practice).
How each factor affects the staining
Membrane topology and compartmentCMTM8 has 4 transmembrane segments, yet HPA describes tissue IHC as cytoplasmic (UniProt Q8IZV2 topology; HPA tissue IHC). Do not require a sharp cell-border outline to score the reported tissue pattern.
Isoforms and processingUniProt lists 2 isoforms, one chain spanning residues 1–173, and no annotated signal peptide, propeptide or glycosylation sites (UniProt Q8IZV2). Epitope coverage and isoform-specific staining cannot be inferred without antibody epitope data.
Strength of tissue evidenceThe tissue IHC profile is Approved but has medium consistency with RNA data and awaits external verification (HPA tissue IHC). HPA055077 is IHC Approved; the supplied record does not mark it IHC Enhanced (HPA antibodies).
IF/ICC Q: Should its pattern match tissue IHC?A: HPA reports approved nucleoplasmic localization in ICC-IF images from HEK293 and Hep-G2, while tissue IHC is described as cytoplasmic (HPA subcellular ICC-IF; HPA tissue IHC). Interpret each assay against its own evidence; this section supplies no IF protocol.
Detection chemistryEndogenous enzyme activity and nonspecific detection can produce chromogenic staining independent of primary-antibody binding (standard IHC practice). Use detection-system controls when an unexpected cell type or diffuse color appears.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive-control liver or pancreas is blank.The expected medium signal may have been lost during the IHC workflow (HPA tissue IHC; standard IHC practice).Check antibody application, retrieval and detection against the validated IHC-P instructions; confirm a working positive control before interpreting study sections (standard IHC practice).
Signal is nuclear only in tissue sections.This differs from HPA's cytoplasmic tissue profile, though nucleoplasm is reported in ICC-IF (HPA tissue IHC; HPA subcellular ICC-IF).Inspect cell boundaries and counterstain, then compare primary-antibody and detection controls (standard IHC practice). Record the assay-specific discrepancy rather than assigning one universal compartment.
Appendix glandular cells stain strongly.HPA reports this cell type as not detected; cross-reactivity or detection background is possible (HPA tissue IHC; standard IHC practice).Compare a no-primary control and a positive tissue on the same run; assess whether color tracks the expected cells (standard IHC practice; HPA tissue IHC).
Color spreads uniformly through the section.Nonspecific binding or detection background may obscure a cellular pattern (standard IHC practice).Review blocking, washes and detection controls; score only resolved cellular staining after background is controlled (standard IHC practice).
Some cells in an otherwise positive tissue are unstained.HPA assigns staining to named cell types, such as hepatocytes in liver and exocrine glandular cells in pancreas (HPA tissue IHC).Identify the relevant cells by morphology and counterstain before scoring; do not assign a whole-tissue intensity to every cell (standard IHC practice; HPA tissue IHC).
A low-staining tissue appears weak.HPA reports low staining in several specified cell types, including cerebral-cortex endothelial cells and stomach glandular cells (HPA tissue IHC).Compare it with liver hepatocytes or pancreatic exocrine glandular cells reported at medium intensity, using the same run and controls (HPA tissue IHC; standard IHC practice).

Sample controls for CMTM8 IHC & IF

🧪Run liver first: hepatocytes should stain at the HPA-reported Medium level (HPA: liver hepatocytes, Medium). Use appendix glandular cells as the negative tissue (HPA: appendix glandular cells, Not detected); compare staining in other cells on the liver slide with background, but do not assume those cells are CMTM8-negative from the hepatocyte entry alone (HPA: liver hepatocytes, Medium).
Positive control tissue: Epididymis (Glandular cells, HPA Medium)
Negative control tissue: Appendix (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show CMTM8 in HEK293, Hep-G2, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and isotype controls matched to the primary antibody’s host species and class, plus CMTM8-knockout tissue if available as a biological negative (standard IHC practice). In liver, quench endogenous peroxidase for chromogenic detection and assess pigment-related background; block endogenous biotin if using avidin–biotin detection (standard IHC practice).
⚠️Feasibility: The selected A11789 caption documents paraffin-section IHC at 1:200, but reports no fixative; a target-specific fixation window or fixation effect is unreported (selected A11789 tissue-IHC caption). Antigen-retrieval requirements and whether frozen sections or IF are easier are unreported in the supplied evidence; optimize retrieval empirically (selected A11789 tissue-IHC caption; standard IHC practice). Liver pigment and endogenous peroxidase can complicate chromogenic scoring, so judge hepatocyte staining against the controls (standard IHC practice; HPA: liver hepatocytes, Medium).

HPA tissue IHC evidence for CMTM8

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Epididymis Glandular cells Medium Protein (IHC) HPA →
Liver Hepatocytes Medium Protein (IHC) HPA →
Lung Macrophages Medium Protein (IHC) HPA →
Pancreas Exocrine glandular cells Medium Protein (IHC) HPA →
Placenta Decidual cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Duodenum Glandular cells Not detected Protein (IHC) HPA →
Endometrium Cells in endometrial stroma Not detected Protein (IHC) HPA →
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced CMTM8 IHC Tips

Troubleshoot CMTM8 staining in paraffin sections by checking retrieval, compartment, cell type and controls before changing the chromogenic workflow.

How should I retrieve CMTM8 in paraffin sections when staining is weak?
Use Tris-EDTA pH 9.0 HIER at 95–98 °C for 20 min for CMTM8 IHC (page retrieval setting: nuclear antigen). Cool sections in retrieval buffer, then compare a stained control with a no-primary control processed in the same run (standard IHC practice). Assess signal in hepatocytes or pancreatic exocrine glandular cells, where medium staining is reported, before increasing antibody concentration (HPA: liver and pancreas). If staining remains weak, test a shorter or longer heating interval on adjacent sections while holding detection conditions constant (standard IHC practice). Record both signal and tissue integrity, because damaged morphology makes compartment scoring unreliable (standard IHC practice).
Could fixation explain variable CMTM8 staining between paraffin blocks?
CMTM8-specific fixation sensitivity is unknown; the selected A11789 image reports paraffin-embedded human tonsils at 1:200 but does not identify a fixative (selected A11789 tissue-IHC caption). For a controlled pilot, process matched specimens with the same 10% neutral buffered formalin workflow and record fixation duration and block age (standard IHC practice). Compare adjacent sections using the same pH 9.0 retrieval and detection conditions (page retrieval setting; standard IHC practice). If staining differs, inspect morphology and internal controls before attributing the difference to CMTM8 biology (standard IHC practice). Do not infer a CMTM8-specific fixation effect from tissue staining or protein topology alone (HPA: tissue IHC; UniProt Q8IZV2: topology).
Should CMTM8 staining be membranous, cytoplasmic or nuclear?
Score compartments separately: CMTM8 is annotated at membrane, cytoplasm and nucleus, with 4 transmembrane segments (UniProt Q8IZV2: subcellular location and topology). Tissue IHC reports cytoplasmic staining in several tissues, including liver and pancreas, whereas cell-based IF reports an approved nucleoplasmic location (HPA: tissue IHC and subcellular). These observations justify documenting membrane, cytoplasmic and nuclear signal independently rather than forcing one pattern across preparations (standard IHC practice). Compare the same cell type and section conditions before treating a compartment change as biological (standard IHC practice). If only diffuse nuclear staining appears in damaged areas, check morphology and no-primary controls before accepting it (standard IHC practice).
How can epitope placement change CMTM8 staining?
CMTM8 has 2 annotated isoforms and a MARVEL domain spanning residues 36–168 (UniProt Q8IZV2: isoforms and domain). Its 4 transmembrane segments span residues 40–60, 70–90, 105–125 and 147–167 (UniProt Q8IZV2: topology). Check the catalog antibody's stated immunogen and isoform coverage before interpreting a negative section, because the payload does not specify its epitope (standard IHC practice; supplied antibody evidence). Keep retrieval and dilution constant while comparing control tissues, then document which compartment changes (standard IHC practice). Do not assign extracellular versus cytoplasmic epitope exposure from these segment coordinates alone; membrane orientation is not supplied (UniProt Q8IZV2: topology).
How can IF help investigate an ambiguous CMTM8 IHC pattern?
Use IF as a separate localisation check: cell-based images exist for HEK293 and Hep-G2, with nucleoplasm approved as the main location (HPA: subcellular). In liver, multiplex CMTM8 with a hepatocyte marker to identify the cell population reported to show medium tissue-IHC staining (HPA: liver hepatocytes; standard IF practice). Choose a red or far-red fluorophore after checking unstained tissue autofluorescence, and include single-label controls for channel bleed-through (standard IF practice). Because the antibody epitope and its membrane-facing side are unspecified, compare staining with and without gentle permeabilisation before interpreting intracellular signal (supplied antibody evidence; standard IF practice). Keep the IF result distinct from chromogenic section scoring (standard IHC/IF practice).
What should I check when CMTM8 chromogenic staining looks diffuse?
Start with a no-primary section and a matched tissue control, then inspect whether colour follows cells or extends across folds and section edges (standard IHC practice). Block endogenous peroxidase before DAB development and keep counterstaining consistent across sections (standard chromogenic IHC practice). The selected A11789 tonsil image used 1:200 in paraffin sections; treat that as an image condition, then titrate around it if background persists (selected A11789 tissue-IHC caption; standard IHC practice). Compare liver hepatocytes or pancreatic exocrine glandular cells with a cell population reported as undetected, such as appendix glandular cells (HPA: tissue IHC). Check retrieval damage before increasing primary antibody concentration (standard IHC practice).
How should I quantify CMTM8 across stained paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the tissue compartment and cell population before scoring; HPA reports medium staining in liver hepatocytes and pancreatic exocrine glandular cells (HPA: tissue IHC). Record the percentage of positive target cells from 0–100% and intensity by a consistent 0–3 scale, then calculate an H-score from 0–300 (standard IHC scoring practice). If counting discrete positive cells, report density per mm² of viable, annotated tissue (standard IHC quantification practice). Normalise each sample to the number or area of eligible target cells, and score nuclear and cytoplasmic signal separately (standard IHC practice; HPA: tissue and subcellular). Apply identical thresholds and imaging settings across the comparison (standard IHC practice).
How do I distinguish credible CMTM8 positivity from artefact?
A credible result should be reproducible in the same cell population and supported by appropriate positive and no-primary controls (standard IHC practice). Medium staining in liver hepatocytes and pancreatic exocrine glandular cells provides tissue-level comparators, while appendix glandular cells are reported as undetected (HPA: tissue IHC). Cytoplasmic tissue staining is reported, although membrane and nuclear locations are also annotated and cell-based IF supports nucleoplasm (HPA: tissue IHC and subcellular; UniProt Q8IZV2: location). Treat isolated edge staining, necrotic debris and signal remaining in the no-primary control as suspect (standard IHC practice). If DAB colour appears broadly, reassess endogenous peroxidase blocking before assigning a CMTM8-positive score (standard chromogenic IHC practice).
Boster reagents

Best CMTM8 / CKLF-like MARVEL transmembrane domain-containing protein 8 IHC Antibodies

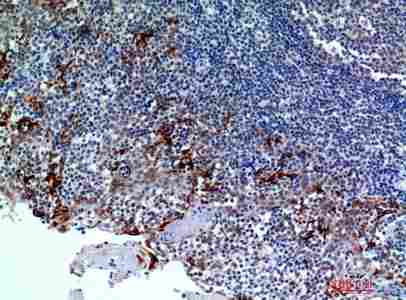
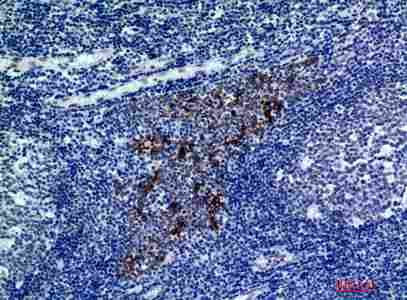
A11789 lists IHC and IF as tested applications (catalog: applications). Its IHC image shows paraffin-embedded human tonsils (IHC image caption), and its listed reactivity covers human and mouse (catalog: reactivity).

Real IHC data Immunohistochemistry (IHC) analysis of paraffin-embedded Human Tonsils, antibody was diluted at 1:200.
Anti-CMTM8/Cklfsf8 Antibody
Cat # A11789

The rendered SKU, A11789, has an IHC image of paraffin-embedded human tonsils stained at 1:200 (IHC image caption). It lists IF as an application (catalog: applications), but supplies no IF image (catalog: if_image_alts).

Which to pick: For tissue IHC, choose A11789: its human tonsil image uses 1:200 on paraffin sections (IHC image caption), within the listed 1:100–1:300 range (catalog: ihc_dilution); the fixative is unreported (IHC image caption). For IF/ICC, A11789 lists IF at 1:50 (catalog: applications; if_dilution), while ICC-specific validation is unreported (catalog: applications). For human or mouse samples, A11789 is a rabbit polyclonal antibody with both species listed as reactive (catalog: host; dilution_raw; reactivity), though its IHC image documents human tissue only (IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q8IZV2 (CKLF8_HUMAN, CKLF-like MARVEL transmembrane domain-containing protein 8).
  2. Human Protein Atlas. CMTM8 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. CMTM8 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. CMTM8 antibody validation summary (2 antibodies).
  5. Identification of prognostic biomarkers in the CMTM family genes of human ovarian cancer through bioinformatics analysis and experimental verification. Frontiers in genetics 2022 — PMC9468640.
  6. CMTM8 inhibits the carcinogenesis and progression of bladder cancer. Oncology reports 2015 — PMC4722886.
  7. Identification and validation of EMT-immune-related prognostic biomarkers CDKN2A, CMTM8 and ILK in colon cancer. BMC gastroenterology 2022 — PMC9013447.
  8. CMTM8 as an LPA1-associated partner mediates lysophosphatidic acid-induced pancreatic cancer metastasis. Annals of translational medicine 2021 — PMC7859753.
  9. PubMed PMID:12782130 — UniProt-cited evidence.
  10. PubMed PMID:17681841 — UniProt-cited evidence.
  11. PubMed PMID:16641997 — UniProt-cited evidence.