FAM50A / Protein FAM50A · IHC design guide

Design Immunohistochemistry for FAM50A

Plan paraffin-section FAM50A IHC around ubiquitous nuclear staining (HPA tissue IHC). Start with the IHC-validated antibody M12622 at 1:50–1:200 (datasheet M12622), and score nuclear DAB staining against controls (standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
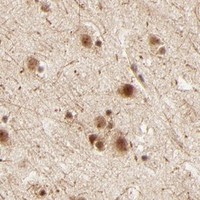
Immunohistochemistry protocol sheet for FAM50A (IHC for FAM50A): expected localisation Ubiquitous nuclear staining (HPA tissue IHC), antibody M12622, validated IHC image, and IHC protocol steps
Printable FAM50A IHC protocol sheet — expected localisation Ubiquitous nuclear staining (HPA tissue IHC), antibody M12622, controls and protocol steps. Open the full FAM50A IHC guide →

FAM50A Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Ubiquitous nuclear staining (HPA tissue IHC)
Staining pattern Widespread nuclear staining across tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M12622)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 44 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat Ubiquitous staining makes negative tissue controls scarce (HPA tissue IHC)
Regulation Expression regulation is not established (UniProt)
Isoform / epitope No isoforms annotated; no membrane-sided epitope split (UniProt)
Section 1

Recommended FAM50A IHC & IF Protocols

The catalog antibody protocol (datasheet: M12622) is followed by published IHC methods for hepatocellular carcinoma tissue microarrays (PMC12432667) and colorectal cancer tissue (PMC11856281).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colorectal adenocarcinoma tissue; fixative not specified (datasheet M12622)
FixationImage fixative and duration unreported (datasheet M12622); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M12622); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M12622)
Primary antibodyRabbit monoclonal (clone 30F36) anti-FAM50A, 1:50-1:200 (datasheet M12622)
Primary incubationOvernight at 4 °C (datasheet M12622)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M12622)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultFAM50A-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet: M12622); neither cited article specifies retrieval conditions (PMC12432667; PMC11856281).
Section 2

What Is the Expected FAM50A Staining Pattern?

FAM50A should appear in nuclei across many cell types in paraffin-section IHC: HPA reports ubiquitous nuclear expression, with high staining in several sampled tissues (HPA tissue IHC: Supported). A nucleoplasmic pattern is also seen by ICC-IF (HPA subcellular: supported). UniProt places FAM50A in the nucleus and annotates no transmembrane segment (UniProt Q14320).

What am I looking at on my slide?
Brown chromogen is concentrated over nuclei in cerebral-cortex neurons or bone-marrow hematopoietic cells.This matches two reported high-staining cell populations and the broader nuclear profile (HPA tissue IHC: High; Supported). Judge localisation in intact cells, then compare intensity with the control section; HPA's High category is not an intensity threshold for every preparation.
Signal is predominantly cytoplasmic, membranous or extracellular while nuclei remain clear.That conflicts with nuclear localisation (UniProt Q14320; HPA tissue IHC: ubiquitous nuclear expression). Check morphology, detection background and antibody specificity before calling it FAM50A. The absence of a transmembrane segment does not, by itself, identify the source of the stain (UniProt Q14320 topology).
A sharply restricted cell population stains, but adjacent intact nuclei in the same section do not.Check whether that population matches the tissue-specific HPA observations before interpreting it (HPA tissue IHC). An unexpected restriction can reflect cross-reactivity or endogenous detection activity (general IHC practice); HPA provides no negative-cell list, so an unlisted cell type is not an established negative.
Brown haze covers tissue and spaces between cells, obscuring nuclear borders.This is not an interpretable nuclear pattern (HPA tissue IHC: ubiquitous nuclear expression). Diffuse deposit can arise from nonspecific binding, insufficient washing or detection background (general IHC practice). Evaluate the no-primary control and whether identifiable nuclei remain selectively stained.
No nuclear signal appears in a section containing cerebral-cortex neurons or bone-marrow hematopoietic cells.Those cells were reported High by HPA, so their absence of staining weakens a negative call (HPA tissue IHC: High). Check tissue preservation, control performance, retrieval and detection as general IHC practice. HPA's Supported rating does not guarantee signal in every paraffin preparation.
💡Expected FAM50A appearanceCall a result positive when intact nuclei show distinct chromogenic staining in an HPA-reported cell population, such as cerebral-cortex neurons or bone-marrow hematopoietic cells (HPA tissue IHC: High); cytoplasmic-only stain or diffuse brown haze warrants background review rather than a positive call (HPA tissue IHC: ubiquitous nuclear expression).
How each factor affects the staining
Expected compartmentNuclear staining is the primary readout (UniProt Q14320; HPA tissue IHC: ubiquitous nuclear expression). ICC-IF resolves the location more specifically to the nucleoplasm (HPA subcellular: supported); that observation supports interpretation but does not set a paraffin-IHC intensity cutoff.
Tissue and cell selectionHPA reports High staining in adipocytes, appendix glandular cells, bone-marrow hematopoietic cells, bronchial respiratory epithelium, cerebral-cortex neurons and colon endothelium (HPA tissue IHC). Its negative and low lists are empty; neither an unlisted tissue nor an unlisted cell type is a validated negative.
Strength of evidenceThe HPA tissue-IHC profile is Supported, with medium consistency between antibody staining and RNA expression (HPA tissue IHC). Antibody HPA003585 is IHC Supported and ICC Enhanced (HPA antibodies). These ratings support the observed pattern; they do not establish target-specific fixation sensitivity.
Topology and processingFAM50A has no annotated transmembrane segment, signal peptide or propeptide, and its listed protein chain spans residues 2–339 (UniProt Q14320). These annotations fit a nuclear readout but do not establish an epitope location, antigen-retrieval condition or tissue-specific fixation effect.
IF/ICC Q: What pattern should I expect?A nucleoplasmic signal is expected: HPA calls nucleoplasm the supported main location and lists ICC-IF images, including A-431, U-251MG and U2OS (HPA subcellular). This guides localisation only; IF/ICC preparation and protocol selection belong to the separate IF/ICC guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Control tissue has weak or absent nuclear stain.Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.Confirm that the selected cell population is present, then review the catalog antibody's IHC-P directions, retrieval, dilution and detection controls (general IHC practice). Do not infer a FAM50A-specific fixation effect.
Brown signal surrounds nuclei but nuclear interiors stay pale.The compartment disagrees with the nuclear IHC profile and supported nucleoplasmic ICC-IF location (HPA tissue IHC; HPA subcellular).Recheck focus and counterstain, then compare with a no-primary control and an HPA-reported positive population (general IHC practice; HPA tissue IHC). Treat persistent cytoplasmic-only signal as unconfirmed.
Only a few unexpected cells stain strongly.Restricted staining may reflect cross-reactivity or endogenous detection activity (general IHC practice). HPA's empty negative list cannot classify those cells as true negatives (HPA tissue IHC).Identify the cells morphologically, compare their localisation with the nuclear profile, and inspect a no-primary control (general IHC practice; HPA tissue IHC). Avoid a specificity claim based on staining intensity alone.
The whole section has granular or diffuse brown background.Nonspecific binding, residual detection reagents or endogenous enzyme activity can obscure nuclear signal (general IHC practice).Compare no-primary and detection controls; review blocking, washing and detection steps in the selected IHC-P workflow (general IHC practice). Score only nuclei whose borders remain interpretable.
Different tissues show unequal nuclear intensity.HPA reports ubiquitous nuclear expression and low tissue specificity, while its listed cell populations have High staining (HPA tissue IHC). Equal intensity across tissues is not established.Score each tissue against its own morphology and controls (general IHC practice). Record compartment and cell type alongside intensity; do not convert an unlisted tissue into a negative control.
An IF image appears nucleoplasmic, but paraffin IHC is unclear.ICC-IF and paraffin-section chromogenic IHC are different preparations; HPA gives separate subcellular and tissue-IHC assessments (HPA subcellular; HPA tissue IHC).Use the IF result as localisation context, then resolve the paraffin result with IHC controls and the catalog antibody's IHC-P guidance (general IHC practice). Do not transfer an IF/ICC protocol into this IHC decision.

Sample controls for FAM50A IHC & IF

🧪Start with bronchus: respiratory epithelial cells should show nuclear staining (HPA: High in respiratory epithelial cells; UniProt Q14320: Nucleus). HPA detects FAM50A in all 44 scored tissues, so there is no supported negative tissue or validated internal negative cell population; use no-primary and isotype controls to judge background, and do not assume unstained cells on the positive slide are true biological negatives (HPA: no negative rows; HPA: detected in all 44 scored tissues).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: FAM50A is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show FAM50A in A-431, U-251MG, U2OS, KOLF2.1J, U2OS, siRNA 1 (10x), U2OS, siRNA 2 (10x), U2OS, scrambled (10x), with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Run a secondary-only section and a nonimmune isotype control matched to the primary antibody’s host species and antibody format; a FAM50A knockout specimen, if available, provides a biological negative (standard IHC practice). Block endogenous peroxidase before HRP–DAB detection and assess any pigment or other tissue background against the control sections (standard chromogenic IHC practice; selected M12622 caption: HRP–DAB detection).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected M12622 paraffin-section caption does not state a fixative (selected M12622 caption: fixative unreported). Heat-mediated retrieval with EDTA at pH 8.0 was used in that IHC example, but a requirement for retrieval across preparations is unreported (selected M12622 caption: EDTA pH 8.0). Frozen-section performance is unreported; ICC-IF images support nucleoplasmic localization, but do not establish that IF or frozen sections are easier than paraffin IHC (HPA: nucleoplasm supported; HPA: ICC-IF images).

HPA tissue IHC evidence for FAM50A

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: FAM50A is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced FAM50A IHC Tips

Troubleshoot FAM50A staining in paraffin sections by checking retrieval, nuclear localisation, controls and scoring before interpreting chromogenic signal.

How should I retrieve FAM50A in paraffin sections when nuclear staining is weak?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet M12622). That condition accompanies FAM50A staining in a paraffin-embedded human colorectal adenocarcinoma section using the catalog antibody at 1:50 overnight at 4°C (caption M12622). If nuclei remain weak, first confirm that the retrieval bath reached its intended temperature and that sections stayed covered; then compare a cautious change in heating time on matched sections (standard IHC practice). Score nuclear signal alongside tissue damage and background, since stronger heating can compromise morphology (standard IHC practice). Keep the antibody dilution and detection conditions constant during that comparison (standard IHC practice).
Could fixation explain inconsistent FAM50A staining between paraffin blocks?
Target-specific FAM50A sensitivity to fixation is unknown from the supplied evidence; the catalog tissue caption does not state its fixative (caption M12622). Record each block's fixative, fixation duration and processing history before comparing nuclear staining across specimens (standard IHC practice). Run blocks with different histories together using EDTA retrieval at pH 8.0, the stated catalog condition, and hold antibody dilution and detection constant (datasheet M12622; standard IHC practice). If one block stains poorly, compare preserved morphology and a separate nuclear control stain before attributing the result to FAM50A abundance (standard IHC practice). Neither widespread tissue staining nor protein topology establishes a fixation effect (HPA tissue IHC; UniProt Q14320 topology).
What staining compartment should count as FAM50A positive in IHC?
Prioritise staining within intact nuclei: FAM50A is annotated as nuclear, and independent subcellular data place it in the nucleoplasm (UniProt Q14320; HPA subcellular). The protein has no annotated transmembrane segment, so a crisp membrane rim alone does not match its reported localisation (UniProt Q14320 topology; HPA subcellular). Check the nuclear signal against a counterstain and assess cells away from section folds, cut edges and damaged areas (standard IHC practice). The tissue profile describes ubiquitous nuclear expression, with high staining reported in several cell populations, so identify the cell type before comparing fields (HPA tissue IHC). Treat predominantly diffuse cytoplasmic or extracellular chromogen as a specificity question that needs controls (HPA subcellular; standard IHC practice).
How should unknown epitope placement affect FAM50A IHC troubleshooting?
The record lists 0 annotated isoforms and gives no antibody epitope, so it cannot establish which sequence the catalog antibody recognises in processed tissue (UniProt Q14320 record; caption M12622). FAM50A has no annotated transmembrane segment or glycosylation sites, while an N-terminal acetylalanine is noted at residue 2 (UniProt Q14320 topology and modified residues). Those annotations do not show whether fixation or retrieval masks this antibody's epitope (UniProt Q14320 record; standard IHC practice). If staining is discordant, compare matched sections across retrieval conditions while holding the antibody at the documented 1:50 starting dilution (caption M12622; standard IHC practice). Use an independent epitope or orthogonal evidence where available before assigning the discordance to an isoform (standard IHC practice).
How can IF help assess a questionable nuclear FAM50A IHC pattern?
Use IF/ICC as a separate localisation check: subcellular images support nucleoplasmic FAM50A, while the supplied catalog tissue example documents chromogenic IHC in a paraffin section (HPA subcellular; caption M12622). Multiplex FAM50A with a marker for the cell population being assessed, and include a nuclear counterstain to identify the compartment in each cell (standard IF practice). Choose spectrally separated fluorophores after checking tissue autofluorescence with an unstained control, favouring a cleaner channel for the weaker signal (standard IF practice). Because the reported location is inside the nucleus and no membrane span is annotated, permeabilise sufficiently to allow nuclear antibody access (HPA subcellular; UniProt Q14320 topology; standard IF practice). Optimise IF fixation and permeabilisation independently of the IHC caption, which reports no fixative (caption M12622; standard IF practice).
How do I distinguish FAM50A staining from chromogenic background?
Compare intact nuclei with adjacent cytoplasm and extracellular spaces, because the expected FAM50A pattern is nuclear or nucleoplasmic (UniProt Q14320; HPA subcellular). The catalog tissue example used 10% goat serum blocking, a 1:50 primary overnight at 4°C, and peroxidase-linked detection with DAB (caption M12622). Include a no-primary section to assess detection-system background, and apply a peroxidase block when using HRP and DAB (standard IHC practice). If background is widespread, titrate primary antibody and shorten chromogen development on adjacent sections while preserving a consistent retrieval condition (standard IHC practice). Inspect pigmented material, folds and tissue edges before counting brown deposits as positive cells (standard IHC practice).
How should I score FAM50A across heterogeneous paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define positivity as nuclear staining in morphologically intact cells, consistent with the reported nuclear and nucleoplasmic localisation (UniProt Q14320; HPA subcellular). For each named cell population, record the percentage of positive nuclei and intensity, or calculate an H-score using percentages at 0–3 intensity grades (standard IHC practice). Normalise positive counts to the total evaluable nuclei of that same population; for spatial comparisons, report positive nuclei per mm² of viable tissue (standard IHC practice). Keep retrieval, antibody dilution, DAB development, imaging and threshold settings consistent across the comparison (standard IHC practice). Exclude necrotic regions, folds and cut edges, and document the exclusion rule before scoring (standard IHC practice).
When is a FAM50A-positive IHC result convincing?
A convincing result shows reproducible nuclear staining in intact cells, matching the reported nuclear and nucleoplasmic localisation (UniProt Q14320; HPA subcellular). Identify the stained cell population before interpreting differences: the tissue profile reports ubiquitous nuclear expression and high staining in selected populations, with supported reliability and medium agreement with RNA data (HPA tissue IHC). Treat a membrane-only pattern, extracellular deposits or staining concentrated at section edges and necrotic areas as suspect until checked on adjacent sections (UniProt Q14320 topology; standard IHC practice). With HRP and DAB detection, compare a no-primary control and assess endogenous peroxidase contribution before calling brown deposits FAM50A positive (caption M12622; standard IHC practice). Interpret intensity differences only between sections processed and scored comparably (standard IHC practice).
Boster reagents

Best FAM50A / Protein FAM50A IHC Antibodies

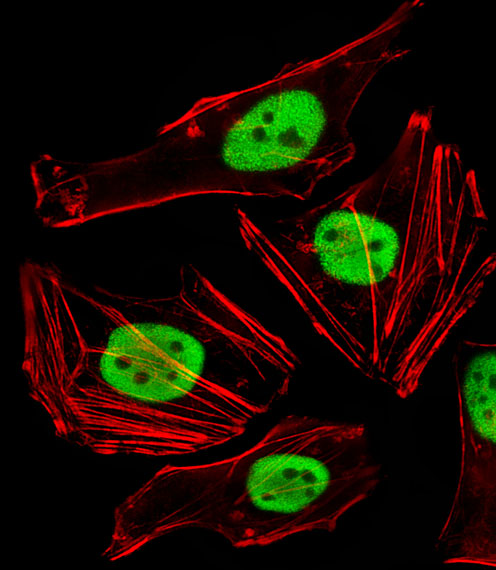
Two anti-FAM50A antibodies have illustrated results: paraffin-section IHC in human tissues (M12622 image captions) and IF in HeLa cells (A12622 image caption).

Real IHC data IHC analysis of FAM50A using anti-FAM50A antibody (M12622). FAM50A was detected in a paraffin-embedded section of human colorectal adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-FAM50A Antibody (M12622) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-FAM50A Rabbit Monoclonal Antibody
Cat # M12622
Real IF data Fluorescent image of Hela cells stained with FAM50A Antibody (C-term). A12622 was diluted at 1:25 dilution. An Alexa Fluor 488-conjugated goat anti-rabbit lgG at 1:400 dilution was used as the secondary antibody (green). Cytoplasmic actin was counterstained with Alexa Fluor® 555 conjugated with Phalloidin (red).
Anti-FAM50A Antibody (C-term)
Cat # A12622

M12622 will render with IHC staining of paraffin-embedded human colorectal adenocarcinoma; its other captions show human spleen and thyroid cancer sections (M12622 image captions). A12622 will render with IF staining of HeLa cells (A12622 image caption).

Which to pick: Choose M12622 for tissue IHC: it is a rabbit monoclonal listed for IHC, with staining shown in paraffin-embedded sections; the captions do not report the fixative (M12622 catalog entry and image captions). For IF in HeLa cells, A12622 has a matching image; for ICC, M12622 is the listed option (A12622 image caption; M12622 application list). M12622 lists human, mouse and rat reactivity, while A12622 lists human only; the illustrated IHC sections are human (catalog reactivity lists; M12622 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q14320 (FA50A_HUMAN, Protein FAM50A).
  2. Human Protein Atlas. FAM50A tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. FAM50A subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. FAM50A antibody validation summary (1 antibodies).
  5. Exploration of signature-related FAM genes and correlation between FAM50A expression and the pathogenesis and prognosis of hepatocellular carcinoma. Translational cancer research 2025 — PMC12432667.
  6. KSHV Reprograms Host RNA Splicing via FAM50A to Activate STAT3 and Drive Oncogenic Cellular Transformation. bioRxiv : the preprint server for biology 2025 — PMC11957025.
  7. KSHV reprograms host RNA splicing via FAM50A to activate STAT3 and drive oncogenic cellular transformation. mBio 2025 — PMC12239556.
  8. FAM50A as a novel prognostic marker modulates the proliferation of colorectal cancer cells via CylinA2/CDK2 pathway. PloS one 2025 — PMC11856281.
  9. PubMed PMID:9339379 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15772651 — UniProt-cited evidence.