FBXL16 / F-box/LRR-repeat protein 16 · IHC design guide

Design Immunohistochemistry for FBXL16

Start FBXL16 chromogenic IHC-P with the catalog antibody at 5 μg/mL (datasheet: IHC-P). Use cerebral cortex neurons as a high-staining reference and adipose adipocytes as a not-detected reference (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for FBXL16 (IHC for FBXL16): expected localisation Cytoplasmic and nuclear in CNS tissue (HPA tissue IHC), antibody A15331, validated IHC image, and IHC protocol steps
Printable FBXL16 IHC protocol sheet — expected localisation Cytoplasmic and nuclear in CNS tissue (HPA tissue IHC), antibody A15331, controls and protocol steps. Open the full FBXL16 IHC guide →

FBXL16 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear in CNS tissue (HPA tissue IHC)
Staining pattern CNS neurons show cytoplasmic and nuclear staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Caudate+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Staining regulation is not established (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended FBXL16 IHC & IF Protocols

Use the catalog antibody’s IHC-P protocol alongside the published FBXL16 tissue microarray workflow (PMC10920083).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A15331); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-FBXL16, 5 μg/mL (datasheet A15331)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultFBXL16-positive staining in neuronal cells of caudate (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and nuclear expression in CNS. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval rule); the published workflow also uses citrate retrieval (PMC10920083).
Section 2

What Is the Expected FBXL16 Staining Pattern?

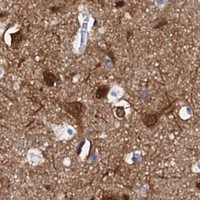
In paraffin-section IHC, expect FBXL16 staining in neuronal cells of the caudate and cerebral cortex, with cytoplasmic and nuclear expression reported in the CNS (HPA tissue IHC: High in both; cytoplasmic and nuclear CNS profile). Collecting ducts in kidney also stain strongly (HPA tissue IHC: High). The tissue profile has Enhanced reliability with medium staining–RNA consistency (HPA tissue IHC). UniProt reports no transmembrane segment and no annotated subcellular location (UniProt Q8N461).

What am I looking at on my slide?
Clear cytoplasmic and nuclear staining in caudate or cerebral-cortex neurons.This matches the reported CNS compartment pattern and High neuronal staining (HPA tissue IHC). Interpret intensity against cells on the same section and a negative control (general IHC practice); intensity alone does not establish specificity.
A dominant cell-surface outline, with little neuronal cytoplasmic or nuclear staining.This diverges from the reported CNS pattern (HPA tissue IHC: cytoplasmic and nuclear). A surface-only interpretation also lacks support from the protein record (UniProt Q8N461: no transmembrane segment). Check whether the outline follows tissue edges or nonspecific chromogen deposition (general IHC practice).
Strong staining in cells reported as undetected, such as adipocytes in adipose tissue.That conflicts with the sampled HPA pattern (HPA tissue IHC: adipocytes Not detected). Consider antibody cross-reactivity or endogenous detection activity; neither cause can be assigned from staining alone. Compare with a no-primary control and the expected positive tissue (general IHC practice).
Diffuse color across tissue, empty spaces, and several cell types.A diffuse field obscures the reported cell-specific contrast (HPA tissue IHC: High in caudate neurons; Not detected in adipose adipocytes). Assess blocking, washes, detection background, and section condition using routine IHC controls (general IHC practice).
No neuronal staining in caudate or cerebral cortex.An absent signal in these reported High tissues makes a negative study result hard to interpret (HPA tissue IHC). Check tissue identity, antibody and detection controls, and whether the chosen retrieval and dilution conditions work in the local assay (general IHC practice).
💡Expected FBXL16 appearanceA convincing positive shows High neuronal staining in caudate or cerebral cortex, with cytoplasmic and nuclear signal (HPA tissue IHC); equally strong, widespread staining in reported undetected cells is suspect (HPA tissue IHC: adipose adipocytes Not detected).
How each factor affects the staining
Tissue and cell choiceCaudate and cerebral-cortex neurons and kidney collecting ducts are reported High; hippocampal neurons and late spermatids are Medium (HPA tissue IHC). Choose the tissue and cell population before judging signal strength.
Subcellular interpretationThe cytoplasmic and nuclear description applies to the CNS profile (HPA tissue IHC). Kidney collecting ducts have a reported intensity, but no compartment assignment in this payload (HPA tissue IHC: kidney High); do not extend the CNS compartment call to kidney.
Evidence and antibody validationThe tissue profile is Enhanced but has medium agreement between staining and RNA (HPA tissue IHC). HPA039504 is IHC Enhanced and HPA056354 is IHC Supported (HPA antibodies); those classifications support review of the observed pattern, not proof of every stained cell.
Isoforms and epitope uncertaintyTwo isoforms are listed (UniProt Q8N461: isoforms 1 and 2). The supplied record gives no antibody epitope or isoform-specific IHC result, so it cannot establish which isoform a stained cell contains or predict a different staining pattern.
IF/ICC Q: Is the IHC compartment pattern confirmed in cultured cells?No main ICC-IF location or cell-line images are supplied (HPA subcellular: location unavailable; image list empty). Use the CNS compartment report as an IHC observation (HPA tissue IHC), without treating it as IF/ICC validation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The expected positive tissue is blank.Caudate and cerebral-cortex neuronal cells are reported High (HPA tissue IHC), so an assay failure is possible; the image alone cannot identify its step.Confirm tissue identity and run working positive and detection controls. Review local retrieval, antibody dilution, and chromogen steps as general IHC checks (general IHC practice); no FBXL16-specific retrieval condition is supplied.
Signal appears only at cell borders in CNS neurons.A border-only pattern differs from reported cytoplasmic and nuclear CNS staining (HPA tissue IHC); UniProt lists no transmembrane segment (UniProt Q8N461).Inspect a counterstained section for cell outlines and compare no-primary and positive-tissue controls before assigning a membrane location (general IHC practice).
Reported undetected adipocytes stain strongly.Adipocytes in adipose tissue are Not detected in the supplied tissue profile (HPA tissue IHC). Cross-reactivity or endogenous detection activity are possibilities, not diagnoses from this image.Compare a no-primary control and a reported positive tissue; review blocking and detection background if the control also develops color (general IHC practice).
The whole section has diffuse chromogen.Broad background can mask the reported contrast between positive neuronal cells and undetected adipocytes (HPA tissue IHC). Its source cannot be identified from the FBXL16 profile.Check washes, blocking, detection controls, and chromogen development against a no-primary section (general IHC practice).
Hippocampus stains less strongly than caudate.That ordering can fit the reference profile: hippocampal neurons are Medium and caudate neurons High (HPA tissue IHC).Score the named neuronal populations on comparable sections before changing assay conditions; verify a high-reference tissue if signal is faint throughout (general IHC practice).
Kidney collecting ducts stain, but their compartment looks different from CNS neurons.Collecting ducts are reported High, while the cytoplasmic and nuclear description is specifically for CNS expression (HPA tissue IHC). The supplied kidney entry gives no compartment call.Record kidney cell type and intensity without assigning its location from the CNS profile; use counterstain and controls to assess whether the observed signal is cellular (general IHC practice).

Sample controls for FBXL16 IHC & IF

🧪Run kidney first: collecting ducts are High for FBXL16 (HPA: kidney, collecting ducts, High). Use adipose tissue as the negative tissue because adipocytes are Not detected (HPA: adipose tissue, adipocytes, Not detected); on the kidney slide, treat cells outside the collecting ducts as internal negatives only where they show background-level staining, rather than assuming every other renal cell type is negative (HPA: kidney row identifies collecting ducts only).
Positive control tissue: Caudate (Neuronal cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for FBXL16; derive a cell-line control from the positive tissue's cell type (Neuronal cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control; a host- and immunoglobulin-class-matched isotype or nonimmune IgG control appropriate to the primary antibody; and, if available, FBXL16 knockout material or a validated antigen-peptide competition control (standard IHC practice). For kidney chromogenic IHC, quench endogenous peroxidase and block endogenous biotin if using avidin–biotin detection (standard IHC practice: renal tissue can contain endogenous biotin).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported in the supplied evidence; the exact A15331 human-spleen tissue-IHC caption gives 5 μg/mL but does not report a fixative (selected-SKU tissue-IHC caption). Retrieval dependency is unreported, so assess antigen retrieval empirically on paraffin sections (supplied evidence; standard IHC practice). Neither frozen sections nor IF/ICC can be judged easier from these data (HPA: no cell lines with ICC-IF images); in kidney IHC, endogenous biotin can produce background with avidin–biotin detection (standard IHC practice).

HPA tissue IHC evidence for FBXL16

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Kidney Collecting ducts High Protein (IHC) HPA →
Hippocampus Neuronal cells Medium Protein (IHC) HPA →
Testis Elongated or late spermatids Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced FBXL16 IHC Tips

Use cell-level controls and matched processing to assess FBXL16 staining in chromogenic IHC; interpret nuclear and cytoplasmic signal against the reported tissue pattern.

How should I adjust antigen retrieval when FBXL16 staining is weak?
Start with citrate buffer at pH 6.0 for HIER at 95–98 °C for 20 min (page retrieval setting). Run a matched positive control, such as neuronal cells in caudate, beside the test section; these cells have high reported staining (HPA: caudate neuronal cells, High). If signal remains weak, compare a longer citrate retrieval or a higher-pH buffer on adjacent sections, while checking tissue morphology and background (standard IHC practice). Keep antibody concentration, detection, and development time constant during that comparison so the retrieval change can be judged independently (standard IHC practice). Do not treat stronger staining alone as proof of FBXL16 specificity (standard IHC practice).
Could fixation account for weak or uneven FBXL16 staining in paraffin sections?
Target-specific FBXL16 sensitivity to fixative type or fixation duration is unknown from the supplied evidence; the selected tissue-IHC caption does not state its fixative (A15331 caption). Record fixative, fixation duration, section thickness, and processing batch before comparing cases, because these variables can alter chromogenic staining (standard IHC practice). If processing is suspect, stain similarly processed positive-control tissue in the same run and compare matched regions away from folds and edges (standard IHC practice). Use the same retrieval and detection settings for that comparison, then change one preparation variable at a time (standard IHC practice). Neither the reported tissue pattern nor protein topology establishes a FBXL16-specific fixation effect (HPA: tissue IHC; UniProt Q8N461).
How should I assess nuclear versus cytoplasmic FBXL16 staining?
Assess nuclear and cytoplasmic signal separately in identifiable cells, because the reported CNS tissue profile includes both compartments (HPA: cytoplasmic and nuclear expression in CNS). FBXL16 has no annotated subcellular location in the supplied protein record and no transmembrane segment, so these features alone cannot establish a required compartment (UniProt Q8N461). Compare candidate staining with high reported neuronal staining in caudate or cerebral cortex and with a no-primary control on adjacent sections (HPA: tissue IHC; standard IHC practice). Score counterstained nuclei and surrounding cytoplasm independently, excluding pigment, folds, and edge deposits from either category (standard IHC practice). Treat a new compartment pattern as provisional until antibody specificity and morphology are checked (standard IHC practice).
Could isoforms or epitope masking explain discordant FBXL16 IHC results?
FBXL16 has 2 listed isoforms, but the supplied evidence does not map the catalog antibody epitope to either one (UniProt Q8N461; A15331 caption). Its F-box domain spans residues 94–139, and an omega-N-methylarginine is listed at residue 92; neither fact establishes antibody sensitivity to modification (UniProt Q8N461). Obtain the antibody's documented immunogen or epitope before claiming isoform coverage, and check whether that sequence is shared by the variants (standard antibody-validation practice). If sections disagree, compare matched retrieval conditions and positive-control staining before attributing the difference to splicing or epitope masking (standard IHC practice). Report the tested antibody and protocol with the result so its scope is clear (standard IHC practice).
How can I adapt FBXL16 staining for tissue immunofluorescence multiplexing?
Pair FBXL16 with a marker that identifies the expected cell population, such as a neuronal marker in caudate, where neuronal staining is reported as high (HPA: caudate neuronal cells, High). Choose spectrally separated fluorophores after inspecting unstained tissue autofluorescence, and include single-label controls to assess bleed-through (standard IF practice). For an intracellular epitope, optimise permeabilisation to allow access to the relevant compartment while preserving the cell marker; FBXL16 has no transmembrane segment, but its antibody epitope is unspecified (UniProt Q8N461; A15331 caption). Score nuclear and cytoplasmic fluorescence separately because both are reported in CNS tissue IHC, then confirm that the signal survives appropriate antibody controls (HPA: CNS profile; standard IF practice).
What should I check when FBXL16 chromogenic staining is diffuse?
Run no-primary and detection-only controls to identify nonspecific detection deposits, and examine unstained sections for pigment before interpreting diffuse colour (standard IHC practice). For peroxidase-based detection, check the peroxidase block and shorten DAB development if the control sections also darken; these are general workflow adjustments (standard IHC practice). Compare background in the same tissue compartment across identically processed slides, since section edges, folds, and poorly preserved areas can accumulate stain (standard IHC practice). High neuronal staining is reported in caudate and cerebral cortex, while adipocytes in adipose tissue are reported as not detected (HPA: tissue IHC). Those patterns guide control selection but cannot validate every stained cell in an experimental section (standard IHC practice).
How should I quantify FBXL16 IHC across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; nuclear and cytoplasmic expression has been reported in CNS tissue (HPA: CNS profile). Within matched regions, record the percentage of positive cells and an intensity-based H-score, or count positive cells per mm² when cell density is the primary endpoint (standard IHC practice). Normalise positive-cell counts to the number of eligible cells, or stained area to analysed tissue area, rather than comparing fields with different cellularity (standard IHC practice). Apply one threshold and imaging or scoring workflow across batches, with blinded review of ambiguous cells where feasible (standard IHC practice). Report compartment-specific results and the selected control tissue alongside summary values (standard IHC practice).
When is an apparent FBXL16-positive cell likely to be artefactual?
First check whether the stained cell type and compartment fit the reported pattern: neuronal cells in caudate and cerebral cortex stain highly, and CNS staining includes cytoplasm and nuclei (HPA: tissue IHC). A signal confined to section edges, folds, or necrotic areas warrants caution because those patterns can arise during chromogenic processing (standard IHC practice). For peroxidase detection, staining that persists in a no-primary control raises concern about endogenous enzyme activity or the detection system (standard IHC practice). Unexpected staining in a cell population reported as not detected, such as adipocytes in adipose tissue, needs independent validation rather than automatic rejection (HPA: adipose tissue adipocytes, Not detected; standard IHC practice). Interpret borderline results cautiously because reported staining and RNA expression show medium consistency (HPA: reliability description).
Boster reagents

Best FBXL16 / F-box/LRR-repeat protein 16 IHC Antibodies

A15331 has human spleen IHC and IF images (catalog: image captions) and lists human, mouse, and rat reactivity (catalog: reactivity).

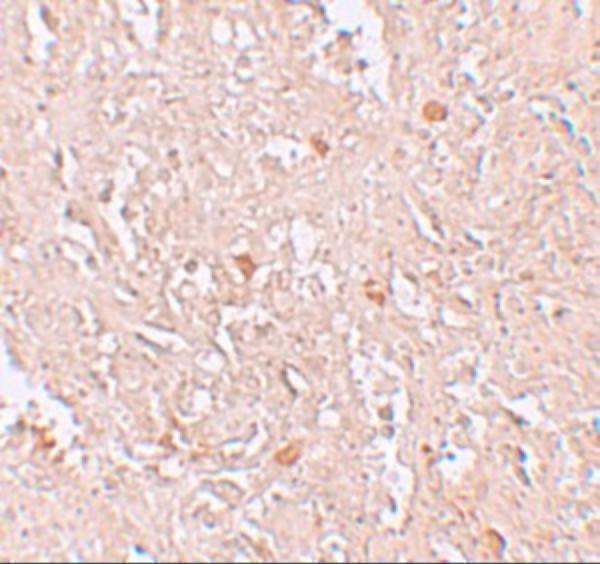
Real IHC data Immunohistochemistry of FBXL16 in human spleen tissue with FBXL16 antibody at 5 μg/mL.
Anti-F-box/LRR-repeat protein 16 FBXL16 Antibody
Cat # A15331

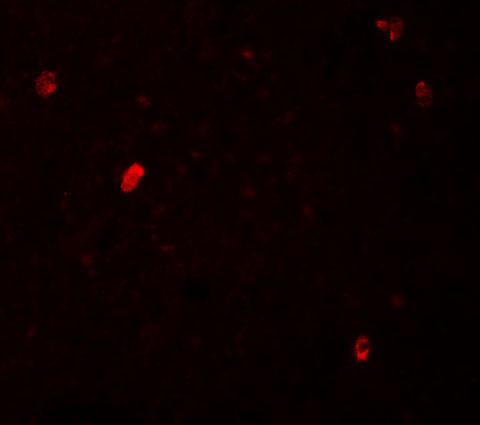
A15331 lists IHC-P and IF applications (catalog: applications). Its images show FBXL16 staining in human spleen tissue by IHC at 5 μg/mL and IF at 20 μg/mL (catalog: image captions).

Which to pick: Choose A15331 for paraffin-section IHC because IHC-P is listed, with a human spleen IHC image at 5 μg/mL (catalog: applications; IHC image caption); the caption does not report a fixative (catalog: IHC image caption). For tissue IF, A15331 has a human spleen image at 20 μg/mL; ICC is not listed (catalog: IF image caption; applications). A15331 is also the cross-species candidate because it lists human, mouse, and rat reactivity, although the supplied IHC and IF images show human tissue only (catalog: reactivity; image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q8N461 (FXL16_HUMAN, F-box/LRR-repeat protein 16).
  2. Human Protein Atlas. FBXL16 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. FBXL16 subcellular location (ICC-IF): Highest expression in SH-SY5Y: 21.4 nTPM.
  4. Human Protein Atlas. FBXL16 antibody validation summary (2 antibodies).
  5. FBXL16 Promotes Endometrial Progesterone Resistance via PP2A(B55α) /Cyclin D1 Axis in Ishikawa. Journal of immunology research 2022 — PMC9467819.
  6. FBXL16 promotes cell growth and drug resistance in lung adenocarcinomas with KRAS mutation by stabilizing IRS1 and upregulating IRS1/AKT signaling. Molecular oncology 2024 — PMC10920083.
  7. FBXL16: a new regulator of neuroinflammation and cognition in Alzheimer's disease through the ubiquitination-dependent degradation of amyloid precursor protein. Biomarker research 2024 — PMC11580471.
  8. PubMed PMID:14702039 — UniProt-cited evidence.
  9. PubMed PMID:11157797 — UniProt-cited evidence.
  10. PubMed PMID:15616553 — UniProt-cited evidence.