GART / Trifunctional purine biosynthetic protein adenosine-3 · IHC design guide

Design Immunohistochemistry for GART

Plan GART staining in paraffin sections with the IHC-tested catalog antibody (datasheet: IHC). Expect widespread cytoplasmic staining (HPA tissue IHC), and use specificity controls because presumed off-target binding was observed (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
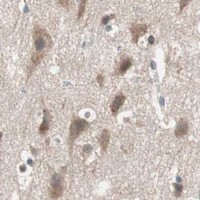
Immunohistochemistry protocol sheet for GART (IHC for GART): expected localisation Cytoplasmic staining across tissues (HPA tissue IHC), antibody M06061, validated IHC image, and IHC protocol steps
Printable GART IHC protocol sheet — expected localisation Cytoplasmic staining across tissues (HPA tissue IHC), antibody M06061, controls and protocol steps. Open the full GART IHC guide →

GART Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining across tissues (HPA tissue IHC)
Staining pattern Cytoplasmic staining in glandular and other cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Heart muscle
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Presumed off-target staining may confound interpretation (HPA tissue IHC)
Regulation Staining-linked regulation unreported (UniProt)
Isoform / epitope 2 isoforms, Long and Short; epitope map unknown (UniProt)
Section 1

Recommended GART IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with one published GART IHC protocol using FFPE xenograft tumors (PMC12463125).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human cervix cancer tissue; fixative not specified (datasheet M06061)
FixationImage fixative and duration unreported (datasheet M06061); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit monoclonal (clone FFD-7) anti-GART, 1:50 (datasheet M06061)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultGART-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page antigen-retrieval specification); the published excerpt gives no retrieval conditions (PMC12463125).
Section 2

What Is the Expected GART Staining Pattern?

GART is expected mainly in the cytoplasm across many tissues (HPA: ubiquitous cytoplasmic IHC profile). Medium staining is reported in several glandular, epithelial, hematopoietic and neuronal cell populations (HPA: tissue IHC). HPA rates the tissue pattern Approved, with medium consistency against RNA data and pending external verification (HPA: tissue IHC reliability). GART has no transmembrane segment (UniProt P22102: topology).

What am I looking at on my slide?
Cytoplasmic staining in appendix glandular cells or bone marrow hematopoietic cells.This fits the reported medium signal in those populations (HPA: tissue IHC). Compare intensity within the same staining run; a positive result does not require every cell to stain equally (general IHC practice).
Predominantly nuclear or crisp cell-surface staining.That differs from the reported cytoplasmic IHC profile and approved cytosolic ICC-IF location (HPA: tissue IHC; HPA: subcellular). Treat it as suspect until an independent control supports it; absent transmembrane topology also gives no basis for a membrane pattern (UniProt P22102: topology).
Strong staining in heart cardiomyocytes or an unexpected structure.Cardiomyocytes are reported as not detected (HPA: heart muscle IHC). Investigate nonspecific binding or endogenous chromogen activity (general IHC practice). HPA also notes presumed off-target staining and staining in unannotated structures, so inspect the relevant images before assigning cell identity (HPA: tissue IHC reliability).
Brown haze across cells, extracellular areas and the negative control.A field-wide deposit cannot establish GART localization (general IHC practice). Check background from detection reagents, inadequate blocking or washing, and chromogen development using a control that omits the primary antibody (general IHC practice).
No staining in an expected positive tissue section.Appendix glandular cells and bone marrow hematopoietic cells are reported at medium intensity (HPA: tissue IHC). Verify that the target cells are present, then review retrieval, antibody dilution and detection controls (general IHC practice); absence alone does not prove biological loss.
💡Expected GART appearanceCall positive when the appropriate cells show predominantly cytoplasmic, approximately medium signal in a reported medium-staining tissue (HPA: tissue IHC); isolated nuclear, membrane or cardiomyocyte staining is suspect against the reported pattern (HPA: tissue IHC; HPA: subcellular).
How each factor affects the staining
Tissue and cell choiceHPA reports low tissue RNA specificity and a ubiquitous cytoplasmic IHC profile, yet cardiomyocytes are not detected (HPA: tissue IHC). Score identified cells rather than treating every tissue compartment as equally positive (general IHC practice).
Strength of tissue evidenceThe tissue IHC rating is Approved, with medium RNA–staining consistency, pending external verification and presumed off-target binding disregarded (HPA: tissue IHC reliability). Interpret unfamiliar staining cautiously.
Isoforms and antibody epitopeUniProt lists 2 isoforms, Long and Short (UniProt P22102: isoforms). The supplied record gives no antibody epitope, so it cannot establish whether either antibody recognizes both forms.
Processing and topologyUniProt lists no signal peptide, propeptide or transmembrane segment and gives a chain spanning residues 2–1010 (UniProt P22102: processing; topology). These annotations provide no basis to expect a secreted or membrane-restricted IHC pattern.
IF/ICC Q&A: where should GART appear?Mainly in the cytosol, with additional mitochondrial localization (HPA: subcellular ICC-IF). This answers the localization question; the paraffin-section IHC pattern remains the basis for scoring chromogenic sections (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive tissue shows no signal.Target cells may be absent from the viewed area, or the IHC workflow may have failed (general IHC practice).Confirm the relevant appendix glandular or bone marrow hematopoietic cells are present (HPA: tissue IHC); check retrieval, antibody dilution and detection with appropriate controls (general IHC practice).
Only nuclei or cell borders stain.This conflicts with cytoplasmic tissue staining and approved cytosolic ICC-IF localization (HPA: tissue IHC; HPA: subcellular).Inspect primary-omission and tissue controls, then reassess antibody specificity and cell boundaries (general IHC practice). Do not score the discordant compartment as established GART localization.
Heart cardiomyocytes stain strongly.Cardiomyocytes are listed as not detected, although HPA cautions that presumed off-target staining occurred (HPA: tissue IHC reliability; heart muscle IHC).Recheck cell identification and compare with primary-omission and detection controls (general IHC practice). Seek independent support before calling cardiomyocyte staining GART.
Diffuse brown background obscures cells.Endogenous detection activity or nonspecific reagent deposition may contribute (general IHC practice); the pattern does not resolve the reported cytoplasmic signal (HPA: tissue IHC).Compare primary-omission controls; review blocking, washes and chromogen development for the detection system in use (general IHC practice).
Mitochondria-like puncta dominate a paraffin section.Mitochondrial localization is additional in ICC-IF, while tissue IHC is summarized as cytoplasmic (HPA: subcellular; tissue IHC). Chromogenic puncta alone cannot identify an organelle (general IHC practice).Score the cytoplasmic tissue pattern first (HPA: tissue IHC). If organelle identity matters, consult the separate IF/ICC guide and use appropriate localization controls (general IF practice).
A weak field appears to contradict a positive call.HPA reports low staining in several listed populations and medium staining in others (HPA: tissue IHC); field selection and cell identity affect comparison (general IHC practice).Identify the scored cell population and compare it with its specific HPA tissue entry (HPA: tissue IHC). Review a reported medium-staining positive control in the same run (general IHC practice).

Sample controls for GART IHC & IF

🧪Run appendix first and assess its glandular cells for GART staining (HPA: Medium in appendix glandular cells). Run heart muscle as the negative tissue (HPA: Not detected in cardiomyocytes); on the appendix slide, cells used as an internal negative reference should show background-only staining, but the supplied HPA rows do not identify a validated internal-negative cell type.
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Heart muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show GART in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, an isotype control matched to the primary antibody’s host species and clonality, and GART-knockout material if available as a biological negative (standard IHC practice). For appendix IHC, block endogenous peroxidase and check staining in inflammatory cells before interpreting the chromogen signal (standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected M06061 paraffin-section caption does not state a fixative (selected caption: paraffin-embedded human cervix cancer; fixative unreported). GART-specific retrieval dependency is unreported; compare standard antigen-retrieval conditions, and do not assume frozen sections or IF/ICC are easier on the basis of the available ICC-IF images (HPA: images in A-431, U-251MG and U2OS). In appendix, endogenous peroxidase in inflammatory cells can complicate chromogenic interpretation (standard IHC practice).

HPA tissue IHC evidence for GART

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification. Presumed off target binding observed and disregarded. Antibody staining in cells/structures not annotated, view images.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Adipocytes Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Section 3

Advanced GART IHC Tips

Troubleshoot GART staining by checking tissue preparation, cytoplasmic localisation, antibody specificity, and consistent scoring across matched paraffin sections.

How should I adjust retrieval when GART staining is weak in paraffin sections?
Start with citrate pH 6.0 heat-induced antigen retrieval at 95–98 °C for 20 min (page retrieval setting). Let slides cool in retrieval buffer, then compare staining with a matched control section processed in the same run (standard IHC practice). If staining remains weak, vary heating time in small increments before testing another buffer or pH as a fallback, and watch for tissue damage or rising background (standard IHC practice). Assess improvement in cytoplasmic staining within identifiable cells, since GART has a ubiquitous cytoplasmic tissue profile and approved cytosolic localisation (HPA tissue IHC; HPA subcellular).
Could fixation explain weak or uneven GART staining?
GART-specific fixation sensitivity is unknown: the selected M06061 paraffin-section caption does not report a fixative, and the supplied record gives no target-specific fixation comparison (selected hero caption; supplied record). Record the fixative, fixation duration, section age, and processing history for each specimen before comparing signal (standard IHC practice). On matched sections, hold retrieval and detection conditions constant while checking whether staining varies with documented processing differences (standard IHC practice). Use preserved tissue morphology and staining in an appropriate control section to judge the run; neither the HPA tissue pattern nor GART topology establishes a fixation effect (standard IHC practice; HPA tissue IHC; UniProt P22102 topology).
Which staining compartment is plausible for GART in IHC?
Prioritise interpretable cytoplasmic staining in intact cells: tissue IHC describes ubiquitous cytoplasmic expression, while cell imaging places GART mainly in the cytosol with an additional mitochondrial location (HPA tissue IHC; HPA subcellular). The UniProt record lists no transmembrane segment or signal sequence, so a crisp cell-surface outline alone warrants scrutiny (UniProt P22102 topology and processing). Compare the suspect pattern with adjacent cells and a matched control section under identical chromogenic detection conditions (standard IHC practice). Do not claim that chromogenic tissue staining resolves mitochondria from diffuse cytosol; use a compartment marker and higher-resolution imaging if that distinction matters (standard microscopy practice; HPA subcellular).
How can isoforms or epitope access complicate GART IHC?
GART has 2 listed isoforms, Long and Short, but the supplied material does not map the catalog antibody epitope to either one (UniProt P22102 isoforms; supplied antibody evidence). Check available antibody epitope documentation before assigning a staining difference to isoform expression, and compare identically processed sections when evaluating it (standard IHC practice). The protein contains an ATP-grasp domain at residues 111–318 and several annotated modified residues, but their effect on this antibody’s binding is unknown (UniProt P22102 domains and modified residues; supplied antibody evidence). Weak staining after retrieval therefore cannot, by itself, identify an isoform or a modification-dependent epitope (standard antibody interpretation).
How should I investigate a GART pattern using multiplex IF?
For a separate IF experiment, pair GART with a marker that identifies the expected cell population in the specimen, then inspect whether signal lies within those cells (standard multiplex IF practice; HPA tissue IHC). Choose spectrally separated fluorophores and assess unstained tissue autofluorescence before assigning a weak channel to GART (standard IF practice). Because GART is mainly cytosolic, use a validated permeabilisation condition that allows antibody access to intracellular epitopes, while checking whether it disrupts morphology or the companion marker (HPA subcellular; standard IF practice). Keep IF findings distinct from chromogenic IHC results: the supplied M06061 caption documents paraffin-section IHC and does not establish an IF fixation or permeabilisation protocol (selected hero caption).
How can I distinguish diffuse GART staining from chromogenic background?
Compare suspected signal with a no-primary control, a matched control section, and tissue morphology before changing antibody concentration (standard IHC practice). Block endogenous peroxidase for peroxidase-based detection and inspect whether residual pigment or precipitate appears independently of cellular boundaries (standard chromogenic IHC practice). Optimise antibody dilution and wash conditions using the same retrieval and chromogen development across sections, recording the conditions that preserve cytoplasmic contrast (standard IHC practice; HPA tissue IHC). Widespread staining alone is not proof of specificity: HPA reports ubiquitous cytoplasmic expression but also medium RNA concordance, pending external verification, and presumed off-target binding (HPA tissue IHC).
What should I measure when comparing GART IHC across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and analysis region before scoring, then report cytoplasmic intensity and percentage of positive cells or a prespecified H-score (standard quantitative IHC practice; HPA tissue IHC). Use the same threshold, magnification, retrieval, detection, and chromogen development for every section in a comparison (standard IHC practice). Normalise positive-cell counts to the number of evaluable cells, or report positive-cell density per mm² of viable tissue when area is the denominator (standard quantitative IHC practice). Exclude folds, necrosis, and poorly preserved edges consistently, and retain a matched control section to detect staining drift between runs (standard IHC practice).
What would make an apparent GART-positive region unconvincing?
Treat predominantly extracellular, sharply membranous, or isolated nuclear staining cautiously because the supported pattern is cytoplasmic and GART has no annotated transmembrane segment (HPA tissue IHC; UniProt P22102 topology). Check whether the signal follows tissue edges, necrotic areas, folds, or endogenous peroxidase activity rather than intact cell boundaries (standard chromogenic IHC practice). Cell identity matters: HPA reports medium staining in cervix glandular cells and no detection in heart cardiomyocytes, but these observations are controls for interpretation rather than universal rules (HPA tissue IHC). Seek reproducible cytoplasmic signal in matched sections and independent specificity evidence before making a biological claim, given HPA’s stated reliability limitations (standard IHC practice; HPA tissue IHC).
Boster reagents

Best GART / Trifunctional purine biosynthetic protein adenosine-3 IHC Antibodies

The IHC-validated anti-GART antibody has an image of paraffin-embedded human cervix cancer (IHC image caption). IF/ICC and human, mouse, and rat reactivity are listed without an IF image (catalog).

Real IHC data Immunohistochemical analysis of paraffin-embedded human cervix cancer, using GART Antibody.
Anti-GART Rabbit Monoclonal Antibody
Cat # M06061

M06061 will render with its IHC image of paraffin-embedded human cervix cancer (IHC image caption). Its listed applications include IHC and ICC/IF, with human, mouse, and rat reactivity; no IF image is provided (catalog).

Which to pick: For tissue IHC, choose M06061: its own image shows paraffin-embedded human cervix cancer, and the caption does not report a fixative (IHC image caption). For IF/ICC, M06061 lists both applications, although no IF image is provided (catalog). For work across the listed species, M06061 is a rabbit monoclonal, clone FFD-7, with human, mouse, and rat reactivity (catalog).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P22102 (PUR2_HUMAN, Trifunctional purine biosynthetic protein adenosine-3).
  2. Human Protein Atlas. GART tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. GART subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the mitochondria..
  4. Human Protein Atlas. GART antibody validation summary (2 antibodies).
  5. A functional genetic screen for metabolic proteins unveils GART and the de novo purine biosynthetic pathway as novel targets for the treatment of luminal A ERα expressing primary and metastatic invasive ductal carcinoma. Frontiers in endocrinology 2023 — PMC10151738.
  6. Placing purines in precision medicine: Targeting a metabolic reliance in KRAS-mutant tumors. iScience 2026 — PMC12937152.
  7. LEDGF Binds H3R17me2a Promoting De Novo Nucleotide Biosynthesis in SETD2 Mutant Clear Cell Renal Cell Carcinoma. Advanced science (Weinheim, Baden-Wurttemberg, Germany) 2025 — PMC12463125.
  8. PubMed PMID:2147474 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.