This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic IHC for GLRX using kidney tubules as a high-staining reference (HPA tissue IHC). Compare cytoplasmic staining across sections (HPA tissue IHC), starting the IHC-validated antibody at 2–5 μg/ml (datasheet A03392-1).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic in tissue sections (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in several tissues (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A03392-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Breast+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining and RNA show medium consistency (HPA tissue IHC) | |
| Regulation | Regulation not annotated (UniProt) | |
| Isoform / epitope | No isoforms annotated; chain spans residues 2–106 (UniProt) |
The catalog antibody’s IHC-P protocol is followed by 3 published GLRX chromogenic IHC protocols (datasheet: A03392-1; PMC8805200; PMC10916419; PMC8442864).
| Sample | Paraffin-embedded human kidney tissue; fixative not specified (datasheet A03392-1) |
| Fixation | Image fixative and duration unreported (datasheet A03392-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A03392-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A03392-1) |
| Primary antibody | Rabbit anti-GLRX, 2-5 μg/ml (datasheet A03392-1) |
| Primary incubation | Overnight at 4 °C (datasheet A03392-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A03392-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | GLRX-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues, including kidney, gastrointestinal tract and placenta. No signal in the no-primary control. |
GLRX should appear mainly in the cytoplasm of stained cells (UniProt P35754: cytoplasm; HPA: cytoplasmic tissue expression). High IHC staining is reported in kidney tubule cells and several glandular or epithelial cell populations (HPA: tissue IHC). Treat these as useful comparators, not universal thresholds: HPA rates the tissue staining Approved but reports medium consistency with RNA expression (HPA: tissue IHC reliability). GLRX has no transmembrane segment (UniProt P35754: topology).
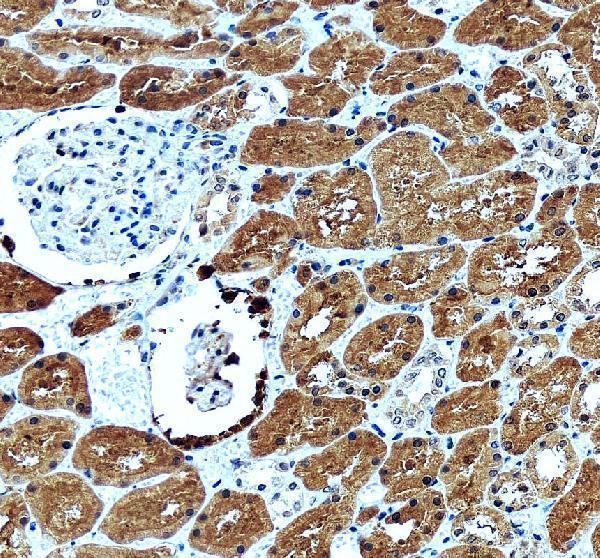
| Kidney tubule cells show clear cytoplasmic chromogenic staining, with little deposit outside the cells. | This fits a useful positive control: kidney tubule cells are High by tissue IHC (HPA: kidney), and GLRX is cytoplasmic (UniProt P35754: subcellular location). Compare the stained cells and compartment together; staining intensity alone does not establish specificity (general IHC practice). |
| Signal is confined to nuclei or forms a discrete intracellular pattern without convincing cytoplasmic staining. | A predominantly nuclear pattern conflicts with the annotated cytoplasmic location (UniProt P35754: subcellular location) and HPA tissue profile (HPA: cytoplasmic expression). Reassess morphology and controls before calling it GLRX; nonspecific binding or chromogen artefact can produce misleading deposits (general IHC practice). |
| Breast adipocytes or colon endothelial cells stain strongly while expected positive cells are weak. | Those specific cell populations are Not detected in HPA tissue IHC (HPA: breast adipocytes; colon endothelial cells). Check antibody specificity and endogenous detection activity with suitable controls (general IHC practice). Their HPA result is a cell-specific comparator, not a claim that every cell in either tissue lacks GLRX. |
| A low-contrast haze covers cells, stroma, and empty spaces rather than following cell boundaries. | Uniform slide-wide deposit is difficult to reconcile with the reported cell-specific cytoplasmic profile (HPA: tissue IHC). Review the no-primary control, blocking, washes, and chromogen development (general IHC practice). The pattern cannot be assigned to GLRX from appearance alone. |
| Kidney tubule cells are unstained, including in the positive-control section. | HPA reports High staining in kidney tubule cells (HPA: kidney). First check section integrity, retrieval, antibody application, and detection using appropriate process controls (general IHC practice). HPA's Approved rating has medium RNA-staining consistency (HPA: tissue IHC reliability), so a single negative section does not establish biological absence. |
| Compartment and topology | GLRX is annotated in the cytoplasm and has no transmembrane segment (UniProt P35754: location; topology). In paraffin IHC, judge the cell-associated cytoplasmic pattern; the topology entry alone does not predict staining at a visible cell boundary or specify an antibody epitope. |
| Choice of tissue comparator | Kidney tubule, duodenal glandular, and pancreatic exocrine glandular cells are High (HPA: tissue IHC). Appendix glandular cells are Medium, while thyroid glandular cells are Low (HPA: tissue IHC). Choose a clearly annotated High population for the positive comparison, and record the exact cell type when interpreting weaker fields. |
| Strength of tissue evidence | The HPA tissue profile is Approved, with medium consistency between antibody staining and RNA expression (HPA: tissue IHC reliability). Three listed antibodies have Approved IHC status (HPA: antibody validation). These ratings support a reference pattern, but do not prove that every positive deposit from a separate catalog antibody is specific. |
| Protein processing and epitope | UniProt lists the GLRX chain as residues 2–106, with no signal peptide, propeptide, or annotated isoforms (UniProt P35754: processing; isoforms). It also lists modified residues at positions 2 and 9 (UniProt P35754: modified residues). Without a mapped antibody epitope, these facts do not predict retrieval needs or fixation sensitivity. |
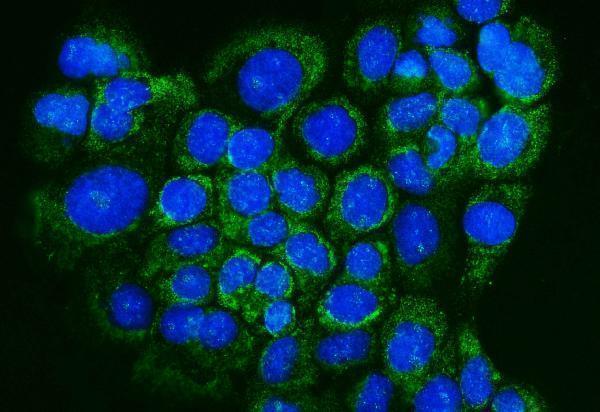
| IF/ICC Q&A: what localisation should be expected? | HPA reports cytosol as supported and plasma membrane as approved in ICC-IF (HPA: subcellular). That observation can inform interpretation of the separate IF/ICC guide; it does not override the cytoplasmic tissue IHC profile or supply an IF/ICC protocol (HPA: tissue IHC; subcellular). |
| Situation | Likely cause | Next action |
|---|---|---|
| No stain in a kidney positive-control section. | The expected High kidney tubule pattern is missing (HPA: kidney); the failed step is not identifiable from this image alone. | Confirm tubules are present, then review retrieval, antibody application, detection reagents, and control-slide results in sequence (general IHC practice). Repeat the control before interpreting test sections. |
| Every tissue compartment stains, including areas outside cells. | Widespread deposit conflicts with the cell-associated cytoplasmic pattern (HPA: tissue IHC; UniProt P35754: cytoplasm). Excess detection background is possible (general IHC practice). | Inspect no-primary controls; review blocking, wash stringency, and chromogen development (general IHC practice). Reassess specificity only after the background is controlled. |
| The signal appears mainly nuclear. | Predominant nuclear staining is inconsistent with the reported cytoplasmic location (UniProt P35754: location; HPA: tissue IHC). | Check counterstain and focus, then compare positive and no-primary controls (general IHC practice). Do not score nuclear-only staining as the expected GLRX pattern without independent validation. |
| Breast adipocytes or colon endothelial cells show unexpected strong staining. | HPA lists those cell populations as Not detected (HPA: breast adipocytes; colon endothelial cells); cross-reactivity or endogenous detection activity is possible (general IHC practice). | Verify cell identity on the section and compare no-primary and detection-system controls (general IHC practice). Report the discrepancy by cell type rather than treating the entire tissue as an HPA negative. |
| A Low population stains as strongly as the kidney control. | HPA lists thyroid glandular cells as Low and kidney tubule cells as High (HPA: thyroid gland; kidney), but staining levels are qualitative reference categories. | Compare matched sections processed together and inspect controls (general IHC practice). Record the observed intensity and cell type; avoid converting HPA categories into a fixed numeric cutoff. |
| The IHC pattern differs from an ICC-IF image showing a cell-edge signal. | HPA reports approved plasma-membrane and supported cytosolic localisation in ICC-IF (HPA: subcellular), while its tissue IHC profile describes cytoplasmic expression (HPA: tissue IHC). | Interpret each preparation against its own HPA reference and verify the IHC cell type and controls (general IHC practice). Do not treat ICC-IF cell-edge signal alone as proof of a membrane-restricted paraffin IHC pattern. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Nasopharynx | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Pancreas | Exocrine glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Colon | Endothelial cells | Not detected | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Use the kidney IHC example as a starting point, then judge GLRX staining by compartment, cell type, controls and the limits of the available evidence.
A03392-1 has IHC data from a human kidney paraffin section (catalog IHC caption) and IF/ICC data from A431 cells (catalog IF caption); its listed reactivity is human (catalog: Human).
A03392-1 will render with human kidney paraffin-section IHC data (catalog IHC caption). The same SKU lists IF and ICC applications (catalog: applications) and shows IF staining of A431 cells (catalog IF caption).
Which to pick: Choose A03392-1 for human paraffin-section IHC: its image shows kidney tissue with EDTA heat retrieval and 2 μg/ml primary antibody (catalog IHC caption); the fixative is unreported (catalog IHC caption). For IF/ICC, the same SKU lists both applications and shows A431-cell IF at 5 μg/ml (catalog: applications; catalog IF caption). No SKU in this payload lists reactivity beyond human, so there is no supported cross-species choice (catalog: reactivity).