IL23A / Interleukin-23 subunit alpha · IHC design guide

Design Immunohistochemistry for IL23A

Plan IL23A paraffin-section IHC with fixation, controls, chromogenic detection, and scoring guidance. Lymph-node non-germinal-center cells show high staining, while immune-cell subsets show a cytoplasmic pattern (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for IL23A (IHC for IL23A): expected localisation Cytoplasm in immune-cell subsets (HPA tissue IHC), antibody A01097, validated IHC image, and IHC protocol steps
Printable IL23A IHC protocol sheet — expected localisation Cytoplasm in immune-cell subsets (HPA tissue IHC), antibody A01097, controls and protocol steps. Open the full IL23A IHC guide →

IL23A Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasm in immune-cell subsets (HPA tissue IHC)
Staining pattern Immune-cell subsets show cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A01097)
Positive control ⓘ Lymph node+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Formaldehyde-fixed paraffin sections (datasheet A01097 IHC-P) (selected-SKU IHC image A01097)
Caveat Secretion can make tissue RNA and protein patterns differ (HPA tissue IHC)
Regulation Produced by activated phagocytes (UniProt)
Isoform / epitope No isoforms; signal 1–19 removed; no TM sidedness (UniProt)
Section 1

Recommended IL23A IHC & IF Protocols

This section pairs the catalog antibody’s IHC-P protocol (datasheet A01097) with one published colorectal cancer tissue protocol (PMC8129521).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleFormaldehyde-fixed, paraffin-embedded human pancreas tissue (datasheet A01097)
FixationImage formalin-fixed; duration unreported (datasheet A01097); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6 (datasheet A01097); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% serum (datasheet A01097)
Primary antibodyRabbit anti-IL23A, 5 μg/mL (datasheet A01097)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultIL23A-positive staining in non-germinal center cells of lymph node (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression mainly in subsets of immune cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated citrate retrieval at pH 6 (datasheet A01097); the published protocol does not state a retrieval method (PMC8129521).
Section 2

What Is the Expected IL23A Staining Pattern?

In paraffin-section IHC, expect IL23A mainly in the cytoplasm of subsets of immune cells, with strong staining in lymph-node non-germinal-center cells (HPA tissue IHC: High; reliability Approved). IL23A has no transmembrane segment and is secreted upon association with IL12B (UniProt Q9NPF7: topology and subcellular location). Interpret extracellular staining cautiously: HPA notes that RNA and protein locations may differ for this secreted protein (HPA tissue IHC: reliability description).

What am I looking at on my slide?
Distinct cytoplasmic staining in a subset of lymph-node non-germinal-center cells.This fits the strongest supplied tissue example (HPA tissue IHC: lymph node, High). A subset pattern also fits HPA’s overall cytoplasmic immune-cell profile (HPA tissue IHC: profile). Score the stained cells and their location, rather than calling the entire lymph node uniformly positive (HPA tissue IHC: cell-specific observation).
Signal appears predominantly nuclear or as a sharp cell-surface rim.That distribution conflicts with the observed cytoplasmic tissue pattern (HPA tissue IHC: profile) and approved cytosolic ICC-IF location (HPA subcellular: Cytosol). Review counterstain separation and detection artefacts before assigning that signal to IL23A (general IHC practice). The absence of a transmembrane segment gives no basis for expecting a membrane-rim pattern (UniProt Q9NPF7: topology).
Broad staining appears in cell types outside the reported pattern.Compare the stained cell type with HPA’s cell-level observations; adipocytes in adipose tissue and respiratory epithelial cells in bronchus were not detected (HPA tissue IHC: negative examples). HPA explicitly disregarded presumed off-target binding (HPA tissue IHC: reliability description). Consider cross-reactivity or endogenous detection activity, then check a matched control (general IHC practice).
A diffuse chromogenic haze obscures cell boundaries across the section.This cannot establish the expected cell-restricted cytoplasmic result (HPA tissue IHC: profile). Compare a no-primary control, inspect washing and detection conditions, and score only distinguishable cellular signal (general IHC practice). Because IL23A is secreted upon association with IL12B, extracellular signal alone does not identify its source cell (UniProt Q9NPF7: subcellular location).
No convincing signal appears in lymph-node non-germinal-center cells.The selected positive reference has High staining in those cells (HPA tissue IHC: lymph node). Confirm that the relevant cells are present, then review staining controls, antigen retrieval and antibody conditions as general IHC checks (general IHC practice). A failed run remains possible; this result alone does not establish absent IL23A expression.
💡Expected IL23A appearanceCall a positive result when a subset of lymph-node non-germinal-center cells shows distinct High cytoplasmic staining (HPA tissue IHC: lymph node and profile); broad nuclear, membrane-rim or non-cell-restricted colour does not match that reference pattern (HPA tissue IHC: profile; HPA subcellular: Cytosol).
How each factor affects the staining
Secretion and cellular originIL23A is secreted upon association with IL12B (UniProt Q9NPF7: subcellular location and subunit). HPA therefore expects tissue RNA and protein locations to differ (HPA tissue IHC: reliability description). Use cell-level staining and controls when attributing a positive chromogenic signal to a producer cell (general IHC practice).
Tissue and cell selectionLymph-node non-germinal-center cells are High; appendix lymphoid tissue, bone-marrow hematopoietic cells and tonsil germinal-center cells are Medium (HPA tissue IHC: positive examples). Select and interpret the relevant cell population within each section; the reported level does not describe every cell in that organ (HPA tissue IHC: cell-specific observations).
Cell-type exceptionRound or early spermatids in testis have Medium staining (HPA tissue IHC: positive example). Thus, an immune-cell-only scoring rule would discard a supplied positive observation. Assess this finding in its stated cell type and tissue context, while applying the same control checks used for other chromogenic signals (general IHC practice).
Antibody evidenceThe listed antibody, HPA001554, is Approved for IHC and ICC (HPA antibodies: validation status). The tissue assessment also says presumed off-target binding was observed and disregarded (HPA tissue IHC: reliability description). Approval supports use of the reported pattern as a reference; unexpected staining still needs cell-level review and controls (general IHC practice).
IF/ICC interpretation?HPA reports an approved cytosolic ICC-IF location, consistent with its cytoplasmic tissue IHC profile (HPA subcellular: Cytosol; HPA tissue IHC: profile). Treat that as a localization cross-check, while scoring the paraffin-section chromogenic result against the tissue and cell observations reported for IHC (HPA tissue IHC: positive examples).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive-reference cells remain blank.The run may have failed, or the relevant cells may be absent from the examined area (general IHC practice).Locate lymph-node non-germinal-center cells, the reported High group (HPA tissue IHC: lymph node). Check run controls and review retrieval and antibody conditions as general IHC variables (general IHC practice).
Signal is predominantly nuclear.Nuclear staining conflicts with the reported cytoplasmic and cytosolic locations (HPA tissue IHC: profile; HPA subcellular: Cytosol).Inspect the counterstain and no-primary control; score nuclear colour separately from convincing cytoplasmic signal (general IHC practice).
Many unexpected cell types stain.Cross-reactivity or endogenous detection activity is possible (general IHC practice); HPA notes presumed off-target binding (HPA tissue IHC: reliability description).Compare each stained cell type with HPA’s positive and not-detected observations, then examine matched detection controls (HPA tissue IHC: cell-level observations; general IHC practice).
Diffuse colour hides cellular detail.Background from blocking, detection or washing conditions may obscure a cell-restricted pattern (general IHC practice).Review the no-primary control and staining conditions; interpret only resolvable cellular staining against HPA’s cytoplasmic reference (general IHC practice; HPA tissue IHC: profile).
Extracellular signal dominates.IL23A is secreted upon association with IL12B, so deposited protein may be spatially separate from its source (UniProt Q9NPF7: subcellular location).Record extracellular and intracellular signals separately; use identifiable cytoplasmic staining to assess agreement with the tissue reference (HPA tissue IHC: profile; general IHC practice).
A supposed negative control contains a few stained cells.HPA’s not-detected entries apply to specified cell types, such as adipocytes in adipose tissue, rather than every cell in a section (HPA tissue IHC: negative examples).Identify the stained cells and score the specified reference cell type; investigate staining outside that cell type with matched controls (HPA tissue IHC: cell-level observations; general IHC practice).

Sample controls for IL23A IHC & IF

🧪Run lymph node first and look for IL23A staining in non-germinal center cells (HPA: High in lymph node non-germinal center cells). Use adrenal gland glandular cells as the negative tissue (HPA: Not detected); on the positive slide, score morphologically identified unstained cells as internal background rather than assuming every other lymph-node cell is negative.
Positive control tissue: Lymph node (Non-germinal center cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show IL23A in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, a host-, isotype-, and clonality-matched control immunoglobulin, and an IL23A knockout specimen processed alongside the test slide. Block endogenous peroxidase for chromogenic detection in lymph node, where hematopoietic cells can contribute background (HPA: lymph node positive row; standard IHC practice).
⚠️Feasibility: The A01097 paraffin-section caption uses heat retrieval in citrate buffer at pH 6, but does not establish that retrieval is required; no target-specific fixation window or fixation effect is reported (A01097 caption). Its narrative mentions formaldehyde while its supplied fixative field says “not stated in the caption,” so the fixative metadata are inconsistent (A01097 caption; supplied fixative field). The evidence does not establish whether frozen sections or IF are easier; because IL23A is secreted upon association with IL12B, assign staining to cells cautiously (UniProt Q9NPF7 subcellular annotation).

HPA tissue IHC evidence for IL23A

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Secreted protein, tissue location of RNA and protein is expected to differ. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Lymph node Non-germinal center cells High Protein (IHC) HPA →
Appendix Lymphoid tissue Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Testis Round or early spermatids Medium Protein (IHC) HPA →
Tonsil Germinal center cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Section 3

Advanced IL23A IHC Tips

Troubleshoot chromogenic IL23A IHC in paraffin sections using the documented antibody conditions, tissue controls, and the expected cellular distribution.

Which retrieval condition should I start with for weak IL23A staining?
Start with heat-mediated citrate retrieval at pH 6 for paraffin-section IL23A IHC (datasheet A01097). Apply identical heating to test and control sections, then compare retrieval duration if staining remains weak; excessive heating can damage morphology (standard IHC practice). The documented primary concentration is 5 µg/ml, with overnight incubation at 4 °C (A01097 tissue-IHC caption). Assess cytoplasmic staining in immune-cell subsets while checking background, because presumed off-target binding has been observed (HPA tissue IHC). If citrate retrieval still fails, evaluate another buffer only as a controlled fallback, holding detection conditions constant (standard IHC practice).
How can I distinguish fixation problems from genuinely low IL23A expression?
Target-specific sensitivity of IL23A staining to fixation duration or fixative choice is unknown from the supplied evidence (evidence limitation). Record fixation and processing conditions for every paraffin block, and compare sections processed alike before attributing signal differences to biology (standard IHC practice). If a poorly staining block also loses established control-antigen staining, investigate tissue preservation and retrieval before changing the IL23A antibody concentration (standard IHC practice). Include a positive tissue control alongside each run; non-germinal center cells in lymph node have reported high staining (HPA tissue IHC). Interpret absent staining cautiously when preservation or control performance is inadequate (standard IHC practice).
Should IL23A appear inside producing cells or outside them?
Expect predominantly cytoplasmic staining in subsets of immune cells in tissue sections (HPA tissue IHC). IL23A has a signal peptide at residues 1–19, no transmembrane segment, and is secreted upon association with IL12B (UniProt Q9NPF7). Thus, cellular staining can identify a candidate producing population, while nearby extracellular signal may be difficult to assign to its source (UniProt Q9NPF7; standard IHC interpretation). Examine the cell outline and adjacent unstained structures at high magnification before calling diffuse chromogen a positive cell (standard IHC practice). IL23A staining alone does not establish that the disulfide-linked IL23A–IL12B heterodimer is present (UniProt Q9NPF7 subunit annotation).
Could processing or isoforms explain discordant IL23A IHC results?
No IL23A isoforms, glycosylation sites, modified residues, or domains are annotated in the supplied record (UniProt Q9NPF7). The precursor contains a signal peptide at residues 1–19 and a mature chain at 20–189 (UniProt Q9NPF7 processing). Check the catalog antibody’s documented immunogen or epitope before assuming that staining detects the mature secreted chain (standard antibody validation practice). An epitope near a processed region could affect interpretation, but its location and accessibility are unspecified here (UniProt Q9NPF7 processing; evidence limitation). Compare an independent epitope reagent or an appropriate specificity control when staining patterns disagree (standard IHC practice).
How should I investigate IL23A localisation with multiplex IF?
For a separate IF experiment, pair IL23A with a validated marker for dendritic or phagocytic cells, which can produce IL23A (UniProt Q9NPF7 tissue specificity). Choose a fluorophore channel with low tissue autofluorescence and inspect unstained and single-label controls before interpreting overlap (standard IF practice). For a cytosolic epitope, use controlled permeabilisation; for an accessible extracellular epitope, assess staining without permeabilisation, since epitope location is unspecified (HPA subcellular; UniProt Q9NPF7 topology; standard IF practice). The HPA reports approved cytosolic localisation in ICC/IF, while tissue IHC chiefly shows cytoplasmic immune-cell subsets (HPA subcellular; HPA tissue IHC). Fluorescent overlap alone cannot establish IL-23 heterodimer formation (UniProt Q9NPF7 subunit annotation).
What should I check when IL23A chromogen appears throughout the section?
First compare a no-primary control and inspect whether the diffuse colour follows tissue folds, edges, or damaged regions (standard IHC practice). The documented tissue example used 10% serum blocking for 1 hour at room temperature and an HRP secondary at 1:250 (A01097 tissue-IHC caption). Verify peroxidase blocking and control chromogen development time, because endogenous enzyme activity or overdevelopment can mimic specific staining (standard chromogenic IHC practice). Reassess primary concentration against the documented 5 µg/ml condition if background persists (A01097 tissue-IHC caption; standard IHC practice). Presumed off-target tissue binding has been observed, so morphology and controls matter (HPA tissue IHC).
How should I score IL23A staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the viable region and cell population before scoring, because reported tissue staining is mainly cytoplasmic in immune-cell subsets (HPA tissue IHC; standard IHC practice). Record the percentage of positive cells and intensity, or calculate an H-score as 1 × weak% + 2 × moderate% + 3 × strong% (standard IHC scoring practice). If counting positive cells, report density per mm² of viable tissue and, where relevant, the fraction among the assessed immune cells (standard IHC quantification practice). Use the same threshold, retrieval, exposure, and counterstain rules across samples (standard IHC practice). Include control-section performance when comparing runs (standard IHC practice).
Which IL23A staining patterns warrant a specificity check?
Give greatest weight to cytoplasmic signal in morphologically plausible immune-cell subsets, consistent with the reported tissue pattern (HPA tissue IHC). Strong nuclear-only staining warrants scrutiny because the approved subcellular location is cytosol and IL23A has no transmembrane segment (HPA subcellular; UniProt Q9NPF7 topology). Check unexpected positive cell types against matched controls rather than assuming every nonimmune cell is negative; presumed off-target binding has been observed (HPA tissue IHC). Discount edge staining, necrotic debris, and colour reproduced in the no-primary control or after inadequate peroxidase blocking (standard chromogenic IHC practice). A convincing signal still identifies IL23A antigen, not necessarily secreted functional IL-23 (UniProt Q9NPF7 subunit annotation).
Boster reagents

Best IL23A / Interleukin-23 subunit alpha IHC Antibodies

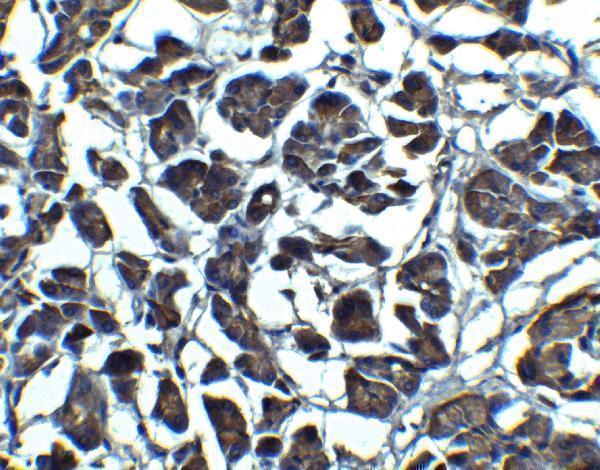
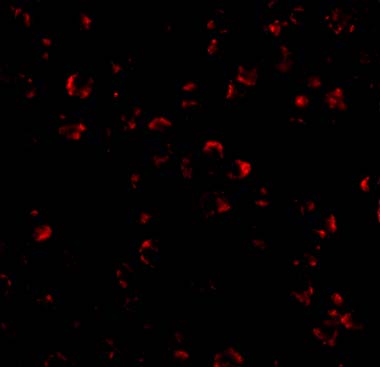
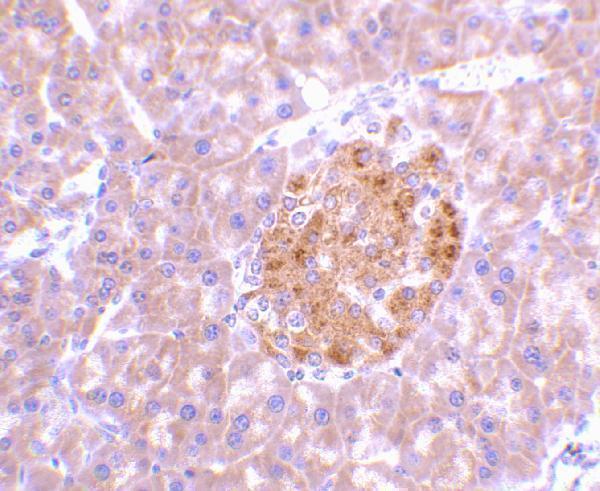
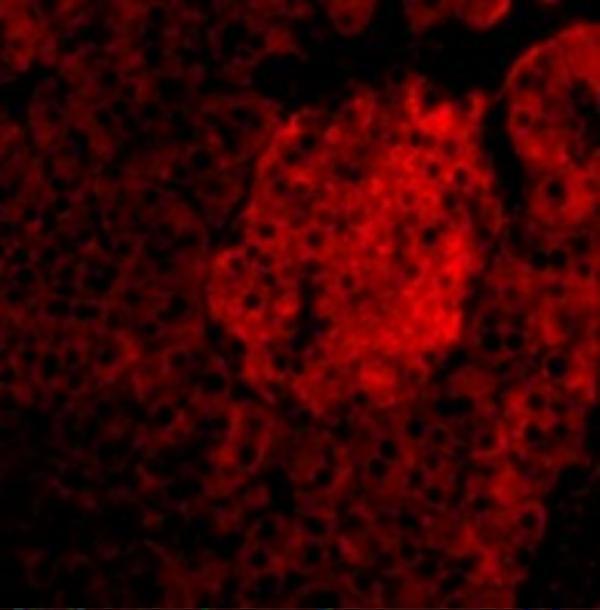
The catalog antibodies have IHC images from human and mouse pancreas and IF images from human Raji cells and human and mouse pancreas (catalog image captions).

Real IHC data Immunohistochemistry Validation of IL-23 in Human Pancreas Tissue Immunohistochemical analysis of paraffin-embedded human pancreas tissue using anti-IL-23 antibody (A01097) at 5 μg/ml. Tissue was fixed with formaldehyde and blocked with 10% serum for 1 h at RT; antigen retrieval was by heat mediation with a citrate buffer (pH6). Samples were incubated with primary antibody overnight at 4˚ C. A goat anti-rabbit IgG H&L (HRP) at 1/250 was used as secondary. Counter stained with Hematoxylin.
Anti-IL-23 Antibody
Cat # A01097
Real IHC data Immunohistochemistry Validation of IL-23 in Mouse Pancreas Tissue Immunohistochemical analysis of paraffin-embedded mouse pancreas tissue using anti-IL-23 antibody (A01097-2) at 2 μg/ml. Tissue was fixed with formaldehyde and blocked with 10% serum for 1 h at RT; antigen retrieval was by heat mediation with a citrate buffer (pH6). Samples were incubated with primary antibody overnight at 4˚ C. A goat anti-rabbit IgG H&L (HRP) at 1/250 was used as secondary. Counter stained with Hematoxylin.
Anti-IL-23 Antibody
Cat # A01097-2

A01097 has IHC-P validation in human pancreas and IF validation in Raji cells and human pancreas (A01097 image captions). A01097-2 has IHC-P validation in mouse pancreas and IF validation in mouse pancreas; its listed reactivity includes human and mouse (A01097-2 image captions; catalog reactivity).

Which to pick: For human tissue IHC, choose A01097: its image shows formaldehyde-fixed paraffin sections stained at 5 μg/mL; for mouse tissue IHC, choose A01097-2, whose corresponding image uses 2 μg/mL (respective IHC image captions). For IF/ICC, choose A01097 when ICC is required because it lists both applications; A01097-2 lists IF but not ICC (catalog applications). A01097-2 lists human and mouse reactivity, though its supplied IHC and IF images show mouse samples; both antibodies are rabbit-hosted, and neither has a reported clone (catalog reactivity, image captions, host and clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NPF7 (IL23A_HUMAN, Interleukin-23 subunit alpha).
  2. Human Protein Atlas. IL23A tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. IL23A subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. IL23A antibody validation summary (1 antibodies).
  5. Identification and Validation of a Six Immune-Related Genes Signature for Predicting Prognosis in Patients With Stage II Colorectal Cancer. Frontiers in genetics 2021 — PMC8129521.
  6. Blocking IL-23 Signaling Mitigates Cigarette Smoke-Induced Murine Emphysema. Environmental toxicology 2024 — PMC11567802.
  7. Cytokine RNA In Situ Hybridization Permits Individualized Molecular Phenotyping in Biopsies of Psoriasis and Atopic Dermatitis. JID innovations : skin science from molecules to population health 2021 — PMC8659380.
  8. Role of macrophage CCAAT/enhancer binding protein delta in the pathogenesis of rheumatoid arthritis in collagen-induced arthritic mice. PloS one 2012 — PMC3454428.
  9. PubMed PMID:11114383 — UniProt-cited evidence.
  10. PubMed PMID:12975309 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.