MAST2 / Microtubule-associated serine/threonine-protein kinase 2 · IHC design guide

Design Immunohistochemistry for MAST2

Plan MAST2 staining in paraffin sections using the catalog antibody at 1:100–1:300 (datasheet). Expect general cytoplasmic staining (HPA tissue IHC), but interpret intensity cautiously because antibody staining has low consistency with RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MAST2 (IHC for MAST2): expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A07003-2, validated IHC image, and IHC protocol steps
Printable MAST2 IHC protocol sheet — expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A07003-2, controls and protocol steps. Open the full MAST2 IHC guide →

MAST2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining in glandular and neuronal cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep section fixation consistent. (standard IHC practice; not target-specific)
Caveat Antibody staining has low consistency with RNA expression (HPA tissue IHC)
Regulation Expression regulation is not specified (UniProt)
Isoform / epitope Two isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended MAST2 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with one published MAST2 IHC protocol using paraffin sections (PMC3661464).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet A07003-2)
FixationImage fixative and duration unreported (datasheet A07003-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-MAST2, 1:100-1:300 (datasheet A07003-2)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMAST2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteTry citrate pH 6.0 HIER at 95–98 °C for 20 min first (page antigen retrieval; UniProt Q6P0Q8: cytoplasmic and membrane localisation).
Section 2

What Is the Expected MAST2 Staining Pattern?

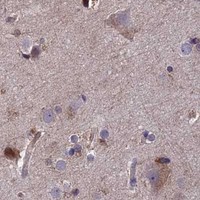
In paraffin IHC, expect mainly cytoplasmic staining in glandular, respiratory epithelial, neuronal, Purkinje, and endothelial cells listed as medium-positive by HPA (HPA tissue IHC). A submembranous component is plausible when MAST2 interacts with CDHR2, although MAST2 has no transmembrane segment (UniProt Q6P0Q8 localisation and topology). HPA rates the tissue staining Approved but reports low consistency with RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic signal in bronchial respiratory epithelium or cerebellar Purkinje cells (HPA tissue IHC).This fits the reported compartment and cell types; HPA records medium staining in both examples (HPA tissue IHC). Score the relevant cells rather than treating every cell in the section as equally positive (general IHC practice).
Strong, predominantly nuclear staining with little cytoplasmic signal (HPA tissue IHC; HPA subcellular ICC-IF).That distribution conflicts with HPA's general cytoplasmic IHC profile and approved cytosolic ICC-IF localisation (HPA tissue IHC; HPA subcellular ICC-IF). Check controls and detection conditions before assigning it to MAST2 (general IHC practice).
Prominent staining of adipocytes or ovarian stroma cells (HPA tissue IHC).HPA reports these cell types as not detected; unexpected signal may reflect cross-reactivity or endogenous detection activity (HPA tissue IHC; general IHC practice). Compare a no-primary control and assess the precise cell type stained (general IHC practice).
Diffuse colour across cells and tissue spaces, without a clear cytoplasmic pattern (HPA tissue IHC).A distribution that obscures cell boundaries is difficult to reconcile with HPA's cytoplasmic profile (HPA tissue IHC). Background from detection reagents or inadequate washing is possible; inspect controls before scoring (general IHC practice).
No signal in bronchial respiratory epithelium or cerebellar Purkinje cells (HPA tissue IHC).HPA reports medium staining in these cells, so an absent signal warrants a technical check, but one section does not establish loss of MAST2 (HPA tissue IHC; general IHC practice). Review tissue integrity, antibody use, retrieval, and detection controls (general IHC practice).
💡Expected MAST2 appearanceCall a result positive when the relevant HPA-listed cells show chiefly cytoplasmic, approximately medium staining; dominant nuclear signal or strong staining of HPA-negative adipocytes is suspect (HPA tissue IHC; HPA subcellular ICC-IF).
How each factor affects the staining
Tissue evidence and confidence (HPA tissue IHC)HPA lists several medium-positive cell types, but its Approved tissue profile has low consistency with RNA expression (HPA tissue IHC). Use the protein staining observations as a guide, with controls, rather than converting RNA abundance into an IHC intensity prediction (general IHC practice).
Membrane proximity (UniProt Q6P0Q8 localisation and topology)MAST2 is cytoplasmic and cytoskeletal and can be recruited beneath the membrane through CDHR2 interaction; it has no transmembrane segment (UniProt Q6P0Q8). A limited peripheral component can fit this biology, while a membrane-only pattern needs independent support (UniProt Q6P0Q8; general IHC practice).
Antibody and isoform coverage (HPA antibodies; UniProt Q6P0Q8 isoforms)HPA lists HPA039722 and HPA040155 as IHC Approved, while UniProt lists two isoforms (HPA antibodies; UniProt Q6P0Q8). No epitope or isoform coverage is supplied here, so staining differences cannot be assigned to a particular isoform from this record alone.
IF/ICC Q&A: where should signal appear? (HPA subcellular ICC-IF)In ICC-IF, HPA reports approved cytosolic localisation; images are listed for A-431, U-251MG, and U2OS (HPA subcellular ICC-IF). HPA039722 has Uncertain ICC validation, so its IHC Approved status does not establish dependable ICC performance (HPA antibodies).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Cytoplasmic staining is weak in an HPA medium-positive cell type (HPA tissue IHC).Low signal may reflect assay conditions or biological variation; HPA's low antibody–RNA consistency limits confidence in any single expected intensity (HPA tissue IHC; general IHC practice).Check tissue integrity and detection controls, then review the catalog antibody's IHC-P conditions and optimise retrieval or antibody concentration within that protocol (general IHC practice).
Nuclei dominate while cytoplasm is faint (HPA tissue IHC; HPA subcellular ICC-IF).The pattern conflicts with reported cytoplasmic and cytosolic localisation; nonspecific staining or detection background is possible (HPA tissue IHC; HPA subcellular ICC-IF; general IHC practice).Inspect the no-primary control, reassess antibody concentration and washing, and compare with the expected cytoplasmic cells on the same slide (general IHC practice; HPA tissue IHC).
Adipocytes or ovarian stroma appear strongly positive (HPA tissue IHC).Both are recorded as not detected; cross-reactivity or endogenous detection activity may produce misleading colour (HPA tissue IHC; general IHC practice).Verify cell identity and examine a no-primary control; review endogenous enzyme blocking if using an enzyme-based chromogenic detection system (general IHC practice).
Colour is diffuse across the section (HPA tissue IHC).Diffuse deposit can obscure the general cytoplasmic profile and may arise from background in the staining workflow (HPA tissue IHC; general IHC practice).Compare no-primary and tissue controls, inspect wash steps and detection reagent background, then score only cells with interpretable localisation (general IHC practice).
All cells, including an HPA medium-positive reference cell type, are unstained (HPA tissue IHC).A failed staining run is possible, although HPA's Approved rating with low RNA consistency means an individual specimen is not a guaranteed positive control (HPA tissue IHC; general IHC practice).Confirm the reference cells are present, check reagent and detection performance with a working control, and review the catalog antibody's IHC-P protocol (general IHC practice).
A peripheral rim appears beside otherwise cytoplasmic staining (UniProt Q6P0Q8 localisation).CDHR2-dependent recruitment can place MAST2 beneath the membrane, but UniProt reports no transmembrane segment (UniProt Q6P0Q8 localisation and topology).Check whether cytoplasmic signal remains in the relevant cells and whether controls are clean; describe a peripheral component without calling MAST2 a transmembrane marker (UniProt Q6P0Q8; general IHC practice).

Sample controls for MAST2 IHC & IF

🧪Run bronchus first: respiratory epithelial cells show Medium MAST2 staining (HPA: bronchus, respiratory epithelial cells, Medium). Use adipose tissue as the negative comparison because adipocytes are Not detected (HPA: adipose tissue, adipocytes, Not detected); on the bronchus slide, cells confirmed to be negative should show counterstain without specific chromogen, since the HPA row does not establish which neighboring cells are negative (HPA: bronchus row).
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MAST2 in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a species- and class-matched isotype control for a monoclonal antibody or matched nonimmune IgG for a polyclonal antibody; and MAST2 knockout material or cognate peptide competition when available (standard IHC controls). Quench endogenous peroxidase and check bronchial mucus for deposited chromogen before scoring epithelial staining (standard chromogenic IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A07003-2 paraffin-section caption does not state a fixative (selected tissue-IHC caption). Retrieval dependence is unreported, so assess standard antigen-retrieval conditions with the positive and negative controls (supplied target/application evidence; standard IHC practice). HPA ICC-IF images in A-431, U-251MG and U2OS show cytosolic localization, but do not establish that IF or frozen sections are easier than paraffin IHC; bronchial mucus can produce misleading surface deposits in chromogenic staining (HPA: subcellular; standard IHC practice).

HPA tissue IHC evidence for MAST2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Caudate Neuronal cells Medium Protein (IHC) HPA →
Cerebellum Purkinje cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Section 3

Advanced MAST2 IHC Tips

Troubleshoot MAST2 staining in paraffin sections by checking retrieval, cellular pattern, controls and scoring before interpreting differences between samples.

What retrieval should I try first when MAST2 staining is weak in paraffin sections?
Start with citrate buffer at pH 6.0 for heat induced epitope retrieval at 95–98 °C for 20 minutes (page retrieval rule: cytoplasmic / membrane antigen). Allow sections to cool in buffer before washing, and process comparison sections in the same run (standard IHC practice). If staining remains weak, compare a longer or shorter retrieval time on adjacent sections while holding antibody dilution and detection constant (standard IHC practice). Check that any gain is cellular rather than diffuse, because MAST2 is reported in the cytoskeleton and cytosol (UniProt Q6P0Q8 subcellular location; HPA: approved cytosol).
Could fixation explain weak or patchy MAST2 staining?
MAST2 specific sensitivity to fixation is unknown from the supplied evidence; the selected image describes paraffin embedded human lung cancer but does not state its fixative (A07003-2 caption). Record the fixative, fixation duration and processing history before comparing sections, because these variables can change antigen accessibility in chromogenic IHC (standard IHC practice). If archival blocks differ, stain adjacent sections from each block in the same run and compare morphology alongside signal (standard IHC practice). Avoid assigning a weak result to MAST2 phosphorylation or membrane association without a controlled comparison, even though both are documented protein features (UniProt Q6P0Q8 modified residues and subcellular location).
Where should convincing MAST2 staining appear within a cell?
Prioritise a cytoplasmic pattern: tissue IHC reports general cytoplasmic expression, and cell imaging assigns MAST2 to the cytosol (HPA: tissue profile; HPA: approved cytosol). A peripheral component can be plausible because interaction with CDHR2 recruits MAST2 to a submembranous area (UniProt Q6P0Q8 subcellular location). MAST2 has no transmembrane segment, so a crisp surface outline alone needs corroboration before being called specific staining (UniProt Q6P0Q8 topology; standard IHC interpretation). Compare the putative pattern with cell morphology, a no primary antibody control and a second validated reagent where available (standard IHC practice).
How should isoforms and epitope placement affect antibody choice?
MAST2 has 2 listed isoforms, so check the antibody’s immunogen against both sequences before treating all staining as total MAST2 (UniProt Q6P0Q8 isoforms; standard IHC practice). The kinase domain spans residues 512–785, the AGC kinase C terminal domain 786–854, and the PDZ domain 1104–1192 (UniProt Q6P0Q8 domains). An epitope overlapping a splice difference could alter which isoform is detected, but the supplied caption does not identify the A07003-2 epitope (A07003-2 caption). If results disagree across antibodies, compare disclosed immunogen regions and cellular patterns on adjacent sections before attributing the difference to biology (standard IHC practice).
How can IF help assess a questionable MAST2 IHC pattern?
Use IF as a separate localisation check, with an epithelial marker when examining the bronchial respiratory epithelial cells reported as MAST2 positive (HPA: bronchus, medium staining; standard IF practice). Choose a red or far red fluorophore and inspect an unstained section, since tissue autofluorescence can obscure green signal (standard IF practice). Permeabilise sufficiently to expose a cytosolic epitope, because MAST2 is assigned to the cytosol and has no transmembrane segment (HPA: approved cytosol; UniProt Q6P0Q8 topology). Compare single label controls before interpreting overlap, and do not treat IF intensity as directly interchangeable with chromogenic IHC intensity (standard IF and IHC practice).
What should I check when the chromogen covers most of the section?
Inspect a no primary antibody control to separate detection background from antibody dependent staining (standard IHC practice). Quench endogenous peroxidase before an HRP and DAB workflow, and check whether pigment or necrotic material persists in the control (standard chromogenic IHC practice). Reduce antibody concentration or incubation strength if diffuse signal remains; the selected paraffin section image reports A07003-2 at 1:100, which is a reference point rather than a universal optimum (A07003-2 caption; standard IHC practice). Retain morphology and a cytoplasmic pattern when judging improvements, because general cytoplasmic staining is reported for MAST2 (HPA: tissue profile).
How should I score MAST2 staining across different sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and scoring area before reviewing chromogen intensity, then exclude folds, edges and necrotic regions (standard IHC practice). For cellular staining, record the percentage of positive cells and an H-score from 0–300 using intensity categories 0–3 (standard IHC scoring practice). Normalise counts to the number of eligible cells, or report positive cell density per mm² when cell counting is the endpoint (standard IHC quantification practice). Score cytoplasmic and peripheral signal separately if both appear, since cytosolic localisation and CDHR2 associated submembranous recruitment are reported (HPA: approved cytosol; UniProt Q6P0Q8 subcellular location).
When is apparent MAST2 positivity likely to be an artefact?
A credible result should show cellular cytoplasmic staining with morphology that fits the scored population (HPA: general cytoplasmic expression; standard IHC interpretation). Treat isolated nuclear staining or a surface only outline cautiously, since the supplied localisation evidence favours cytosol and submembranous recruitment rather than a transmembrane protein (HPA: approved cytosol; UniProt Q6P0Q8 topology). Check edge concentrated colour, necrotic regions and signal in a no primary antibody control for processing artefact or endogenous enzyme activity (standard chromogenic IHC practice). Interpret tissue differences cautiously because HPA rates its MAST2 tissue staining approved but reports low consistency with RNA expression (HPA: tissue IHC reliability).
Boster reagents

Best MAST2 / Microtubule-associated serine/threonine-protein kinase 2 IHC Antibodies

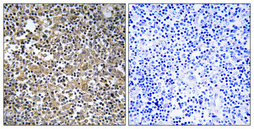
A07003-2 has an IHC image from paraffin-embedded human lung cancer (catalog image caption). IF is listed as an application, and human and mouse are listed as reactive species (catalog applications and reactivity).

Real IHC data Immunohistochemistry validation of MAST2 using Anti-MAST205 Antibody (A07003-2). Immunohistochemical analysis of paraffin-embedded human lung cancer. Antibody was diluted at 1:100 (4°C
Anti-MAST205 Antibody
Cat # A07003-2

A07003-2 has an IHC image from paraffin-embedded human lung cancer (catalog image caption). IF is listed for A07003-2, but no IF image is supplied; human and mouse are listed as reactive species (catalog applications and reactivity).

Which to pick: Choose A07003-2 for paraffin-section IHC because its own image documents that preparation in human lung cancer; the fixative is unreported (catalog image caption). For IF/ICC, A07003-2 lists IF, though the payload supplies no IF image or ICC validation (catalog applications and image alts). A07003-2 is polyclonal and lists human and mouse reactivity, but its IHC image documents human tissue only (catalog dilution_raw, reactivity, and image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q6P0Q8 (MAST2_HUMAN, Microtubule-associated serine/threonine-protein kinase 2).
  2. Human Protein Atlas. MAST2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. MAST2 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. MAST2 antibody validation summary (2 antibodies).
  5. A functional yeast survival screen of tumor-derived cDNA libraries designed to identify anti-apoptotic mammalian oncogenes. PloS one 2013 — PMC3661464.
  6. Mutations in MAST1 Cause Mega-Corpus-Callosum Syndrome with Cerebellar Hypoplasia and Cortical Malformations. Neuron 2018 — PMC6436622.
  7. PubMed PMID:12117771 — UniProt-cited evidence.
  8. PubMed PMID:16710414 — UniProt-cited evidence.
  9. PubMed PMID:15489334 — UniProt-cited evidence.