This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
For human paraffin sections, use the IHC-validated antibody at 2–5 μg/ml for chromogenic NUDCD1 staining (datasheet A10778-1). Assess cytoplasmic and nuclear staining, including high levels in smooth muscle cells, while accounting for uncertain tissue-IHC reliability (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic and nuclear tissue staining (HPA tissue IHC) | |
| Staining pattern | High smooth muscle staining, cytoplasmic and nuclear (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A10778-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation conditions consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Antibody staining has low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | Isoform 2 is predominantly expressed in testis (UniProt) | |
| Isoform / epitope | 3 isoforms; epitope coverage is unspecified (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by published NUDCD1 staining methods for colorectal tissue and paraffin sections (PMC9476325; PMC8351729).
| Sample | Paraffin-embedded human lung cancer tissue; fixative not specified (datasheet A10778-1) |
| Fixation | Image fixative and duration unreported (datasheet A10778-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A10778-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A10778-1) |
| Primary antibody | Rabbit anti-NUDCD1, 2-5 μg/ml (datasheet A10778-1) |
| Primary incubation | Overnight at 4 °C (datasheet A10778-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A10778-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | NUDCD1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic and nuclear expression in several tissues, high levels in smooth muscle cells. No signal in the no-primary control. |
NUDCD1 is reported in the cytoplasm and nucleus and has no transmembrane segment (UniProt Q96RS6 topology and subcellular location). In tissue IHC, expect staining in smooth muscle cells and in several glandular, glial, and kidney tubular cell populations (HPA: tissue IHC). Treat this as a provisional pattern: HPA rates the tissue IHC evidence Uncertain because antibody staining and RNA expression show low consistency (HPA: tissue reliability).
| Smooth muscle cells stain strongly, while selected glandular cells, glia, or kidney tubular cells show more moderate nuclear and cytoplasmic staining (HPA: tissue IHC). | This fits the reported tissue distribution and compartments (HPA: tissue IHC; UniProt Q96RS6 subcellular location). Record the cell type and compartment separately: a positive field should not be reduced to a single whole-section intensity score (general IHC practice). |
| The dominant signal outlines cell borders or appears confined to a membrane, with little intracellular staining. | A membrane-only pattern conflicts with the reported nuclear and cytoplasmic distribution and the absence of a transmembrane segment (UniProt Q96RS6 topology and subcellular location). Check morphology, detection controls, and antibody specificity before assigning it to NUDCD1 (general IHC practice). |
| Adipocytes, esophageal squamous epithelium, or prostatic glandular cells stain prominently. | HPA lists these specific cell populations as not detected by tissue IHC (HPA: adipose tissue, esophagus, prostate). Prominent staining warrants review for cross-reactivity or endogenous detection activity (general IHC practice); HPA's uncertain reliability prevents calling every such focus definitively false (HPA: tissue reliability). |
| Color spreads across tissue structures, blank areas, or multiple unrelated cell types without clear cellular boundaries. | This is difficult to interpret as the reported compartment-specific pattern (HPA: tissue IHC). Diffuse signal can arise from background staining or detection chemistry (general IHC practice); compare a no-primary control and assess whether staining follows identifiable cells (general IHC practice). |
| No staining appears in smooth muscle cells or in HPA-reported medium-level cell populations. | An absent signal in those populations conflicts with the reported IHC observations (HPA: tissue IHC), but it does not alone prove target absence. Review section quality and assay controls, then optimize general IHC conditions before interpreting a negative result (general IHC practice). |
| Compartment and topology (UniProt Q96RS6 subcellular location and topology) | NUDCD1 is annotated in nucleus and cytoplasm, without a transmembrane segment (UniProt Q96RS6). Score intracellular signal by compartment; a membrane-only pattern needs independent verification (general IHC practice). |
| Cell-specific reference pattern (HPA: tissue IHC) | HPA reports high staining in smooth muscle cells and medium staining in listed glandular cells, glia, and kidney tubular cells (HPA: tissue IHC). Its listed negative cell populations are useful comparison regions, subject to the Uncertain reliability rating (HPA: tissue reliability). |
| Isoform expression (UniProt Q96RS6 tissue specificity) | Isoform 1 is reported in leukemias, various solid tumor cell lines, testis, and heart; isoform 2 is predominant in testis and weak in tumor cells (UniProt Q96RS6 tissue specificity). The supplied record does not establish which isoforms an IHC antibody detects; avoid isoform-specific conclusions from staining alone. |
| Antibody validation (HPA: HPA023183) | HPA labels this antibody's IHC result Uncertain, while its ICC result is Supported (HPA: HPA023183). Keep those application-specific assessments distinct when judging tissue sections; an ICC validation label does not resolve the tissue IHC uncertainty (HPA: antibody validation; tissue reliability). |
| Q: What should IF/ICC show? A: Mainly nucleoplasmic signal, with additional cytosolic signal (HPA: subcellular ICC-IF). | The supported ICC-IF localization is nucleoplasm plus cytosol (HPA: subcellular ICC-IF). Use it as a compartment comparison only; tissue IHC retains its separate Uncertain reliability rating (HPA: tissue reliability). |
| Situation | Likely cause | Next action |
|---|---|---|
| A positive-looking field shows only membrane outlines. | The pattern conflicts with the annotated nuclear and cytoplasmic location and lack of a transmembrane segment (UniProt Q96RS6). | Inspect cellular morphology and compare a no-primary control; confirm the compartment with an independent specificity check before scoring NUDCD1 (general IHC practice). |
| Strong color appears in adipocytes, esophageal squamous cells, or prostatic glands. | Those cell populations are listed as not detected in HPA tissue IHC (HPA: adipose tissue, esophagus, prostate); cross-reactivity or endogenous activity is possible (general IHC practice). | Run a no-primary control and check whether the signal is cell-bound and reproducible (general IHC practice). Interpret discordance cautiously because HPA tissue reliability is uncertain (HPA: tissue reliability). |
| The entire section has diffuse brown background. | Nonspecific binding or endogenous enzyme activity can obscure cell-specific chromogenic staining (general IHC practice). | Compare no-primary and detection controls; review blocking, washes, and chromogen development, then reassess nuclear and cytoplasmic boundaries (general IHC practice; UniProt Q96RS6 subcellular location). |
| A section expected to contain smooth muscle cells has no detectable signal. | HPA reports high staining in smooth muscle cells, so a blank section may reflect assay performance or sampling (HPA: tissue IHC; general IHC practice). | Confirm that the relevant cells are present, inspect a positive control section, and review retrieval and detection settings using standard IHC controls (general IHC practice). Do not infer NUDCD1-specific fixation sensitivity from this result. |
| Only one intracellular compartment stains in tissue IHC. | HPA tissue IHC describes nuclear and cytoplasmic expression, but its evidence is uncertain (HPA: tissue profile and reliability); a single compartment is therefore a discrepancy to assess, not a definitive failure. | Score nucleus and cytoplasm separately, review counterstain and section morphology, and compare an independent antibody or orthogonal result if available (general IHC practice). |
| ICC-IF looks convincing, but the paraffin-section IHC pattern remains ambiguous. | The antibody has supported ICC and uncertain IHC validation, which are different application assessments (HPA: HPA023183). | Use the ICC-IF nucleoplasm and cytosol pattern as a localization reference (HPA: subcellular ICC-IF); resolve tissue IHC with tissue-specific controls and cautious scoring (general IHC practice; HPA: tissue reliability). |



Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Breast | Myoepithelial cells | Medium | Protein (IHC) | HPA → |
| Caudate | Glial cells | Medium | Protein (IHC) | HPA → |
| Cerebral cortex | Glial cells | Medium | Protein (IHC) | HPA → |
| Colon | Glandular cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
| Oral mucosa | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot NUDCD1 staining in paraffin sections by checking retrieval, compartment, cell type and assay controls before interpreting chromogenic signal.
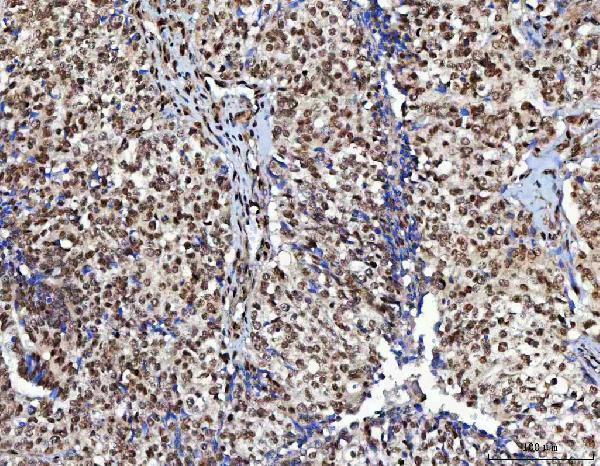
A10778-1 has IHC images from human paraffin-embedded lung and ovarian cancer sections and an IF image from HELA cells (catalog: IHC/IF captions).
A10778-1 will render with its IHC figure from a human paraffin-embedded lung cancer section (catalog: card figure caption). Its additional IHC caption documents human ovarian cancer tissue, and its IF caption documents HELA cells (catalog: IHC/IF captions).
Which to pick: Choose A10778-1 for human paraffin-section IHC: its caption documents EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody (catalog: IHC caption); the fixative is unreported (catalog: IHC caption). For IF/ICC, the same SKU has an IF image from HELA cells at 5 μg/ml (catalog: IF caption). Human, mouse and rat are listed as reactive species, but the supplied IHC and IF images document human samples only; clonality is unspecified (catalog: reactivity, IHC/IF captions, clone field).