NUDT7 / Peroxisomal coenzyme A diphosphatase NUDT7 · IHC design guide

Design Immunohistochemistry for NUDT7

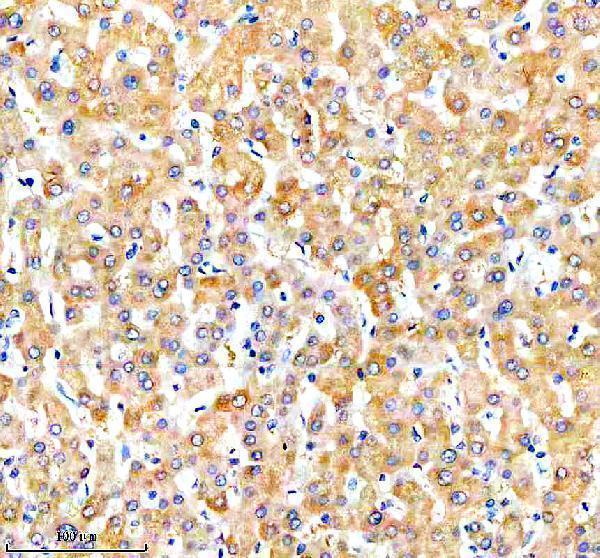
Plan NUDT7 IHC in paraffin sections around the often granular cytoplasmic tissue pattern (HPA tissue IHC). Human liver sections are shown with the catalog antibody at 2 μg/ml (datasheet A10663-1); assess staining against a matched control.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NUDT7 (IHC for NUDT7): expected localisation Granular cytoplasm (HPA tissue IHC); peroxisome (UniProt), antibody A10663-1, validated IHC image, and IHC protocol steps
Printable NUDT7 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); peroxisome (UniProt), antibody A10663-1, controls and protocol steps. Open the full NUDT7 IHC guide →

NUDT7 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); peroxisome (UniProt)
Staining pattern Often granular cytoplasmic staining across cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A10663-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep formalin fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Liver-enhanced RNA expression (HPA tissue RNA)
Isoform / epitope 3 isoforms; verify epitope coverage (UniProt)
Section 1

Recommended NUDT7 IHC & IF Protocols

The catalog antibody protocol is followed by published NUDT7 IHC methods for mouse colon tissue and tissue samples, including human samples (PMC7139971; PMC9523354).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver tissue; fixative not specified (datasheet A10663-1)
FixationImage fixative and duration unreported (datasheet A10663-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A10663-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A10663-1)
Primary antibodyRabbit anti-NUDT7, 2-5 μg/ml (datasheet A10663-1)
Primary incubationOvernight at 4 °C (datasheet A10663-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A10663-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNUDT7-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression, often with a granular pattern. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet A10663-1); citrate pH 6.0 in a pressure cooker is a published mouse-colon alternative (PMC7139971).
Section 2

What Is the Expected NUDT7 Staining Pattern?

NUDT7 is a peroxisomal protein with no transmembrane segment (UniProt P0C024). In paraffin-section IHC, expect cytoplasmic staining, often granular, with strong signal in kidney proximal tubules and several glandular cell populations (HPA: tissue IHC). HPA rates the tissue pattern Supported, with medium consistency between staining and RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Granular cytoplasmic staining in kidney proximal tubules, with weaker or absent staining in some neighboring cells.This fits the reported cytoplasmic, often granular tissue pattern and a High rating for proximal tubules (HPA: tissue IHC). Score intensity by cell population rather than calling the whole section uniformly positive (general IHC interpretation).
Strong nuclear staining dominates, with little cytoplasmic signal.This does not match the reported tissue-IHC pattern (HPA: ubiquitous cytoplasmic expression, often granular). Check controls before calling it specific. Nuclear signal alone cannot resolve the localisation question: HPA also reports approved nucleoplasmic staining in ICC-IF, while UniProt assigns NUDT7 to peroxisomes (HPA: subcellular; UniProt P0C024).
Adipocytes or bone-marrow hematopoietic cells stain as strongly as the chosen positive population.These populations are rated Not detected in HPA tissue IHC (HPA: adipocytes; bone-marrow hematopoietic cells). Investigate cross-reactivity or chromogenic detection background; an unexpected positive is a warning, not proof of either cause (general IHC interpretation).
Diffuse color covers cells, extracellular spaces, and the section edge without a clear cellular pattern.That distribution is difficult to assign to NUDT7 because the reported pattern is cytoplasmic and often granular (HPA: tissue IHC). Review no-primary and detection-only controls for background, then reassess localisation only where cell boundaries are interpretable (general IHC practice).
No convincing cytoplasmic staining appears in kidney proximal tubules on an otherwise interpretable section.This conflicts with a High HPA rating for that cell population (HPA: kidney proximal tubules). Treat the run as inconclusive until the antibody, detection controls, and general paraffin-IHC workflow have been checked; one negative section does not overturn the atlas pattern (general IHC interpretation).
💡Expected NUDT7 appearanceCall a positive result when identifiable kidney proximal tubules or HPA-listed High glandular cells show clear, often granular cytoplasmic signal (HPA: tissue IHC); widespread extracellular color or strong signal in HPA Not detected populations warrants a background check (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
Choice of comparison cellsKidney proximal tubules and glandular cells in adrenal gland, appendix, breast, duodenum, and gallbladder are rated High; adipocytes are rated Not detected (HPA: tissue IHC). Compare named cell populations rather than assigning one expected intensity to an entire organ (general IHC interpretation).
Strength of the reference patternHPA calls the tissue-IHC result Supported and reports medium agreement between antibody staining and RNA expression (HPA: tissue IHC reliability). Use its pattern as an interpretation reference while treating a single discordant section as a reason to investigate, not as a definitive biological exception.
Protein organisationNUDT7 has no transmembrane segment, signal peptide, or propeptide; its annotated chain spans residues 1–238 (UniProt P0C024). These annotations support an intracellular interpretation but do not identify the antibody epitope or establish how paraffin processing affects it.
Isoforms and antibody validationUniProt lists 3 isoforms (UniProt P0C024). The supplied HPA antibody HPA042042 is IHC Supported and ICC Approved (HPA: antibodies). Those labels do not establish which isoforms its staining detects or make the tissue-IHC result an IHC Enhanced validation.
IF/ICC Q: Should the IHC pattern be read as an IF localisation result?A: No direct one-to-one prediction follows. HPA reports mainly Golgi apparatus with additional nucleoplasm in ICC-IF, whereas its tissue IHC is often granular cytoplasm and UniProt annotates peroxisomes (HPA: subcellular; HPA: tissue IHC; UniProt P0C024). Interpret the assays with their own controls.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive comparison area has little or no signal.Kidney proximal tubules are rated High, so a blank result there raises a run-level question (HPA: kidney proximal tubules). The supplied sources do not identify a NUDT7-specific fixation or retrieval failure.Check section integrity and positive and detection controls; review the routine paraffin-IHC retrieval and detection steps before changing scoring (general IHC practice). Record any workflow change without claiming target-specific retrieval sensitivity.
The whole section has a weak, even chromogenic haze.A uniform haze lacks the cellular, often granular distribution reported for NUDT7 (HPA: tissue IHC). Non-specific reagent binding or endogenous detection activity are general IHC possibilities, not documented NUDT7 properties.Inspect no-primary and detection-only controls; check blocking, washes, and chromogen development under the laboratory's standard IHC workflow (general IHC practice). Reassess only after the background is separated from cellular signal.
Adipocytes or bone-marrow hematopoietic cells appear strongly positive.Both populations are rated Not detected in the supplied tissue profile (HPA: adipocytes; bone-marrow hematopoietic cells). Unexpected color can reflect cross-reactivity or detection background, but appearance alone cannot identify the mechanism.Compare the suspect cells with a High-rated population in the same run and inspect control sections (HPA: tissue IHC; general IHC practice). Report the discrepancy at cell-population level rather than reclassifying the tissue as wholly positive.
Nuclear color is stronger than cytoplasmic color in tissue IHC.The observed IHC reference pattern is cytoplasmic (HPA: tissue IHC). Approved nucleoplasmic ICC-IF staining exists, so nuclear color is a localisation discrepancy requiring assessment, not automatic proof of artefact (HPA: subcellular).Check no-primary controls and cell boundaries, then score nuclear and cytoplasmic signal separately (general IHC practice). Describe the discordance alongside the HPA IHC and ICC-IF observations without treating either assay as a substitute for the other.
Only a smooth cytoplasmic wash is visible where granular staining was expected.HPA describes cytoplasmic expression as often granular, which permits some variation but gives no basis to assign featureless diffuse color to NUDT7 by itself (HPA: tissue IHC).Compare cell-level signal with the run's negative controls and High-rated proximal tubules (HPA: kidney proximal tubules; general IHC practice). Score the result as uncertain if background prevents a reliable cellular call.
A low-staining brain region is used to judge whether the antibody worked.HPA rates cells in the cerebellar molecular layer and hippocampal glia Low, and UniProt describes brain expression as weak (HPA: tissue IHC; UniProt P0C024). A faint result there is a poor stand-alone failure check.Use a High-rated cell population, such as kidney proximal tubules, to assess the run, and keep the brain observation separate in the record (HPA: tissue IHC; general IHC practice).

Sample controls for NUDT7 IHC & IF

🧪Run breast tissue first and score its glandular cells for staining (HPA: High in breast glandular cells). Run adipose tissue as the negative control (HPA: adipocytes Not detected); adipocytes within the breast section, if present, should remain at background (HPA: adipocytes Not detected).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NUDT7 in Hep-G2, MCF-7, U2OS, with annotated localisation: Golgi apparatus (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control (selected A10663-1 caption: rabbit primary at 2 μg/ml). Use NUDT7 knockout material as a biological specificity control, and quench endogenous peroxidase before chromogenic detection (selected A10663-1 caption: HRP/DAB detection).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A10663-1 tissue-IHC caption does not state the fixative (selected A10663-1 caption: fixative unreported). The paraffin-section example uses heat retrieval in EDTA at pH 8.0; it does not establish that retrieval is required (selected A10663-1 caption). Neither frozen sections nor IF/ICC is established as easier by the supplied evidence; assess adipocyte staining cautiously because lipid vacuoles leave little cytoplasm to score (HPA: adipocytes Not detected; standard IHC practice).

HPA tissue IHC evidence for NUDT7

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Ciliated cells (cell body) High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Soft tissue Peripheral nerve Not detected Protein (IHC) HPA →
Section 3

Advanced NUDT7 IHC Tips

Use the catalog antibody’s liver section as an IHC reference, then assess cytoplasmic staining alongside cell identity and tissue preservation (datasheet A10663-1; HPA: tissue profile).

What retrieval condition should I start with for weak NUDT7 staining in paraffin sections?
Start with heat-mediated EDTA retrieval at pH 8.0 for paraffin sections (datasheet A10663-1). The selected liver image used this condition, followed by 10% goat serum and 2 μg/ml primary antibody overnight at 4°C (datasheet A10663-1). If signal is weak, compare retrieval exposure on serial sections while holding antibody concentration, detection, and section thickness constant (standard IHC practice). Assess tissue preservation alongside granular cytoplasmic staining, since damaged morphology makes puncta harder to judge (standard IHC practice; HPA: granular cytoplasmic profile). Treat another buffer or pH as a documented fallback after evaluating the EDTA baseline (standard IHC practice).
Could fixation explain weak or uneven NUDT7 staining?
Target-specific sensitivity to fixation is unknown: the selected paraffin-section caption does not state a fixative (datasheet A10663-1). Record the fixative, fixation duration, processing schedule, and section age for each specimen before comparing staining across blocks (standard IHC practice). Use similarly processed serial sections to distinguish a block-specific loss of signal from an assay-wide problem, with the catalog antibody’s liver condition as a reference (standard IHC practice; datasheet A10663-1). Do not infer a NUDT7 fixation effect from its peroxisomal annotation or reported tissue staining (UniProt P0C024: peroxisome; HPA: tissue profile). If morphology is poor, resolve processing quality before interpreting staining intensity (standard IHC practice).
How should I judge cytoplasmic, peroxisomal, or nuclear NUDT7 staining?
Expect a predominantly cytoplasmic, often granular IHC pattern when evaluating tissue sections (HPA: tissue profile). NUDT7 is annotated as peroxisomal and has no transmembrane segment, so a punctate cytoplasmic pattern is biologically plausible, although chromogenic IHC alone cannot assign individual puncta to peroxisomes (UniProt P0C024: localisation and topology; standard IHC practice). The HPA cell imaging record instead reports mainly Golgi localisation with additional nucleoplasmic localisation (HPA: subcellular profile). Evaluate nuclear or compact perinuclear staining against cytoplasmic staining, morphology, and controls rather than dismissing it automatically (HPA: subcellular profile; standard IHC practice). Record the compartment scored so these distinct localisation records remain visible in the interpretation (standard IHC practice).
Could splice variants or epitope access change my IHC result?
NUDT7 has 3 annotated isoforms, but the supplied antibody caption does not identify its epitope or establish isoform coverage (UniProt P0C024: isoforms; datasheet A10663-1). Its annotated Nudix hydrolase domain spans residues 37–172, and one modified residue is N6-succinyllysine at position 20 (UniProt P0C024: domain and modified residues). These annotations do not establish whether either region is recognised by this antibody or altered by tissue processing (UniProt P0C024: annotations; datasheet A10663-1). If specimens disagree, compare matched sections under the same retrieval and detection conditions before proposing isoform-specific staining (standard IHC practice). Request epitope information or use an independently validated reagent if isoform discrimination is essential (standard IHC practice).
How can IF help resolve an ambiguous NUDT7 IHC pattern?
Use IF as a localisation follow-up to the chromogenic IHC result, with a cell-type marker appropriate to the section; a liver experiment can pair NUDT7 with a hepatocyte marker (datasheet A10663-1: liver IHC; standard IF practice). Choose spectrally separated fluorophores and inspect unstained tissue before selecting channels, since tissue autofluorescence can confound a weak signal (standard IF practice). NUDT7 has no transmembrane segment, but its antibody epitope and accessibility are unspecified; choose permeabilisation according to whether that epitope is exposed or lies behind a cellular or peroxisomal membrane (UniProt P0C024: topology and peroxisome; datasheet A10663-1). Compare marker overlap and punctate distribution with secondary-only controls, without transferring the 2 μg/ml IHC concentration directly to IF (standard IF practice; datasheet A10663-1).
What should I check when DAB background obscures NUDT7 staining?
First compare a primary-antibody omission control with the stained section to identify signal arising from detection reagents or tissue (standard IHC practice). The selected workflow used a peroxidase-conjugated secondary and DAB, making endogenous peroxidase blocking and controlled chromogen development relevant general IHC steps (datasheet A10663-1; standard IHC practice). Its liver section used 10% goat serum before 2 μg/ml primary antibody, providing a documented starting condition for that specimen (datasheet A10663-1). If background persists, adjust blocking, washing, primary concentration, or DAB development one variable at a time (standard IHC practice). Preserve enough counterstain to identify cells while checking whether apparent puncta follow tissue folds, edges, or damaged areas (standard IHC practice).
How should I quantify NUDT7 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and cytoplasmic compartment before scoring, because the reported tissue pattern is widespread and often granular (HPA: tissue profile; standard IHC practice). For comparable regions, report the percentage of positive cells and an H-score from staining intensity and positive-cell fraction; puncta density per mm² can complement those measures when individual granules remain resolvable (standard IHC practice). Normalise counts to viable tissue area or the number of eligible cells, and use identical thresholds and acquisition settings across sections (standard IHC practice). Exclude folds, edges, necrosis, and poorly preserved regions using preset criteria (standard IHC practice). Include a same-run reference section and report cell-type-specific results rather than a whole-section average alone (standard IHC practice).
When is apparent NUDT7 positivity more likely to be artefact?
A plausible positive result has interpretable cellular staining, often granular and cytoplasmic, in a well-preserved region (HPA: tissue profile; standard IHC practice). High staining in kidney proximal tubule cell bodies is reported, whereas adipocytes are listed as not detected, so cell identity matters when choosing comparison regions (HPA: kidney and adipose tissue). Diffuse staining confined to section edges, folds, or necrotic areas warrants scrutiny before scoring (standard IHC practice). Strong DAB signal in a primary-antibody omission control suggests a detection or endogenous-enzyme contribution rather than confirmed NUDT7 (standard IHC practice). Reconcile nuclear or perinuclear staining with the separate cell-imaging localisation record and an independent control before assigning it to NUDT7 (HPA: subcellular profile; standard IHC practice).
Boster reagents

Best NUDT7 / Peroxisomal coenzyme A diphosphatase NUDT7 IHC Antibodies

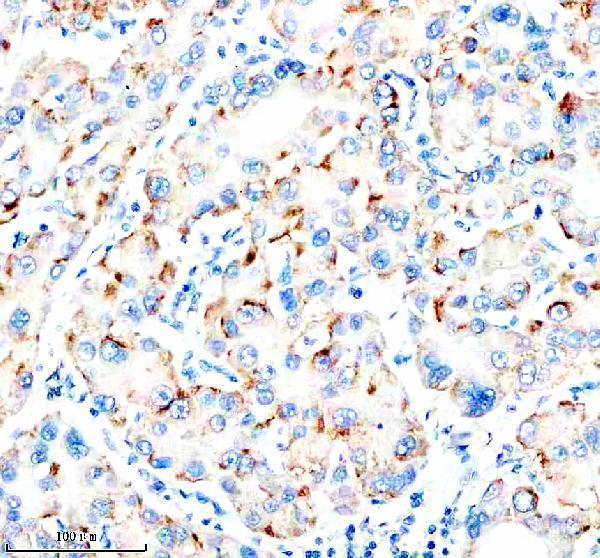
A10663-1 has real NUDT7 IHC data from paraffin-embedded human liver and liver cancer sections (catalog image captions); its listed reactivity includes human, mouse and rat (catalog reactivity).

Real IHC data IHC analysis of NUDT7 using anti-NUDT7 antibody (A10663-1). NUDT7 was detected in a paraffin-embedded section of human liver tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-NUDT7 Antibody (A10663-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-NUDT7 Antibody ®
Cat # A10663-1

A10663-1 is the only SKU shown and is listed for IHC (catalog applications). Its images show staining of paraffin-embedded human liver and liver cancer sections (A10663-1 image captions).

Which to pick: Choose A10663-1 for paraffin-section IHC; its captions document human liver and liver cancer staining, but do not report the fixative (A10663-1 image captions). No IF/ICC-validated SKU is provided (catalog applications; no IF images). A10663-1 lists human, mouse and rat reactivity, while its specified IHC dilution and image evidence cover human tissue only (catalog reactivity and IHC dilution; A10663-1 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P0C024 (NUDT7_HUMAN, Peroxisomal coenzyme A diphosphatase NUDT7).
  2. Human Protein Atlas. NUDT7 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. NUDT7 subcellular location (ICC-IF): Mainly localized to the Golgi apparatus. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. NUDT7 antibody validation summary (1 antibodies).
  5. NUDT7 Loss Promotes Kras(G12D) CRC Development. Cancers 2020 — PMC7139971.
  6. NUDT7 Modulates the UBA52-SREBF1 Signaling Axis to Promote PRRSV Replication via Lipid Synthesis. International journal of biological sciences 2026 — PMC12839166.
  7. Deficiency of peroxisomal NUDT7 stimulates de novo lipogenesis in hepatocytes. iScience 2022 — PMC9523354.
  8. Dysregulation of the NUDT7-PGAM1 axis is responsible for chondrocyte death during osteoarthritis pathogenesis. Nature communications 2018 — PMC6109082.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:15616553 — UniProt-cited evidence.
  11. PubMed PMID:11415433 — UniProt-cited evidence.