NXN / Nucleoredoxin · IHC design guide

Design Immunohistochemistry for NXN

Plan NXN IHC in paraffin sections using cytoplasmic staining as the observed tissue pattern; kidney tubule cells show high staining (HPA tissue IHC). Start the catalog antibody at 2–5 μg/ml and assess staining by cell type (datasheet A08028-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NXN (IHC for NXN): expected localisation Cytoplasmic staining in tissues (HPA tissue IHC), antibody A08028-1, validated IHC image, and IHC protocol steps
Printable NXN IHC protocol sheet — expected localisation Cytoplasmic staining in tissues (HPA tissue IHC), antibody A08028-1, controls and protocol steps. Open the full NXN IHC guide →

NXN Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in tissues (HPA tissue IHC)
Staining pattern Cytoplasmic staining; kidney tubule cells high (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A08028-1)
Positive control ⓘ Kidney+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining varies substantially by tissue and cell type (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope 3 isoforms; epitope coverage unreported (UniProt; datasheet A08028-1)
Section 1

Recommended NXN IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: A08028-1) is accompanied by 2 published NXN protocols: paraffin HCC tissue microarrays (PMC9352874) and frozen mouse liver sections (PMC10967286).

Recommended immunohistochemistry (IHC-P) protocol parameters
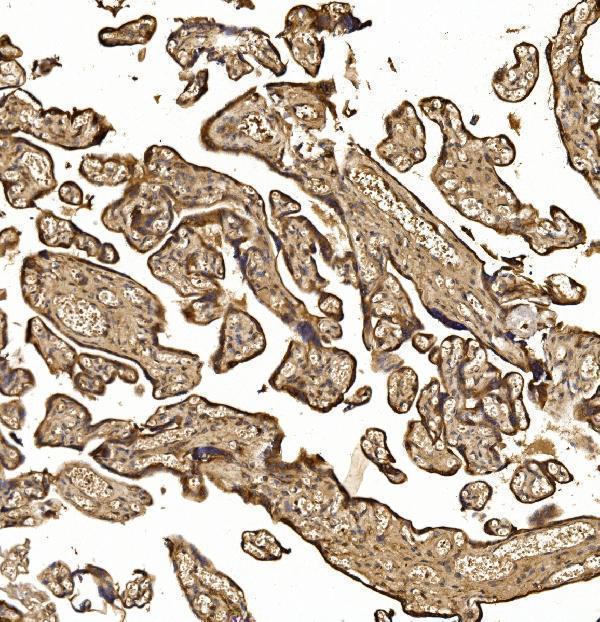
SampleParaffin-embedded human placenta tissue; fixative not specified (datasheet A08028-1)
FixationImage fixative and duration unreported (datasheet A08028-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A08028-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A08028-1)
Primary antibodyRabbit anti-NXN, 2-5 μg/ml (datasheet A08028-1)
Primary incubationOvernight at 4 °C (datasheet A08028-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A08028-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNXN-positive staining in cells in tubules of kidney (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues. No signal in the no-primary control.
💡Decision noteFor paraffin sections, start with heat-mediated EDTA retrieval at pH 8.0 (datasheet: A08028-1). The frozen-section protocol does not specify retrieval (PMC10967286).
Section 2

What Is the Expected NXN Staining Pattern?

NXN should appear mainly in the cytoplasm, especially in kidney tubular cells, where HPA reports high staining; several other cell types show medium staining (HPA tissue IHC). Cytosolic staining fits the approved ICC-IF location, while UniProt also lists the nucleus and reports no transmembrane segment (HPA subcellular; UniProt Q6DKJ4 localization and topology). HPA rates the tissue IHC pattern Approved, pending external verification (HPA tissue IHC).

What am I looking at on my slide?
Kidney tubules show strong cytoplasmic staining; bronchial respiratory epithelium shows weaker staining.This matches HPA's High kidney tubular and Medium bronchial epithelial scores (HPA tissue IHC). Compare compartments within each cell type; intensity alone cannot establish antibody specificity.
Staining is confined to cell borders or is strongly nuclear with little cytoplasmic signal.A border-only pattern conflicts with the reported cytosolic location and lack of a transmembrane segment (HPA subcellular; UniProt Q6DKJ4 topology). UniProt also lists the nucleus, so nuclear signal needs controls rather than automatic rejection (UniProt Q6DKJ4 localization).
Adipocytes or heart muscle cardiomyocytes stain as strongly as kidney tubules.HPA reports NXN as not detected in those cells but High in kidney tubules (HPA tissue IHC). Check cell identification, antibody-dependent staining and endogenous chromogen activity before calling the unexpected signal NXN (general IHC practice).
Color covers stroma, empty spaces and cells without a clear intracellular pattern.This is background rather than the cell-associated cytoplasmic pattern reported by HPA (HPA tissue IHC). Inspect a no-primary control and review blocking, washes and chromogen development (general IHC practice).
Kidney tubules have no signal, including in an otherwise well-preserved section.That conflicts with HPA's High tubular score (HPA tissue IHC). Check the catalog antibody's IHC-P instructions, detection reagents and a concurrent positive section; one negative run cannot establish that NXN is absent (general IHC practice).
💡Expected NXN appearanceCall a convincing positive when kidney tubular cells show high, predominantly cytoplasmic staining (HPA tissue IHC; HPA subcellular); widespread extracellular color or equally strong staining in HPA-undetected adipocytes is suspect (HPA tissue IHC; general IHC practice).
How each factor affects the staining
Compartment and topologyHPA's approved ICC-IF location is cytosol, and its tissue IHC profile is cytoplasmic (HPA subcellular; HPA tissue IHC). UniProt also lists the nucleus and no transmembrane segment; score mixed nuclear signal cautiously and question a border-only pattern (UniProt Q6DKJ4 localization and topology).
Cell type and reference intensityHPA scores kidney tubules High; bone marrow hematopoietic cells, bronchial respiratory epithelium and several other listed cells Medium (HPA tissue IHC). Adipocytes and cardiomyocytes are Not detected, providing useful within-panel comparisons (HPA tissue IHC).
Strength of pattern evidenceHPA marks tissue IHC Approved with external verification pending; its supplied antibody entry, HPA023566, is Approved for IHC and ICC (HPA tissue IHC; HPA antibodies). The payload does not report an Enhanced IHC rating, so treat the pattern as a reference, not independent confirmation.
Isoforms and epitope coverageUniProt lists 3 NXN isoforms and a thioredoxin domain at residues 167–321 (UniProt Q6DKJ4). Antibody epitope and isoform coverage are not supplied; an unexpected result cannot be attributed to a particular isoform from these records.
Antigen retrieval and fixationRetrieval is an IHC-P workflow variable (general IHC practice). Neither supplied source establishes an NXN-specific retrieval condition or fixation effect; follow the catalog antibody's IHC-P instructions and assess changes against a concurrent positive control.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in kidney tubulesA failed stain or detection step is possible; HPA reports High tubular staining (HPA tissue IHC).Run a known-positive kidney section alongside the sample; verify the catalog antibody's IHC-P instructions, reagent order and chromogen activity (general IHC practice).
All cells show uniform brown hazeBackground from blocking, washing, chromogen development or endogenous enzyme activity is possible (general IHC practice).Compare a no-primary control; review blocking and washes, and address endogenous activity as appropriate for the chromogen system (general IHC practice).
Adipocytes or cardiomyocytes look strongly positiveThose cells are Not detected in the supplied HPA tissue profile; nonspecific or endogenous signal is possible (HPA tissue IHC; general IHC practice).Confirm cell identity and compare no-primary and positive-tissue controls before interpreting the color as NXN (general IHC practice).
Signal outlines membranes but spares cytoplasmThis disagrees with the reported cytosolic location and no-transmembrane topology (HPA subcellular; UniProt Q6DKJ4 topology).Check for edge or precipitate artefacts and compare the pattern with a positive kidney section and no-primary control (general IHC practice).
Only nuclei stainUniProt lists a nuclear location, but HPA's approved ICC-IF location is cytosol and tissue IHC is described as cytoplasmic (UniProt Q6DKJ4 localization; HPA subcellular; HPA tissue IHC).Record the discrepancy; inspect cytoplasmic staining in the positive control and check the no-primary control before assigning nuclear specificity (general IHC practice).
Can ICC-IF images confirm this IHC-P result?HPA reports cytosolic ICC-IF localization and lists A-431, U-251MG and U2OS images, but these are a different application (HPA subcellular).Use ICC-IF as a compartment comparison; judge paraffin-section staining against HPA tissue IHC and IHC-P controls (HPA tissue IHC; general IHC practice).

Sample controls for NXN IHC & IF

🧪Run kidney first and score NXN staining in tubular cells, where HPA reports High expression (HPA: Kidney, cells in tubules, High). Use adipose tissue as the negative comparator, focusing on adipocytes reported as Not detected; on the kidney slide, use nearby non-tubular cells to assess background without assuming they are NXN-negative (HPA: Adipose tissue, adipocytes, Not detected; HPA: Kidney, cells in tubules, High).
Positive control tissue: Kidney (Cells in tubules, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NXN in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section, a host- and isotype-matched rabbit IgG control, and NXN-knockout tissue if available (selected-SKU caption: rabbit anti-NXN/NRX antibody; standard IHC controls). For chromogenic staining, quench endogenous peroxidase and assess endogenous biotin when using the caption’s streptavidin-biotin detection system, particularly in kidney tubules (selected-SKU caption: SABC/DAB detection; standard kidney IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state a fixative (selected-SKU caption: fixative not stated). The caption uses heat-mediated EDTA retrieval at pH 8.0, but does not establish whether NXN staining depends on retrieval (selected-SKU caption: EDTA retrieval, pH 8.0). The supplied evidence does not establish that frozen sections or IF are easier; kidney tubules also warrant an endogenous-biotin check with the caption’s SABC method (HPA: Cytosol, approved ICC-IF location; selected-SKU caption: SABC detection; standard kidney IHC practice).

HPA tissue IHC evidence for NXN

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Kidney Cells in tubules High Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Cervix Squamous epithelial cells Medium Protein (IHC) HPA →
Endometrium Cells in endometrial stroma Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Section 3

Advanced NXN IHC Tips

Troubleshoot NXN staining by checking retrieval, compartment, tissue controls, and cell-specific scoring against the supplied IHC evidence.

Which antigen retrieval conditions should I start with for NXN paraffin-section IHC?
Start with heat-mediated retrieval in EDTA, pH 8.0, the condition used for the catalog antibody in human placenta sections (datasheet A08028-1). After retrieval, let sections cool consistently and compare them with a control section processed in the same run (standard IHC practice). If staining remains weak, vary heating duration on matched sections before considering another retrieval buffer; excessive heating can damage morphology and complicate interpretation (standard IHC practice). Keep antibody concentration at the caption's 2 μg/ml during that comparison so a change in signal can be attributed to retrieval more clearly (datasheet A08028-1).
How should I troubleshoot weak NXN staining when fixation conditions differ?
The selected paraffin-section caption does not report a fixative, so target-specific NXN sensitivity to fixation is unknown (datasheet A08028-1). Record fixative, fixation duration, processing history, and section age for each specimen, then compare sections processed alike when assessing weak staining (standard IHC practice). Use the documented EDTA, pH 8.0 retrieval condition and 2 μg/ml primary concentration as starting points, changing one step at a time (datasheet A08028-1; standard IHC practice). Include a control tissue with expected staining in each run; differences between batches alone cannot establish an NXN-specific fixation effect (HPA: high in kidney tubular cells; standard IHC practice).
Where should credible NXN staining appear in tissue sections?
Expect predominantly cytoplasmic staining: tissue IHC describes cytoplasmic expression across several tissues, while approved subcellular data place NXN in the cytosol (HPA tissue IHC; HPA subcellular). UniProt also lists the nucleus, so a nuclear component warrants assessment alongside the cytoplasmic pattern rather than automatic rejection (UniProt Q6DKJ4 subcellular). In kidney, compare tubular cells with surrounding structures on the same section because tubular-cell staining is reported as high (HPA: high in kidney tubular cells). A crisp membrane-only rim is difficult to reconcile with a protein lacking a transmembrane segment; check morphology and secondary-only controls before scoring it (UniProt Q6DKJ4 topology; standard IHC practice).
Can this IHC stain distinguish NXN isoforms or reveal epitope masking?
NXN has 3 annotated isoforms, but the supplied antibody caption provides no epitope map or isoform-specific validation (UniProt Q6DKJ4 isoforms; datasheet A08028-1). Score the observed staining as NXN-associated signal without assigning it to a particular isoform unless an independently validated isoform-specific reagent is available (standard IHC interpretation). The thioredoxin domain spans residues 167–321, and the record lists N-terminal acetylation at residue 2; neither feature locates this antibody's epitope (UniProt Q6DKJ4 domains and modified residues). If staining varies with retrieval, compare matched sections and preserve the same detection settings, because altered accessibility alone does not identify an isoform (standard IHC practice).
How can I use IF to check NXN localisation alongside tissue IHC?
Treat IF as a separate validation experiment: the supplied catalog-antibody evidence documents paraffin-section chromogenic IHC, while HPA reports cytosolic localisation from ICC/IF images (datasheet A08028-1; HPA subcellular). Multiplex NXN with a marker identifying the expected cell population, such as kidney tubular cells, and check whether the signals occur in the same cells (HPA: high in kidney tubular cells; standard IF practice). Choose spectrally separated fluorophores and consider a far-red NXN channel when tissue autofluorescence obscures shorter wavelengths, using single-stain controls to assess bleed-through (standard IF practice). For a cytosolic epitope, permeabilise fixed cells or sections sufficiently to admit antibody, then compare compartment patterns with chromogenic IHC (HPA subcellular; standard IF practice).
What should I change if NXN DAB staining is diffuse or widespread?
First examine no-primary and secondary-only controls, especially if brown signal appears beyond plausible cytoplasmic compartments or persists in cells expected to be negative (HPA tissue IHC; standard IHC practice). The selected caption used 10% goat serum blocking, 2 μg/ml primary overnight at 4°C, and a biotinylated secondary for 30 minutes at 37°C (datasheet A08028-1). For DAB detection, check endogenous peroxidase blocking and inspect any background from the biotin-based detection system using appropriate controls (datasheet A08028-1; standard IHC practice). If background persists, titrate primary concentration and washing conditions on matched sections while preserving the same retrieval and imaging settings (standard IHC practice).
How should I quantify NXN staining across tissue samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; kidney tubular cells provide a reported high-expression reference, whereas adipocytes are reported as undetected (HPA tissue IHC). For cell-level chromogenic IHC, record the percentage of positive cells and intensity grades 0–3, then calculate an H-score from 0–300 (standard IHC scoring practice). Alternatively, measure NXN-positive cell density per mm² within a consistently annotated tissue region when cell counts are the main outcome (standard IHC quantification practice). Normalise to the number of eligible cells or evaluable tissue area, and keep section processing, DAB development, and scoring thresholds consistent across samples (standard IHC practice).
How do I separate true NXN staining from tissue artefacts?
A credible signal should occur in intact cells with a chiefly cytoplasmic pattern and agree with tissue context, such as strong kidney tubular-cell staining (HPA tissue IHC; HPA subcellular). Investigate membrane-only staining because NXN lacks a transmembrane segment, while assessing any nuclear signal against UniProt's additional nuclear annotation (UniProt Q6DKJ4 topology and subcellular). Exclude section edges, folds, and necrotic regions from scoring when they show disproportionate DAB deposition or poor morphology (standard IHC practice). If signal remains in a no-primary control, investigate endogenous enzyme activity or detection-system background before interpreting it as NXN; compare with expected low or undetected cells (standard IHC practice; HPA tissue IHC).
Boster reagents

Best NXN / Nucleoredoxin IHC Antibodies

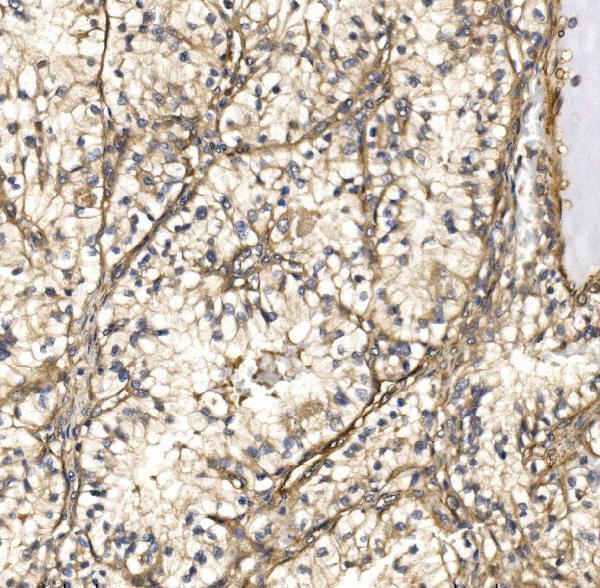
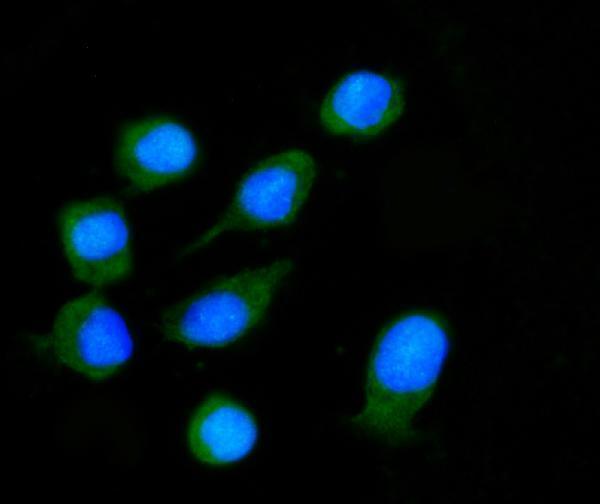
A08028-1 has IHC images from paraffin-embedded human placenta and renal clear cell carcinoma (IHC captions), plus IF data from Caco-2 cells (IF caption); catalog reactivity is human (catalog).

Real IHC data IHC analysis of NXN/NRX using anti-NXN/NRX antibody (A08028-1). NXN/NRX was detected in a paraffin-embedded section of human placenta tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-NXN/NRX Antibody (A08028-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-NXN/NRX Antibody ®
Cat # A08028-1

A08028-1 has IHC images from paraffin-embedded human placenta and human renal clear cell carcinoma (IHC captions). A08028-1 is listed for IF/ICC (catalog applications), with an IF image from Caco-2 cells (IF caption).

Which to pick: For tissue IHC, choose A08028-1 at 2–5 μg/ml (datasheet: IHC dilution); its IHC captions document paraffin sections with EDTA retrieval at pH 8.0, while the fixative is unreported (IHC captions). For IF/ICC, A08028-1 is listed at 5 μg/ml (catalog applications and IF dilution), with an IF image from Caco-2 cells (IF caption); its clone type is unreported (catalog clone field). For cross-species work, no listed SKU has documented nonhuman reactivity (catalog: human only).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q6DKJ4 (NXN_HUMAN, Nucleoredoxin).
  2. Human Protein Atlas. NXN tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. NXN subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. NXN antibody validation summary (1 antibodies).
  5. NXN suppresses metastasis of hepatocellular carcinoma by promoting degradation of Snail through binding to DUB3. Cell death & disease 2022 — PMC9352874.
  6. Nucleoredoxin Redox Interactions Are Sensitized by Aging and Potentiated by Chronic Alcohol Consumption in the Mouse Liver. Antioxidants (Basel, Switzerland) 2024 — PMC10967286.
  7. PubMed PMID:14702039 — UniProt-cited evidence.
  8. PubMed PMID:16625196 — UniProt-cited evidence.
  9. PubMed PMID:15489334 — UniProt-cited evidence.