This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan POLR3H paraffin IHC with the catalog antibody at 1:100–1:300 (datasheet A30654). Compare the expected nuclear location (UniProt) with the observed nuclear and cytoplasmic tissue profile, using Sertoli cells as a high-staining reference (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear and cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | General nuclear and cytoplasmic staining across cell types (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 8.0 HIER, heat-mediated (datasheet A30654) | |
| Positive control | Testis+4 more · see all | |
| Negative control | Adipose tissue |
| Fixation | Keep fixation consistent between paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Medium IHC–RNA consistency; verify the pattern (HPA tissue IHC) | |
| Regulation | Expression regulation unreported (UniProt) | |
| Isoform / epitope | Two isoforms; epitope impact unspecified (UniProt) |
The catalog antibody’s IHC-P protocol is paired with one published POLR3H protocol using formalin-fixed, paraffin-embedded breast cancer specimens (PMC13186826).
| Sample | Paraffin-embedded Human brain tissue; fixative not specified (datasheet A30654) |
| Fixation | Image fixative and duration unreported (datasheet A30654); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 8.0 (datasheet A30654); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-POLR3H, 1:100 - 1:300 (datasheet A30654) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | POLR3H-positive staining in sertoli cells of testis (HPA tissue IHC: High). HPA tissue profile: General nuclear and cytoplasmic expression. No signal in the no-primary control. |
POLR3H is a nuclear RNA polymerase III subunit with no transmembrane segment (UniProt Q9Y535). In paraffin sections, expect prominent staining in testicular Sertoli cells and moderate staining in several glandular, epithelial, hematopoietic, and neuronal cell types (HPA tissue IHC). HPA describes a general nuclear and cytoplasmic pattern, but rates its tissue IHC evidence Approved, with medium consistency against RNA expression and external verification pending (HPA tissue IHC).
| Strong Sertoli-cell staining with discernible nuclei in testis. | This matches the clearest listed tissue reference: Sertoli cells are High (HPA tissue IHC). Assess the cellular distribution alongside morphology; HPA reports general nuclear and cytoplasmic tissue staining, while UniProt assigns POLR3H to the nucleus (HPA tissue IHC; UniProt Q9Y535). |
| Moderate staining in glandular, respiratory epithelial, hematopoietic, or neuronal cells. | This can fit the reported pattern: adrenal, appendix, and breast glandular cells; bronchial respiratory epithelial cells; marrow hematopoietic cells; and cortical neurons are Medium (HPA tissue IHC). Identify the stained cells before comparing intensity across sections (general IHC practice). |
| Predominantly cell-surface or extracellular staining, without convincing cellular staining. | Treat this as a pattern requiring investigation: UniProt places POLR3H in the nucleus and lists no transmembrane segment, while HPA describes nuclear and cytoplasmic tissue staining (UniProt Q9Y535; HPA tissue IHC). Check section morphology and staining controls for artefact (general IHC practice). |
| Strong adipocyte staining or staining that obscures cell boundaries throughout the section. | Adipocytes are Not detected in the supplied HPA tissue IHC result (HPA tissue IHC). Check for cross-reactivity, endogenous detection activity, or nonspecific background before assigning the signal to POLR3H (general IHC practice). Other cell types require their own evidence because HPA reports low tissue specificity (HPA tissue IHC). |
| No staining in a technically adequate testis section containing Sertoli cells. | This conflicts with the listed High Sertoli-cell result (HPA tissue IHC). Review tissue identification, section quality, antibody and detection controls, and the general antigen-retrieval workflow before interpreting the sample as POLR3H-negative (general IHC practice). |
| Tissue and cell context | HPA reports Low tissue specificity by RNA and a general nuclear and cytoplasmic tissue IHC profile (HPA tissue IHC). Compare named cell populations: Sertoli cells are High, several listed populations are Medium, and adipocytes are Not detected (HPA tissue IHC). |
| Antibody validation | The listed HPA046787 antibody is Approved for IHC; its tissue profile has medium consistency with RNA expression and awaits external verification (HPA antibodies; HPA tissue IHC). Use controls when a sample differs from the reference pattern (general IHC practice). |
| Isoforms and epitope coverage | UniProt lists 2 POLR3H isoforms, but the supplied evidence gives no antibody epitope or isoform-specific staining result (UniProt Q9Y535; HPA antibodies). Avoid assigning a staining difference to a particular isoform without separate validation (general IHC practice). |
| What should IF/ICC show? | HPA reports mainly nucleoplasmic localization, with additional vesicle and centrosome signals; its listed antibody is Supported for ICC (HPA subcellular; HPA antibodies). Those cell-image observations provide context for compartment assessment but do not establish an IHC retrieval condition (HPA subcellular; general IHC practice). |
| Situation | Likely cause | Next action |
|---|---|---|
| Sertoli cells show little or no signal. | The expected High reference signal is absent; the cause cannot be assigned from the supplied tissue data alone (HPA tissue IHC). | Confirm Sertoli cells are present, then check positive-control staining, antibody handling, retrieval, and detection steps (general IHC practice). |
| Most cells and extracellular spaces have diffuse chromogen. | Nonspecific background or detection activity can obscure cellular localization (general IHC practice). | Inspect a no-primary control and review blocking, washes, and chromogen development; reassess identifiable cells afterward (general IHC practice). |
| Adipocytes stain strongly. | This differs from the Not detected adipocyte result (HPA tissue IHC); cross-reactivity or background is possible (general IHC practice). | Compare with a no-primary control and a Sertoli-cell positive control before calling adipocyte signal specific (general IHC practice; HPA tissue IHC). |
| Signal appears mainly on cell surfaces. | A dominant surface pattern does not match the reported nuclear and cytoplasmic profile or the absence of a transmembrane segment (HPA tissue IHC; UniProt Q9Y535). | Check morphology, section edges, and detection controls; score convincing intracellular staining separately (general IHC practice). |
| The nuclear component is difficult to judge. | Dense chromogen or an unclear counterstain can hide compartment boundaries (general IHC practice). | Review development and counterstaining, then compare nuclei and cytoplasm in intact cells (general IHC practice; HPA tissue IHC). |
| A weakly stained tissue differs from a reference image. | The HPA IHC profile has medium consistency with RNA expression and awaits external verification (HPA tissue IHC). | Confirm the same cell type is being compared and interpret the difference with section controls; avoid inferring a POLR3H-specific fixation effect from these data (general IHC practice; HPA tissue IHC). |
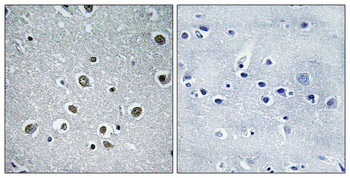
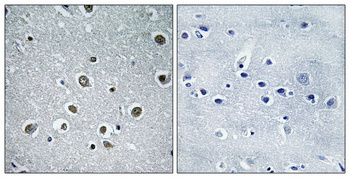


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Testis | Sertoli cells | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot POLR3H staining in paraffin sections by checking retrieval, nuclear localisation, controls and cell-specific scoring before interpreting differences between specimens.
Both antibodies have IHC images of paraffin-embedded human brain (catalog IHC captions); both list IF and human, mouse, and rat reactivity (catalog applications/reactivity).
A30654 has an IHC image of paraffin-embedded human brain with retrieval and peptide pre-absorption control details (A30654 IHC caption). A13065-1 has an IHC image of paraffin-embedded human brain and lists IF as an application (A13065-1 IHC caption; catalog applications).
Which to pick: For tissue IHC, start with A30654: its paraffin-section caption reports retrieval and a peptide pre-absorption control; the fixative is unreported (A30654 IHC caption). For IF/ICC, choose A30654 if ICC is needed, since it lists both applications; A13065-1 lists IF (catalog applications). Both list human, mouse, and rat reactivity, but their IHC images show human brain only (catalog reactivity; IHC captions).