PRMT7 / Protein arginine N-methyltransferase 7 · IHC design guide

Design Immunohistochemistry for PRMT7

Plan chromogenic PRMT7 IHC on paraffin sections with a 2–5 μg/ml starting range for the catalog antibody (datasheet A05485-2). Assess cytoplasmic staining across tissue cell types (HPA tissue IHC), and score any nuclear staining separately because a nuclear location is also annotated (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PRMT7 (IHC for PRMT7): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear location annotated (UniProt), antibody A05485-2, validated IHC image, and IHC protocol steps
Printable PRMT7 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear location annotated (UniProt), antibody A05485-2, controls and protocol steps. Open the full PRMT7 IHC guide →

PRMT7 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear location annotated (UniProt)
Staining pattern Widespread cytoplasmic staining across cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A05485-2)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Widespread staining limits negative tissue controls (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope Four isoforms; no transmembrane segment; verify epitope coverage (UniProt)
Section 1

Recommended PRMT7 IHC & IF Protocols

The catalog antibody has a datasheet IHC protocol (datasheet: A05485-2); the published PRMT7 IHC methods below provide tissue-specific starting points (PMC4413634; PMC10539571; PMC1609128; PMC12490292).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human ovarian cancer tissue; fixative not specified (datasheet A05485-2)
FixationImage fixative and duration unreported (datasheet A05485-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A05485-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05485-2)
Primary antibodyRabbit anti-PRMT7, 2-5 μg/ml (datasheet A05485-2)
Primary incubationOvernight at 4 °C (datasheet A05485-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A05485-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPRMT7-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A05485-2). The breast tissue study used citrate pH 6 with microwave heating (PMC4413634: methods).
Section 2

What Is the Expected PRMT7 Staining Pattern?

PRMT7 should show broadly distributed cytoplasmic staining in tissue IHC, with high staining reported in selected glandular, epithelial, hematopoietic, tubular, and macrophage populations (HPA: ubiquitous cytoplasmic expression; HPA: tissue IHC). Nuclear localization is biologically plausible (UniProt Q9NVM4: cytosol and nucleus), but the predominantly nucleoplasmic pattern comes from ICC-IF rather than paraffin IHC (HPA: subcellular ICC-IF). PRMT7 has no transmembrane segment (UniProt Q9NVM4: topology). HPA rates the tissue IHC pattern Supported, with medium agreement between staining and RNA data (HPA: tissue IHC).

What am I looking at on my slide?
Clear cytoplasmic staining in appendix or colon glandular cells, kidney tubular cells, or lung macrophages (HPA: High in these cell populations).This matches reported high-intensity tissue IHC sites (HPA: tissue IHC). Compare the relevant cell population with neighboring cells on the same section; widespread expression means a completely blank surrounding tissue is not required for a credible result (HPA: ubiquitous cytoplasmic expression).
Nuclear staining accompanies cytoplasmic staining, while the expected cytoplasmic population remains visible (HPA: tissue IHC; UniProt Q9NVM4: nucleus).Nuclear PRMT7 is plausible (UniProt Q9NVM4: nucleus). The mainly nucleoplasmic signal, with an additional nucleolar fibrillar-center signal, was observed by ICC-IF (HPA: subcellular ICC-IF); it should not be used as the sole criterion for a positive paraffin IHC section.
Staining is confined to cell membranes or extracellular material, with no convincing intracellular signal (UniProt Q9NVM4: topology and localization).That distribution conflicts with the reported cytosolic and nuclear locations and the absence of a transmembrane segment (UniProt Q9NVM4). Treat it as suspect; assess morphology and a no-primary control before assigning it to PRMT7 (general IHC practice).
Strong signal appears chiefly in an unexpected population while the reported high-staining population is weak, such as stromal cells beside unstained appendix glands (HPA: High in appendix glandular cells).The mismatch raises concern for nonspecific binding or endogenous detection activity (general IHC practice). It does not establish that the unexpected cell population lacks PRMT7: HPA describes broadly distributed cytoplasmic expression and provides no negative tissue in this record (HPA: tissue IHC).
Color covers the section diffusely, obscures cell boundaries, or also appears in the no-primary control (general IHC practice).The distribution is unsuitable for assigning cellular PRMT7 localization (general IHC practice). Evaluate detection background and endogenous activity before scoring; HPA's tissue profile describes cell-associated cytoplasmic staining, not an interpretable diffuse haze (HPA: tissue IHC).
💡Expected PRMT7 appearanceCall a section positive when recognizable cells show intracellular, predominantly cytoplasmic staining, with strong signal possible in the specified HPA High populations; isolated membrane, extracellular, or control-positive staining is suspect (HPA: tissue IHC; UniProt Q9NVM4: localization and topology; general IHC practice).
How each factor affects the staining
Tissue and cell choice (HPA: tissue IHC)High staining is reported in appendix, colon, duodenum, and gallbladder glandular cells; bronchial respiratory epithelium; kidney tubules; bone-marrow hematopoietic cells; and lung macrophages (HPA: tissue IHC). Low-staining examples include skeletal-muscle myocytes and hippocampal neurons, so these offer a weaker sensitivity check (HPA: Low in these populations).
Compartment and assay context (UniProt Q9NVM4; HPA: tissue IHC and subcellular ICC-IF)For IHC, HPA describes ubiquitous cytoplasmic expression; UniProt also lists the nucleus (HPA: tissue IHC; UniProt Q9NVM4). IF/ICC Q&A: Where should signal appear? Mainly in the nucleoplasm, with an additional nucleolar fibrillar-center signal in HPA's ICC-IF observations (HPA: subcellular ICC-IF).
Antibody evidence (HPA: antibody validation)The listed antibody, HPA044241, is rated Supported for IHC and Enhanced for ICC (HPA: antibody validation). These are application-specific evidence grades; the stronger ICC grade does not establish an equally strong paraffin-section nuclear pattern (HPA: antibody validation; HPA: tissue IHC and subcellular ICC-IF).
Protein form (UniProt Q9NVM4: isoforms, processing, topology)Four isoforms are recorded, but this payload gives no isoform-specific staining pattern or antibody epitope (UniProt Q9NVM4: isoforms). PRMT7 has no annotated signal peptide, propeptide, or transmembrane segment, and its annotated chain spans residues 1–692 (UniProt Q9NVM4: processing and topology); these facts do not establish assay-specific retrieval or fixation effects.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in appendix or colon glands, kidney tubules, or another reported High population (HPA: tissue IHC).The expected population may have been missed, or the staining run may have failed; a single absent signal does not identify a PRMT7-specific cause (HPA: tissue IHC; general IHC practice).Confirm the relevant cells are present and examine a known-positive section processed in the same run; verify the primary-antibody, detection, and counterstain steps against the chosen IHC procedure (HPA: High populations; general IHC practice).
Only nuclear signal is visible in tissue IHC, with little cytoplasmic staining (HPA: tissue IHC).PRMT7 can be nuclear, but the predominantly nucleoplasmic observation comes from ICC-IF; nuclear-only tissue staining has weaker support here (UniProt Q9NVM4: nucleus; HPA: subcellular ICC-IF).Check a reported cytoplasmic High population and review the no-primary control before interpreting the nuclear signal; score the IHC and ICC-IF evidence separately (HPA: tissue IHC and subcellular ICC-IF; general IHC practice).
Strong membrane-like or extracellular staining dominates (UniProt Q9NVM4: topology and localization).This conflicts with PRMT7's reported intracellular locations and lack of a transmembrane segment; nonspecific signal is possible (UniProt Q9NVM4; general IHC practice).Recheck tissue morphology, compare with the no-primary control, and assess whether credible intracellular staining is also present in an HPA High population (general IHC practice; HPA: tissue IHC).
Brown signal persists in the no-primary control, particularly among blood-rich cells or macrophages (general chromogenic IHC practice).Endogenous enzyme activity or detection-reagent background can mimic positive chromogenic staining; lung macrophages and bone-marrow hematopoietic cells are also reported PRMT7 High populations (general IHC practice; HPA: tissue IHC).Apply the detection system's appropriate endogenous-activity control or blocking step, then compare primary-present and no-primary sections before calling those cells positive (general IHC practice).
A diffuse haze makes cell boundaries difficult to identify (general IHC practice).Nonspecific reagent binding or excessive detection background can obscure the cellular distribution (general IHC practice).Review blocking, washes, antibody concentration, detection exposure, and the no-primary control using the established IHC procedure; reassess only where cell-associated signal can be distinguished (general IHC practice).
A low-staining tissue gives a faint or apparently negative result (HPA: Low in skeletal-muscle myocytes and hippocampal neurons).Low reported staining provides a limited positive-control challenge, while HPA reports no negative tissue in this payload (HPA: tissue IHC).Check an HPA High cell population in the same validated workflow before inferring assay failure or absence of PRMT7 from the low-staining specimen (HPA: tissue IHC; general IHC practice).

Sample controls for PRMT7 IHC & IF

🧪Run colon first and look for staining in glandular cells (HPA: High in colon glandular cells). HPA detects PRMT7 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and treat unstained neighboring cells only as background references, not confirmed internal negatives (HPA: no negative rows; standard IHC practice).
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: None in HPA: PRMT7 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PRMT7 in A-431, U-251MG, U2OS, HeLa BAC 5821, HeLa , with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide and a concentration-matched rabbit IgG isotype control, matching the caption’s rabbit primary antibody (selected-SKU caption: rabbit anti-PRMT7; standard IHC practice). A PRMT7 knockout specimen or a validated peptide-block control can test target dependence; quench endogenous peroxidase before HRP–DAB detection, particularly where inflammatory cells are present (standard IHC practice; selected-SKU caption: HRP–DAB detection).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative unreported). The caption uses heat-mediated EDTA retrieval at pH 8.0, providing an IHC-P starting condition, but does not establish that retrieval is required for every specimen (selected-SKU caption: EDTA retrieval). The supplied evidence does not establish that frozen sections or IF/ICC are easier; in colon, distinguish glandular-cell staining from luminal debris and nonspecific chromogen deposits (HPA: High in colon glandular cells; standard IHC practice).

HPA tissue IHC evidence for PRMT7

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: PRMT7 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced PRMT7 IHC Tips

Troubleshoot PRMT7 staining in paraffin sections by checking retrieval, compartment, cell identity, and controls before comparing signal intensity.

What retrieval should I try first for weak PRMT7 staining?
Start with heat-mediated retrieval in EDTA, pH 8.0 (datasheet A05485-2). The selected paraffin-section image used that retrieval before incubation with 2 μg/ml primary antibody overnight at 4°C (caption A05485-2). If signal is weak, check heating consistency, section adherence, and whether the retrieval solution reached its intended pH before changing conditions (standard IHC practice). Compare any adjusted retrieval with the starting condition on adjacent sections, keeping antibody concentration and detection constant (standard IHC practice). Stronger retrieval can increase tissue damage or background, so judge both signal and morphology (standard IHC practice).
Could fixation explain inconsistent PRMT7 staining between paraffin sections?
Target-specific fixation sensitivity is unknown: the selected PRMT7 paraffin-section caption does not state a fixative (caption A05485-2). Record each specimen’s fixative and processing history, then compare sections processed alike before attributing intensity differences to biology (standard IHC practice). If staining varies, review tissue preservation, section quality, retrieval, and detection alongside fixation records (standard IHC practice). Use the documented EDTA, pH 8.0 retrieval as a common starting condition when assessing comparable sections (datasheet A05485-2). Neither tissue staining patterns nor protein topology establishes how PRMT7 responds to a particular fixative (HPA: tissue IHC profile; UniProt Q9NVM4: topology).
Should PRMT7 staining be nuclear or cytoplasmic?
Evaluate nuclear and cytoplasmic staining separately: PRMT7 is annotated in the nucleus and cytosol (UniProt Q9NVM4: subcellular location). Tissue IHC shows ubiquitous cytoplasmic expression with supported reliability and medium consistency with RNA data (HPA: tissue IHC). Cellular imaging reports enhanced nucleoplasmic localisation and an additional nucleolar fibrillar-center location (HPA: subcellular). Thus, assess the compartment within intact cells rather than treating one compartment alone as proof of specificity (UniProt Q9NVM4: subcellular location; HPA: tissue IHC and subcellular). Use a nuclear counterstain and matched exposure or development conditions to compare compartment patterns across sections (standard IHC practice).
How could PRMT7 isoforms or epitope accessibility affect IHC?
PRMT7 has 4 annotated isoforms, but the supplied antibody caption does not identify its recognized epitope (UniProt Q9NVM4: isoforms; caption A05485-2). Avoid assuming that a negative cell lacks every isoform until the antibody’s epitope and isoform coverage are established (UniProt Q9NVM4: isoforms; caption A05485-2). The protein contains two SAM-dependent methyltransferase domains, at residues 14–345 and 358–684, and an annotated modified arginine at residue 32 (UniProt Q9NVM4: domains and modified residues). These features identify questions for epitope review; they do not establish that modification or domain structure changes staining (UniProt Q9NVM4: domains and modified residues). Compare staining with an independently validated antibody when isoform coverage matters (standard IHC practice).
How should I assess PRMT7 by IF alongside this IHC result?
Treat IF/ICC as a separate application; the selected antibody evidence describes chromogenic staining of a paraffin section (caption A05485-2). Multiplex PRMT7 with a marker for the cell type being assessed, then use a nuclear counterstain to evaluate its reported nucleoplasmic localisation (HPA: subcellular; standard IF practice). Choose fluorophores after inspecting tissue autofluorescence and include single-label controls to assess channel bleed-through (standard IF practice). PRMT7 is annotated in the cytosol and nucleus and has no transmembrane segment, so an intracellular epitope requires access through the plasma membrane and, for nuclear signal, the nuclear envelope (UniProt Q9NVM4: subcellular location and topology; standard IF practice). Adjust permeabilisation against morphology and background using IF controls (standard IF practice).
How can I reduce diffuse DAB background without losing PRMT7 signal?
Begin with the documented 10% goat-serum block and 2 μg/ml primary antibody used for the selected paraffin-section image (caption A05485-2). Its detection used a peroxidase-conjugated secondary antibody and DAB chromogen (caption A05485-2). Include a peroxidase block and a no-primary control to identify endogenous enzyme activity or detection-system staining (standard chromogenic IHC practice). If diffuse colour persists, adjust washing, antibody concentration, and DAB development one variable at a time while retaining a known staining reference (standard IHC practice). Score cellular staining only where morphology remains intact, since deposited chromogen outside cells can obscure the expected pattern (standard IHC practice; UniProt Q9NVM4: subcellular location).
What is a defensible way to quantify PRMT7 IHC staining? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring because tissue IHC reports cytoplasmic staining while cellular imaging highlights the nucleoplasm (HPA: tissue IHC and subcellular). For a defined population, report the percentage of positive cells and an intensity-based H-score, keeping nuclear and cytoplasmic scores separate (standard IHC practice; UniProt Q9NVM4: subcellular location). If counting positive cells across regions, report density per mm² of viable tissue and normalise comparisons to the same cell type or tissue area (standard IHC practice). Keep section thickness, retrieval, DAB development, and scoring thresholds consistent across samples (standard IHC practice). Exclude damaged and necrotic regions using prespecified rules (standard IHC practice).
Which patterns suggest true PRMT7 staining rather than artefact?
Seek reproducible cellular staining in a plausible compartment: PRMT7 is annotated in the cytosol and nucleus (UniProt Q9NVM4: subcellular location). As reference populations, HPA reports high tissue staining in kidney tubule cells and lung macrophages, while ovarian stromal cells are listed as low (HPA: tissue IHC). Check whether apparent positives follow cell identity and morphology across adjacent regions rather than section edges or necrotic areas (standard IHC practice). An isolated edge signal, staining over necrosis, or DAB colour in a no-primary control warrants investigation of processing or endogenous enzyme activity (standard IHC practice). Interpret intensity cautiously because HPA rates tissue staining as supported with medium RNA consistency (HPA: tissue IHC reliability).
Boster reagents

Best PRMT7 / Protein arginine N-methyltransferase 7 IHC Antibodies

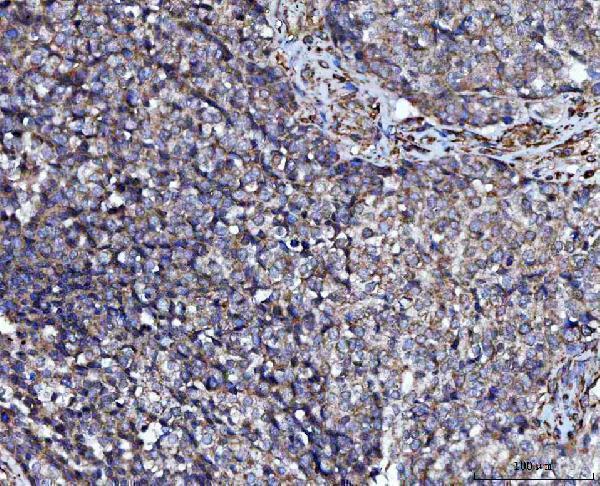
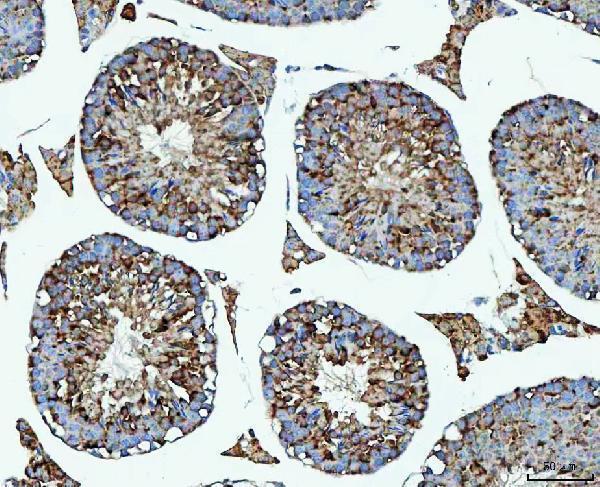
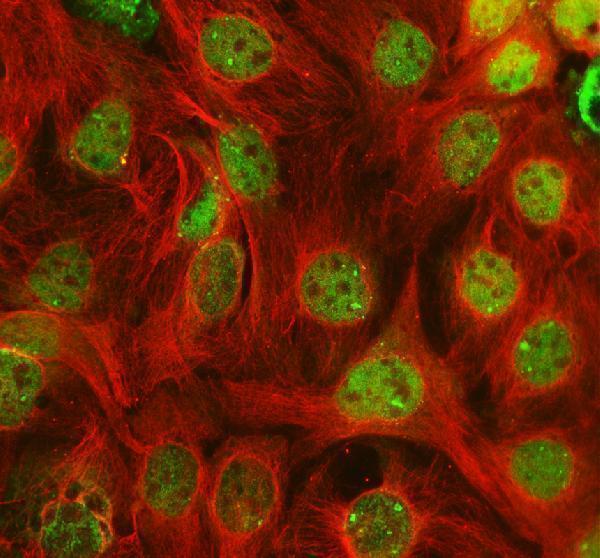
A05485-2 has IHC images from human ovarian cancer and mouse and rat testis paraffin sections, plus IF data from CACO-2 cells (catalog image captions).

Real IHC data IHC analysis of PRMT7 using anti-PRMT7 antibody (A05485-2). PRMT7 was detected in a paraffin-embedded section of human ovarian cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-PRMT7 Antibody (A05485-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-PRMT7 Antibody ®
Cat # A05485-2

A05485-2 was demonstrated by IHC on human ovarian cancer and mouse and rat testis paraffin sections (catalog IHC image captions). The same SKU was demonstrated by IF/ICC in CACO-2 cells (catalog IF image caption).

Which to pick: Choose A05485-2 for paraffin-section IHC; its captions report EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody, while the fixative is unreported (catalog IHC image captions). For IF/ICC, A05485-2 has a CACO-2 image at 5 μg/ml (catalog IF image caption). For cross-species IHC, its human, mouse and rat tissue images provide examples for all three listed reactive species; clonality is unreported (catalog IHC image captions; catalog reactivity and clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NVM4 (ANM7_HUMAN, Protein arginine N-methyltransferase 7).
  2. Human Protein Atlas. PRMT7 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. PRMT7 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the nucleoli fibrillar center..
  4. Human Protein Atlas. PRMT7 antibody validation summary (1 antibodies).
  5. Protein arginine methyltransferase 7 promotes breast cancer cell invasion through the induction of MMP9 expression. Oncotarget 2015 — PMC4413634.
  6. PRMT7 Inhibits the Proliferation and Migration of Gastric Cancer Cells by Suppressing the PI3K/AKT Pathway via PTEN. Journal of Cancer 2023 — PMC10539571.
  7. The testis-specific factor CTCFL cooperates with the protein methyltransferase PRMT7 in H19 imprinting control region methylation. PLoS biology 2006 — PMC1609128.
  8. Protein arginine methyltransferase 7 regulates the cell cycle and promotes the progression of prostate cancer. Oncology letters 2025 — PMC12490292.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:11572484 — UniProt-cited evidence.