RLIM / E3 ubiquitin-protein ligase RLIM · IHC design guide

Design Immunohistochemistry for RLIM

This RLIM paraffin IHC guide describes nuclear and cytoplasmic tissue staining (HPA tissue IHC). It pairs the catalog antibody’s 2–5 μg/ml range (datasheet A05428-1) with compartmental scoring and matched controls (standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RLIM (IHC for RLIM): expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A05428-1, validated IHC image, and IHC protocol steps
Printable RLIM IHC protocol sheet — expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A05428-1, controls and protocol steps. Open the full RLIM IHC guide →

RLIM Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cells across tissues show nuclear and cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A05428-1)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Low staining–RNA consistency limits interpretation (HPA tissue IHC)
Regulation Intensity regulation not specified (UniProt)
Isoform / epitope Two isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended RLIM IHC & IF Protocols

The catalog antibody protocol is provided separately (datasheet: A05428-1). These 3 published RLIM IHC protocols cover medulloblastoma, liver, and breast and head and neck specimens (PMC8982406; PMC5669951; PMC3784382).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded diffuse large B-cell lymphoma of human intestine tissue; fixative not specified (datasheet A05428-1)
FixationImage fixative and duration unreported (datasheet A05428-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A05428-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05428-1)
Primary antibodyRabbit anti-RLIM, 2-5 μg/ml (datasheet A05428-1)
Primary incubationOvernight at 4 °C (datasheet A05428-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A05428-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRLIM-positive staining in adipocytes of adipose tissue (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic and nuclear expression in all tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet: A05428-1); published retrieval conditions may require optimization for their respective antibodies (PMC5669951; PMC3784382).
Section 2

What Is the Expected RLIM Staining Pattern?

RLIM is annotated in the nucleus (UniProt Q9NVW2) and has no transmembrane segment (UniProt Q9NVW2 topology). In paraffin sections, expect nuclear staining with possible cytoplasmic staining across tissues (HPA: tissue IHC profile). HPA reports medium staining in several cell populations and low staining in others (HPA: tissue IHC). Its IHC assessment is Approved, with low consistency between antibody staining and RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Distinct nuclear staining, with or without cytoplasmic staining, in an expected cell population.This fits RLIM's nuclear annotation and HPA's broader tissue pattern (UniProt Q9NVW2; HPA: tissue IHC profile). Compare nuclei with the counterstain before scoring; cytoplasmic color alone gives weaker support for identity (HPA: ICC-IF nucleoplasm supported, cytosol uncertain).
A strong membrane outline or cytoplasmic staining that obscures nuclei.A membrane outline conflicts with the absence of a transmembrane segment (UniProt Q9NVW2 topology). Cytoplasmic staining is reported in tissue IHC, but a cytoplasm-only result deserves review against the expected nuclear component (HPA: tissue IHC profile; UniProt Q9NVW2).
Strong staining confined to an unexpected cell population while expected cells appear unstained.Consider cross-reactivity or endogenous detection activity, then inspect morphology and controls (general IHC practice). HPA reports expression across tissues, so a cell population cannot be declared RLIM-negative solely from this record (HPA: tissue IHC profile).
Diffuse color covers cells and spaces without clear nuclear boundaries.This limits localization scoring and can reflect background from blocking, detection, washing, or excess antibody (general IHC practice). It does not establish RLIM expression, even where tissue staining has been reported (HPA: tissue IHC profile).
No convincing signal in bone marrow hematopoietic cells or bronchial respiratory epithelial cells.Both have medium staining in HPA tissue IHC (HPA: bone marrow and bronchus). An absent result calls for a run-level check, but HPA's Approved assessment has low staining–RNA consistency, so a single section is not definitive (HPA: tissue IHC reliability).
💡Expected RLIM appearanceCall a positive result when identifiable nuclei stain in an expected cell population, allowing some cytoplasmic color (UniProt Q9NVW2; HPA: tissue IHC profile); HPA reports medium staining in bone marrow hematopoietic cells, while broad haze or a membrane outline is suspect (HPA: bone marrow; general IHC practice; UniProt Q9NVW2 topology).
How each factor affects the staining
Compartment evidence (UniProt Q9NVW2; HPA: tissue IHC and ICC-IF).UniProt places RLIM in the nucleus; HPA tissue IHC reports nuclear and cytoplasmic expression. In ICC-IF, nucleoplasm is supported and cytosol is uncertain. Give clear nuclear staining the greatest interpretive weight (UniProt Q9NVW2; HPA: tissue IHC profile; HPA: ICC-IF).
Tissue and cell context (HPA: tissue IHC).HPA records medium staining in adipocytes, bone marrow hematopoietic cells, and bronchial respiratory epithelial cells, among others; hepatocytes, prostate glandular cells, and soft tissue fibroblasts are low. Choose comparison cells accordingly, without treating low as absent (HPA: tissue IHC).
Validation and RNA agreement (HPA: tissue IHC; HPA: HPA018895).HPA labels tissue IHC Approved yet notes low consistency with RNA expression; HPA018895 is IHC Approved, without an Enhanced designation in the supplied record. Interpret staining alongside compartment, morphology, and controls; RNA level alone cannot confirm an IHC signal (HPA: tissue IHC reliability; HPA: HPA018895; general IHC practice).
Isoforms and processing (UniProt Q9NVW2).UniProt lists 2 isoforms and a single annotated chain spanning residues 1–624, with no signal peptide or propeptide. The record supplies no antibody epitope or isoform-specific staining evidence; do not infer which isoform a positive section detects (UniProt Q9NVW2).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected nuclei are pale while the section has little specific color.The assay may have insufficient detectable signal; the result alone cannot identify which workflow step failed (general IHC practice).Check the positive tissue control, antibody incubation, retrieval, detection reagents, and counterstain using the validated IHC-P workflow (general IHC practice). Compare with HPA's medium-staining cell populations (HPA: tissue IHC).
Cytoplasmic color dominates and nuclear staining is absent.HPA permits cytoplasmic tissue staining, but this pattern lacks the nuclear component supported by UniProt and HPA ICC-IF (HPA: tissue IHC and ICC-IF; UniProt Q9NVW2).Review nuclear boundaries against the counterstain and compare a positive control; assess background before assigning RLIM localization (general IHC practice).
An unexpected cell population is strongly stained.Cross-reactivity or endogenous detection activity is possible (general IHC practice); broad RLIM tissue expression prevents a categorical negative call for that population (HPA: tissue IHC profile).Check cell identity and run appropriate detection controls; compare expected nuclear localization and HPA cell-level staining before scoring (general IHC practice; UniProt Q9NVW2; HPA: tissue IHC).
Diffuse staining obscures the tissue pattern.Nonspecific antibody binding, incomplete blocking, or detection background can obscure nuclear detail (general IHC practice).Inspect control sections and review blocking, washes, antibody concentration, and detection steps in the validated IHC-P workflow (general IHC practice). Score only interpretable cells.
A low-staining tissue appears negative.HPA records low staining in hepatocytes, prostate glandular cells, and soft tissue fibroblasts; a negative-looking section may offer limited sensitivity for assessment (HPA: tissue IHC).Include a tissue with an HPA medium-staining cell population in the same run, then assess the low-staining section with the controls (HPA: tissue IHC; general IHC practice).
IF/ICC question: where should RLIM appear?HPA supports nucleoplasmic localization and labels additional cytosolic localization uncertain (HPA: ICC-IF); UniProt annotates the nucleus (UniProt Q9NVW2).Look for nucleoplasmic signal and interpret cytosolic signal cautiously; assess localization with an appropriate nuclear counterstain and controls (HPA: ICC-IF; general IF practice).

Sample controls for RLIM IHC & IF

🧪Run adipose tissue first and score adipocytes, which have Medium RLIM staining (HPA: adipose tissue, adipocytes, Medium). HPA detects RLIM in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and treat cells without nuclear staining on the positive slide as candidate background only, not validated RLIM-negative cells (HPA: no negative rows; HPA: RLIM detected in all 45 tissues; UniProt: nucleus).
Positive control tissue: Adipose tissue (Adipocytes, HPA Medium)
Negative control tissue: None in HPA: RLIM is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RLIM in A-431, U-251MG, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide and a concentration-matched rabbit IgG isotype control, alongside an RLIM-knockout specimen or validated peptide-block control (selected-SKU caption: rabbit anti-RLIM antibody; standard IHC controls). Quench endogenous peroxidase before HRP/DAB detection, and assess nonspecific staining around adipocyte vacuoles (selected-SKU caption: HRP/DAB detection; HPA: adipose tissue, adipocytes; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected-SKU paraffin-section caption does not state a fixative (selected-SKU caption: fixative unreported). The reported IHC procedure uses heat retrieval in EDTA at pH 8.0; its retrieval requirement has not been established by comparison with an unretrieved section (selected-SKU caption: EDTA retrieval, pH 8.0). The supplied evidence does not establish whether frozen sections or IF are easier; IF can be assessed for nucleoplasmic signal, while adipocyte vacuoles may complicate tissue scoring (HPA: nucleoplasm supported; HPA: adipose tissue, adipocytes; standard IHC practice).

HPA tissue IHC evidence for RLIM

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Adipocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: RLIM is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced RLIM IHC Tips

These questions address RLIM staining in paraffin sections with chromogenic IHC; the immunofluorescence entry covers related imaging decisions.

How should I retrieve RLIM in paraffin sections when staining is weak?
Start with heat mediated retrieval in EDTA at pH 8.0 (datasheet A05428-1). The selected paraffin section image used that retrieval before 2 μg/ml primary antibody overnight at 4°C (datasheet A05428-1). If staining is weak, check that sections reached the intended retrieval temperature and compare retrieval durations on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Judge improvement by clearer staining in intact cells, since excess heating can damage morphology and make apparent signal harder to interpret (standard IHC practice).
Can fixation explain inconsistent RLIM staining between paraffin blocks?
RLIM specific sensitivity to fixation is unknown from the supplied evidence, and the selected paraffin section caption does not state its fixative (datasheet A05428-1). Record each block's fixative and fixation duration before comparing staining, because fixation can alter epitope accessibility in paraffin IHC (standard IHC practice). Process comparison sections together and apply the same EDTA pH 8.0 retrieval to limit variation from subsequent steps (datasheet A05428-1; standard IHC practice). If blocks differ, compare morphology and an independently validated control alongside RLIM staining; a signal difference alone cannot establish fixation sensitivity for this antibody (standard IHC practice).
Should cytoplasmic RLIM staining count as a positive IHC result?
Prioritize staining in intact nuclei: RLIM is annotated as nuclear, and nucleoplasm is the supported main location in subcellular imaging (UniProt Q9NVW2; HPA subcellular). Tissue IHC also reports nuclear and cytoplasmic expression, while the additional cytosolic location in subcellular imaging is uncertain (HPA tissue IHC; HPA subcellular). Score nuclear and cytoplasmic staining separately against a nuclear counterstain, recording the cell type and section quality for each compartment (standard IHC practice). Treat diffuse cytoplasmic staining without a reproducible nuclear pattern cautiously, especially where background or damaged tissue obscures cell boundaries (standard IHC practice; UniProt Q9NVW2).
Could isoforms or epitope accessibility explain discordant RLIM staining?
RLIM has 2 annotated isoforms, but the supplied antibody caption does not identify the recognized epitope or establish isoform coverage (UniProt Q9NVW2; datasheet A05428-1). It also lists phosphorylation at serines 164, 195, 228, and 230; their effect on this antibody's staining is unknown (UniProt Q9NVW2). When sections disagree, compare adjacent sections under the same retrieval and detection conditions before attributing the difference to an isoform or modification (standard IHC practice). Document the antibody's epitope if independently available, then assess whether that sequence is shared by the isoforms being investigated (standard IHC practice; UniProt Q9NVW2).
How can IF help assess an ambiguous RLIM IHC pattern?
For a separate IF assessment, pair RLIM with a marker for the expected cell type, such as hematopoietic cells in bone marrow, and compare both signals with nuclear staining (HPA tissue IHC; standard IF practice). Choose fluorophores after checking tissue autofluorescence and favor a spectrally separated longer wavelength channel when background is high (standard IF practice). RLIM has no annotated transmembrane segment and is mainly nucleoplasmic, so permeabilisation should permit access to an intracellular epitope if the antibody recognizes one (UniProt Q9NVW2; HPA subcellular; standard IF practice). Keep the IF assessment distinct from the paraffin chromogenic result, whose caption reports heat retrieval, peroxidase detection, and DAB (datasheet A05428-1).
What should I check when RLIM IHC shows diffuse brown background?
Compare a section processed without primary antibody with the test section to assess secondary reagent and chromogen background (standard IHC practice). The selected paraffin image used 10% goat serum blocking, a peroxidase conjugated secondary reagent, and DAB development (datasheet A05428-1). Check whether a peroxidase block, wash conditions, and DAB development produce clean negative areas; these are general chromogenic IHC controls rather than RLIM specific evidence (standard IHC practice). Evaluate background separately from nuclear signal, because RLIM's supported nucleoplasmic location and the reported tissue cytoplasmic pattern require compartment aware interpretation (HPA subcellular; HPA tissue IHC).
How should I quantify RLIM staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and score nuclear and cytoplasmic signal separately before comparing sections (standard IHC practice; HPA tissue IHC). For intact cells, record the percentage positive and staining intensity, then calculate an H-score using the same intensity thresholds across the cohort (standard IHC practice). Where cell numbers vary, report positive cells per mm² of viable tissue or normalize positive cells to all assessable cells of the defined population (standard IHC practice). Exclude folds, necrosis, and poorly preserved edges consistently, and retain the retrieval and development settings with each score for auditability (standard IHC practice).
How do I distinguish credible RLIM staining from an IHC artefact?
Look for reproducible staining in intact cells with a clear nuclear component, consistent with RLIM's nuclear annotation and supported nucleoplasmic location (UniProt Q9NVW2; HPA subcellular). Record cell identity rather than assuming every stained cell is equivalent: tissue IHC reports cytoplasmic and nuclear expression across tissues, with low consistency against RNA expression (HPA tissue IHC). Suspect artefact when signal tracks section edges, necrosis, or a no primary control, or when brown deposits follow endogenous peroxidase activity (standard IHC practice). Interpret cytoplasmic only staining cautiously because cytosol is an uncertain additional location in subcellular imaging (HPA subcellular).
Boster reagents

Best RLIM / E3 ubiquitin-protein ligase RLIM IHC Antibodies

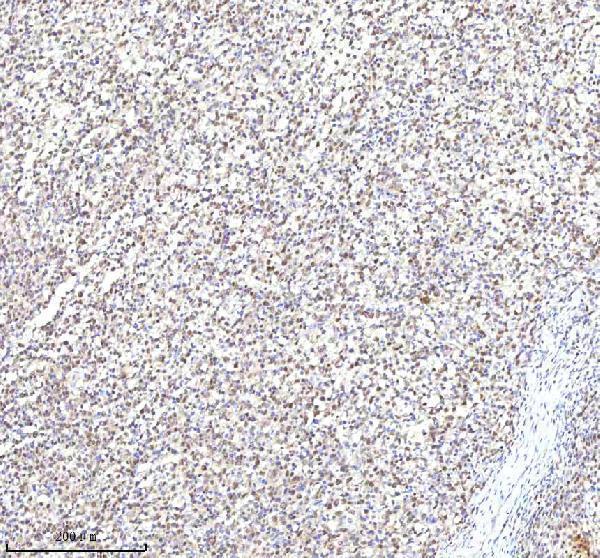
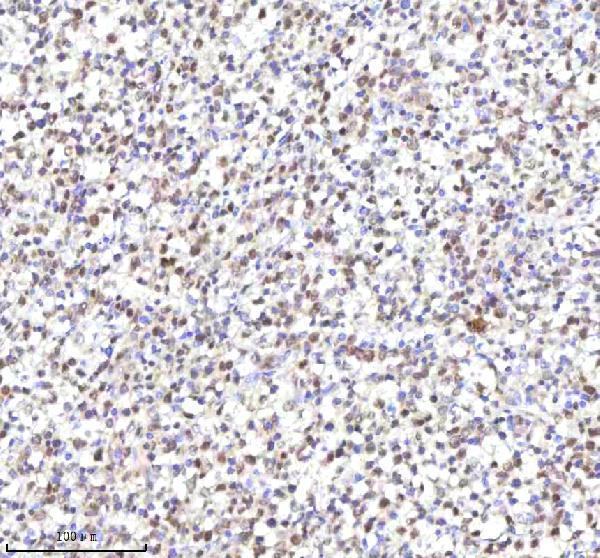
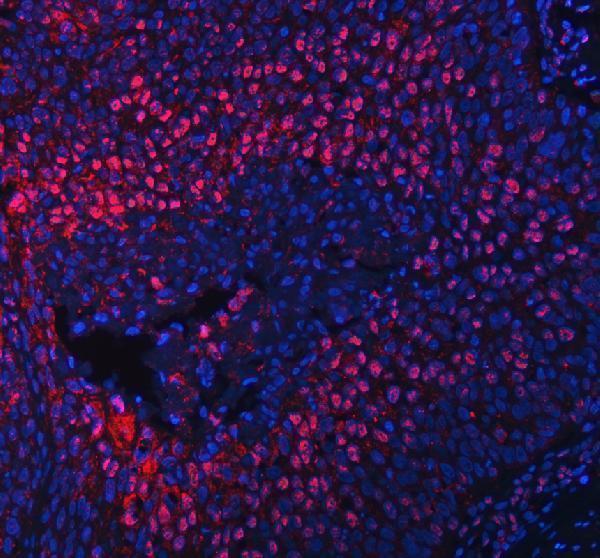
The catalog antibody has IHC images from paraffin sections of human lymphoma and esophageal carcinoma, plus an IF image from human esophageal carcinoma (A05428-1 image captions).

Real IHC data IHC analysis of RLIM using anti-RLIM antibody (A05428-1). RLIM was detected in a paraffin-embedded section of diffuse large B-cell lymphoma of human intestine tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-RLIM Antibody (A05428-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-RLIM Antibody ®
Cat # A05428-1

A05428-1 is the sole SKU; its IHC images show human intestinal diffuse large B-cell lymphoma and esophageal squamous carcinoma in paraffin sections (A05428-1 IHC captions). Its IF image shows human esophageal squamous carcinoma in a paraffin section (A05428-1 IF caption).

Which to pick: For tissue IHC, choose A05428-1: its paraffin-section captions document EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml; the fixative is unreported (A05428-1 IHC captions). For IF, A05428-1 has a human tissue image at 5 μg/ml, while ICC is not listed as a tested application (A05428-1 IF caption; catalog applications). Its stated reactivity includes human, mouse and rat, but the supplied IHC and IF images show human tissue only (A05428-1 catalog reactivity; image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NVW2 (RNF12_HUMAN, E3 ubiquitin-protein ligase RLIM).
  2. Human Protein Atlas. RLIM tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. RLIM subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. RLIM antibody validation summary (1 antibodies).
  5. Sequential stabilization of RNF220 by RLIM and ZC4H2 during cerebellum development and Shh-group medulloblastoma progression. Journal of molecular cell biology 2022 — PMC8982406.
  6. RLIM suppresses hepatocellular carcinogenesis by up-regulating p15 and p21. Oncotarget 2017 — PMC5669951.
  7. Functional activity of RLIM/Rnf12 is regulated by phosphorylation-dependent nucleocytoplasmic shuttling. Molecular biology of the cell 2013 — PMC3784382.
  8. An RNF12-USP26 amplification loop drives germ cell specification and is disrupted by disease-associated mutations. Science signaling 2022 — PMC7613676.
  9. PubMed PMID:10508479 — UniProt-cited evidence.
  10. PubMed PMID:11013082 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.