This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan RNF220 paraffin IHC around cytoplasmic staining in most tissues (HPA tissue IHC). Compare positive and undetected cell populations reported by HPA, and interpret staining cautiously because antibody staining has low consistency with RNA expression (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic in most tissues (HPA tissue IHC); nucleus annotated (UniProt) | |
| Staining pattern | Cytoplasmic staining in cells of most tissues (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A11818-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Low consistency between staining and RNA data (HPA tissue IHC) | |
| Regulation | Abundant in brain and spinal cord (UniProt) | |
| Isoform / epitope | 2 isoforms; verify epitope coverage (UniProt) |
The catalog antibody’s paraffin IHC protocol is supplemented by published RNF220 staining methods for human medulloblastoma and mouse frozen tissue (PMC8982406; PMC10400574; PMC8373269).
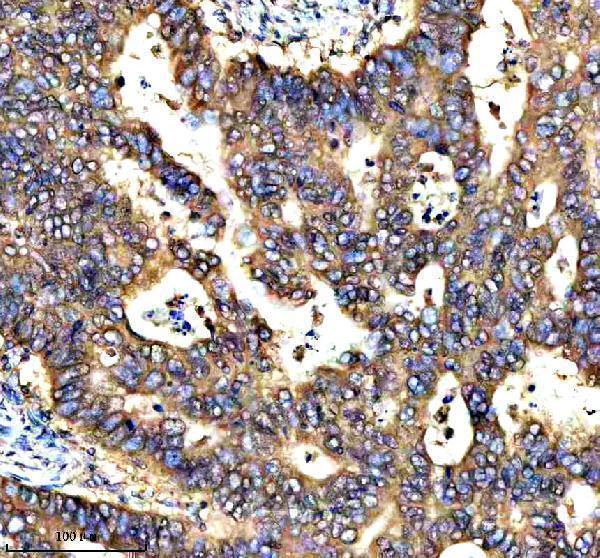
| Sample | Paraffin-embedded human stomach cancer tissue; fixative not specified (datasheet A11818-1) |
| Fixation | Image fixative and duration unreported (datasheet A11818-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A11818-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A11818-1) |
| Primary antibody | Rabbit anti-RNF220, 2-5 μg/ml (datasheet A11818-1) |
| Primary incubation | Overnight at 4 °C (datasheet A11818-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A11818-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | RNF220-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
In paraffin-section IHC, expect mainly cytoplasmic RNF220 staining in expressing cells, including caudate and hippocampal neurons, cerebral-cortex glia, and cerebellar molecular-layer cells (HPA: tissue IHC). RNF220 is also annotated in the nucleus and has no transmembrane segment (UniProt Q5VTB9: subcellular location and topology). HPA rates the tissue staining “Approved,” while reporting low consistency with RNA expression and pending external verification (HPA: tissue IHC reliability).
| Moderate cytoplasmic staining in caudate or hippocampal neurons, cerebral-cortex glia, or cerebellar molecular-layer cells (HPA: tissue IHC). | This matches the reported tissue IHC distribution and provides a useful slide-level positive reference (HPA: tissue IHC). Compare signal with adjacent cells and the negative control; “Medium” is HPA’s reported level, not a universal intensity threshold for every stain (HPA: tissue IHC; general IHC practice). |
| Predominantly nuclear chromogenic staining, with little cytoplasmic signal, in an otherwise positive tissue (HPA: tissue IHC). | Treat a nuclear-only IHC result as a compartment mismatch requiring control review: HPA describes cytoplasmic tissue staining (HPA: tissue IHC). Nuclear localisation remains biologically plausible because UniProt lists the nucleus and HPA supports nucleoplasmic ICC-IF localisation (UniProt Q5VTB9: subcellular location; HPA: subcellular ICC-IF). |
| Strong staining in adipocytes or heart-muscle cardiomyocytes, which HPA scores “Not detected” (HPA: tissue IHC). | Check for antibody cross-reactivity or endogenous chromogenic detection activity before assigning that signal to RNF220 (general IHC practice). HPA’s “Not detected” calls are observations for its tissue assay, not proof that every specimen must be negative (HPA: tissue IHC and reliability). |
| Brown colour spread broadly across cells or tissue, without a readable cytoplasmic pattern (HPA: tissue IHC profile). | Diffuse background prevents a reliable RNF220 localisation call. Review the negative control and detection conditions for nonspecific binding or endogenous activity, then judge whether cell boundaries and compartments become distinguishable (general IHC practice). |
| No specific staining in caudate neurons or hippocampal neurons, both scored “Medium” by HPA (HPA: tissue IHC). | First check that the tissue, staining run, and controls are interpretable; an absent signal in a reported positive cell population can reflect assay performance or specimen variation (HPA: tissue IHC; general IHC practice). HPA’s low RNA–staining consistency also limits how confidently one negative slide can be interpreted biologically (HPA: reliability). |
| Which compartment should guide paraffin-section IHC interpretation? | Use HPA’s predominantly cytoplasmic tissue profile while allowing that RNF220 can occupy the nucleus (HPA: tissue IHC; UniProt Q5VTB9: subcellular location). A nuclear signal alone does not establish a correct chromogenic result; interpret it with tissue context and controls (general IHC practice). |
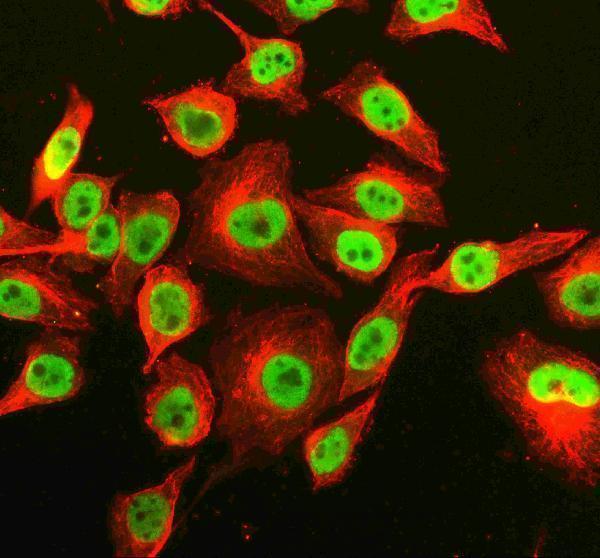
| What should IF/ICC show? | HPA reports supported nucleoplasmic localisation in ICC-IF and lists images from HEK293, MCF-7, and U2OS cells (HPA: subcellular ICC-IF). That observation comes from a different assay and does not replace the cytoplasmic tissue IHC profile (HPA: subcellular ICC-IF and tissue IHC). |
| How strong is the tissue-pattern evidence? | The tissue IHC assessment is “Approved,” but HPA reports low consistency between staining and RNA expression and says external verification is pending (HPA: tissue IHC reliability). Use the listed positive and “Not detected” cell populations as comparison points, with that limitation visible in the interpretation (HPA: tissue IHC). |
| Can molecular structure explain a membrane pattern? | UniProt annotates no transmembrane segment, and lists cytoplasmic and nuclear localisation (UniProt Q5VTB9: topology and subcellular location). A sharply membrane-restricted IHC pattern therefore needs control review before attribution to RNF220; these annotations do not identify the cause of that pattern (general IHC practice). |
| Do isoforms or processing predict a different stain? | UniProt lists 2 isoforms, no signal peptide or propeptide, and a 1–566 chain (UniProt Q5VTB9: isoforms and processing). Those annotations alone do not establish isoform-specific staining, epitope recognition, shedding, or fixation sensitivity for the antibody used (UniProt Q5VTB9: annotations). |
| Situation | Likely cause | Next action |
|---|---|---|
| A reported positive cell population has no visible signal (HPA: tissue IHC). | The stain may have failed, or the specimen may differ from HPA’s example; absent staining alone cannot distinguish those explanations (general IHC practice; HPA: tissue IHC reliability). | Check the run’s positive and negative controls, tissue integrity, and detection steps; compare another HPA-listed positive population before scoring the specimen negative (HPA: tissue IHC; general IHC practice). |
| Only nuclei stain in a tissue section (HPA: tissue IHC profile). | The result differs from HPA’s mainly cytoplasmic IHC profile, although nuclear RNF220 is annotated and nucleoplasmic ICC-IF staining is supported (HPA: tissue IHC and subcellular ICC-IF; UniProt Q5VTB9: subcellular location). | Inspect negative controls and cell morphology, then report the nuclear pattern separately from the expected tissue IHC pattern; avoid calling it artefact or confirmed RNF220 solely from localisation (general IHC practice). |
| Adipocytes or cardiomyocytes stain prominently (HPA: tissue IHC). | HPA reports RNF220 as “Not detected” in those cell types; cross-reactivity or endogenous detection activity is a possible explanation for an unexpected chromogenic signal (HPA: tissue IHC; general IHC practice). | Compare the negative control and a reported positive cell population on the same run; assess endogenous peroxidase activity when using peroxidase-based detection (HPA: tissue IHC; general IHC practice). |
| Colour is diffuse and cell compartments cannot be resolved (HPA: tissue IHC profile). | Nonspecific antibody or detection background can obscure a cytoplasmic signal (general IHC practice). | Review blocking, antibody concentration, washing, and detection exposure using appropriate controls; score RNF220 only after cellular staining can be distinguished from background (general IHC practice). |
| Signal appears membrane-restricted (UniProt Q5VTB9: topology). | A membrane-only pattern is difficult to reconcile with the annotated absence of a transmembrane segment and the reported cytoplasmic tissue pattern (UniProt Q5VTB9: topology; HPA: tissue IHC). | Check tissue morphology and negative controls, then compare the same run with an HPA-listed positive cell population before attributing the membrane signal to RNF220 (HPA: tissue IHC; general IHC practice). |
| IHC looks cytoplasmic while a separate IF/ICC image looks nucleoplasmic (HPA: tissue IHC and subcellular ICC-IF). | HPA reports those different patterns across tissue IHC and ICC-IF, and UniProt annotates both cytoplasm and nucleus (HPA: tissue IHC and subcellular ICC-IF; UniProt Q5VTB9: subcellular location). | Interpret each assay against its own reported pattern and controls; do not use the ICC-IF observation alone to reject a readable cytoplasmic tissue IHC result (HPA: tissue IHC and subcellular ICC-IF; general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Cells in molecular layer | Medium | Protein (IHC) | HPA → |
| Cerebral cortex | Glial cells | Medium | Protein (IHC) | HPA → |
| Endometrium | Glandular cells | Low | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot RNF220 staining in paraffin sections by checking retrieval, cellular localisation, controls and scoring before interpreting signal (datasheet A11818-1; HPA tissue IHC).
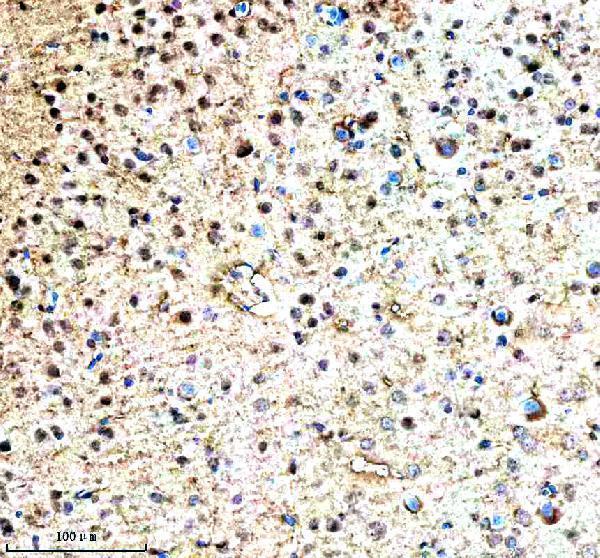
The IHC-validated anti-RNF220 antibody has paraffin-section images from human stomach cancer and mouse and rat brain, plus an IF/ICC image from HeLa cells (A11818-1 image captions).
The sole card, A11818-1, lists IHC for human, mouse and rat and shows staining in paraffin-embedded human stomach cancer, mouse brain and rat brain sections (catalog applications/reactivity; A11818-1 IHC captions). It also lists IF/ICC and shows RNF220 staining in HeLa cells (catalog applications; A11818-1 IF caption).
Which to pick: Choose A11818-1 for chromogenic tissue IHC: its paraffin-section captions report EDTA pH 8 antigen retrieval and DAB detection; the fixative is unreported (A11818-1 IHC captions). For IF/ICC, the same SKU has a HeLa-cell fluorescence image and a listed IF/ICC application (A11818-1 IF caption; catalog applications). For cross-species IHC, its captions show human, mouse and rat sections, matching its listed reactivity (A11818-1 IHC captions; catalog reactivity).