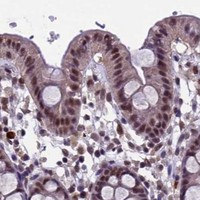
RNF40 / E3 ubiquitin-protein ligase BRE1B · IHC design guide

Design Immunohistochemistry for RNF40

Plan RNF40 paraffin IHC around mainly nuclear staining in most cell types, with unstained adipocytes as a comparison (HPA tissue IHC). This guide covers the catalog antibody’s 2–5 μg/ml IHC range and chromogenic detection (datasheet A06979-2).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RNF40 (IHC for RNF40): expected localisation Mainly nuclear in most cell types (HPA tissue IHC), antibody A06979-2, validated IHC image, and IHC protocol steps
Printable RNF40 IHC protocol sheet — expected localisation Mainly nuclear in most cell types (HPA tissue IHC), antibody A06979-2, controls and protocol steps. Open the full RNF40 IHC guide →

RNF40 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Mainly nuclear in most cell types (HPA tissue IHC)
Staining pattern Variable nuclear staining in most cells; adipocytes unstained (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06979-2)
Positive control ⓘ Cerebral cortex+4 more · see all
Negative control ⓘ Adipose tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A06979-2)
Caveat Adipocytes may be unstained despite broad tissue expression (HPA tissue IHC)
Regulation Higher expression in testis, heart and pancreas (UniProt)
Isoform / epitope 3 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended RNF40 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by 2 published RNF40 IHC protocols with methods stated in the supplied excerpts (PMC5007379; PMC12210586).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet A06979-2)
FixationImage fixative and duration unreported (datasheet A06979-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06979-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06979-2)
Primary antibodyRabbit anti-RNF40, 2-5 μg/ml (datasheet A06979-2)
Primary incubationOvernight at 4 °C (datasheet A06979-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A06979-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
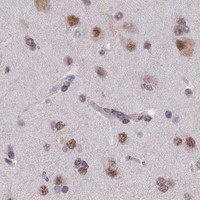
Expected resultRNF40-positive staining in neuropil of cerebral cortex (HPA tissue IHC: High). HPA tissue profile: Mainly nuclear expression at variable levels in essentially all cell types, except in adipose cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A06979-2); the published protocols used different retrieval conditions (PMC5007379; PMC12210586).
Section 2

What Is the Expected RNF40 Staining Pattern?

RNF40 is expected mainly in nuclei across most cell types (UniProt O75150: nucleus; HPA tissue IHC: mainly nuclear). HPA reports variable staining and no detection in adipocytes (HPA tissue IHC). Its IHC tissue profile is Approved, with medium consistency between staining and RNA data (HPA tissue IHC). RNF40 has no annotated transmembrane segment (UniProt O75150 topology).

What am I looking at on my slide?
Nuclear staining in rectal, stomach, or epididymal glandular cells.This fits the reported high signal in those cells and the mainly nuclear tissue pattern (HPA tissue IHC). Score the stained nuclei against nearby cells and the run control; intensity can vary across cell types (HPA tissue IHC; standard IHC practice).
Predominantly cytoplasmic or membrane staining, with little nuclear signal.That distribution conflicts with RNF40’s nuclear annotation and the mainly nuclear IHC profile (UniProt O75150; HPA tissue IHC). Treat it as a possible staining artefact or off-target signal; review morphology and controls before assigning it to RNF40 (standard IHC practice).
Clear staining in adipocytes.HPA reports RNF40 as not detected in adipocytes (HPA tissue IHC). Investigate cross-reactivity, endogenous detection activity, or misidentified cells; an isolated unexpected stain does not establish RNF40 expression (standard IHC practice).
Diffuse colour across cells, stroma, or the whole section.A widespread, poorly defined deposit cannot be scored as the expected nuclear pattern (HPA tissue IHC; standard IHC practice). Check a reagent control and inspect washing, blocking, and chromogen development before interpreting faint nuclei (standard IHC practice).
No nuclear signal in a section containing expected positive glandular cells.Absence in rectal, stomach, or epididymal glandular cells conflicts with their reported high staining (HPA tissue IHC). Check the same-run positive control and detection steps first; a failed run cannot support a tissue-negative conclusion (standard IHC practice).
💡Expected RNF40 appearanceA convincing positive result shows variable, mainly nuclear staining in expected cell types, including strongly stained rectal, stomach, or epididymal glandular cells; isolated adipocyte or dominant membrane staining warrants investigation (HPA tissue IHC; UniProt O75150; standard IHC practice).
How each factor affects the staining
Tissue choice and cell identityHPA reports high glandular-cell staining in rectum, stomach, and epididymis, medium staining in several other sampled cells, and no detection in adipocytes (HPA tissue IHC). Compare like cell types when choosing a control; whole-tissue appearance alone can obscure a cell-specific pattern (standard IHC practice).
A special case in cerebral cortexNeuropil is listed as high in the HPA tissue table, alongside an overall mainly nuclear profile (HPA tissue IHC). Assess cortical signal in its tissue context; neuropil staining alone is a poor substitute for confirming the expected nuclear pattern elsewhere (HPA tissue IHC; standard IHC practice).
IHC antibody evidenceHPA041330 is IHC Approved, while HPA054227 has no listed IHC status (HPA antibodies). The overall tissue profile is Approved with medium staining–RNA consistency, so unexpected staining still calls for appropriate controls (HPA tissue IHC; standard IHC practice).
Isoforms and protein annotationUniProt lists isoforms 1, 3, and 4, one annotated chain spanning residues 1–1001, and no signal peptide or propeptide (UniProt O75150). These annotations do not identify the antibody epitope or establish an isoform-specific staining pattern (UniProt O75150).
IF/ICC Q&A: What should an IF cross-check show?HPA supports nucleoplasmic localization in ICC-IF images from A-431, HeLa, and U2OS; HPA054227 is ICC Supported (HPA subcellular; HPA antibodies). Use that as a localization comparison, while interpreting paraffin-section staining against the tissue IHC evidence (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive glandular cells have no nuclear stain.The reported high IHC signal makes a technical failure plausible, although one section cannot identify its cause (HPA tissue IHC; standard IHC practice).Review the same-run positive control, primary-antibody step, retrieval record, and chromogenic detection; repeat with controlled conditions before calling the tissue negative (standard IHC practice).
The stain is mostly cytoplasmic or outlines cell membranes.This differs from the mainly nuclear tissue pattern and nuclear UniProt annotation (HPA tissue IHC; UniProt O75150). Off-target staining or precipitate is possible (standard IHC practice).Check morphology and reagent controls, then repeat the stain and score only reproducible, cell-associated signal in the expected compartment (standard IHC practice).
Adipocytes appear positive.Adipocytes are reported as not detected, so cross-reactivity or endogenous detection activity should be considered (HPA tissue IHC; standard IHC practice).Confirm cell identity; compare a reagent control and assess endogenous enzyme activity for the chromogen system used (standard IHC practice).
Colour is diffuse over the section.Nonspecific reagent binding, insufficient washing, or excess chromogen development can obscure nuclear detail (standard IHC practice).Inspect the reagent control; review blocking, wash consistency, detection timing, and whether nuclei remain distinguishable (standard IHC practice).
Staining varies sharply between otherwise comparable areas.RNF40 levels can vary among cell types, while uneven staining can also arise during a run (HPA tissue IHC; standard IHC practice).Compare the same cell type across intact areas and the same-run control; investigate uneven reagent coverage before interpreting the difference biologically (standard IHC practice).
Cortical neuropil stains strongly but nuclei are uncertain.HPA lists high neuropil staining while summarizing tissue expression as mainly nuclear (HPA tissue IHC). That combination needs compartment-specific interpretation (standard IHC practice).Document neuropil and nuclear signal separately; verify nuclear staining in an expected positive glandular control before treating neuropil signal as confirmation (HPA tissue IHC; standard IHC practice).

Sample controls for RNF40 IHC & IF

🧪Run stomach first: its glandular cells show High RNF40 staining (HPA: High in stomach glandular cells). Use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes); on the stomach slide, cells serving as internal negatives should lack specific nuclear staining, without assuming any named cell type is negative because RNF40 is ubiquitously expressed (UniProt O75150 tissue specificity; UniProt O75150 nucleus).
Positive control tissue: Cerebral cortex (Neuropil, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RNF40 in A-431, HeLa, U2OS, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and rabbit IgG controls matched to the primary antibody’s isotype and clonality (selected A06979-2 tissue-IHC caption: rabbit primary); use RNF40 knockout material as a biological specificity control. Quench endogenous peroxidase and assess background before interpreting HRP/DAB staining (selected A06979-2 tissue-IHC caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A06979-2 tissue-IHC caption does not state the fixative. The reported paraffin-section staining used heat retrieval in EDTA at pH 8.0, so that is a documented starting condition; whether retrieval is essential is unreported (selected A06979-2 tissue-IHC caption). Frozen sections cannot be judged easier from the supplied evidence; IF/ICC has separate nucleoplasmic localisation evidence (HPA: supported nucleoplasm), while HRP/DAB stomach sections require attention to endogenous peroxidase background (selected A06979-2 tissue-IHC caption: HRP/DAB detection).

HPA tissue IHC evidence for RNF40

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebral cortex Neuropil High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Rectum Glandular cells High Protein (IHC) HPA →
Stomach Glandular cells High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced RNF40 IHC Tips

Troubleshoot RNF40 staining in paraffin sections by checking nuclear localisation, section controls, and the conditions documented for the catalog antibody (UniProt O75150; datasheet A06979-2).

Which retrieval conditions should I try first for weak RNF40 staining?
Start with heat-mediated antigen retrieval in EDTA buffer at pH 8.0 (datasheet A06979-2). The documented paraffin-section example then used 2 μg/ml catalog antibody overnight at 4°C; keep these conditions constant while assessing retrieval (datasheet A06979-2). Record the heating and cooling times because the caption specifies neither, and compare sections processed in the same run (datasheet A06979-2; standard IHC practice). If nuclear signal remains weak, vary retrieval duration on matched sections before considering another buffer as a fallback (UniProt O75150: nucleus; standard IHC practice). Judge improvement by nuclear signal alongside preserved morphology and low background in the negative control (UniProt O75150: nucleus; standard IHC practice).
Could fixation explain inconsistent nuclear RNF40 staining?
The catalog image shows a paraffin-embedded section, but its caption does not state the fixative, so RNF40-specific fixation sensitivity is unknown (datasheet A06979-2). Record fixative, time before fixation, fixation duration, and processing history for each specimen before comparing staining intensity (standard IHC practice). For a pilot, stain matched sections together using the documented pH 8.0 EDTA retrieval and 2 μg/ml overnight antibody incubation (datasheet A06979-2; standard IHC practice). Compare nuclear staining with morphology and a consistently processed positive control, since damaged or unevenly processed tissue can complicate interpretation (UniProt O75150: nucleus; standard IHC practice). Do not assign a fixation threshold or preferred fixative to RNF40 without a direct comparison (datasheet A06979-2: fixative unreported).
Should RNF40 staining be nuclear throughout the section?
Expect predominantly nuclear staining: UniProt assigns RNF40 to the nucleus, and HPA supports nucleoplasmic localisation (UniProt O75150: nucleus; HPA subcellular: supported nucleoplasm). HPA tissue IHC reports variable nuclear expression in essentially all cell types except adipose cells, so intensity need not be uniform (HPA tissue IHC: Approved). Compare nuclei within the same cell population and use a counterstain to separate weak nuclear signal from surrounding chromogen (HPA tissue IHC: variable nuclear expression; standard IHC practice). Persistent cytoplasmic or extracellular colour without corresponding nuclear signal warrants checks of blocking, detection, and section quality (UniProt O75150: nucleus; standard IHC practice). Treat apparent neuropil staining cautiously because HPA also lists high signal there despite its mainly nuclear summary (HPA tissue IHC: cerebral cortex neuropil, High).
How could isoforms or epitope accessibility affect this IHC result?
RNF40 has 3 listed isoforms, numbered 1, 3, and 4, but the supplied caption does not map the catalog antibody epitope (UniProt O75150: isoforms; datasheet A06979-2). Consequently, staining cannot establish which isoform is present in a particular nucleus (UniProt O75150: isoforms; standard IHC interpretation). RNF40 has no annotated transmembrane segment and has listed acetyllysine and phosphoserine residues; neither fact establishes how fixation or retrieval affects this antibody (UniProt O75150: topology and modified residues). Ask for epitope mapping or validate with an independent antibody before making isoform-specific claims (standard IHC practice). When comparing specimens, keep pH 8.0 EDTA retrieval constant so a processing change does not masquerade as a biological difference (datasheet A06979-2; standard IHC practice).
How should I investigate RNF40 by multiplex IF after IHC?
Use a separate IF/ICC optimisation: HPA reports nucleoplasmic RNF40 in ICC/IF images from A-431, HeLa, and U2OS, without supplying fixation conditions here (HPA subcellular). Pair RNF40 with a marker identifying the cell population being assessed, such as a glandular-cell marker when examining the HPA-listed glandular compartments (HPA tissue IHC: glandular cells; standard IF practice). Choose spectrally separated fluorophores and place the weaker readout away from prominent tissue autofluorescence, using single-colour and unstained controls (standard IF practice). Because RNF40 is nuclear and has no transmembrane segment, optimise permeabilisation for access to an intracellular nuclear epitope while preserving nuclear morphology (UniProt O75150: nucleus and topology; standard IF practice). Do not transfer the paraffin IHC incubation as an established IF dilution (datasheet A06979-2: IHC caption).
What causes diffuse or granular background in RNF40 chromogenic IHC?
First compare the stained section with a no-primary control; colour in both implicates the detection workflow or tissue rather than demonstrated RNF40 binding (standard IHC practice). Include a peroxidase block before HRP detection and inspect endogenous pigment, folds, and tissue edges before scoring DAB (standard IHC practice). The documented example used 10% goat-serum blocking, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase-conjugated secondary for 30 minutes at 37°C (datasheet A06979-2). If background persists, assess antibody concentration and blocking on matched sections while retaining the documented pH 8.0 EDTA retrieval (datasheet A06979-2; standard IHC practice). Credible RNF40 signal should favour nuclei over diffuse extracellular colour (UniProt O75150: nucleus; standard IHC interpretation).
How should I score variable RNF40 nuclear staining? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable tissue area before scoring, then count nuclear-positive cells against all eligible nuclei in that population (HPA tissue IHC: variable nuclear expression; standard IHC practice). Report percentage positive and an H-score from 0–300 using the same intensity categories and threshold across slides (standard IHC scoring). If cell abundance differs substantially, add positive-nucleus density per mm² and retain the area denominator (standard IHC scoring). Normalise nuclear positivity to eligible nuclei, rather than total section area, when comparing cell populations (standard IHC scoring). Score matched sections with the same retrieval, detection, and imaging conditions; HPA rates tissue staining Approved but notes only medium consistency with RNA expression (datasheet A06979-2; HPA tissue IHC: reliability).
How can I distinguish true RNF40 staining from artefact?
Favour signal that resolves to nuclei in intact, viable cells, consistent with UniProt nuclear assignment and HPA-supported nucleoplasmic localisation (UniProt O75150: nucleus; HPA subcellular). Compare the suspected positive cells with nearby morphology and expected tissue patterns; HPA describes variable nuclear expression and reports adipocytes as undetected (HPA tissue IHC: Approved; adipose tissue, Not detected). Treat colour concentrated at section edges, folds, or necrotic areas as suspect until matched controls exclude a processing effect (standard IHC practice). A no-primary control helps reveal endogenous enzyme or detection-associated colour, while a positive control checks that the staining run worked (standard IHC practice). Do not equate RNF40 staining intensity with H2BK120ub1 activity without measuring that downstream mark separately (UniProt O75150: RNF20/40 function; standard IHC interpretation).
Boster reagents

Best RNF40 / E3 ubiquitin-protein ligase BRE1B IHC Antibodies

RNF40 IHC images cover human paraffin sections, and an IF image covers a human paraffin section (A06979-2 image captions); a second antibody lists human, mouse and rat reactivity (M06979-1 catalog).

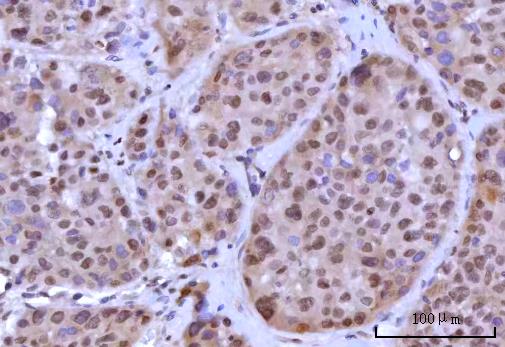
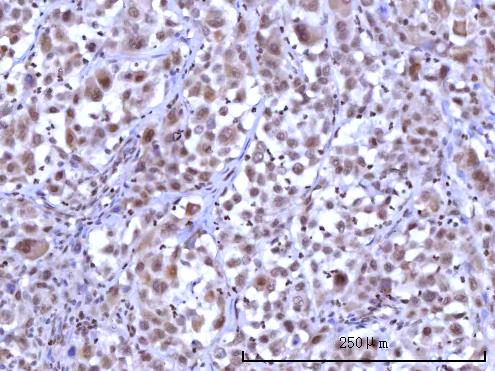
Real IHC data IHC analysis of RNF40 using anti-RNF40 antibody (A06979-2). RNF40 was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-RNF40 Antibody (A06979-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-RNF40 Antibody ®
Cat # A06979-2

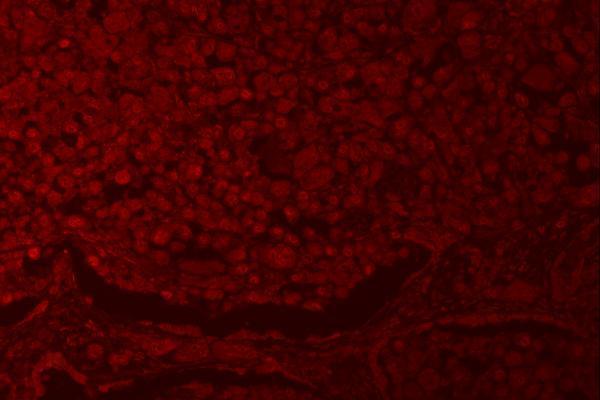
A06979-2 has IHC images from human paraffin sections of liver cancer, lung adenocarcinoma and testicular seminoma, plus an IF image from a human paraffin section of lung cancer (A06979-2 image captions). M06979-1 lists IHC and human, mouse and rat reactivity, but supplies no IHC or IF image (M06979-1 catalog).

Which to pick: For tissue IHC, start with A06979-2 because its own captions document paraffin section staining at 2 μg/ml after EDTA pH 8.0 retrieval; the fixative is unreported (A06979-2 IHC image captions). For tissue IF, A06979-2 has a paraffin section image at 5 μg/ml, while ICC validation is unreported (A06979-2 IF image caption and application list). For mouse or rat studies, M06979-1 is the rabbit monoclonal option listing those species and IHC, though its catalog supplies no IHC image or tissue processing details (M06979-1 catalog).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O75150 (BRE1B_HUMAN, E3 ubiquitin-protein ligase BRE1B).
  2. Human Protein Atlas. RNF40 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. RNF40 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. RNF40 antibody validation summary (2 antibodies).
  5. RNF40 epigenetically modulates glycolysis to support the aggressiveness of basal-like breast cancer. Cell death & disease 2023 — PMC10539310.
  6. The histone H2B ubiquitin ligase RNF40 is required for HER2-driven mammary tumorigenesis. Cell death & disease 2020 — PMC7568723.
  7. Ubiquitin ligase RNF20/40 facilitates spindle assembly and promotes breast carcinogenesis through stabilizing motor protein Eg5. Nature communications 2016 — PMC5007379.
  8. RNF20/RNF40 supports the aggressive behavior in cervical cancer by regulating a peroxisome-based anti-ferroptotic mechanism. Cell communication and signaling : CCS 2025 — PMC12210586.
  9. PubMed PMID:10944455 — UniProt-cited evidence.
  10. PubMed PMID:9734811 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.