RPA1 / Replication protein A 70 kDa DNA-binding subunit · IHC design guide

Design Immunohistochemistry for RPA1

Plan chromogenic RPA1 IHC in paraffin sections around the general nuclear staining pattern reported in tissue (HPA tissue IHC). This guide covers fixation consistency, tissue controls and interpretation of possible PML-body enrichment in cells with alternative lengthening of telomeres (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RPA1 (IHC for RPA1): expected localisation General nuclear staining in tissue (HPA tissue IHC), antibody M01317-1, validated IHC image, and IHC protocol steps
Printable RPA1 IHC protocol sheet — expected localisation General nuclear staining in tissue (HPA tissue IHC), antibody M01317-1, controls and protocol steps. Open the full RPA1 IHC guide →

RPA1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General nuclear staining in tissue (HPA tissue IHC)
Staining pattern Nuclear staining across many tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M01317-1)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat PML-body enrichment may vary with ALT status (UniProt)
Regulation DNA damage recruits RPA1 to chromatin (UniProt)
Isoform / epitope 0 annotated isoforms; Met1 removal may affect an N-terminal epitope (UniProt)
Section 1

Recommended RPA1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with published RPA1 staining protocols for breast, glioma and head and neck tissue (PMC10063624; PMC12235235; PMC6139602).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet M01317-1)
FixationImage fixative and duration unreported (datasheet M01317-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M01317-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M01317-1)
Primary antibodyRabbit monoclonal (clone BB-18) anti-RPA1, 1:50 (datasheet M01317-1)
Primary incubationOvernight at 4 °C (datasheet M01317-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M01317-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRPA1-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA, pH 8.0 (datasheet: M01317-1); the published protocols used citrate, pH 6.0 (PMC10063624; PMC12235235; PMC6139602).
Section 2

What Is the Expected RPA1 Staining Pattern?

RPA1 should stain nuclei across many cell types in paraffin sections (HPA: general nuclear expression; low tissue specificity). HPA reports high staining in several epithelial, neural, adipose and hematopoietic cell populations, with overall tissue IHC reliability rated Supported and medium consistency with RNA data (HPA: tissue IHC). Its nuclear location and lack of a transmembrane segment support a nuclear, rather than membrane, interpretation (UniProt P27694: subcellular location; topology).

What am I looking at on my slide?
Nuclear chromogen in the expected cells, with cell boundaries and nuclear counterstain still readable.This fits the reported general nuclear pattern (HPA: tissue IHC). Compare nuclei within each cell population; an HPA High designation describes observed staining in that population, not a requirement that every nucleus stain equally (HPA: tissue IHC; general IHC practice).
Predominantly cytoplasmic, membranous or extracellular color, with little convincing nuclear signal.The compartment disagrees with the reported nuclear location and lack of a transmembrane segment (UniProt P27694: subcellular location; topology). Review staining controls and reagent background before assigning this color to RPA1 (general IHC practice).
Strong staining in an unexpected cell population while expected nuclei show little or no signal.Treat identity and specificity as unresolved. Cross-reactivity or endogenous detection activity can mimic a positive result (general IHC practice). HPA reports broad expression and lists no negative tissue here, so an unlisted cell population alone cannot establish a false positive (HPA: tissue IHC).
Haze or granular color extends across nuclei, cytoplasm and surrounding section.Diffuse color without clear nuclear enrichment does not match the reported pattern (HPA: tissue IHC). Background from detection reagents, inadequate blocking or residual reagent can obscure the result; inspect a negative reagent control and the tissue morphology (general IHC practice).
No nuclear signal in a section containing one of the HPA High cell populations.A technical failure is plausible, but a single blank section does not prove RPA1 absence. Confirm that the relevant cells are present, then examine positive controls and detection performance (HPA: tissue IHC; general IHC practice). HPA supplies no target-specific fixation sensitivity here.
💡Expected RPA1 appearanceCall a section positive when interpretable nuclear staining is present in the relevant cells, potentially strong in HPA High populations; dominant cytoplasmic, membranous or diffuse color is suspect (HPA: tissue IHC; UniProt P27694: subcellular location; topology).
How each factor affects the staining
CompartmentScore nuclei as the primary compartment (HPA: general nuclear expression; UniProt P27694: nucleus). PML body enrichment is reported for cells using alternative lengthening of telomeres; it is not a required appearance in routine tissue IHC (UniProt P27694: subcellular location).
Tissue and cell contextHPA reports High staining in adipocytes, adrenal and breast glandular cells, bone marrow hematopoietic cells, bronchial respiratory epithelial cells, caudate glia, cerebellar Purkinje cells and cortical neurons (HPA: tissue IHC). These examples guide a positive tissue check; no negative tissue is supplied (HPA: tissue IHC).
Strength of evidenceThe overall tissue IHC profile is Supported, with medium staining–RNA consistency (HPA: tissue IHC). The listed IHC antibodies HPA006914 and CAB004563 are each Supported; the supplied record does not rate either IHC antibody Enhanced (HPA: antibody validation). Interpret unusual patterns with controls.
Assay-specific localisationHPA ICC-IF reports enhanced nucleoplasmic localisation, supporting a nuclear expectation while documenting a different assay (HPA: subcellular ICC-IF). Its ICC validation entry is for HPA046497; it does not establish an IHC-P protocol or tissue staining level for that antibody (HPA: antibody validation).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected nuclear staining is absent in a positive tissue check.The relevant HPA High cells may be missing from the section, or an IHC step may have failed; the record gives no RPA1-specific fixation explanation (HPA: tissue IHC; general IHC practice).Verify cell identity and morphology, then check the run's positive control, detection reagents and recorded antigen-retrieval conditions (general IHC practice). Do not infer a target-specific retrieval requirement from HPA.
Color is concentrated outside nuclei.A dominant cytoplasmic or membrane pattern conflicts with reported localisation (HPA: tissue IHC; UniProt P27694: subcellular location; topology). Detection background is another possibility (general IHC practice).Compare with a negative reagent control, check for precipitate and reassess whether nuclear staining survives background subtraction by visual inspection (general IHC practice).
Broad brown haze makes nuclei hard to distinguish.Nonspecific reagent binding, excess detection signal or insufficient removal of residual reagents can raise background (general IHC practice).Inspect a negative reagent control; review blocking, washing and detection conditions while preserving readable nuclear counterstain (general IHC practice).
A surprising cell type appears strongly positive.RPA1 has low tissue specificity, and the supplied HPA list contains examples rather than a complete set of positives and negatives (HPA: tissue IHC). Cross-reactivity or endogenous activity remains possible (general IHC practice).First verify nuclear localisation and cell identity. Compare a negative reagent control and an independently validated antibody result if available (HPA: tissue IHC; general IHC practice).
Tissue color persists in the negative reagent control.Endogenous detection activity or background from the detection system can produce color independent of primary antibody binding (general IHC practice).Check the detection chemistry and its appropriate blocking control; interpret RPA1 only after control color is resolved (general IHC practice).
Can IF/ICC establish the expected compartment?HPA reports enhanced nucleoplasmic localisation by ICC-IF, whereas this guide's primary readout is chromogenic tissue IHC (HPA: subcellular ICC-IF; tissue IHC).Use the separate IF/ICC guide for that assay. Treat its nucleoplasmic result as supporting localisation, while scoring this section against tissue IHC evidence and controls (HPA: subcellular ICC-IF; tissue IHC).

Sample controls for RPA1 IHC & IF

🧪Run breast tissue first and assess glandular-cell nuclei for RPA1 staining (HPA: breast glandular cells, High; UniProt P27694: nucleus). HPA detects RPA1 in all 45 scored tissues, so use no-primary and isotype controls instead of a negative tissue; erythrocytes on the positive slide, if present, should lack nuclear staining because they have no nuclei (HPA: no negative tissue; standard histology).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: RPA1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RPA1 in A-431, A-549, U2OS, HeLa BAC 4595, HeLa , with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section and a concentration- and clonality-matched rabbit IgG isotype control; use an RPA1 knockout sample processed alongside the positive sample as a biological negative (caption: rabbit primary; standard IHC practice). For breast sections developed with HRP/DAB, quench endogenous peroxidase and check for background staining (caption: breast section with HRP/DAB; standard IHC practice).
⚠️Feasibility: No supplied source reports an RPA1-specific fixation window or fixation effect, and the selected M01317-1 paraffin-section caption does not state the fixative (caption: fixative unreported). The caption uses heat-mediated EDTA retrieval at pH 8.0, but does not establish that retrieval is required; the supplied evidence also does not establish whether frozen sections or IF are easier (caption: EDTA retrieval; HPA: ICC-IF images). In breast sections, score glandular nuclei rather than empty lumina or adipocyte lipid spaces (HPA: breast glandular cells, High; UniProt P27694: nucleus; standard histology).

HPA tissue IHC evidence for RPA1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: RPA1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced RPA1 IHC Tips

Use nuclear staining and the selected antibody’s paraffin-section evidence to troubleshoot RPA1 chromogenic IHC (UniProt P27694; datasheet M01317-1).

What retrieval conditions should I start with for weak RPA1 staining?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet M01317-1). The selected tissue image used this retrieval before overnight incubation at 4°C with antibody diluted 1:50 (datasheet M01317-1). If nuclear staining remains weak, compare modest changes in heating time on matched sections while keeping detection and imaging conditions fixed (standard IHC practice). Judge each change by nuclear signal and tissue preservation, because the expected pattern is generally nuclear (HPA: general nuclear expression). Record the heating method and duration so that an apparent gain in signal can be reproduced (standard IHC practice).
Could fixation explain variable RPA1 staining across my sections?
Target-specific fixation sensitivity is unknown: the selected image identifies a paraffin-embedded breast cancer section but does not state its fixative (datasheet M01317-1). Record the fixative, fixation duration, tissue thickness and processing history for each specimen before comparing nuclear staining (standard IHC practice). If these differ, test matched sections with the stated EDTA pH 8.0 retrieval and 1:50 antibody dilution first (datasheet M01317-1). Compare viable regions with similar tissue preservation and assess background alongside nuclear signal (standard IHC practice). Do not attribute a fixation effect to RPA1 without a controlled comparison of specimens processed under documented conditions (standard IHC practice).
How should I troubleshoot RPA1 staining outside the nucleus?
Prioritise nuclear staining when assessing RPA1 in paraffin sections: tissue IHC shows general nuclear expression, and subcellular imaging places it in the nucleoplasm (HPA: tissue IHC; HPA: subcellular). RPA1 has no annotated transmembrane segment, so membrane outlining is inconsistent with its recorded topology (UniProt P27694 topology). Review cytoplasmic or membrane staining against a negative control, the DAB development time and tissue morphology before scoring it (standard IHC practice). Nuclear foci can be biologically plausible, but PML-body enrichment is reported specifically in cells displaying alternative lengthening of telomeres (UniProt P27694 localisation). Do not assign that mechanism from a chromogenic pattern alone (standard IHC interpretation).
Could processing or modifications change which RPA1 epitope my antibody detects?
No RPA1 isoforms are annotated, while the record lists full-length residues 1–616 and an N-terminally processed chain beginning at residue 2 (UniProt P27694 processing and isoforms). Annotated modifications include acetylation near residues 163 and 167 and phosphorylation at 180 and 191 (UniProt P27694 modified residues). The supplied antibody caption does not identify its epitope, so these annotations cannot establish whether the staining changes with processing or modification (datasheet M01317-1). For discrepant nuclear staining, compare controls processed together and check whether epitope-mapping information is available before proposing a modification-specific explanation (standard IHC practice). Keep retrieval conditions constant during that comparison (datasheet M01317-1).
How can companion IF help assess the nuclear IHC pattern?
For companion IF, multiplex RPA1 with a marker of the expected cell type, such as a glandular-cell marker when evaluating breast glandular cells (HPA: high expression in breast glandular cells; standard IF practice). Choose spectrally separated fluorophores and a channel with low tissue autofluorescence, then inspect single-channel images before interpreting overlap (standard IF practice). Because RPA1 is nucleoplasmic and has no transmembrane segment, use permeabilisation compatible with access to its nuclear epitope (HPA: subcellular; UniProt P27694 topology; standard IF practice). Include a nuclear counterstain and appropriate single-stain controls to assess localisation and bleed-through (standard IF practice). The supplied tissue caption documents chromogenic paraffin IHC, not an IF fixation condition (datasheet M01317-1).
How do I reduce diffuse DAB background without losing nuclear signal?
The selected paraffin-section image used 10% goat serum blocking, antibody at 1:50 overnight at 4°C, and a peroxidase-linked secondary for 30 minutes at 37°C (datasheet M01317-1). Use those documented conditions as a reference while changing one background-control step at a time (standard IHC practice). Add an endogenous peroxidase block before DAB development and assess a primary-omission control for detection-system background (standard chromogenic IHC practice). If haze persists, adjust washing, antibody concentration or DAB development while checking that nuclei remain discernible (standard IHC practice; HPA: general nuclear expression). Score background separately from the nuclear signal so reduced staining is not mistaken for improved specificity (standard IHC practice).
What is a defensible way to score RPA1 in paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score RPA1 within viable, predefined cell populations and use nuclear staining as the positive compartment (HPA: general nuclear expression; standard IHC practice). Report the percentage of positive nuclei and, when intensity matters, an H-score using intensity categories 0–3 multiplied by their percentages, yielding 0–300 (standard IHC scoring practice). Normalise counts to all evaluable nuclei in the same cell population, or report positive nuclei per mm² of viable tissue when density is the question (standard IHC practice). Apply identical thresholds, DAB development and region-selection rules across sections (standard IHC practice). Document excluded folds, edges and necrotic areas before comparing specimens (standard IHC practice).
How can I distinguish genuine RPA1 staining from section artefact?
A credible RPA1 result shows nuclear signal in preserved cells, consistent with general nuclear tissue expression and nucleoplasmic localisation (HPA: tissue IHC; HPA: subcellular). In breast sections, glandular-cell staining has supporting tissue evidence, but expression is not restricted to that population (HPA: high in breast glandular cells; HPA: low tissue specificity). Check unexpected membrane or broad cytoplasmic staining against morphology and controls, given RPA1’s nuclear location and lack of a transmembrane segment (UniProt P27694 localisation and topology; standard IHC practice). Exclude staining confined to section edges, folds or necrosis from scoring (standard IHC practice). A primary-omission control helps identify endogenous enzyme or detection-system signal during DAB interpretation (standard chromogenic IHC practice).
Boster reagents

Best RPA1 / Replication protein A 70 kDa DNA-binding subunit IHC Antibodies

Anti-RPA1 antibodies have IHC images from human paraffin tissue sections and IF images from A549 cells (catalog image captions); listed reactivity covers human, monkey and mouse (catalog reactivity).

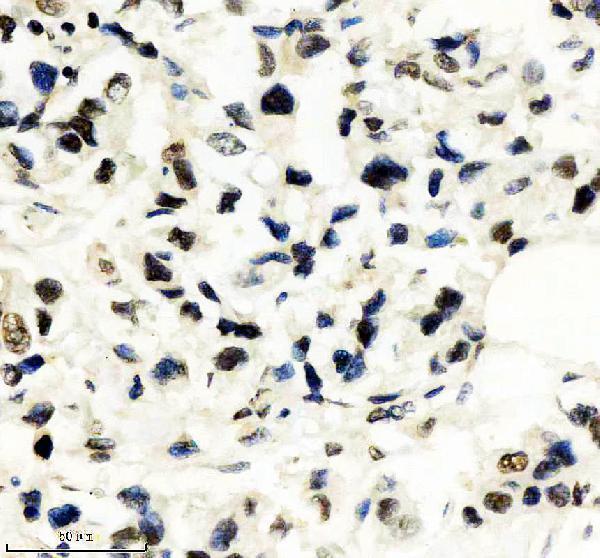
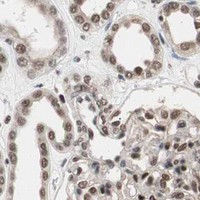
Real IHC data IHC analysis of RPA1 using anti-RPA1 antibody (M01317-1). RPA1 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1: 50 rabbit anti-RPA1 Antibody (M01317-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-RPA70 Monoclonal Antibody
Cat # M01317-1
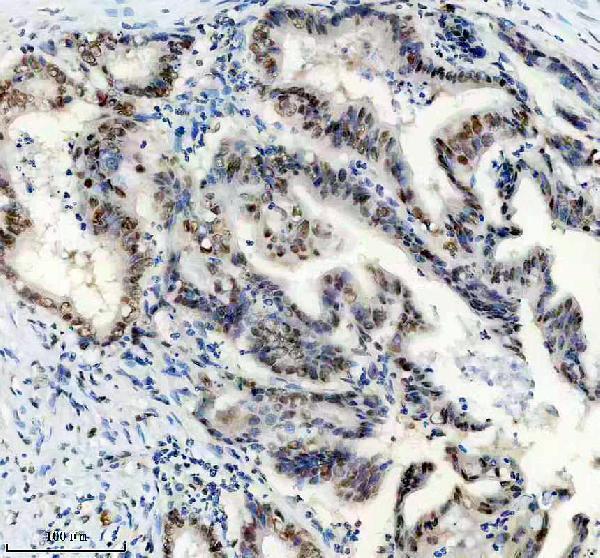
Real IHC data IHC analysis of RPA70 using anti-RPA70 antibody (M01317-2). RPA70 was detected in paraffin-embedded section of human intestinal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml mouse anti-RPA70 Antibody (M01317-2) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-RPA70 RPA1 Antibody ® (monoclonal, 11H4)
Cat # M01317-2
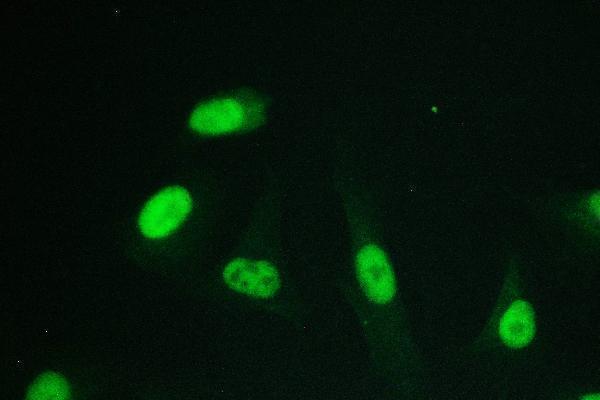
Real IF data IF analysis of RPA70 using anti-RPA70 antibody (PB9886). RPA70 was detected in an immunocytochemical section of A549 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-RPA70 Antibody (PB9886) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-RPA70/RPA1 Antibody ®
Cat # PB9886

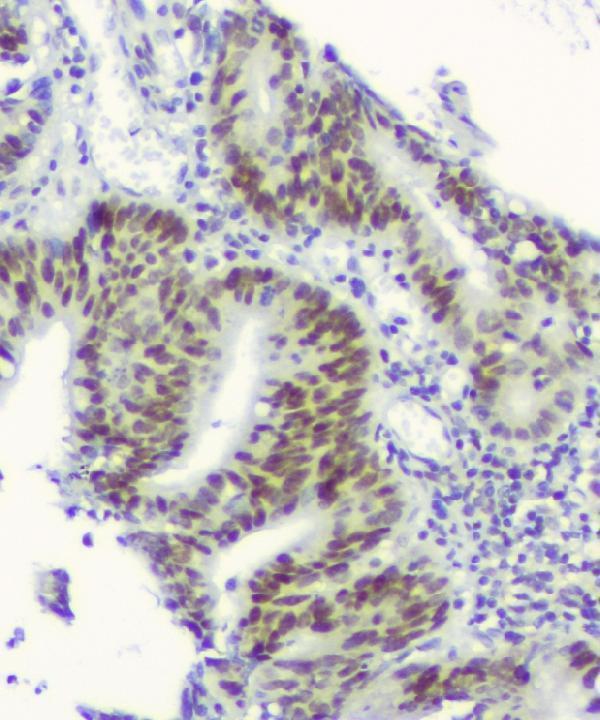
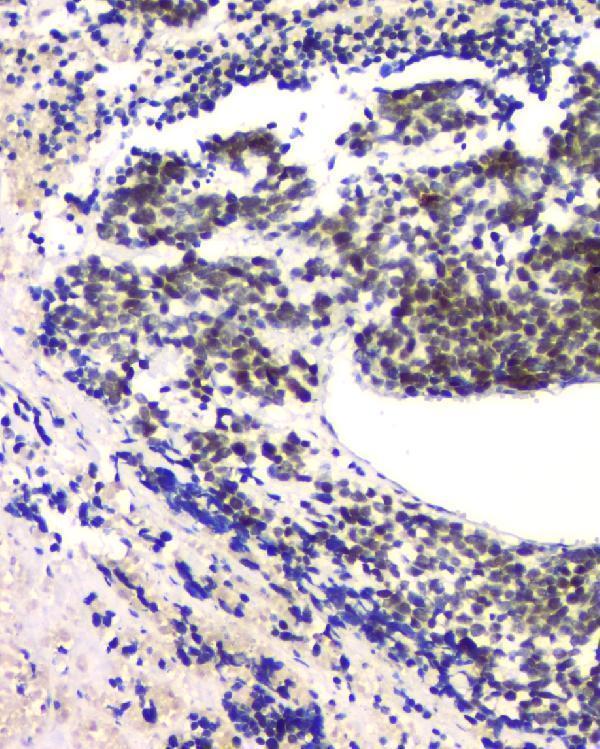
M01317-1 has IHC images from human breast cancer, colon cancer and colon sections; M01317-2 has IHC images from human intestinal and lung cancer sections (catalog IHC captions). M01317-2 and PB9886 have IF images from A549 cells (catalog IF captions).

Which to pick: For tissue IHC, choose rabbit monoclonal M01317-1 or mouse monoclonal M01317-2 (catalog applications and clones); each has an IHC image using EDTA retrieval at pH 8.0 on a paraffin section, with the fixative unreported (respective IHC captions). For IF/ICC, PB9886 has an A549 IF image and lists both IF and ICC applications (catalog IF caption and applications). For monkey or mouse samples, M01317-2 lists reactivity with both species, although its supplied IHC and IF images use human samples (catalog reactivity and image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P27694 (RFA1_HUMAN, Replication protein A 70 kDa DNA-binding subunit).
  2. Human Protein Atlas. RPA1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. RPA1 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. RPA1 antibody validation summary (3 antibodies).
  5. Unravelling the clinicopathological and functional significance of replication protein A (RPA) heterotrimeric complex in breast cancers. NPJ breast cancer 2023 — PMC10063624.
  6. Role and mechanism of RPA1 in the development and progression of glioma. Experimental and therapeutic medicine 2025 — PMC12235235.
  7. Clinicopathological and functional evaluation of replication protein A in epithelial ovarian cancers: A target validation study. Translational oncology 2026 — PMC12925576.
  8. Identification of potential biomarkers of head and neck squamous cell carcinoma using iTRAQ based quantitative proteomic approach. Data in brief 2018 — PMC6139602.
  9. PubMed PMID:2050703 — UniProt-cited evidence.
  10. PubMed PMID:8420996 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.