This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
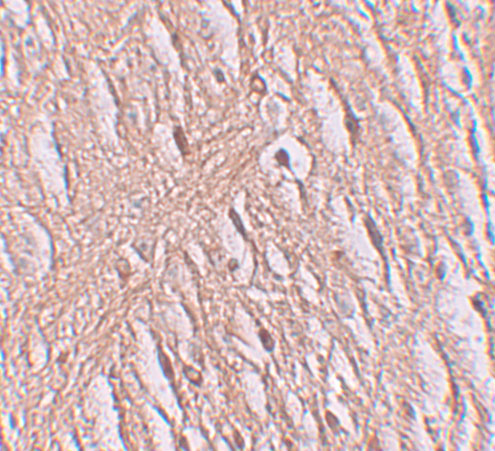
Plan chromogenic SLC39A9 IHC-P around the general cytoplasmic tissue pattern and the cell types with high staining (HPA tissue IHC). A catalog image of human brain uses 2.5 μg/mL as a starting antibody concentration (datasheet: A13097-2).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | General cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in glandular, neuronal and endothelial cells (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific); optimize empirically. | |
| Caveat | Smooth muscle and marrow cells show low staining (HPA tissue IHC) | |
| Regulation | Expression regulation is not specified (UniProt) | |
| Isoform / epitope | 3 isoforms; extracellular versus cytoplasmic epitope access may differ (UniProt) |
Compare the catalog antibody’s IHC-P protocol with two published SLC39A9 tissue protocols (PMC11212825; PMC8977092).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A13097-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-SLC39A9, 2.5 μg/mL (datasheet A13097-2) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | SLC39A9-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control. |
SLC39A9 is an 8-pass membrane protein annotated at the trans-Golgi network, cell membrane and other sites (UniProt Q9NUM3 topology; UniProt Q9NUM3 subcellular). In tissue IHC, expect chiefly cytoplasmic staining, including strong staining in glandular and selected epithelial, neuronal and endothelial cells (HPA: general cytoplasmic expression; HPA: High in listed cell types). HPA rates its tissue staining Approved, meaning antibody staining is consistent with RNA data but awaits external verification (HPA: Approved).
| Cytoplasmic brown signal in adrenal, appendix, breast or duodenal glandular cells. | This fits the reported IHC profile: HPA records High staining in those glandular cells and describes overall expression as cytoplasmic (HPA: High in glandular cells; HPA: general cytoplasmic expression). Compare staining within the relevant cells, rather than treating every cell in the section as an equivalent positive. |
| Signal is confined to extracellular material, with little staining inside the expected cells. | That distribution does not fit the reported cytoplasmic IHC profile or the annotated membrane-associated locations (HPA: general cytoplasmic expression; UniProt Q9NUM3 subcellular). Check section deposits and detection artefacts before interpreting it as SLC39A9. A punctate intracellular pattern alone is not a failure of localisation. |
| Strong staining appears chiefly in smooth muscle or bone marrow hematopoietic cells. | HPA reports Low staining in these cells, so a dominant signal warrants scrutiny (HPA: Low in smooth muscle cells; HPA: Low in hematopoietic cells). Review morphology and background controls for cross-reactivity or endogenous detection activity. Low is not a validated absence of protein. |
| Brown colour spreads across cells, stroma and blank areas without cellular boundaries. | A diffuse deposit cannot be scored as the reported cell-associated cytoplasmic pattern (HPA: general cytoplasmic expression). In routine chromogenic IHC, uneven reagent coverage, insufficient washing or detection background can produce this appearance; assess a no-primary control alongside the section. |
| No cellular signal appears in a section expected to show strong staining. | First verify that the section contains the relevant cells: HPA reports High staining in bronchial respiratory epithelium, cerebellar Purkinje cells and cortical neurons, among others (HPA: High in listed cell types). A blank result may reflect the run or specimen; HPA tissue levels do not establish SLC39A9-specific fixation sensitivity. |
| Which cells serve as comparison points? | HPA records High staining in several glandular populations, bronchial respiratory epithelium, Purkinje cells, cortical neurons and colon endothelial cells (HPA: tissue IHC). Smooth muscle and bone marrow hematopoietic cells are Low comparators, not confirmed negatives (HPA: Low in listed cell types; HPA: no negative tissues listed). |
| How far does the antibody evidence extend? | The tissue IHC antibody HPA007921 is Approved, and HPA reports consistency with RNA data pending external verification (HPA: HPA007921 IHC Approved; HPA: reliability description). This supports an expected pattern, but does not make an unexpected stain specific by itself. |
| What does protein topology tell us? | SLC39A9 has 8 annotated transmembrane segments and no annotated signal peptide or propeptide (UniProt Q9NUM3 topology; UniProt Q9NUM3 processing). Topology supports a membrane-associated interpretation; without an antibody epitope map, it does not specify retrieval conditions or predict whether a given stain will succeed. |
| Do variants or modifications change the call? | UniProt lists 3 isoforms and glycosylation sites at residues 29 and 241 (UniProt Q9NUM3 isoforms; UniProt Q9NUM3 glycosylation). The supplied record does not link those features to this antibody's epitope or to a distinct tissue IHC pattern. |
| IF/ICC: What localisation should I compare? | HPA reports approved endoplasmic reticulum localisation by ICC-IF, while UniProt also annotates Golgi, cell membrane, perinuclear cytoplasm, mitochondrion and nucleus (HPA: subcellular ICC-IF; UniProt Q9NUM3 subcellular). Interpret IF on its own guide page; these records do not establish an IF protocol or require tissue IHC to resolve individual organelles. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected glandular or epithelial cells remain unstained. | The section may lack intact target cells, or an IHC workflow step may have failed; HPA reports High staining in specific cell populations, not in every field (HPA: tissue IHC). | Confirm cell identity on the counterstain, then check a known staining section and the run controls. Review retrieval, primary incubation and detection as general IHC workflow checks; do not infer SLC39A9-specific fixation failure. |
| Only a fine perinuclear or punctate cytoplasmic pattern is visible. | The recorded tissue pattern is broadly cytoplasmic, and UniProt annotates trans-Golgi and perinuclear locations (HPA: general cytoplasmic expression; UniProt Q9NUM3 subcellular). | Score signal in identifiable cells and compare it with the HPA tissue pattern. Do not reject intracellular puncta solely because the IHC image cannot resolve their organelle. |
| A smooth muscle or marrow field looks more intense than the expected positive cells. | Those cell types are reported Low, so the contrast is discordant with the HPA tissue observations (HPA: Low in smooth muscle cells; HPA: Low in hematopoietic cells). | Check tissue identity and a no-primary control for endogenous or detection signal; review antibody specificity before calling the discordant cells positive. |
| The entire section has brown haze. | Uniform haze obscures the reported cytoplasmic cellular pattern (HPA: general cytoplasmic expression). In chromogenic IHC, nonspecific detection signal or insufficient washing can contribute. | Compare the no-primary control and inspect reagent coverage. Optimize washing or detection conditions as general IHC practice, then reassess identifiable cells. |
| Signal appears only as extracellular deposits. | This location conflicts with HPA's cytoplasmic tissue profile and UniProt's annotated cellular locations (HPA: general cytoplasmic expression; UniProt Q9NUM3 subcellular). | Inspect the section for precipitate or damaged areas, review the detection control, and repeat interpretation in intact cells before assigning SLC39A9 staining. |
| IHC looks cytoplasmic, but an ICC-IF reference looks reticular. | HPA describes tissue IHC broadly as cytoplasmic and its ICC-IF localisation as endoplasmic reticulum; the methods resolve different levels of detail (HPA: tissue IHC profile; HPA: subcellular ICC-IF). | Use the tissue cell-type and cytoplasmic criteria for this IHC readout. Consult the separate IF/ICC guide for fluorescence localisation; do not force a fine organelle assignment from chromogenic tissue IHC. |
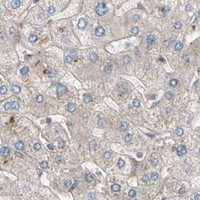
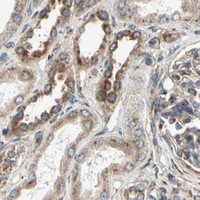


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — High consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: SLC39A9 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot SLC39A9 staining by checking retrieval, compartment pattern, cell identity and controls before comparing chromogenic IHC scores.
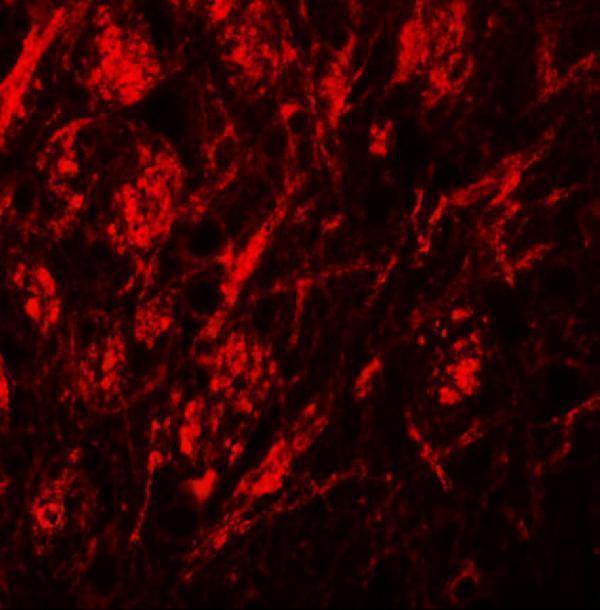
A13097-2 is an anti-SLC39A9 antibody with IHC-P and IF applications (catalog: applications) and figures showing human brain tissue in both assays (catalog image captions).
A13097-2 has a human brain tissue IHC image at 2.5 μg/mL (catalog IHC image caption). Its IF image shows human brain tissue at 20 μg/mL; Human and Mouse reactivity are listed (catalog IF image caption; catalog: reactivity).
Which to pick: For paraffin-section IHC, choose A13097-2 because IHC-P is listed (catalog: applications); its own IHC image shows human brain tissue, but the fixative is unreported (catalog IHC image caption). For IF, choose A13097-2 based on its human brain tissue IF image; ICC validation is unreported (catalog IF image caption; catalog: applications). For cross-species work, A13097-2 lists Human and Mouse reactivity, while both pictured assays use human tissue; the antibody host is rabbit and no clone is specified (catalog: reactivity, host, clone; catalog image captions).