STBD1 / Starch-binding domain-containing protein 1 · IHC design guide

Design Immunohistochemistry for STBD1

Plan chromogenic STBD1 IHC in paraffin sections using cytoplasmic staining in skeletal myocytes and placental syncytiotrophoblasts as reference patterns (HPA tissue IHC). The catalog antibody has a human placenta IHC example at 2 μg/ml (datasheet A10113-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
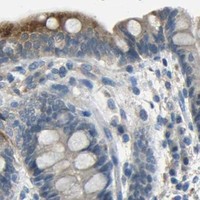
Immunohistochemistry protocol sheet for STBD1 (IHC for STBD1): expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC), antibody A10113-1, validated IHC image, and IHC protocol steps
Printable STBD1 IHC protocol sheet — expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC), antibody A10113-1, controls and protocol steps. Open the full STBD1 IHC guide →

STBD1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC)
Staining pattern Cytoplasmic in myocytes, syncytiotrophoblasts and hepatocytes (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A10113-1)
Positive control ⓘ Colon+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A10113-1)
Caveat Antibody staining and RNA show medium consistency (HPA tissue IHC)
Regulation No regulatory trigger specified (UniProt)
Isoform / epitope No isoforms; epitopes at 1–6 are external, 24–358 cytoplasmic (UniProt)
Section 1

Recommended STBD1 IHC & IF Protocols

The catalog antibody’s retrieval protocol (datasheet: A10113-1) is complemented by published STBD1 IHC protocols for renal tissue (PMC12293080) and human colon tissue (PMC8166871).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet A10113-1)
FixationImage fixative and duration unreported (datasheet A10113-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A10113-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A10113-1)
Primary antibodyRabbit anti-STBD1, 2-5 μg/ml (datasheet A10113-1)
Primary incubationOvernight at 4 °C (datasheet A10113-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A10113-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSTBD1-positive staining in enterocytes of colon (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues at variable levels, most abundant in skeletal muscle, placental trophoblasts and hepatocytes. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A10113-1). Use boiling citrate pH 6.0 when reproducing the renal protocol (PMC12293080).
Section 2

What Is the Expected STBD1 Staining Pattern?

In paraffin-section IHC, expect mainly cytoplasmic STBD1 staining in skeletal myocytes, placental syncytiotrophoblasts and selected epithelial cells (HPA: tissue IHC, Enhanced reliability). STBD1 has a transmembrane anchor near its N terminus, with most of the protein on the cytoplasmic side; UniProt also places it at endoplasmic-reticulum and preautophagosomal membranes (UniProt O95210: topology and subcellular location). Interpret staining by cell type as well as compartment.

What am I looking at on my slide?
Distinct cytoplasmic staining in skeletal myocytes or placental syncytiotrophoblast cell bodies.This matches the strongest listed tissue patterns, both scored High (HPA: tissue IHC). Compare stained cells with adjacent unstained structures when judging specificity; intensity across a whole section alone is less informative (general IHC practice).
Cytoplasmic staining in hepatocytes, cardiomyocytes or intestinal enterocytes.These are plausible STBD1-positive cells, but the reported levels differ: hepatocytes and cardiomyocytes are Medium, colon enterocytes High, and duodenal enterocytes Medium (HPA: tissue IHC). Do not require one uniform intensity across organs.
Predominantly nuclear staining, or a pattern that cannot be assigned to cytoplasm.Treat it as discordant with the documented localisation, then review morphology and controls before calling it STBD1 (HPA: cytoplasmic tissue IHC; UniProt O95210: membrane topology). Nuclear colour alone does not establish target localisation (general IHC practice).
Prominent staining in adipocytes, marrow hematopoietic cells or bronchial respiratory epithelium.These cell populations are listed as Not detected (HPA: tissue IHC). Consider cross-reactivity, endogenous chromogen activity or other background; a stain in an unexpected cell type is a warning, not proof of which mechanism caused it (general IHC practice).
Diffuse colour across tissue and blank areas, or no signal in a known-positive section.Diffuse colour obscures cell-specific interpretation; an absent signal in skeletal myocytes or placental syncytiotrophoblasts conflicts with their reported High staining (HPA: tissue IHC). Check the control and detection workflow before assigning a biological negative (general IHC practice).
💡Expected STBD1 appearanceCall a section positive when chromogenic signal is chiefly cytoplasmic in the expected cells, especially High-staining skeletal myocytes or placental syncytiotrophoblasts; isolated nuclear colour or broad cell-independent colour is discordant (HPA: tissue IHC; UniProt O95210: topology).
How each factor affects the staining
Cellular compartmentA membrane-associated, cytoplasm-facing pattern is plausible: residues 7–23 form the transmembrane segment and residues 24–358 face the cytoplasm (UniProt O95210: topology). Tissue IHC is described broadly as cytoplasmic, so do not demand visible organelle resolution (HPA: tissue IHC).
Tissue and cell selectionUse the named cell population, not an entire organ, as the comparison: HPA scores skeletal myocytes and placental syncytiotrophoblasts High, hepatocytes Medium, and adipocytes Not detected (HPA: tissue IHC).
Antibody evidenceHPA lists 2 rabbit polyclonal antibodies with Enhanced IHC validation, HPA011952 and HPA012849 (HPA: antibody validation). Enhanced supports the reported pattern across independent antibodies or orthogonal data; it does not certify every signal in a new section.
Low kidney stainingAvoid a categorical kidney-negative call: HPA lists proximal-tubule cell bodies as Low, while UniProt reports no kidney expression in its tissue-specificity summary (HPA: tissue IHC; UniProt O95210: tissue specificity). Record the observed cell-level result and method.
IF/ICC localisation?On its separate IF/ICC guide, expect endoplasmic-reticulum localisation: HPA approves that location and lists A-431 images (HPA: subcellular ICC-IF). This supports a compartment comparison, not an IF result or protocol for the paraffin-section IHC assay.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive skeletal muscle or placenta has no detectable chromogenic signal.The run may have failed, or the sampled section may lack interpretable target cells; HPA reports High staining in skeletal myocytes and syncytiotrophoblast cell bodies (HPA: tissue IHC).Confirm those cells are present, then review the run's positive control, primary-antibody step, retrieval setting and detection reagents (general IHC practice). Do not label the tissue biologically negative from this run.
Colour is diffuse or appears similarly in tissue and empty slide regions.Non-specific deposition or detection background may overwhelm cellular detail (general IHC practice); the reported STBD1 tissue pattern is cytoplasmic and cell-associated (HPA: tissue IHC).Review the no-primary control, washes, blocking and chromogen development time (general IHC practice). Score STBD1 only where cellular morphology remains interpretable.
Signal is mainly nuclear, with little cytoplasmic staining.That compartment conflicts with HPA's cytoplasmic IHC profile and UniProt's cytoplasm-facing membrane topology (HPA: tissue IHC; UniProt O95210: topology). The discordance alone does not identify its cause.Check nuclear counterstain against the chromogen, inspect controls and repeat with an independently validated antibody if available (general IHC practice; HPA: two Enhanced IHC antibodies).
Strong signal appears in adipocytes or bronchial respiratory epithelium.Both cell types are Not detected in the HPA tissue record (HPA: tissue IHC). Cross-reactivity or endogenous detection activity is possible, but morphology and controls are needed to distinguish them (general IHC practice).Confirm cell identity, inspect the no-primary control and check the detection system's endogenous-activity controls (general IHC practice). Treat the unexpected signal as unresolved until it is reproduced specifically.
A kidney proximal-tubule section shows faint staining.HPA records Low staining in proximal-tubule cell bodies, although UniProt reports no kidney expression (HPA: tissue IHC; UniProt O95210: tissue specificity). The sources do not resolve this difference.Document the cell type and intensity, compare controls and avoid using kidney as an absolute negative reference (HPA: tissue IHC; general IHC practice).
Liver or heart appears weaker than skeletal muscle.That ranking is compatible with HPA: hepatocytes and cardiomyocytes are Medium, while skeletal myocytes are High (HPA: tissue IHC). Different intensities alone do not imply assay failure.Score the relevant cells within each section and compare against the same run's controls before adjusting workflow conditions (general IHC practice).

Sample controls for STBD1 IHC & IF

🧪Run skeletal muscle first: myocytes should stain (HPA: High in skeletal-muscle myocytes). Use adipose tissue as a negative comparator (HPA: STBD1 not detected in adipocytes); on the muscle slide, assess interstitial nonmyocytes for background staining without assuming every such cell is STBD1-negative (HPA: skeletal-muscle row specifies myocytes).
Positive control tissue: Colon (Enterocytes, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show STBD1 in A-431, with annotated localisation: Endoplasmic reticulum (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide, a concentration-matched rabbit isotype control, and STBD1-knockout tissue if available (caption: rabbit primary antibody; standard IHC controls). Quench endogenous peroxidase before HRP/DAB detection and check for background within muscle fibers (caption: HRP/DAB detection; standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A10113-1 paraffin-section caption does not state the fixative (caption: fixative unreported). That caption reports heat-mediated retrieval in EDTA at pH 8.0, but does not establish that retrieval is required for all specimens (caption: EDTA retrieval). Paraffin-section IHC is directly documented; whether frozen sections or IF are easier is unreported, while muscle-fiber background should be checked against the negative controls (caption: paraffin-section IHC; standard IHC practice).

HPA tissue IHC evidence for STBD1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Colon Enterocytes High Protein (IHC) HPA →
Placenta Syncytiotrophoblasts - cell body High Protein (IHC) HPA →
Skeletal muscle Myocytes High Protein (IHC) HPA →
Appendix Enterocytes Medium Protein (IHC) HPA →
Cerebral cortex Neuronal cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced STBD1 IHC Tips

Troubleshoot STBD1 chromogenic IHC in paraffin sections using the selected antibody’s tissue staining conditions and the reported cellular distribution.

What should I change when STBD1 staining is weak after antigen retrieval?
Start with heat-mediated retrieval in EDTA, pH 8.0 (datasheet A10113-1). The selected paraffin-section image used that retrieval before incubation with 2 μg/ml antibody overnight at 4°C (datasheet A10113-1). If staining remains weak, compare longer and shorter heating on matched sections while keeping antibody concentration and detection constant (standard IHC practice). Check a skeletal-muscle control for myocyte staining and a placenta control for syncytiotrophoblast staining (HPA: High in myocytes and syncytiotrophoblasts). Record whether retrieval improves the expected cytoplasmic pattern without increasing diffuse tissue background (HPA: cytoplasmic tissue expression; standard IHC practice).
Could fixation explain weak or uneven STBD1 staining in paraffin sections?
The selected paraffin-section caption does not report a fixative, so STBD1-specific sensitivity to fixation is unknown (datasheet A10113-1). Record the specimen’s actual fixative, fixation duration and processing history before comparing slides (standard IHC practice). When feasible, compare sections from similarly handled specimens using the stated EDTA, pH 8.0 retrieval and 2 μg/ml antibody conditions (datasheet A10113-1; standard IHC practice). If a control stains but the test specimen does not, assess preservation and handling alongside biological variation (standard IHC practice). Do not infer a fixation effect from tissue expression patterns or membrane topology alone (HPA: tissue IHC profile; UniProt O95210 topology).
Which STBD1 staining pattern should I expect in tissue sections?
Assess staining chiefly in the cytoplasm, with attention to possible perinuclear enrichment (HPA: cytoplasmic tissue expression; UniProt O95210: perinuclear concentration). STBD1 is associated with endoplasmic-reticulum and preautophagosomal membranes, and is also reported at the sarcolemma and T-tubules (UniProt O95210 subcellular location). Its 7–23 transmembrane segment leaves residues 24–358 on the cytoplasmic side, which helps frame epitope-access questions (UniProt O95210 topology). Compare myocytes, syncytiotrophoblasts or hepatocytes with the relevant tissue architecture rather than scoring all cells together (HPA: tissue IHC profile; standard IHC practice). Predominantly nuclear staining warrants scrutiny against the expected distribution (HPA: cytoplasmic tissue expression; standard IHC practice).
How should epitope position affect interpretation of STBD1 IHC?
Check the antibody’s stated immunogen or epitope before interpreting a negative section; the supplied caption does not identify it (datasheet A10113-1). STBD1 has a short extracellular segment at residues 1–6 and a cytoplasmic segment at 24–358 (UniProt O95210 topology). Its CBM20 domain occupies 258–357, while annotated phosphoserines include positions 65, 117, 148, 175 and 188 (UniProt O95210 domains and modified residues). These annotations identify regions to consider when reviewing epitope access, but do not establish how this antibody responds to processing (UniProt O95210; standard IHC practice). No isoforms are listed in the supplied record; avoid assigning a staining difference to a specific isoform without independent evidence (UniProt O95210 isoforms).
How can I assess STBD1 by IF alongside a cell-type marker?
Treat IF as a separate application: the selected antibody evidence here describes chromogenic IHC in a paraffin section (datasheet A10113-1). For multiplexing, pair STBD1 with a validated marker identifying the expected myocytes, syncytiotrophoblasts or hepatocytes, and include single-stain controls (HPA: tissue IHC profile; standard IF practice). Choose fluorophores after measuring the tissue’s autofluorescence, favoring a well-separated channel for weaker signals (standard IF practice). If the mapped epitope lies within residues 24–358, assess permeabilisation for access to its cytoplasmic side; confirm epitope position from antibody documentation first (UniProt O95210 topology; standard IF practice). Evaluate cellular overlap and compartmental pattern against controls (standard IF practice).
What should I check when DAB staining appears widespread or granular?
Compare a no-primary control and an appropriate positive tissue section before changing the antibody concentration (standard IHC practice). The selected protocol used 10% goat-serum block, 2 μg/ml primary overnight at 4°C, and a peroxidase-linked secondary for 30 minutes at 37°C (datasheet A10113-1). Check peroxidase blocking, wash steps, DAB development time and counterstain intensity as general chromogenic IHC variables (standard IHC practice). Inspect necrotic areas and section edges separately, since local staining there can complicate interpretation (standard IHC practice). A convincing result should retain the reported cytoplasmic distribution in appropriate cells (HPA: cytoplasmic tissue expression and tissue IHC profile).
How should I quantify STBD1 staining across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and scoring region before comparing sections; hepatocytes, myocytes and syncytiotrophoblasts have reported STBD1 staining (HPA: tissue IHC profile; standard IHC practice). For cellular scoring, report percentage of positive cells and an H-score based on staining intensity; keep thresholds fixed across specimens (standard IHC practice). If the question concerns tissue distribution, report positive-cell density per mm² of viable tissue and exclude necrotic or damaged regions consistently (standard IHC practice). Normalise to the number of eligible cells or measured viable area, and document section thickness and imaging settings (standard IHC practice). Score cytoplasmic signal separately from unexpected nuclear or diffuse background signal (HPA: cytoplasmic tissue expression; standard IHC practice).
How can I distinguish genuine STBD1 signal from artefact?
Look for reproducible cytoplasmic staining in the relevant cell type, supported by positive and no-primary controls (HPA: cytoplasmic tissue expression; standard IHC practice). Myocytes and syncytiotrophoblasts show High staining in the supplied tissue profile, while hepatocytes show Medium staining (HPA: tissue IHC profile). Strong nuclear-only signal, staining confined to section edges or necrosis, and signal persisting without primary antibody each warrant investigation (HPA: cytoplasmic tissue expression; standard IHC practice). Check endogenous peroxidase contribution before attributing unexpected DAB deposits to STBD1 (standard IHC practice). Interpret a plausible membrane-adjacent or perinuclear pattern alongside cellular morphology, given the reported membrane associations and perinuclear concentration (UniProt O95210 subcellular location; standard IHC practice).
Boster reagents

Best STBD1 / Starch-binding domain-containing protein 1 IHC Antibodies

A10113-1 has IHC images from human paraffin sections and an IF image from HeLa cells (catalog image captions); its listed reactivity is human (catalog: reactivity).

Real IHC data IHC analysis of STBD1 using anti-STBD1 antibody (A10113-1). STBD1 was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-STBD1 Antibody (A10113-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-STBD1 Antibody ®
Cat # A10113-1

A10113-1 has IHC images from paraffin sections of human liver cancer, placenta, and testicular germ cell tumor tissue (catalog IHC captions). The same SKU has IF data from HeLa cells and lists both IF and ICC as applications (catalog IF caption; catalog: applications).

Which to pick: Choose A10113-1 for human tissue IHC: its paraffin-section images use EDTA pH 8.0 retrieval and DAB detection; the fixative is unreported (catalog IHC captions). For IF/ICC, A10113-1 lists both applications and has HeLa-cell IF data at 5 μg/mL; its clone type is unreported (catalog: applications; catalog IF caption; catalog: clone). No cross-species option is supported because A10113-1 lists human reactivity only (catalog: reactivity).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O95210 (STBD1_HUMAN, Starch-binding domain-containing protein 1).
  2. Human Protein Atlas. STBD1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. STBD1 subcellular location (ICC-IF): Localized to the endoplasmic reticulum..
  4. Human Protein Atlas. STBD1 antibody validation summary (2 antibodies).
  5. Transcriptomic and Proteomic Analysis of Clear Cell Foci (CCF) in the Human Non-Cirrhotic Liver Identifies Several Differentially Expressed Genes and Proteins with Functions in Cancer Cell Biology and Glycogen Metabolism. Molecules (Basel, Switzerland) 2020 — PMC7570661.
  6. Asiatic Acid Alleviates Renal Damage by Upregulating STBD1-Mediated Glycophagy in Diabetic Kidney Disease. Biomedicines 2025 — PMC12293080.
  7. Model-based analysis uncovers mutations altering autophagy selectivity in human cancer. Nature communications 2021 — PMC8166871.
  8. Glycophagy is an ancient bilaterian pathway supporting metabolic adaptation through STBD1 structural evolution. Communications biology 2026 — PMC12913940.
  9. PubMed PMID:9794794 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.