TRPS1 / Zinc finger transcription factor Trps1 · IHC design guide

Design Immunohistochemistry for TRPS1

Plan TRPS1 chromogenic IHC in paraffin sections using expected nuclear staining in squamous epithelium and breast and endometrial glands (HPA tissue IHC). The catalog antibody has an IHC-P working range of 2–5 μg/mL (datasheet A02328-2).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TRPS1 (IHC for TRPS1): expected localisation Nuclear staining in glandular and squamous cells (HPA tissue IHC), antibody A02328-2, validated IHC image, and IHC protocol steps
Printable TRPS1 IHC protocol sheet — expected localisation Nuclear staining in glandular and squamous cells (HPA tissue IHC), antibody A02328-2, controls and protocol steps. Open the full TRPS1 IHC guide →

TRPS1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in glandular and squamous cells (HPA tissue IHC)
Staining pattern Nuclei of squamous cells, some glia, breast/endometrial glands (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02328-2)
Positive control ⓘ Breast+4 more · see all
Negative control ⓘ Adrenal gland+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Only a subset of glial cells shows nuclear staining (HPA tissue IHC)
Regulation Androgen-dependent prostate cancer: higher expression (UniProt)
Isoform / epitope 3 isoforms; epitope coverage is unspecified (UniProt; datasheet A02328-2)
Section 1

Recommended TRPS1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol uses EDTA pH 8.0 retrieval (datasheet: A02328-2). Three published FFPE TRPS1 protocols provide additional examples (PMC11270280; PMC13143365; PMC11503264).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A02328-2)
FixationImage fixative and duration unreported (datasheet A02328-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02328-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02328-2)
Primary antibodyRabbit anti-TRPS1, 2-5 μg/ml (datasheet A02328-2)
Primary incubationOvernight at 4 °C (datasheet A02328-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A02328-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTRPS1-positive staining in glandular cells of breast (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in squamous epithelium, subset of glial cell, and in glandular cells of breast and endometrium. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet: A02328-2); optimize retrieval and dilution when using another antibody (PMC13143365; PMC11503264).
Section 2

What Is the Expected TRPS1 Staining Pattern?

TRPS1 should appear predominantly in nuclei, consistent with its nuclear localisation and lack of a transmembrane segment (UniProt Q9UHF7: nucleus; no transmembrane segment). In tissue IHC, expect staining in breast glandular cells and several squamous epithelia, with a subset of glial cells also reported (HPA tissue IHC: nuclear expression profile). HPA rates the tissue staining profile Enhanced, while describing its consistency with RNA expression as medium (HPA tissue IHC: reliability).

What am I looking at on my slide?
Distinct nuclear staining in breast glandular cells or cervical, esophageal, oral mucosal, or vaginal squamous epithelial cells.This matches the reported compartment and high-staining cell populations (HPA tissue IHC: nuclear profile; High in these populations). Judge the relevant cells individually: a positive result need not mean every cell in the section has equal intensity (standard IHC interpretation).
Predominantly cytoplasmic, membranous, or extracellular colour, with little convincing nuclear staining.The compartment conflicts with the expected nuclear pattern (UniProt Q9UHF7: nucleus; HPA tissue IHC: nuclear expression). Treat it as a possible staining artefact and inspect localisation in a known-positive control before calling TRPS1 positive (standard IHC practice).
Strong colour in cells outside the reported positive population, especially without staining in the expected cells.Check cell identity and nuclear localisation before scoring. Cross-reactivity or endogenous detection activity is possible (standard IHC practice); the HPA cell-type profile supports an expectation, not a universal exclusion rule (HPA tissue IHC: cell-specific observations).
Diffuse colour across nuclei, cytoplasm, and surrounding tissue, with poor separation between cells.Diffuse background obscures the compartment needed for interpretation (UniProt Q9UHF7: nucleus). Review the negative reagent control, blocking, washes, and detection conditions as general IHC checks; this appearance alone cannot identify its cause (standard IHC practice).
No convincing nuclear signal in a breast glandular or listed high-staining squamous epithelial control.An expected positive population is missing (HPA tissue IHC: High in breast glandular cells and listed squamous epithelia). Verify that those cells are present and that the control and detection run worked before interpreting an unknown sample as negative (standard IHC practice).
💡Expected TRPS1 appearanceCall positive a clearly resolved nuclear signal in the appropriate glandular or squamous epithelial cells, strongest in the HPA High populations; isolated cytoplasmic or diffuse colour without convincing nuclear staining is suspect (UniProt Q9UHF7: nucleus; HPA tissue IHC: nuclear profile and staining levels).
How each factor affects the staining
CompartmentTRPS1 is a nuclear transcriptional repressor with no annotated transmembrane segment, supporting a nuclear scoring criterion (UniProt Q9UHF7: function, localisation, topology). HPA ICC-IF further places it in the nucleoplasm (HPA subcellular: supported).
Tissue and cell populationBreast glandular cells and squamous epithelial cells in cervix, esophagus, oral mucosa, and vagina stain High; endometrial glandular cells and caudate glial cells stain Medium (HPA tissue IHC: cell-specific levels). Choose a control by cell population, not tissue name alone (standard IHC practice).
Validation scopeThe tissue profile is Enhanced but has medium consistency with RNA data (HPA tissue IHC: reliability). HPA071767 is Enhanced for IHC, while HPA060380 has Supported ICC and no listed IHC status (HPA antibodies: application validation). Interpret each status within its stated application.
Low or undetected comparatorsHPA reports Low staining in kidney tubule cells and Not detected in adrenal gland glandular cells, among other specified populations (HPA tissue IHC: Low; Not detected). These observations describe those sampled cell populations; they do not establish that every cell in either organ is negative.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in the chosen positive control.The expected cell population may be absent from the section, or a general staining step may have failed (standard IHC practice).Confirm breast glandular or listed high-staining squamous cells are present (HPA tissue IHC: High). Check the catalog antibody's IHC-P instructions, retrieval run, detection reagents, and a working control together (standard IHC practice).
Only faint nuclei are visible.The selected population may normally stain Low or Medium (HPA tissue IHC: cell-specific levels); inadequate signal is also possible (standard IHC practice).Compare the same run with a High population before changing conditions (HPA tissue IHC: High populations). Review the catalog antibody's IHC-P dilution and detection instructions if that control is also faint (standard IHC practice).
Colour is chiefly cytoplasmic or membranous.This differs from the reported nuclear localisation; nonspecific staining or detection background may be involved (UniProt Q9UHF7: nucleus; standard IHC practice).Inspect nuclear detail and the known-positive control. Review negative reagent controls and wash conditions before accepting any cells as positive (standard IHC practice).
Unexpected cells stain more strongly than the expected population.Cell identification may be mistaken, or cross-reactivity or endogenous detection activity may contribute (standard IHC practice).Identify the stained cells morphologically, check for nuclear signal, and compare controls (standard IHC practice). Use HPA's cell-specific observations as context rather than treating unlisted cells as automatically negative (HPA tissue IHC: profile).
A broad haze makes nuclear scoring difficult.General background from detection, blocking, or washing may obscure true cell boundaries; the image alone cannot distinguish these causes (standard IHC practice).Compare a negative reagent control, then review blocking, wash, detection, and counterstain conditions in the IHC workflow (standard IHC practice). Score only nuclei that can be distinguished from surrounding background.
Does an ICC-IF image establish how to run this paraffin IHC assay?The assays have separate validation entries: HPA reports nucleoplasmic ICC-IF localisation, while its antibody records distinguish ICC from IHC status (HPA subcellular; HPA antibodies).Use the nucleoplasmic image as a localisation cross-check (HPA subcellular: supported). For this section, follow the catalog antibody's IHC-P instructions and its IHC validation status; use the separate IF/ICC guide for that assay.

Sample controls for TRPS1 IHC & IF

🧪Run breast first: its glandular cells should show nuclear TRPS1 staining (HPA: High in breast glandular cells; UniProt Q9UHF7: nucleus). Use adrenal gland as the negative tissue (HPA: Not detected in adrenal glandular cells); on the breast slide, adjacent unstained nonglandular nuclei, if present, provide a background reference but are not a validated TRPS1-negative population (HPA: breast glandular-cell staining only).
Positive control tissue: Breast (Glandular cells, HPA High)
Negative control tissue: Adrenal gland (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TRPS1 in MCF-7, U-251MG, U2OS, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a host-matched rabbit control IgG matched to the primary’s clonality when known (selected-SKU caption: rabbit anti-TRPS1); and TRPS1-knockout material as a biological specificity control. Quench endogenous peroxidase before HRP/DAB detection and inspect the breast section for pigment or other background that could mimic chromogen (selected-SKU caption: breast tissue with HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact selected-SKU tissue-IHC caption does not state the fixative (selected-SKU caption: fixative not stated). Heat retrieval in EDTA at pH 8.0 preceded staining at 2 μg/ml overnight at 4°C in the reported paraffin-section example; this supports starting conditions but does not establish how retrieval depends on fixation (selected-SKU caption). HPA shows nucleoplasmic ICC-IF localization in MCF-7, U-251MG and U2OS cells, but the supplied evidence does not establish that IF or frozen sections are easier than paraffin IHC (HPA subcellular: nucleoplasm, supported; HPA ICC-IF image cell lines).

HPA tissue IHC evidence for TRPS1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Breast Glandular cells High Protein (IHC) HPA →
Cervix Squamous epithelial cells High Protein (IHC) HPA →
Esophagus Squamous epithelial cells High Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells High Protein (IHC) HPA →
Vagina Squamous epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Colon Endothelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced TRPS1 IHC Tips

Troubleshoot TRPS1 staining in paraffin sections by checking nuclear localisation, documented retrieval conditions, tissue context and assay controls.

How should I optimise retrieval when TRPS1 nuclear staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A02328-2). The catalog antibody produced TRPS1 staining in a paraffin section of human breast cancer after that retrieval, followed by 2 μg/ml primary antibody overnight at 4°C (datasheet A02328-2). If nuclei remain weak, compare retrieval heating and cooling conditions on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Include a breast glandular-cell control, where high nuclear expression is reported, and assess whether tissue morphology deteriorates as retrieval increases (HPA tissue IHC; standard IHC practice).
Can I adjust fixation to rescue weak TRPS1 staining?
The catalog image describes a paraffin-embedded section but does not report its fixative, so TRPS1-specific fixation sensitivity is unknown (datasheet A02328-2). Do not infer a preferred fixative or fixation duration from the reported tissue staining or TRPS1 protein features (datasheet A02328-2; HPA tissue IHC; UniProt Q9UHF7). For new specimens, document the fixative, time to fixation and fixation duration, then process comparison sections consistently (standard IHC practice). If staining varies, compare sections with matched retrieval, 2 μg/ml primary antibody and detection conditions, checking nuclear signal alongside preserved morphology (datasheet A02328-2; standard IHC practice).
What staining pattern should count as TRPS1 positive?
Score TRPS1 primarily in nuclei: UniProt places it in the nucleus, and HPA supports nucleoplasmic localisation (UniProt Q9UHF7; HPA subcellular). HPA reports nuclear expression in breast and endometrial glandular cells, squamous epithelium and a subset of glial cells (HPA tissue IHC). Examine nuclear staining in the expected cell population before considering whole-section signal or cytoplasmic colour (HPA tissue IHC; standard IHC practice). If staining is predominantly cytoplasmic, inspect the counterstain, section integrity and no-primary control, then repeat with the documented EDTA pH 8.0 retrieval if needed (UniProt Q9UHF7; datasheet A02328-2; standard IHC practice).
Could TRPS1 isoforms explain inconsistent staining across sections?
TRPS1 has 3 annotated isoforms, but the supplied antibody evidence does not identify which isoforms or sequence region the catalog antibody recognises (UniProt Q9UHF7; datasheet A02328-2). Therefore, do not assign a negative section to isoform loss without epitope-mapping evidence (UniProt Q9UHF7; standard IHC interpretation). TRPS1 is a nuclear zinc-finger transcriptional repressor with annotated phosphorylation sites, including serines 90 and 127; their effect on this antibody’s IHC staining is unreported (UniProt Q9UHF7; datasheet A02328-2). Compare positive-control nuclei under identical retrieval and detection conditions before interpreting differences between specimens as biological variation (HPA tissue IHC; standard IHC practice).
How can I adapt the TRPS1 localisation check to multiplex IF?
On a separate IF assay, pair TRPS1 with a marker for the expected cell population and verify that TRPS1 signal lies within nuclei defined by a DNA counterstain (HPA tissue IHC; HPA subcellular; standard IF practice). Select spectrally separated fluorophores after examining tissue autofluorescence and include single-stain controls for channel bleed-through (standard IF practice). Because TRPS1 is nuclear and has no transmembrane segment, use permeabilisation appropriate for access to a nuclear epitope, then optimise it against nuclear morphology (UniProt Q9UHF7; standard IF practice). HPA reports nucleoplasmic localisation in ICC/IF images, but that does not establish IF performance for the catalog antibody (HPA subcellular; datasheet A02328-2).
What should I change when TRPS1 IHC shows diffuse brown background?
First compare the stained section with a no-primary control to distinguish antibody-associated background from detection chemistry (standard IHC practice). The catalog image used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, an anti-rabbit secondary and DAB development (datasheet A02328-2). Check peroxidase blocking and shorten DAB development if the no-primary control is brown; these are general chromogenic IHC controls (standard IHC practice). If background appears only with primary antibody, optimise blocking and primary exposure while retaining a nuclear-positive control, since expected TRPS1 localisation is nuclear (UniProt Q9UHF7; standard IHC practice).
How should I quantify TRPS1 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region before scoring, then record the percentage of TRPS1-positive nuclei and, where useful, an intensity-weighted H-score (standard IHC practice; UniProt Q9UHF7). An H-score sums percentages of cells at each intensity multiplied by intensity grade; apply one threshold and scoring rule across the comparison (standard IHC practice). Normalise positive-nucleus counts to the number of evaluable nuclei in that population, or report positive-cell density per mm² of analysed tissue (standard IHC practice). Keep breast glandular cells and squamous epithelial cells distinct during analysis because HPA reports high expression in both populations (HPA tissue IHC).
How do I distinguish genuine TRPS1 staining from an artefact?
A convincing signal is nuclear within an appropriate cell population, consistent with UniProt nuclear localisation and HPA tissue patterns (UniProt Q9UHF7; HPA tissue IHC). High staining is reported in breast glandular cells and several squamous epithelia, whereas adrenal glandular cells and bone-marrow hematopoietic cells are reported as not detected (HPA tissue IHC). Treat staining confined to section edges, necrotic areas or damaged cells cautiously, and compare intact central tissue with the same counterstain (standard IHC practice). Diffuse cytoplasmic DAB or brown signal in a no-primary control warrants checking endogenous peroxidase blocking and detection reagents before assigning TRPS1 positivity (UniProt Q9UHF7; standard IHC practice).
Boster reagents

Best TRPS1 / Zinc finger transcription factor Trps1 IHC Antibodies

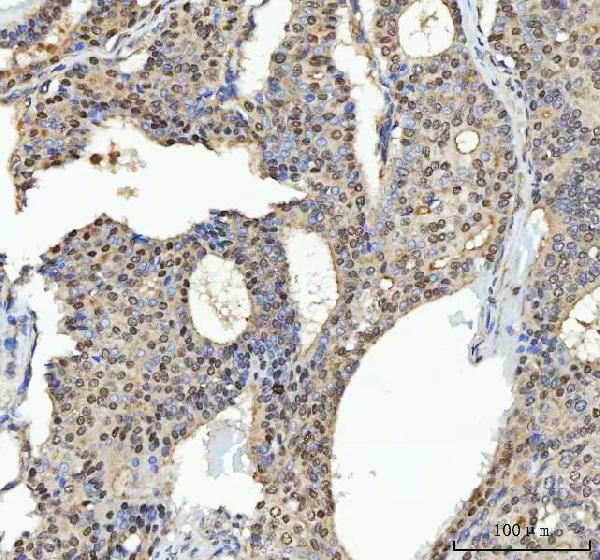
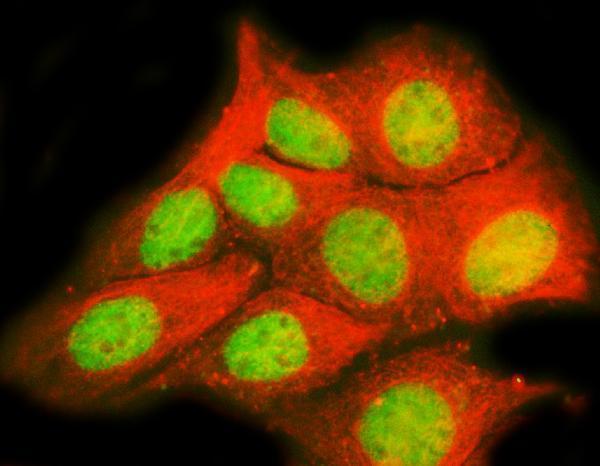
A02328-2 has IHC data from human breast cancer paraffin sections and IF/ICC data from MCF-7 cells (catalog IHC and IF captions); listed reactivity is human (catalog: Human).

Real IHC data IHC analysis of TRPS1 using anti-TRPS1 antibody (A02328-2). TRPS1 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-TRPS1 Antibody (A02328-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-TRPS1 Antibody ®
Cat # A02328-2

A02328-2 is listed for IHC and shown on a human breast cancer paraffin section (catalog applications; catalog IHC caption). A02328-2 is also listed for IF/ICC and shown on MCF-7 cells (catalog applications; catalog IF caption).

Which to pick: Choose A02328-2 for human paraffin-section IHC; its own IHC caption shows that preparation with 2 μg/ml primary antibody and EDTA retrieval at pH 8.0 (catalog IHC caption). The fixative is unreported (catalog IHC caption). For IF/ICC, the same SKU has an MCF-7 image at 5 μg/ml; cross-species reactivity and clonality are unreported, so neither supports a selection claim (catalog IF caption; catalog reactivity and antibody details).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9UHF7 (TRPS1_HUMAN, Zinc finger transcription factor Trps1).
  2. Human Protein Atlas. TRPS1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. TRPS1 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. TRPS1 antibody validation summary (2 antibodies).
  5. TRPS1 Expression Is Frequently Seen in a Subset of Cutaneous Mesenchymal Neoplasms and Tumors of Uncertain Differentiation: A Potential Diagnostic Pitfall. Dermatopathology (Basel, Switzerland) 2024 — PMC11270280.
  6. A Comprehensive Review of TRPS1 as a Diagnostic Immunohistochemical Marker for Primary Breast Carcinoma: Latest Insights and Diagnostic Pitfalls. Cancers 2024 — PMC11545765.
  7. TRPS1 Expression Across the Spectrum of Paget Disease and Morphologic Mimics. Applied immunohistochemistry & molecular morphology : AIMM 2026 — PMC13143365.
  8. Expression of TRPS1 in Metastatic Tumors of the Skin: An Immunohistochemical Study of 72 Cases. Dermatopathology (Basel, Switzerland) 2024 — PMC11503264.
  9. PubMed PMID:10615131 — UniProt-cited evidence.
  10. PubMed PMID:10974077 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.