This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic AADAT IHC in paraffin sections using hepatocytes and renal proximal tubules as positive references (HPA tissue IHC). Assess cytoplasmic staining (HPA tissue IHC) and start with the catalog antibody’s 1:50–1:200 IHC dilution range (datasheet A09111).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in tissue; mitochondrial protein (HPA tissue IHC; UniProt) | |
| Staining pattern | Hepatocyte and proximal-tubule cytoplasm; low GI gland staining (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, heat-mediated (datasheet A09111) | |
| Positive control | Kidney+1 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | RNA and antibody staining have medium agreement (HPA tissue IHC) | |
| Regulation | Liver-enhanced RNA expression (HPA tissue RNA) | |
| Isoform / epitope | 2 isoforms; mature chain spans residues 30–425; check epitope coverage (UniProt) |
Compare the catalog antibody’s citrate pH 6.0 HIER protocol (datasheet A09111) with the published TNBC IHC protocol (PMC12874059).
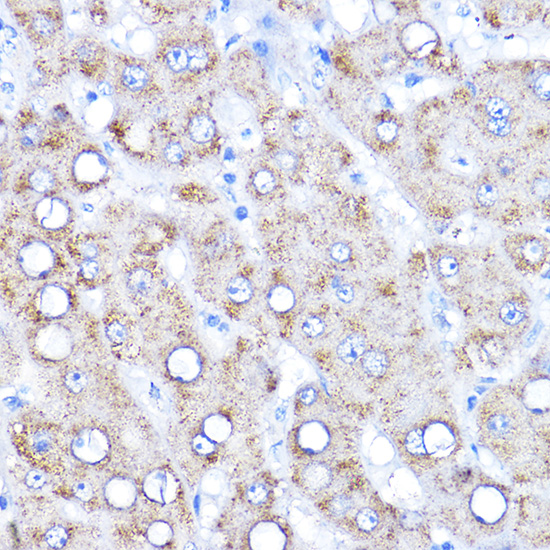
| Sample | Paraffin-embedded human liver tissue; fixative not specified (datasheet A09111) |
| Fixation | Image fixative and duration unreported (datasheet A09111); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Citrate pH 6.0 (datasheet A09111); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-AADAT, 1:50-1:200 (datasheet A09111) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | AADAT-positive staining in proximal tubules (cell body) of kidney (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in liver, renal tubules and low expression in the gastrointestinal tract. No signal in the no-primary control. |
In paraffin-section IHC, expect cytoplasmic AADAT staining in hepatocytes and renal proximal tubules, with weaker staining in some gastrointestinal glandular cells (HPA tissue IHC). UniProt places AADAT in mitochondria and annotates no transmembrane segment (UniProt Q8N5Z0). HPA rates its tissue IHC reliability Enhanced, while reporting medium consistency between antibody staining and RNA expression (HPA tissue IHC).
| Hepatocytes and renal proximal tubule cell bodies show moderate cytoplasmic chromogen; gastrointestinal glandular cells show weaker staining. | This matches the reported tissue pattern: hepatocytes and proximal tubules stain at Medium level, while the gastrointestinal tract has low expression (HPA tissue IHC). Score the relevant cells and their cytoplasm, rather than treating every colored structure in the section as target signal (general IHC practice). |
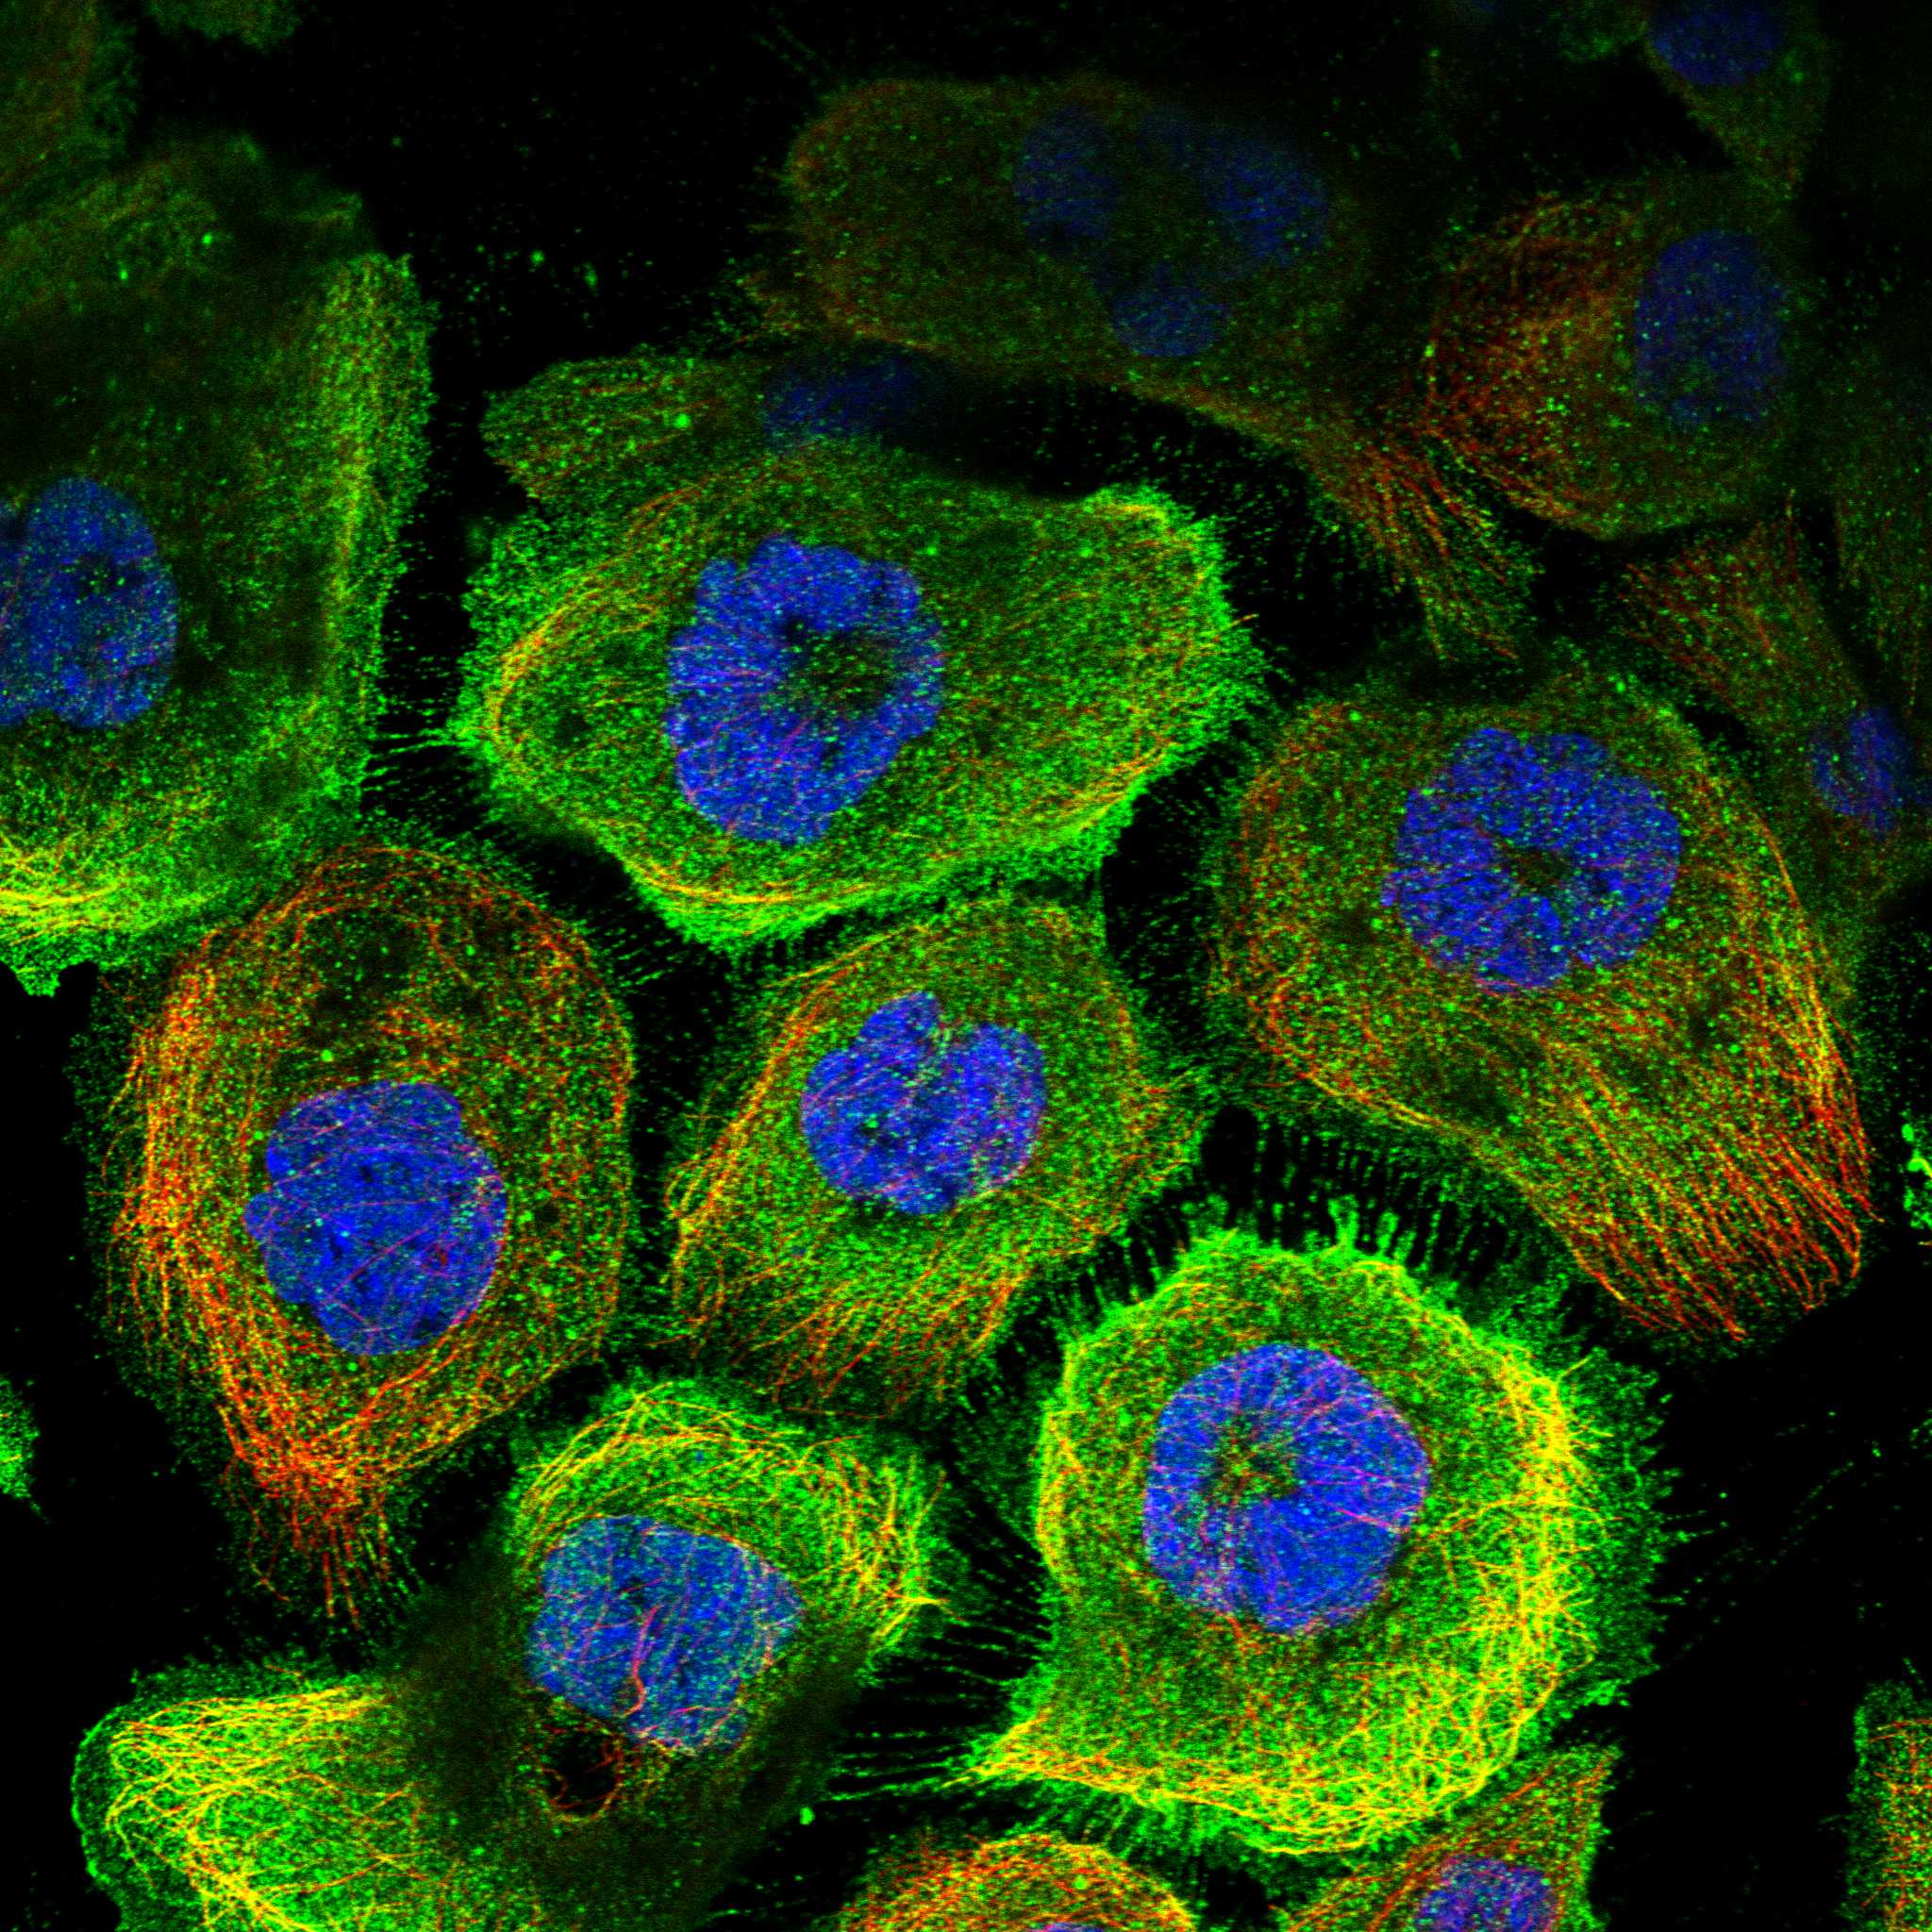
| Strong nuclear staining appears in otherwise positive cells, or a membrane rim dominates the chromogenic IHC result. | Nuclear dominance conflicts with cytoplasmic tissue IHC and mitochondrial annotation; investigate artefact (HPA tissue IHC; UniProt Q8N5Z0). A membrane rim needs separate evaluation: HPA reports approved plasma-membrane localisation in ICC-IF, so its IF observation cannot simply be dismissed or assumed to validate membrane staining in paraffin IHC (HPA subcellular ICC-IF). |
| Adipocytes, respiratory epithelial cells or bone-marrow hematopoietic cells stain prominently. | HPA reports AADAT as Not detected in those cells (HPA tissue IHC). A strong result there raises concern for cross-reactivity, endogenous chromogenic activity or nonspecific binding (general IHC practice). Review the negative control and compare the suspect cells with hepatocytes or proximal tubules before assigning target positivity. |
| Color spreads across stroma, lumina and many unrelated cells without clear cell-body localisation. | This is less persuasive than the reported cytoplasmic staining of selected cell types (HPA tissue IHC). Diffuse color can reflect background from detection chemistry, antibody concentration or incomplete blocking (general IHC practice); it does not establish a new AADAT-positive tissue pattern. |
| Hepatocytes or renal proximal tubules lack visible signal in the same run. | Both are reported at Medium staining level and provide useful positive reference cells (HPA tissue IHC). Check section quality, retrieval, antibody application and detection with run controls (general IHC practice). Absence of staining alone does not prove biological absence, particularly given HPA's reported medium staining–RNA consistency (HPA tissue IHC). |
| Tissue and cell selection | Liver hepatocytes and kidney proximal tubules are reported at Medium level; gastrointestinal glandular cells are low (HPA tissue IHC). Use the first two as positive references and interpret a faint gastrointestinal result in that context, without imposing a single intensity threshold across tissues. |
| Compartment evidence | UniProt assigns AADAT to mitochondria and annotates no transmembrane segment; tissue IHC describes cytoplasmic expression (UniProt Q8N5Z0; HPA tissue IHC). Conventional chromogenic IHC may show cell-body cytoplasm without resolving individual mitochondria (general microscopy practice). |
| IHC versus IF/ICC localisation | Q: Should an IF/ICC plasma-membrane image redefine the paraffin IHC pattern? A: No. HPA's approved ICC-IF main location is plasma membrane, with vesicles additional, whereas its tissue IHC profile is cytoplasmic (HPA subcellular ICC-IF; HPA tissue IHC). Interpret each application against its own evidence. |
| Protein forms and epitope information | UniProt lists two isoforms and a chain spanning residues 30–425 (UniProt Q8N5Z0). No antibody epitope or isoform-specific IHC result is supplied, so neither feature predicts which form the IHC-validated antibody detects or explains a missing tissue signal. |
| Validation strength | HPA lists antibody HPA037502 as IHC Enhanced and ICC Approved; its tissue profile notes medium consistency with RNA expression (HPA antibodies; HPA tissue IHC). These labels support using the reported pattern as a reference, while leaving discrepant cells and compartments to be checked with controls. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected hepatocyte and proximal-tubule staining is absent. | A failed retrieval, primary-antibody or detection step is possible (general IHC practice); both cell types have Medium staining in HPA (HPA tissue IHC). | Review the run's positive control and each IHC step, then repeat under the established paraffin IHC conditions (general IHC practice). Do not infer AADAT loss from one blank section. |
| The whole section has diffuse brown background. | Nonspecific antibody binding, excess primary antibody or detection background can obscure a cell-specific pattern (general IHC practice). | Compare a no-primary control, check blocking and detection, and optimize primary-antibody concentration within a validated IHC workflow (general IHC practice). Reassess hepatocytes and proximal tubules against the HPA pattern (HPA tissue IHC). |
| Unexpected cell types stain strongly. | Cross-reactivity or endogenous chromogenic activity is possible (general IHC practice), especially in cells reported Not detected by HPA (HPA tissue IHC). | Inspect tissue-matched negative controls and the detection-only control; confirm that expected positive cells stain in the same run (general IHC practice; HPA tissue IHC). Treat the unexpected cells as unresolved until those checks agree. |
| Nuclear color dominates the section. | That compartment conflicts with HPA's cytoplasmic tissue profile and UniProt's mitochondrial annotation (HPA tissue IHC; UniProt Q8N5Z0). | Check counterstain, chromogen deposition and no-primary control before scoring nuclei as positive (general IHC practice). Re-evaluate whether cytoplasmic cell-body staining remains in the reported positive cells (HPA tissue IHC). |
| Gastrointestinal glands look nearly negative while liver and kidney controls stain. | Gastrointestinal glandular staining is reported as low, compared with Medium hepatocyte and proximal-tubule staining (HPA tissue IHC). | Interpret the faint result against the stronger controls and local background (general IHC practice). Avoid increasing detection solely to force gastrointestinal glands to match liver or kidney intensity (HPA tissue IHC). |
| A membrane rim appears in paraffin IHC and resembles the ICC-IF report. | HPA approves plasma-membrane localisation in ICC-IF, while its tissue IHC profile describes cytoplasm; the supplied evidence does not resolve this application difference (HPA subcellular ICC-IF; HPA tissue IHC). | Score the IHC slide against its tissue controls and cytoplasmic reference pattern; inspect negative controls for edge staining (HPA tissue IHC; general IHC practice). Record persistent membrane staining as a discrepancy, rather than assigning it automatically to AADAT. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Kidney | Proximal tubules (cell body) | Medium | Protein (IHC) | HPA → |
| Liver | Hepatocytes | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot AADAT staining in paraffin sections by checking retrieval, compartment, cell identity, and controls before interpreting intensity.
A09111 has real IHC data from paraffin-embedded human liver (A09111 IHC image caption). IF/ICC is listed without an IF image (catalog applications; catalog IF image alts). Human, mouse, and rat reactivity is listed (catalog reactivity).
A09111 is listed for IHC, IF, and ICC and for human, mouse, and rat reactivity (catalog applications; catalog reactivity). Its IHC image shows paraffin-embedded human liver stained at 1:200 after high-pressure retrieval in 10 mM citrate, pH 6.0 (A09111 IHC image caption); no IF image is supplied (catalog IF image alts).
Which to pick: Choose A09111 for paraffin-section tissue IHC based on its human liver image (A09111 IHC image caption); the fixative is unreported (A09111 IHC image caption). For IF/ICC, A09111 is listed with a 1:50–1:200 dilution range, though no IF image is supplied (catalog applications; catalog IF dilution; catalog IF image alts). A09111 is the listed option for human, mouse, and rat, and its IHC caption identifies it as a rabbit polyclonal antibody (catalog reactivity; A09111 IHC image caption).