ACAD9 / Complex I assembly factor ACAD9, mitochondrial · IHC design guide

Design Immunohistochemistry for ACAD9

Plan ACAD9 paraffin IHC around granular cytoplasmic staining (HPA tissue IHC) and mitochondrial inner membrane association (UniProt). This guide covers cell-specific controls, scoring and the catalog antibody’s IHC concentration of 2–5 μg/ml (datasheet A05223-3).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ACAD9 (IHC for ACAD9): expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial inner membrane (UniProt), antibody A05223-3, validated IHC image, and IHC protocol steps
Printable ACAD9 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial inner membrane (UniProt), antibody A05223-3, controls and protocol steps. Open the full ACAD9 IHC guide →

ACAD9 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial inner membrane (UniProt)
Staining pattern General granular cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A05223-3)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Low staining in skeletal myocytes (HPA tissue IHC) despite higher muscle expression (UniProt)
Regulation Higher expression in heart, muscle and CNS (UniProt)
Isoform / epitope No isoforms annotated; mature chain spans residues 38–621 (UniProt)
Section 1

Recommended ACAD9 IHC & IF Protocols

The catalog antibody protocol uses heat-mediated EDTA pH 8.0 retrieval (datasheet A05223-3). The published femur IHC protocol below uses citrate retrieval (PMC13039524: methods).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A05223-3)
FixationImage fixative and duration unreported (datasheet A05223-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A05223-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05223-3)
Primary antibodyRabbit anti-ACAD9, 2-5 μg/ml (datasheet A05223-3)
Primary incubationOvernight at 4 °C (datasheet A05223-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A05223-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultACAD9-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression with granular pattern. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 retrieval for the catalog antibody (datasheet A05223-3); consider 0.01 M citrate when optimizing femur sections (PMC13039524: methods).
Section 2

What Is the Expected ACAD9 Staining Pattern?

ACAD9 is essentially associated with the mitochondrial inner membrane, with no annotated transmembrane segment (UniProt Q9H845 topology). In paraffin-section IHC, expect granular cytoplasmic staining in the cell types HPA identifies as positive, including appendix and colon glandular cells and cerebellar granular-layer cells (HPA tissue IHC). HPA rates its tissue staining evidence Supported, with medium agreement between staining and RNA data and external verification pending (HPA tissue IHC).

What am I looking at on my slide?
Granular cytoplasmic staining in appendix or colon glandular cells, or cerebellar granular-layer cells (HPA tissue IHC: High).This matches HPA's general granular cytoplasmic profile and is consistent with mitochondrial localisation (HPA tissue IHC; UniProt Q9H845 localisation). Chromogenic IHC cannot resolve the inner membrane itself (general IHC practice).
Predominantly nuclear or sharp cell-surface staining, without a granular cytoplasmic component.That compartment conflicts with ACAD9's mitochondrial assignment (UniProt Q9H845 localisation; HPA subcellular ICC-IF). Check whether the pattern also appears in a reagent control before interpreting it as ACAD9 (general IHC practice).
Strong staining in adipocytes, ovarian stromal cells, or smooth muscle cells (HPA tissue IHC: Not detected).Treat an isolated signal there as possible cross-reactivity or endogenous chromogenic activity, especially if expected positive cells fail to stain (general IHC practice). HPA's Not detected result is an observed IHC finding, not proof that ACAD9 is absent from every cell (HPA tissue IHC).
Uniform colour across stroma, lumens, or most cells, obscuring cytoplasmic granules.Diffuse signal cannot establish ACAD9 localisation against HPA's granular cytoplasmic profile (HPA tissue IHC). Assess reagent-control staining and detection background, then compare cell-restricted staining within the same section (general IHC practice).
No staining in a section containing HPA-high appendix glandular cells or cerebellar granular-layer cells (HPA tissue IHC).A blank expected-positive compartment makes the run inconclusive; review tissue preservation, retrieval, antibody and detection controls (general IHC practice). HPA's Supported rating and pending external verification also limit certainty about any single reference tissue (HPA tissue IHC).
💡Expected ACAD9 appearanceCall positive a granular cytoplasmic signal in an HPA-high cell type, such as appendix glandular cells or cerebellar granular-layer cells (HPA tissue IHC: High); prominent nuclear, surface, or uniform stromal colour is suspicious against the mitochondrial assignment (UniProt Q9H845 localisation; general IHC practice).
How each factor affects the staining
Compartment and resolutionACAD9 is essentially inner-membrane-associated despite lacking a transmembrane segment (UniProt Q9H845 topology). Expect a cytoplasmic mitochondrial pattern; routine chromogenic IHC cannot identify which mitochondrial membrane contains the antigen (general IHC practice).
Choice of reference cellsHPA reports High staining in several epithelial and neural cell types, but Low staining in skeletal myocytes (HPA tissue IHC). UniProt describes higher expression in skeletal muscle (UniProt Q9H845 tissue specificity); expression and IHC intensity should therefore be interpreted separately.
Antibody and epitope evidenceHPA037716 is Supported for IHC; HPA046720 has no listed IHC status (HPA antibody validation). UniProt lists a mature chain spanning residues 38–621 (UniProt Q9H845 processing). The supplied record gives no antibody epitope, so epitope-dependent staining predictions are unverified.
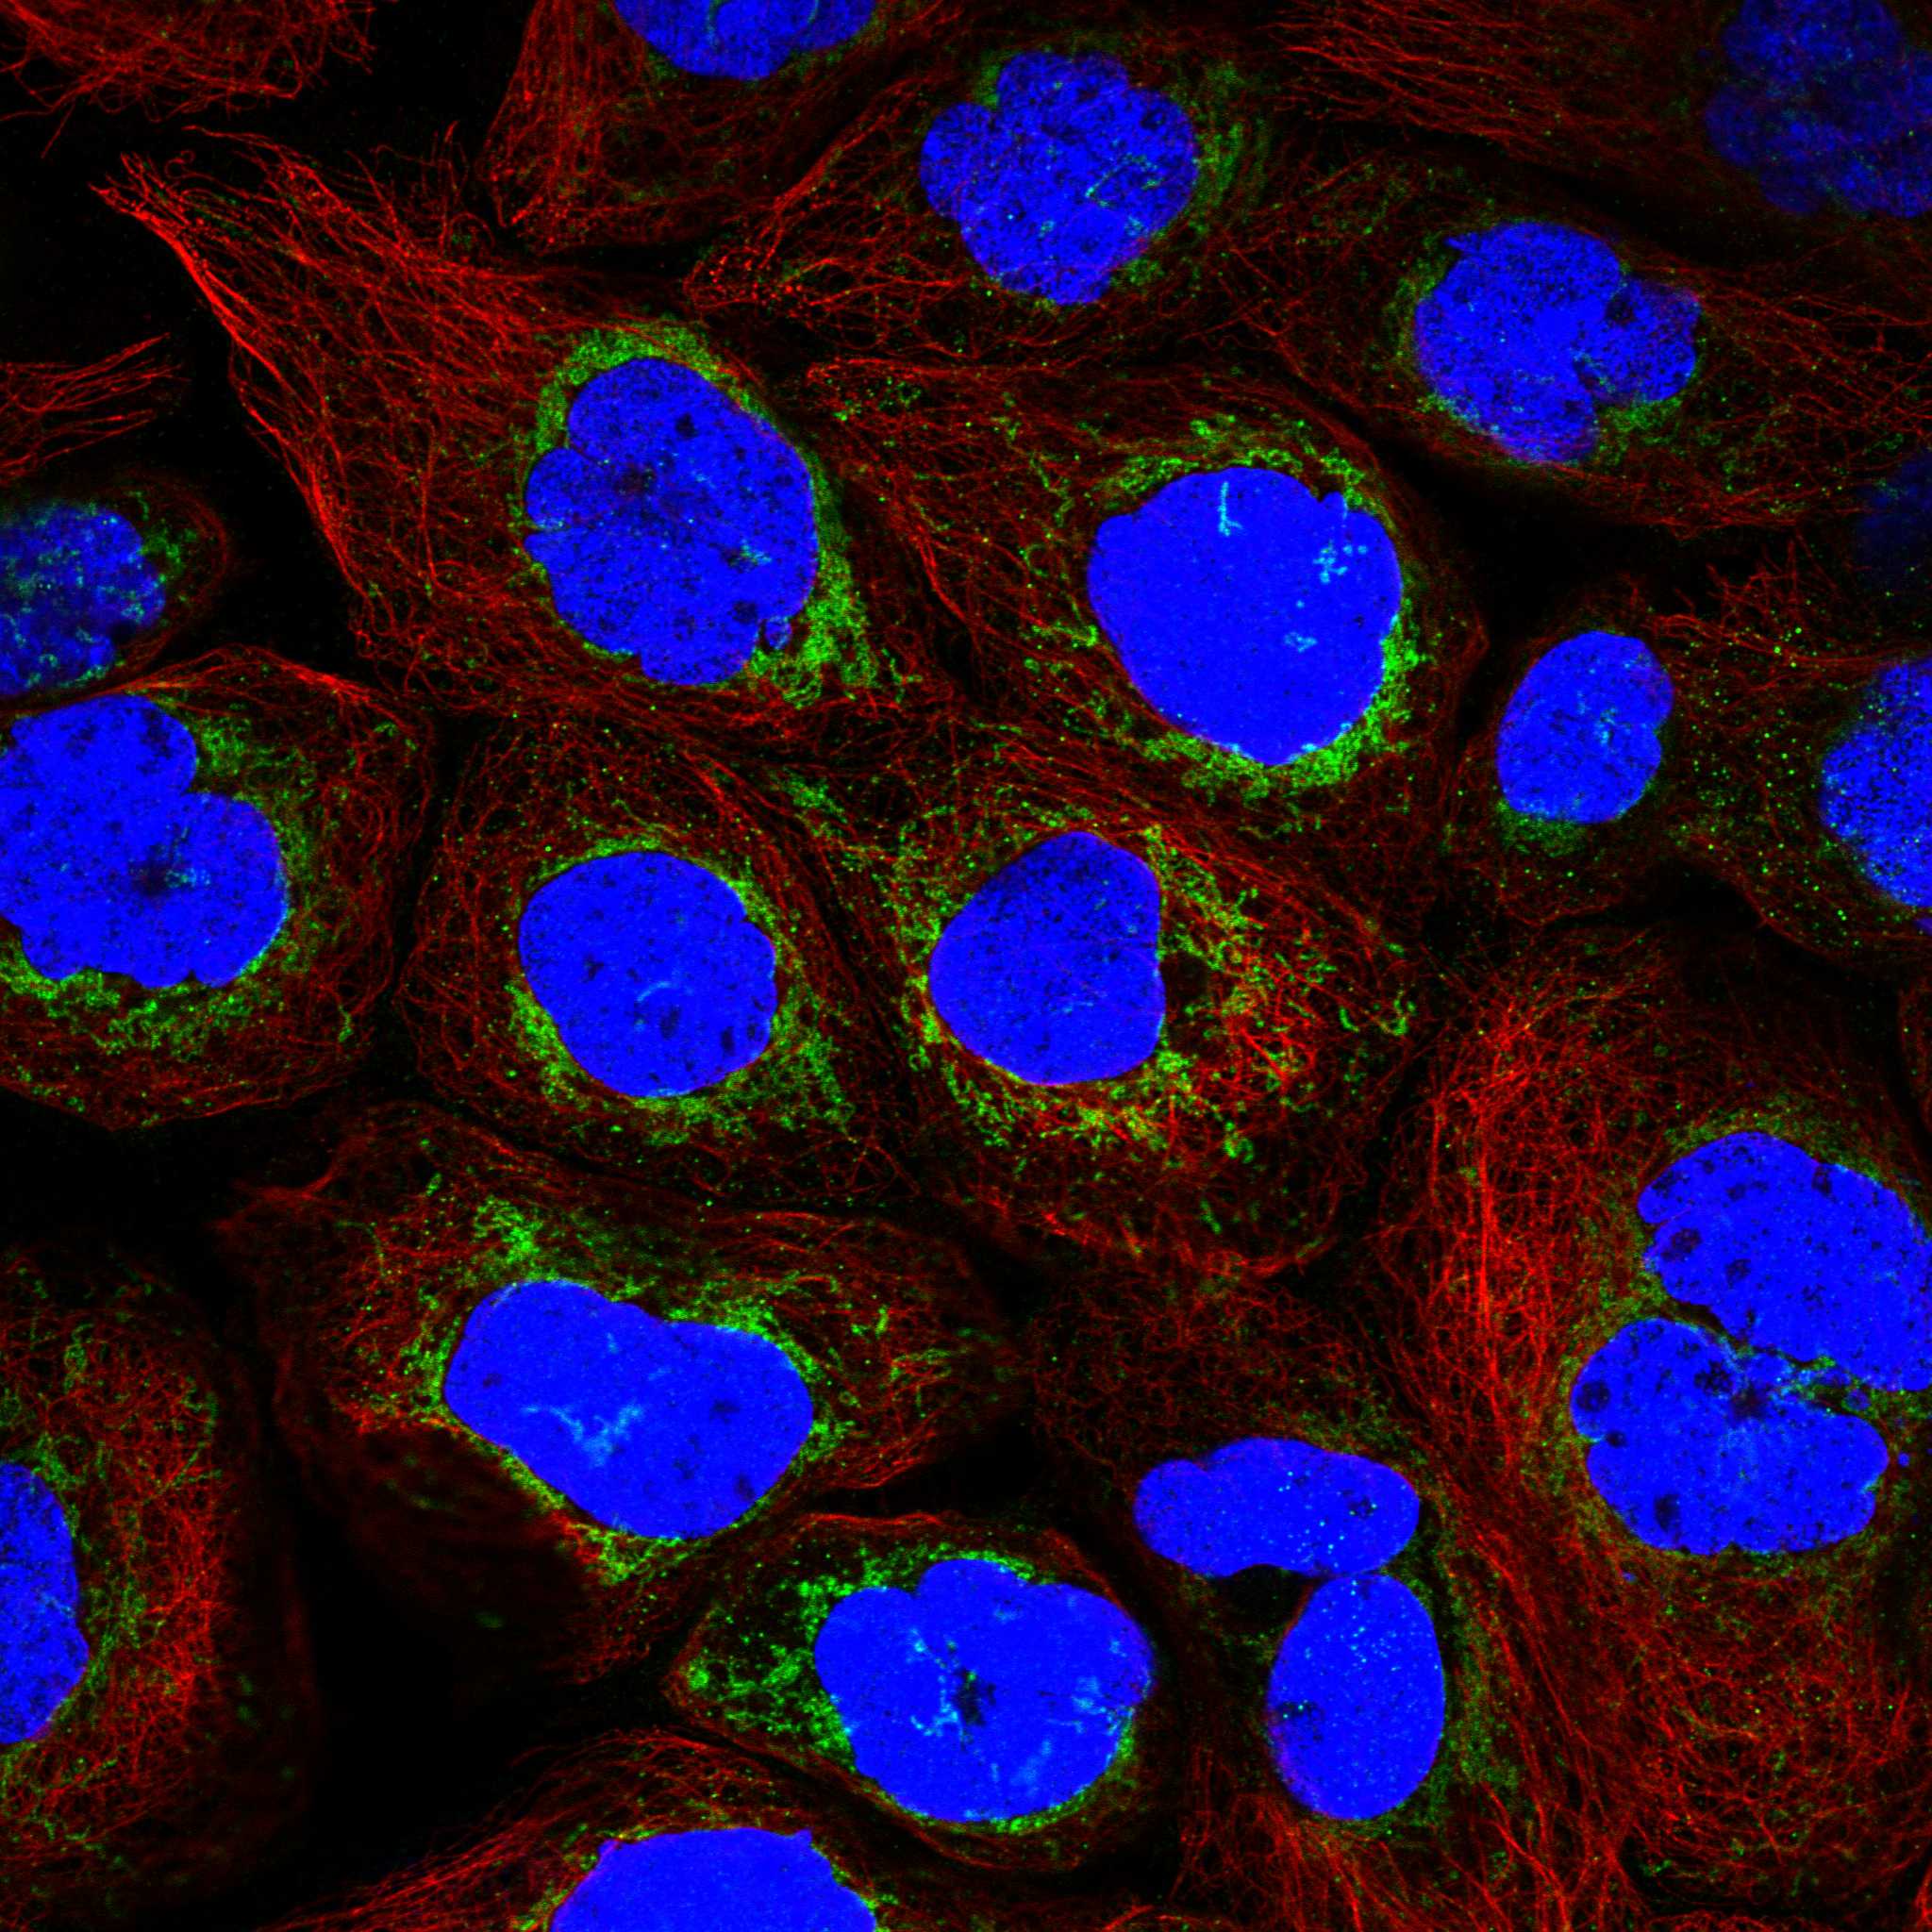
IF/ICC: What pattern corroborates IHC?Mitochondrial localisation in A-431 or U2OS images supports the compartment call (HPA subcellular ICC-IF: Mitochondria, enhanced). This answers the IF/ICC localisation question; those images do not establish a paraffin-section IHC protocol or tissue intensity (HPA subcellular ICC-IF; HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
An expected-positive glandular or cerebellar cell population is blank (HPA tissue IHC: High).The run may have failed at retrieval, primary-antibody staining, or chromogenic detection (general IHC practice).Check run controls and the catalog antibody's IHC-P instructions; compare another HPA-high cell population before assigning a biological negative (HPA tissue IHC; general IHC practice).
Cytoplasmic staining is weak but still granular.HPA intensity varies by cell type: prostate glandular cells and skeletal myocytes are Low (HPA tissue IHC).Compare like cell types and exposure conditions; use an HPA-high reference population to judge assay performance (HPA tissue IHC; general IHC practice).
Most of the section has diffuse brown colour.Excess detection background or endogenous chromogenic activity may obscure the granular profile (general IHC practice; HPA tissue IHC: granular cytoplasm).Inspect reagent controls, blocking and wash performance, then score only cell-associated granular staining (general IHC practice).
Nuclear or surface staining dominates.That distribution conflicts with mitochondrial ACAD9 (UniProt Q9H845 localisation; HPA subcellular ICC-IF).Compare reagent controls and an HPA-high cell population; avoid calling ACAD9 positive from the discordant compartment alone (general IHC practice; HPA tissue IHC).
Adipocytes or smooth muscle stain strongly (HPA tissue IHC: Not detected).Cross-reactivity or endogenous detection activity is possible; HPA's tissue evidence remains Supported with external verification pending (general IHC practice; HPA tissue IHC).Check reagent controls and whether expected-positive cells show the granular profile; report the discordance rather than treating HPA's Not detected result as an absolute biological negative (HPA tissue IHC).

Sample controls for ACAD9 IHC & IF

🧪Run colon first: glandular cells should stain (HPA: High in colon glandular cells). Use smooth muscle tissue as the negative comparator (HPA: Not detected in smooth muscle cells); on the colon slide, assess morphologically identified smooth muscle cells for background-level staining as an internal comparator, while verifying their signal on that section.
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ACAD9 in A-431, U2OS, with annotated localisation: Mitochondria (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section and a concentration-matched rabbit isotype control (selected-SKU IHC caption: rabbit primary antibody). Use ACAD9 knockout material, if available, as a biological specificity control; block endogenous peroxidase and check erythrocytes and inflammatory cells for residual DAB signal in the colon section (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact A05223-3 tissue-IHC caption does not report a fixative. Heat retrieval in EDTA at pH 8.0 is a documented starting condition, but retrieval dependency is unreported (selected-SKU IHC caption: heat-mediated EDTA retrieval, pH 8.0). The supplied evidence does not establish whether frozen sections or IF are easier; colonic erythrocytes and inflammatory cells warrant scrutiny for peroxidase background (standard chromogenic IHC practice).

HPA tissue IHC evidence for ACAD9

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Cerebellum Cells in granular layer High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced ACAD9 IHC Tips

Use the documented ACAD9 staining conditions as a starting point, then assess compartment, cell type and controls before scoring paraffin sections.

How should I optimize retrieval when ACAD9 staining is weak in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A05223-3). Keep the catalog antibody at the documented 2 μg/ml and incubate overnight at 4°C while assessing retrieval, so changes in staining are easier to attribute (datasheet A05223-3; standard IHC practice). If signal remains weak, compare a shorter and longer heating period on adjacent sections while keeping the buffer unchanged (standard IHC practice). If that fails, test an alternative retrieval buffer as a fallback, with a matched positive-control section in every run (standard IHC practice). Judge improvement by granular cytoplasmic staining rather than diffuse darkening (HPA: general cytoplasmic expression with granular pattern).
Could fixation explain weak or uneven ACAD9 staining?
The ACAD9 tissue caption describes a paraffin section but does not state its fixative, so target-specific fixation sensitivity is unknown (datasheet A05223-3). Record each specimen’s fixative and fixation duration, then compare sections processed and stained together before attributing a signal difference to ACAD9 expression (standard IHC practice). Use the documented EDTA pH 8.0 retrieval and 2 μg/ml primary concentration consistently in that comparison (datasheet A05223-3). Include a positive-control section with each batch and inspect tissue preservation; patchy staining in poorly preserved areas calls for caution (standard IHC practice). Neither the tissue staining profile nor mitochondrial location establishes a fixation effect (HPA: tissue IHC profile; UniProt Q9H845: inner-membrane association).
Which ACAD9 staining pattern should I accept as correctly localised?
Look for granular cytoplasmic staining in paraffin sections, matching the reported tissue pattern (HPA: general cytoplasmic expression with granular pattern). ACAD9 is associated with the mitochondrial inner membrane, and independent imaging places it in mitochondria (UniProt Q9H845: subcellular location; HPA: mitochondria, enhanced). At routine chromogenic resolution, score the cytoplasmic granularity without claiming that individual DAB puncta identify a particular mitochondrial membrane (standard IHC practice). Compare staining across intact cells and nearby tissue, using the same exposure to retrieval, primary antibody and chromogen (standard IHC practice). Predominantly nuclear or uniform extracellular staining warrants a specificity review before it is called ACAD9 (UniProt Q9H845: mitochondrial location; standard IHC practice).
Can processing or epitope position change how ACAD9 appears in IHC?
Check the catalog antibody’s stated immunogen or epitope before interpreting a failed stain, because the supplied tissue caption does not identify it (datasheet A05223-3). The record lists a processed ACAD9 chain spanning residues 38–621, with no annotated isoforms or transmembrane segment (UniProt Q9H845: processing, isoforms and topology). Those annotations alone cannot establish whether this antibody recognizes the precursor, mature chain or a modification-sensitive epitope (UniProt Q9H845: processing and modified residues; standard IHC practice). If competing antibodies are available, compare ones with documented, distinct epitopes on adjacent sections under matched staining conditions (standard IHC practice). Interpret disagreement with staining controls and tissue morphology before assigning it to an ACAD9 variant (standard IHC practice).
How can IF help investigate an ambiguous chromogenic ACAD9 pattern?
Use a separate IF assay to compare ACAD9 with a mitochondrial marker and a marker identifying the cell type being assessed; mitochondrial localisation is supported independently (HPA: mitochondria, enhanced; standard IF practice). Choose well-separated fluorophores and inspect unstained tissue in each channel, especially where tissue autofluorescence may resemble puncta (standard IF practice). ACAD9 is essentially membrane-associated but has no annotated transmembrane segment or established epitope orientation for this antibody (UniProt Q9H845: location and topology; datasheet A05223-3: epitope unstated). Compare gentle and stronger permeabilisation with matched controls to establish access to the antibody’s epitope, without assuming which side of the membrane it faces (standard IF practice).
How do I reduce diffuse DAB staining without losing ACAD9 signal?
First compare a no-primary section with the stained section to distinguish detection-system background from primary-dependent staining (standard IHC practice). The documented assay used a peroxidase-conjugated secondary and DAB, so apply a peroxidase block as a general chromogenic IHC step, then check secondary-only signal (datasheet A05223-3; standard IHC practice). The caption used 10% goat serum for blocking and 2 μg/ml primary antibody overnight at 4°C; retain those conditions as the initial comparison (datasheet A05223-3). If background persists, titrate primary concentration or DAB development on matched sections while preserving a positive control (standard IHC practice). Prefer crisp granular cytoplasmic staining over diffuse haze (HPA: tissue staining pattern).
What should I measure when comparing ACAD9 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region before scoring, because ACAD9 staining varies among tissue cell types (HPA: tissue IHC profile). For chromogenic sections, record the percentage of positive target cells and staining intensity, or calculate an H-score from those two observations (standard IHC practice). When cell density differs, report positive cells per mm² of viable tissue or per total counted target cells, and state the denominator (standard IHC practice). Use matched retrieval, antibody concentration, DAB development and image-analysis thresholds across groups (standard IHC practice). Exclude folds and necrotic areas, and report granular cytoplasmic staining separately from nonspecific diffuse colour (HPA: tissue staining pattern; standard IHC practice).
When should an apparent ACAD9-positive cell be treated as artefact?
Give greatest weight to staining within intact cells that has a granular cytoplasmic pattern, consistent with ACAD9’s mitochondrial location (HPA: tissue staining pattern; UniProt Q9H845: subcellular location). Check the cell identity: HPA reports high staining in cerebellar granular-layer cells but no detection in adipocytes, so a signal in the latter needs closer scrutiny (HPA: cerebellum and adipose tissue IHC). Treat isolated section-edge darkening, necrotic debris and extracellular precipitate as possible processing artefacts (standard IHC practice). A positive no-primary control suggests detection-system background, including endogenous peroxidase activity in a DAB assay (standard IHC practice). Reassess predominantly nuclear staining against a positive-control section before assigning it to ACAD9 (UniProt Q9H845: mitochondrial location; standard IHC practice).
Boster reagents

Best ACAD9 / Complex I assembly factor ACAD9, mitochondrial IHC Antibodies

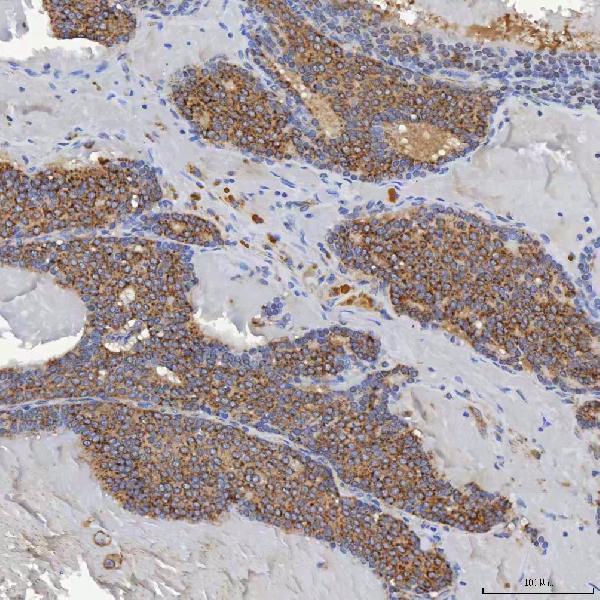
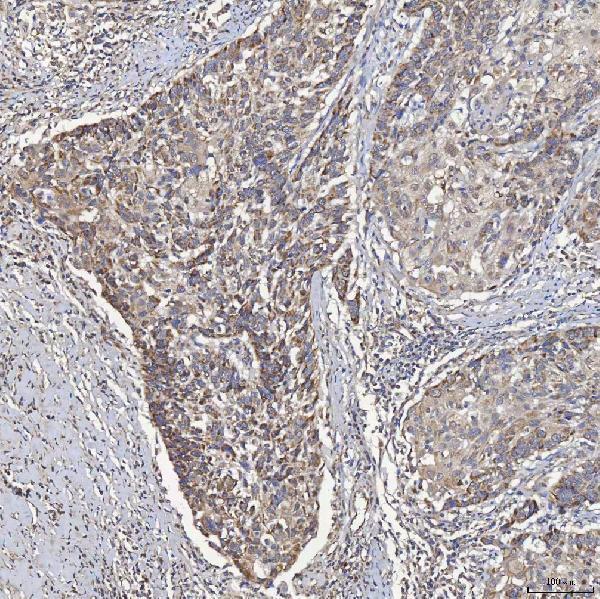
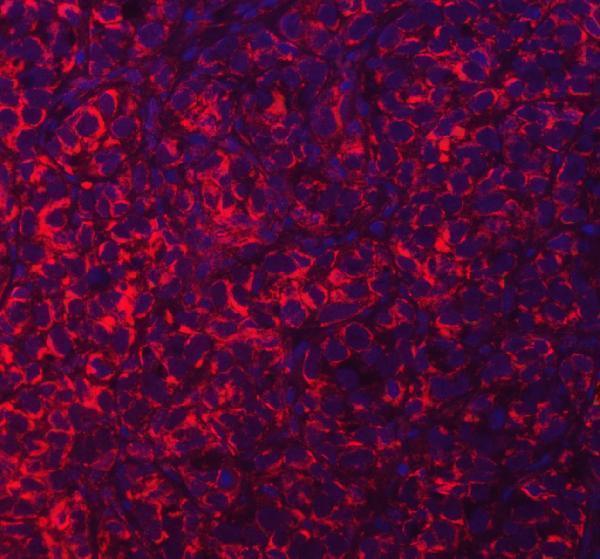
A05223-3 has human paraffin-section IHC images and a human paraffin-section IF image (catalog image captions).

Real IHC data IHC analysis of ACAD9 using anti-ACAD9 antibody (A05223-3). ACAD9 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ACAD9 Antibody (A05223-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-ACAD9 Antibody ®
Cat # A05223-3

A05223-3 is listed for human IHC and IF (catalog applications; reactivity: Human). Its IHC captions show human breast, larynx, liver, and lung cancer sections, while its IF caption shows a human breast cancer section (catalog image captions).

Which to pick: For human paraffin-section IHC, choose A05223-3; its own IHC captions document EDTA retrieval at pH 8.0 and staining at 2 μg/ml (A05223-3 IHC captions). For IF, the same SKU has a human paraffin-section image at 5 μg/ml; ICC validation is unreported (A05223-3 IF caption; catalog applications). No cross-species option is documented because reactivity is listed only for human, and the paraffin-section captions do not report a fixative (catalog reactivity; A05223-3 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.