This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
This ACER3 paraffin IHC guide uses ER/Golgi localisation as a molecular expectation (UniProt). Compare staining with high signal in placenta decidual cells (HPA tissue IHC) and optimize the catalog antibody within 1:100–1:300 (datasheet).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | ER/Golgi membranes expected; tissue compartment unreported (UniProt; HPA tissue IHC) | |
| Staining pattern | Endothelial cell staining; subcellular pattern unspecified (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Endometrium+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Low agreement between antibody staining and RNA expression (HPA tissue IHC) | |
| Regulation | Expression regulation unreported (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope location and coverage unknown (UniProt) |
Compare the catalog antibody's IHC-P protocol with the published mouse liver IHC method (PMC11873283: IHC methods).
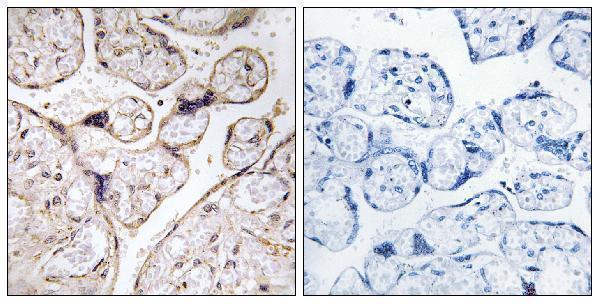
| Sample | Paraffin-embedded human placenta tissue; fixative not specified (datasheet A10457-2) |
| Fixation | Image fixative and duration unreported (datasheet A10457-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ACER3, 1:100-1:300 (datasheet A10457-2) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ACER3-positive staining in glandular cells of endometrium (HPA tissue IHC: High). HPA tissue profile: Expressed in endothelial cells. No signal in the no-primary control. |
ACER3 is a 7-pass protein of the endoplasmic reticulum and Golgi membranes (UniProt Q9NUN7 topology and subcellular location). In paraffin-section IHC, assess membrane-associated cytoplasmic staining in the relevant cell population: HPA reports high staining in lung macrophages, endometrial glandular cells and several other specified cells (HPA tissue IHC). Treat the pattern as provisional because HPA rates its IHC antibody Approved but reports low consistency with RNA expression (HPA tissue IHC; HPA antibodies).
| Staining follows a cytoplasmic, often perinuclear, membrane-associated pattern in lung macrophages or endometrial glandular cells (UniProt Q9NUN7 subcellular location; HPA: High in both cell populations). | This fits the predicted ER/Golgi compartment and an HPA-observed positive population (UniProt Q9NUN7 subcellular location; HPA tissue IHC). Score the identified cells and their staining intensity; the distribution alone does not prove antibody specificity (general IHC practice). |
| Strong nuclear-only staining appears while cytoplasmic staining is absent (observed-slide scenario). | A nuclear-only pattern conflicts with ACER3's annotated ER/Golgi membrane location (UniProt Q9NUN7 subcellular location). Check a no-primary control and an HPA-observed positive cell population before interpreting that signal as ACER3 (general IHC practice; HPA tissue IHC). |
| Strong signal appears in adipocytes that were chosen as a low-signal comparator (observed-slide scenario; HPA: Not detected in adipose-tissue adipocytes). | HPA reports those adipocytes as Not detected, so strong staining there warrants a specificity or detection-background check (HPA tissue IHC; general IHC practice). HPA's Approved rating and low RNA–staining consistency limit the certainty of any tissue-based call (HPA tissue IHC). |
| Color spreads across tissue or appears in empty areas without a cell-specific pattern (observed-slide scenario). | Interpret this as background until controls establish otherwise (general IHC practice). Uneven blocking, residual detection activity or excess detection reagent can obscure a membrane-associated cytoplasmic pattern (general IHC practice; UniProt Q9NUN7 subcellular location). |
| No signal appears in lung macrophages or endometrial glandular cells (observed-slide scenario; HPA: High in both cell populations). | A negative result in an HPA-observed positive population calls for a run-level check before a biological conclusion (HPA tissue IHC; general IHC practice). Verify cell identification, tissue preservation, retrieval and detection controls; HPA staining is a reference pattern, not a guarantee for every specimen (general IHC practice; HPA tissue IHC). |
| Which compartment should guide scoring? | ACER3 has 7 transmembrane segments and is annotated at ER and Golgi membranes (UniProt Q9NUN7 topology and subcellular location). Its exact antibody epitope is not supplied, so topology alone cannot set an antigen-retrieval condition (UniProt Q9NUN7 topology; evidence limitation). |
| Which cells provide useful comparators? | HPA reports High staining in lung macrophages, endometrial glandular cells, kidney glomerular cells and placental decidual cells; adipose-tissue adipocytes are Not detected (HPA tissue IHC). Choose comparators by the specified cell type within each tissue (HPA tissue IHC). |
| How firm is the tissue pattern? | The tissue-IHC reliability label is Approved, with low consistency between antibody staining and RNA expression; the listed antibody's IHC status is Approved (HPA tissue IHC; HPA antibodies). Interpret an unexpected cell pattern cautiously and review controls (general IHC practice). |
| Do variants or processing predict another pattern? | UniProt lists 2 isoforms, one chain spanning residues 1–267, and no annotated signal peptide, propeptide or glycosylation sites (UniProt Q9NUN7 isoforms, processing and glycosylation). The supplied record does not map an antibody epitope to either isoform (evidence limitation). |
| What does IF/ICC add? | HPA summarizes the ICC-IF location as Membrane but supplies no main location or cell-line images (HPA subcellular ICC-IF). That summary supports a broad membrane expectation; it cannot establish an IF staining pattern or an IF protocol (HPA subcellular ICC-IF; evidence limitation). |
| Situation | Likely cause | Next action |
|---|---|---|
| The HPA-observed positive cells are unstained (HPA: High in lung macrophages and endometrial glandular cells). | The cells may be missed during scoring, or a staining-run step may have failed (general IHC practice). | Locate the specified cells, then check the run's positive control, retrieval and detection steps (HPA tissue IHC; general IHC practice). |
| Only nuclei are stained (observed-slide scenario). | Nuclear-only signal does not match the annotated ER/Golgi membrane location (UniProt Q9NUN7 subcellular location). | Compare with a no-primary control and an HPA-observed positive population; withhold an ACER3 call if nuclear-only staining persists (general IHC practice; HPA tissue IHC). |
| Strong staining appears in adipose-tissue adipocytes (observed-slide scenario; HPA: Not detected). | The result disagrees with the HPA cell-specific reference and may reflect nonspecific staining or detection activity (HPA tissue IHC; general IHC practice). | Check no-primary and detection controls, then score adipocytes separately from neighboring cells (general IHC practice; HPA tissue IHC). |
| Background obscures cell boundaries (observed-slide scenario). | Blocking, washing or detection background may reduce readable contrast (general IHC practice). | Review the no-primary control and the blocking and wash steps; judge positive staining only where cell boundaries remain interpretable (general IHC practice). |
| A tissue appears mixed or patchy (observed-slide scenario). | HPA levels apply to named cell populations, not every cell in that tissue; its staining has low RNA consistency (HPA tissue IHC). | Score the named cells separately and record distribution alongside intensity (HPA tissue IHC; general IHC practice). |
| An IF image appears to conflict with IHC (observed-slide scenario). | HPA's ICC-IF entry reports only Membrane, without a main location or cell-line images (HPA subcellular ICC-IF). | Keep IF interpretation in its own guide and compare only the broad membrane expectation here; do not infer an IF protocol from the IHC record (HPA subcellular ICC-IF; evidence limitation). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Endometrium | Glandular cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in glomeruli | High | Protein (IHC) | HPA → |
| Lung | Macrophages | High | Protein (IHC) | HPA → |
| Placenta | Decidual cells | High | Protein (IHC) | HPA → |
| Skin | Fibroblasts | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
Troubleshoot ACER3 staining in paraffin sections by checking retrieval, cell type and membrane associated localisation before comparing signal intensity.
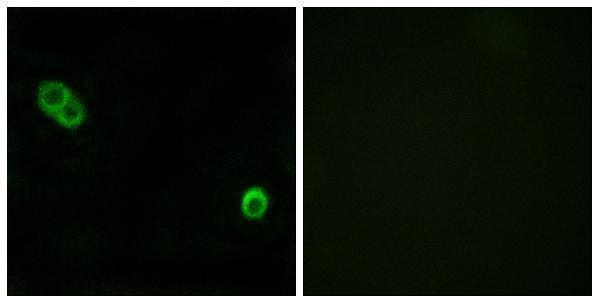
A10457-2 lists IHC and IF applications and human and mouse reactivity (catalog); its figures show paraffin-embedded human placenta IHC and MCF7-cell IF (image captions).
A10457-2 is listed for IHC and IF in human and mouse samples (catalog: applications and reactivity). Its IHC figure shows paraffin-embedded human placenta, and its IF figure shows MCF7 cells; both captions call the antibody “PHCA” (image captions).
Which to pick: For tissue IHC, A10457-2 has a paraffin-embedded human placenta image (IHC caption); the fixative is unreported (IHC caption). For cell IF, A10457-2 has an MCF7 image (IF caption), while ICC is not separately listed (catalog: applications). A10457-2 also lists mouse reactivity, but the supplied figures do not show mouse samples (catalog: reactivity; image captions); clonality is unreported (catalog: clone field).