ACOT9 / Acyl-coenzyme A thioesterase 9, mitochondrial · IHC design guide

Design Immunohistochemistry for ACOT9

Plan ACOT9 staining in paraffin sections using the expected granular cytoplasmic pattern (HPA tissue IHC). This guide covers fixation, interpretation and controls, including tissue choices supported by the Human Protein Atlas (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ACOT9 (IHC for ACOT9): expected localisation Granular cytoplasmic, mitochondrial pattern (HPA tissue IHC), antibody A14147-1, validated IHC image, and IHC protocol steps
Printable ACOT9 IHC protocol sheet — expected localisation Granular cytoplasmic, mitochondrial pattern (HPA tissue IHC), antibody A14147-1, controls and protocol steps. Open the full ACOT9 IHC guide →

ACOT9 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasmic, mitochondrial pattern (HPA tissue IHC)
Staining pattern Cells across tissues show granular cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining and RNA expression have medium consistency (HPA tissue IHC)
Regulation Expression regulation is not annotated (UniProt)
Isoform / epitope 4 isoforms; the mature chain starts at residue 22 (UniProt)
Section 1

Recommended ACOT9 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with two published ACOT9 paraffin-section IHC workflows (PMC13374139; PMC13335382).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon carcinoma tissue; fixative not specified (datasheet A14147-1)
FixationImage fixative and duration unreported (datasheet A14147-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ACOT9, 1:50-1:200 (datasheet A14147-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultACOT9-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression with granular, mitochondrial pattern in all tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval rule); the first published workflow also uses citrate pH 6.0 (PMC13374139).
Section 2

What Is the Expected ACOT9 Staining Pattern?

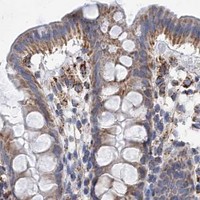
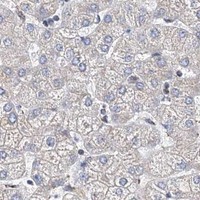
ACOT9 is annotated in the mitochondrial matrix and inner membrane, with no transmembrane segment (UniProt Q9Y305 topology). In paraffin-section IHC, expect granular cytoplasmic staining in cells such as lung macrophages, bronchial respiratory epithelial cells, and adrenal glandular cells (HPA: High in each). HPA describes a granular mitochondrial pattern across tissues, but rates tissue IHC reliability Supported, with medium agreement between antibody staining and RNA expression (HPA: tissue IHC).

What am I looking at on my slide?
Granular cytoplasmic stain in lung macrophages, with less signal in nearby cells.This fits the reported mitochondrial-looking tissue pattern and a High score for macrophages (HPA: tissue IHC; HPA: High in lung macrophages). Score the named cell population, not the whole lung section. Granularity supports the interpretation; bright cytoplasm alone does not establish mitochondrial identity by IHC.
Predominantly nuclear or smooth cell-border stain in a tissue section.That pattern differs from HPA's granular cytoplasmic tissue IHC profile (HPA: tissue IHC). Check controls, detection background, and whether the signal belongs to the intended cells before calling it ACOT9. HPA's separate ICC-IF record reports approved plasma-membrane, cytosol, and additional nucleoplasm localization, so compartment disagreement warrants investigation rather than an automatic artefact call (HPA: subcellular ICC-IF).
Strong stain in adipocytes, skeletal myocytes, or vaginal squamous epithelial cells.Those specific cell populations were Not detected in HPA tissue IHC (HPA: adipocytes; HPA: skeletal myocytes; HPA: vaginal squamous epithelial cells). Recheck cell identification and controls. Cross-reactivity or endogenous chromogen activity are possible explanations; a negative score for one cell type does not mean every cell in that tissue must be unstained.
Uniform haze covers cells and spaces between them.A widespread, nongranular deposit cannot be assigned confidently to the reported ACOT9 tissue pattern (HPA: tissue IHC). In general chromogenic IHC practice, incomplete blocking, residual detection activity, or excess reagent can produce background. Compare the primary-antibody omission control with the test section before scoring intensity.
No detectable stain in a section containing bronchial respiratory epithelial cells.HPA scores those cells High, making them a useful positive comparator (HPA: High in bronchial respiratory epithelial cells). Confirm that the expected cells are present and that the IHC-validated antibody and detection run worked. A failed run or sample-specific loss of signal remains possible; this record supplies no ACOT9-specific fixation-sensitivity evidence.
💡Expected ACOT9 appearanceCall a result positive when the appropriate cells show granular cytoplasmic signal—for example, High staining in lung macrophages or bronchial respiratory epithelium (HPA: tissue IHC)—while broad haze, isolated nuclear stain, or strong staining in HPA Not detected cell populations calls for control review (HPA: tissue IHC; HPA: adipocytes).
How each factor affects the staining
Subcellular interpretationUniProt places ACOT9 in the mitochondrial matrix and inner membrane and lists no transmembrane segment (UniProt Q9Y305 topology). HPA tissue IHC describes granular cytoplasm (HPA: tissue IHC). Neither source makes an individual chromogenic granule definitive proof of mitochondrial localization.
IHC evidence strengthThe HPA tissue profile is Supported with medium staining–RNA consistency, and antibody HPA035533 is IHC Supported (HPA: tissue IHC; HPA: antibodies). Treat a mismatched cell or compartment as a result to verify against controls, not as a resolved biological change.
Isoforms and antibody recognitionUniProt lists four ACOT9 isoforms and a processed chain spanning residues 22–439 (UniProt Q9Y305 isoforms; processing). No antibody epitope or isoform-specific IHC behavior is supplied, so these annotations cannot predict which isoform a section detects.
IF/ICC Q: Should its localization match tissue IHC?A: The HPA ICC-IF record lists approved plasma membrane and cytosol, with additional approved nucleoplasm localization, in imaged cell lines (HPA: subcellular ICC-IF). Interpret that separate assay on its own terms; this section gives no IF protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive cells are blank.The staining run may have failed, or the expected cell population may be absent from the examined area.Locate the cells on the counterstain and include a known High comparator, such as bronchial respiratory epithelium (HPA: High). Check the IHC-validated antibody, detection reagents, and run controls using general IHC practice; no ACOT9-specific fixation effect is documented here.
Chromogen appears in primary-antibody omission controls.Residual endogenous detection activity or background from the detection system may be contributing; this is a general chromogenic IHC concern.Review the omission control alongside the stained section. Apply the detection-system blocking steps appropriate to the chromogen and tissue, then reassess whether signal is restricted to plausible cells and granular cytoplasm (HPA: tissue IHC).
Signal is diffuse rather than granular.Nonspecific background or an overly strong detection signal may obscure the pattern; the source record does not identify a target-specific cause.Compare positive and omission controls, then optimize the catalog antibody and detection conditions within the validated IHC workflow. Score cell-associated granularity only after the background is controlled (HPA: granular cytoplasmic tissue pattern).
Strong signal is scored in an expected negative cell population.Cell misidentification, cross-reactivity, or endogenous detection activity may explain the mismatch.Identify the exact cells with the counterstain and review controls. Compare with HPA's Not detected adipocytes, skeletal myocytes, or vaginal squamous epithelial cells as applicable (HPA: tissue IHC); avoid calling an entire mixed tissue negative.
The section shows mainly nuclear or cell-edge staining.The tissue result conflicts with the granular cytoplasmic IHC profile, although HPA reports other compartments in ICC-IF (HPA: tissue IHC; HPA: subcellular ICC-IF).Check omission controls and cell identification, then repeat or corroborate the IHC finding if needed. Record the assay and compartment separately; the ICC-IF annotation alone does not validate a nuclear-dominant chromogenic tissue result.
Two sections show different staining intensity.Different proportions of scored cell types can change the apparent section-level result; HPA scores named populations within tissues (HPA: tissue IHC).Compare the same cell type at similar locations and report its intensity and granular distribution. Use HPA's High and Not detected cell populations as qualitative references (HPA: tissue IHC), while documenting the run controls before interpreting a biological difference.

Sample controls for ACOT9 IHC & IF

🧪Run adrenal gland first: glandular cells should stain strongly (HPA: High in adrenal gland glandular cells). Use vagina as the negative tissue (HPA: Not detected in vaginal squamous epithelial cells); on the adrenal slide, non-glandular cells without specific chromogen above background can serve as internal background comparators, but their ACOT9 status is unreported (HPA: adrenal gland row identifies glandular cells only).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ACOT9 in A-431, U-251MG, U2OS, with annotated localisation: Plasma membrane (approved), Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a host- and isotype-matched rabbit IgG control for the polyclonal primary (selected-SKU caption: pAb and goat anti-rabbit secondary; standard IHC practice). Use ACOT9 knockout material as a biological negative, or an immunizing-peptide block if that peptide is available (standard IHC practice). Check adrenal sections for endogenous peroxidase and, if using avidin–biotin detection, endogenous biotin before interpreting chromogen (standard IHC practice; selected-SKU caption: avidin–peroxidase detection).
⚠️Feasibility: An ACOT9-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative not stated). ACOT9-specific retrieval dependence is also unreported; optimize antigen retrieval for the chosen antibody, and do not assume frozen sections or IF will be easier (supplied target/application evidence; standard IHC practice). Interpret IF localization cautiously because the supplied records differ: UniProt places ACOT9 in mitochondria, while HPA ICC-IF reports mainly plasma membrane and cytosol staining (UniProt Q9Y305 subcellular location; HPA subcellular summary).

HPA tissue IHC evidence for ACOT9

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebellum Synaptic glomeruli - core High Protein (IHC) HPA →
Fallopian tube Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Vagina Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced ACOT9 IHC Tips

Troubleshooting ACOT9 chromogenic IHC in paraffin sections requires attention to retrieval, granular cytoplasmic staining, antibody controls, and cell-specific scoring.

How should I retrieve ACOT9 in paraffin sections when staining is weak?
Start with citrate pH 6.0 heat-induced epitope retrieval at 95–98 °C for 20 min (page retrieval setting). After cooling, compare a known positive compartment and a primary-antibody omission control on sections processed together; the selected product image shows cytoplasmic staining in paraffin-embedded human colon carcinoma at 1:50 (caption: A14147-1). If signal remains weak, test a different retrieval buffer on adjacent sections as a fallback while holding antibody concentration and detection constant (general IHC practice). Excessive retrieval can damage morphology or increase diffuse background, so judge improvement by preserved tissue architecture and a clearer granular cytoplasmic pattern (general IHC practice; HPA: tissue IHC profile).
Could fixation explain weak or uneven ACOT9 staining?
ACOT9-specific fixation sensitivity is unknown from the supplied evidence; the selected tissue caption identifies paraffin embedding but does not report a fixative (caption: A14147-1). Record fixative, fixation duration, section thickness, and processing history for each specimen before comparing stain intensity across cases (general IHC practice). If staining varies between regions, compare morphology, retrieval uniformity, and a same-run control section before attributing the difference to ACOT9 abundance (general IHC practice). Optimize fixation and retrieval on matched material when possible, since either inadequate preservation or epitope masking can change chromogenic staining independently of protein expression (general IHC practice).
What staining pattern should count as ACOT9-positive in tissue IHC?
Prioritize granular cytoplasmic staining in morphologically intact cells: HPA reports that pattern across tissues, and UniProt places ACOT9 in the mitochondrial matrix and inner membrane (HPA: tissue IHC profile; UniProt Q9Y305: subcellular location). The selected paraffin-section image reports cytoplasmic staining in human colon carcinoma, without resolving individual mitochondria (caption: A14147-1). HPA cell-based subcellular data additionally report plasma membrane, cytosol, and nucleoplasm locations, so compartment assignments should remain assay-specific rather than automatically transferred to chromogenic tissue sections (HPA: subcellular). Examine serial sections and appropriate controls before calling isolated nuclear or crisp surface staining specific ACOT9 signal (general IHC practice).
Can this IHC stain distinguish ACOT9 isoforms or processing states?
The supplied record lists 4 ACOT9 isoforms, but no antibody epitope or isoform-specific tissue validation is supplied (UniProt Q9Y305: isoforms; caption: A14147-1). ACOT9 has a processed chain spanning residues 22–439 and HotDog ACOT-type domains at 84–209 and 289–401; those annotations alone cannot show which forms this antibody recognizes in sections (UniProt Q9Y305: processing and domains). Its reported acetylation at residue 103 likewise does not establish a staining effect without mapped epitope evidence (UniProt Q9Y305: modified residues). For isoform claims, obtain epitope mapping and isoform-specific validation, then interpret the chromogenic stain only within what those controls establish (general IHC practice).
How can I check the ACOT9 pattern with multiplex IF?
Treat IF as a separate assay: the selected antibody evidence here is a paraffin-section chromogenic image, while HPA lists cell lines with ICC/IF images (caption: A14147-1; HPA: subcellular). Pair ACOT9 with a marker identifying the cell population being examined, such as a macrophage marker when evaluating lung macrophages, which HPA scores High (HPA: lung macrophages). Choose spectrally separated fluorophores after inspecting tissue autofluorescence and include single-stain controls for channel bleed-through (general IF practice). Because UniProt places ACOT9 at the mitochondrial matrix and inner membrane without a transmembrane segment, verify that fixation and permeabilisation permit access to the antibody’s mapped epitope; the epitope is not specified here (UniProt Q9Y305: location and topology; general IF practice).
How do I troubleshoot diffuse or granular background in ACOT9 IHC?
Run a primary-antibody omission section alongside the test section; the selected image used PBS in place of primary antibody as its negative control (caption: A14147-1). Block endogenous peroxidase before chromogenic development and assess nonspecific secondary-reagent binding with appropriate controls (general chromogenic IHC practice). If both test and control show staining, inspect detection chemistry, washing, tissue folds, and precipitate before changing the ACOT9 antibody concentration (general IHC practice). If only the test section is diffusely positive, titrate the primary antibody and reassess retrieval against an intact positive region; expected tissue staining is granular and cytoplasmic (general IHC practice; HPA: tissue IHC profile).
How should I quantify ACOT9 staining across tissue samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, because HPA reports High staining in lung macrophages but Not detected in adipocytes and skeletal myocytes (HPA: tissue IHC). For comparable sections, record the percentage of positive cells and staining intensity, then calculate an H-score from intensity-weighted percentages if graded scoring is reliable (general IHC practice). Alternatively, measure positive-cell density per mm² of viable tissue when cell abundance is the question (general IHC practice). Normalize to the counted target-cell population or viable tissue area, keep imaging and development settings consistent, and exclude folds, necrosis, and section edges from analysis (general IHC practice).
When is an apparent ACOT9-positive cell likely an artefact?
A convincing tissue signal should follow cell morphology and show granular cytoplasmic staining, the reported HPA tissue pattern for ACOT9 (HPA: tissue IHC profile). Review cell identity carefully: HPA scores lung macrophages High, while adipocytes and skeletal myocytes are Not detected in its tissue survey (HPA: tissue IHC). Isolated nuclear staining, edge-only colour, necrotic debris, or signal reproduced in the primary-antibody omission control needs investigation before being interpreted as ACOT9 expression (general IHC practice; caption: A14147-1 negative control). Check endogenous peroxidase activity and detection background, then compare intact regions and controls processed in the same run before making a biological claim (general chromogenic IHC practice).
Boster reagents

Best ACOT9 / Acyl-coenzyme A thioesterase 9, mitochondrial IHC Antibodies

A14147-1 has an IHC image from paraffin-embedded human colon carcinoma (image caption). Its listed reactivity covers human, mouse, and rat (catalog: reactivity); no IF image is supplied (catalog: IF images).

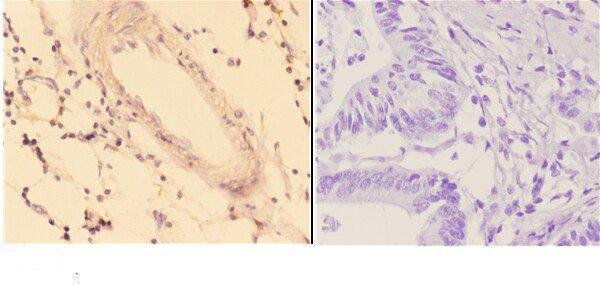
Real IHC data Immunohistochemistry (IHC) analyzes of ACOT9 pAb bin paraffin-embedded human colon carcinoma tissue at 1:50,showing cytoplasmic staining.Negative control (the right)Using PBS instead of primary antibody, secondary antibody is Goat Anti-Rabbit IgG-biotin followed by avidin-peroxidase.
Anti-ACOT9 Antibody
Cat # A14147-1

A14147-1 is listed for IHC in human, mouse, and rat samples (catalog: applications and reactivity). Its own image shows cytoplasmic staining in paraffin-embedded human colon carcinoma at 1:50, with a PBS primary-omission control (A14147-1 image caption).

Which to pick: Choose A14147-1 for paraffin-section tissue IHC based on its human colon carcinoma image (A14147-1 image caption). The caption does not report the fixative (A14147-1 image caption). No SKU is listed for IF/ICC (catalog: applications and IF images); A14147-1 is the cross-species IHC candidate because it is listed as rabbit polyclonal and reactive with human, mouse, and rat, although its IHC image documents only human tissue (catalog: host and reactivity; A14147-1 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9Y305 (ACOT9_HUMAN, Acyl-coenzyme A thioesterase 9, mitochondrial).
  2. Human Protein Atlas. ACOT9 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. ACOT9 subcellular location (ICC-IF): Mainly localized to the plasma membrane and cytosol. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. ACOT9 antibody validation summary (1 antibodies).
  5. ACOT9, a mitochondrial metabolism-related gene, promotes ROS-associated epithelial remodeling in laryngeal squamous cell carcinoma. Journal of translational medicine 2026 — PMC13374139.
  6. Establishment of prognostic prediction model based on lipid metabolism related genes in esophageal squamous cell carcinoma by machine learning algorithms. BMC gastroenterology 2026 — PMC13335382.
  7. Prognosis and pain dissection of novel signatures in kidney renal clear cell carcinoma based on fatty acid metabolism-related genes. Frontiers in oncology 2022 — PMC9780486.
  8. PubMed PMID:10810093 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:17974005 — UniProt-cited evidence.