ADCY6 / Adenylate cyclase type 6 · IHC design guide

Design Immunohistochemistry for ADCY6

Plan ADCY6 paraffin IHC around the cytoplasmic staining observed in most tissues (HPA tissue IHC). This guide covers fixation consistency and interpretation of an antibody directed at ADCY5/6 (datasheet: A05655-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ADCY6 (IHC for ADCY6): expected localisation Cytoplasmic in most tissues (HPA tissue IHC), antibody A05655-1, validated IHC image, and IHC protocol steps
Printable ADCY6 IHC protocol sheet — expected localisation Cytoplasmic in most tissues (HPA tissue IHC), antibody A05655-1, controls and protocol steps. Open the full ADCY6 IHC guide →

ADCY6 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic in most tissues (HPA tissue IHC)
Staining pattern Cytoplasmic signal; medium in glandular cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A05655-1)
Caveat ADCY5/6-directed antibody may also detect ADCY5 (datasheet: A05655-1)
Regulation Expression regulation is unreported (UniProt)
Isoform / epitope 2 isoforms; epitope differences unknown; membrane face matters (UniProt)
Section 1

Recommended ADCY6 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with one published ADCY6 IHC protocol for breast cancer samples (PMC9377375).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human brain tissue; fixative not specified (datasheet A05655-1)
FixationImage fixative and duration unreported (datasheet A05655-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ADCY6, 1:100-1:300 (datasheet A05655-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultADCY6-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page antigen-retrieval rule); the published protocol used 100 °C for 16 min (PMC9377375).
Section 2

What Is the Expected ADCY6 Staining Pattern?

ADCY6 is a 12-pass membrane protein associated with the cell membrane, cilia and stereocilia (UniProt O43306 topology and subcellular location). In tissue IHC, HPA reports cytoplasmic staining in most tissues, including medium staining in colon glandular cells and bronchial respiratory epithelial cells (HPA tissue IHC). Its IHC reliability is Approved, with low consistency between antibody staining and RNA expression (HPA tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic staining in colon glandular cells or bronchial respiratory epithelial cells.This resembles HPA's reported medium staining in those cells (HPA tissue IHC). Assess the cell type alongside the signal: the tissue result provides a useful comparison, while HPA reports low consistency between antibody staining and RNA expression (HPA tissue IHC reliability).
A cell-edge or projection-associated signal accompanies cytoplasmic staining.A membrane-associated component is biologically plausible because ADCY6 has 12 transmembrane segments and is assigned to the cell membrane, cilia and stereocilia (UniProt O43306 topology and subcellular location). HPA's tissue IHC summary nevertheless describes the observed pattern as cytoplasmic (HPA tissue IHC).
Strong nuclear staining dominates otherwise plausible positive cells.Nuclear localisation is absent from the supplied UniProt and HPA locations (UniProt O43306 subcellular location; HPA tissue IHC and ICC-IF). Treat a nuclear-only result as suspect and compare it with a no-primary control before assigning it to ADCY6 (standard IHC practice).
The strongest signal occurs in adipocytes or oral squamous epithelial cells.HPA reports ADCY6 as not detected in those respective cell types (HPA tissue IHC). Consider antibody cross-reactivity or endogenous chromogenic activity, and check controls; a discordant field alone cannot identify its cause (standard IHC practice; HPA tissue IHC reliability).
Broad, nearly uniform colour obscures cell boundaries and tissue structure.This is difficult to score against HPA's cell-specific observations (HPA tissue IHC). A no-primary control can reveal detection-system background; uneven washing or excessive detection development can also obscure localisation (standard IHC practice).
💡Expected ADCY6 appearanceA credible positive is cell-associated, predominantly cytoplasmic staining in HPA-reported positive cells, such as medium staining in colon glandular cells; strong nuclear-only or uniform tissue-wide colour is suspect (HPA tissue IHC; UniProt O43306 subcellular location; standard IHC practice).
How each factor affects the staining
Topology and compartmentADCY6 spans the membrane 12 times, with annotated cytoplasmic and extracellular regions (UniProt O43306 topology). The location of this antibody's epitope is not supplied, so topology cannot predict which staining conditions will expose it.
Tissue-pattern confidenceThe catalog antibody is IHC Approved, while HPA reports low agreement between antibody staining and RNA expression (HPA antibody CAB018365; HPA tissue IHC reliability). Use the listed cells and levels as comparisons, not as guaranteed results for every section.
Antigen retrievalFor paraffin IHC, follow the IHC-validated antibody's documented retrieval conditions when available, then compare positive tissue and controls (standard IHC practice). The supplied UniProt and HPA records do not establish an ADCY6-specific retrieval requirement or fixation sensitivity.
Chromogenic detectionEndogenous activity and nonspecific detection can produce colour without a matching primary-antibody signal; no-primary and detection controls help identify this contribution (standard IHC practice). The HPA tissue images alone do not establish its source in a new specimen.
IF/ICC Q: Should the IHC cytoplasmic pattern also appear in IF?A: HPA's ICC-IF summary assigns ADCY6 to the Golgi apparatus, whereas its tissue IHC summary says cytoplasmic expression in most tissues (HPA ICC-IF; HPA tissue IHC). Interpret each application against its own observations; CAB018365 is IHC Approved and ICC Uncertain (HPA antibody CAB018365).
Isoform interpretationUniProt lists 2 ADCY6 isoforms (UniProt O43306 isoforms). No antibody epitope or isoform-specific staining evidence is supplied, so an unusual tissue pattern cannot be assigned to an isoform from these records.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in colon glandular cells or bronchial respiratory epithelial cells.Those cells have medium HPA tissue IHC staining, but a new section may fail for a technical reason or differ from the reference (HPA tissue IHC; standard IHC practice).Confirm the expected cell type is present; check the documented antibody dilution, retrieval and detection steps, then compare a positive control in the same run (standard IHC practice).
Signal appears only in nuclei.This conflicts with the supplied membrane and cytoplasmic locations and with HPA's tissue IHC pattern (UniProt O43306 subcellular location; HPA tissue IHC).Review the no-primary control and nuclear counterstain, and assess whether cytoplasmic cell-associated signal remains when background is excluded (standard IHC practice).
Adipocytes or oral squamous cells stain more strongly than expected positive cells.HPA reports these cell types as not detected; cross-reactivity or detection background is possible, but the slide alone cannot distinguish them (HPA tissue IHC; standard IHC practice).Compare adjacent expected-positive cells and a no-primary control, then reassess antibody and detection conditions before calling the unexpected signal ADCY6 (standard IHC practice).
Diffuse colour masks gland boundaries or individual cells.Nonspecific detection, insufficient washing or overdevelopment may obscure a localised chromogenic result (standard IHC practice).Check no-primary and detection controls; review blocking, washes and development time, and score only where cell boundaries remain interpretable (standard IHC practice).
An IF/ICC image looks Golgi-associated while tissue IHC looks broadly cytoplasmic.Those are the respective HPA summaries; the catalog antibody has ICC Uncertain status, so the two views have different validation context (HPA ICC-IF; HPA tissue IHC; HPA antibody CAB018365).Assess the tissue slide against the HPA tissue IHC reference. Treat the IF/ICC image as application-specific context, rather than requiring an identical chromogenic pattern (HPA tissue IHC; HPA ICC-IF).
Different paraffin sections give inconsistent intensity.HPA rates tissue IHC Approved but notes low consistency with RNA expression; the supplied sources do not identify an ADCY6-specific fixation effect (HPA tissue IHC reliability).Compare matched cell types and same-run controls; record retrieval, antibody dilution and detection conditions before interpreting intensity differences biologically (standard IHC practice).

Sample controls for ADCY6 IHC & IF

🧪Run bone marrow first: hematopoietic cells should stain at the HPA Medium level (HPA: bone marrow, hematopoietic cells). Use adipose tissue as the negative tissue; adipocytes are Not detected (HPA: adipose tissue, adipocytes). On the positive slide, neighboring nonhematopoietic cells can serve as a background reference, but these HPA rows do not establish them as ADCY6-negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ADCY6 in A-431, U-251MG, U2OS, with annotated localisation: Golgi apparatus (approved) (HPA subcellular).
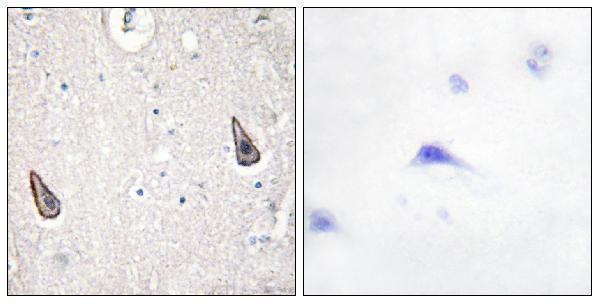
Technical controls: Include no-primary (secondary-only) and host- and clonality-matched isotype controls; use ADCY6 knockout material as a biological negative if available (standard IHC practice). The caption shows peptide blocking with an antibody labeled ADCY5/6, so that result demonstrates competition but does not establish ADCY6-specific staining (selected-SKU tissue-IHC caption). Quench endogenous peroxidase in bone marrow and check the no-primary slide for residual chromogenic signal (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and retrieval effect are unreported in the supplied evidence; optimize antigen retrieval empirically for the catalog antibody (supplied HPA/UniProt record and selected-SKU tissue-IHC caption; standard IHC practice). The paraffin-section caption does not report a fixative, so it does not establish fixation; the evidence also does not show that frozen sections or IF would be easier (selected-SKU tissue-IHC caption; supplied HPA ICC-IF record). Endogenous peroxidase in bone marrow myeloid cells can complicate chromogenic scoring (standard IHC practice). The selected A05655-1 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image A05655-1).

HPA tissue IHC evidence for ADCY6

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Cerebral cortex Endothelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Section 3

Advanced ADCY6 IHC Tips

Troubleshoot ADCY6 staining in paraffin section chromogenic IHC, with one entry on adapting the assay to IF/ICC.

How should I retrieve ADCY6 in paraffin sections when staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page IHC retrieval setting). If staining remains weak, compare a longer incubation in the same buffer on serial sections, checking whether tissue morphology and background deteriorate (general IHC practice). Run a known positive cell population alongside the test section, such as bronchial respiratory epithelial cells, and compare signal at the same antibody concentration (HPA: Medium in bronchial respiratory epithelial cells). Because ADCY6 spans the membrane 12 times, retrieval may expose different epitopes unevenly; optimise against the antibody’s stated immunogen when available (UniProt O43306 topology; general IHC practice).
Could fixation explain absent ADCY6 staining in my paraffin sections?
Target-specific ADCY6 sensitivity to fixation is unknown from the supplied evidence; the selected product caption identifies paraffin-embedded human brain tissue but does not state its fixative (A05655-1 caption). Record fixative, fixation duration and section age, then compare sections processed under documented conditions while holding retrieval and detection constant (general IHC practice). Include an internal tissue control and a no-primary control to distinguish lost antigen signal from chromogenic background (general IHC practice). Avoid assigning weak staining to fixation alone: antibody concentration, retrieval and detection can also change signal, and the available caption does not resolve those variables (A05655-1 caption; general IHC practice).
Should ADCY6 staining appear on membranes, in cytoplasm or near the Golgi?
Assess membrane-associated staining in the relevant cell population because ADCY6 is annotated at the cell membrane, cilium and stereocilium (UniProt O43306 subcellular annotation). Cytoplasmic signal can also be plausible in tissue sections: HPA describes cytoplasmic expression in most tissues, while its ICC/IF localisation is approved at the Golgi apparatus (HPA tissue IHC profile; HPA subcellular). Compare the staining pattern with matched morphology and a no-primary control before accepting diffuse cytoplasmic colour as specific (general IHC practice). Record membrane, perinuclear and diffuse cytoplasmic signal separately; a chromogenic section cannot by itself establish colocalisation with a subcellular organelle (general IHC practice).
Can this antibody distinguish ADCY6 isoforms or separate ADCY6 from ADCY5?
Check the immunogen and antibody specificity before assigning staining to an ADCY6 isoform: the record lists 2 isoforms, without supplying their distinguishing epitopes (UniProt O43306 isoforms). The selected image caption calls its reagent an ADCY5/6 antibody, so peptide blocking in that image supports peptide-dependent staining but does not establish ADCY6-only recognition (A05655-1 caption). Map any disclosed epitope against the annotated cytoplasmic and extracellular regions before choosing permeabilisation or interpreting a negative result (UniProt O43306 topology; general IHC practice). If isoform or ADCY5 discrimination matters, use independently validated specificity controls and report the unresolved identity of shared staining (general IHC practice).
How should I adapt the ADCY6 assay for multiplex IF?
Pair ADCY6 with a marker for the expected cell population, such as a respiratory epithelial marker in bronchus, and assess overlap at the cell level (HPA: Medium in bronchial respiratory epithelial cells; general IF practice). Choose spectrally separated fluorophores and place the weaker target signal in a channel with low tissue autofluorescence, after inspecting unstained tissue (general IF practice). For an intracellular epitope, test gentle detergent permeabilisation; for an extracellular epitope, first assess staining without permeabilisation, using the antibody’s disclosed immunogen to decide (UniProt O43306 topology; general IF practice). Include single-stain and no-primary controls, and treat the selected paraffin-section chromogenic image as IHC evidence rather than IF validation (A05655-1 caption; general IF practice).
What should I change when ADCY6 DAB staining is widespread?
Compare the section with a no-primary control and inspect pigment, tissue edges and damaged areas before changing the antibody concentration (general IHC practice). For a peroxidase-based DAB workflow, apply an endogenous peroxidase block and evaluate whether colour persists where the primary antibody is omitted (general IHC practice). Titrate the primary antibody and detection reagent on serial sections, keeping retrieval at citrate pH 6.0 initially so that the source of background remains identifiable (page IHC retrieval setting; general IHC practice). Widespread signal needs particular scrutiny because HPA reports cytoplasmic staining in most tissues but low consistency with RNA expression (HPA tissue IHC profile; HPA reliability description).
How can I quantify ADCY6 staining without mistaking tissue composition for expression? ⚠ ANSWER MARKED FOR VERIFICATION
Define the eligible cell population and compartment before scoring, then record staining intensity and the percentage of positive cells for an H-score (general IHC practice). Alternatively, count positive cells per mm² of viable tissue or report positive area relative to the annotated cell area, using the same rule across specimens (general IHC practice). Normalise to the number or area of eligible cells, excluding necrosis, folds and tissue loss rather than using whole-section area indiscriminately (general IHC practice). Report membrane-associated and cytoplasmic scores separately when both occur, and retain matched staining conditions because ADCY6 has membrane annotations while HPA describes cytoplasmic tissue staining (UniProt O43306 subcellular annotation; HPA tissue IHC profile).
How do I distinguish convincing ADCY6 staining from chromogenic artefact?
Prioritise staining within intact, identifiable cells and assess its compartment against ADCY6’s membrane and cell-projection annotation and HPA’s cytoplasmic tissue profile (UniProt O43306 subcellular annotation; HPA tissue IHC profile). Compare expected populations, such as bronchial respiratory epithelial cells with medium HPA staining, against squamous epithelial cells of oral mucosa reported as not detected (HPA tissue IHC). Discount colour confined to section edges, necrotic regions or a no-primary control, and investigate endogenous peroxidase signal in DAB assays (general IHC practice). Interpret a positive result cautiously because HPA rates the tissue antibody Approved while reporting low consistency between staining and RNA expression (HPA reliability description).
Boster reagents

Best ADCY6 / Adenylate cyclase type 6 IHC Antibodies

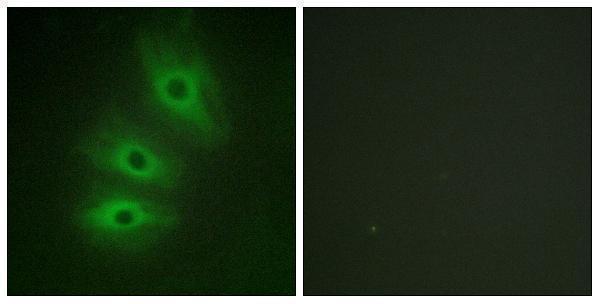
The catalog lists one IHC/IF antibody, A05655-1, with images from paraffin-embedded human brain tissue and HeLa cells; its listed reactivity covers human, mouse and rat (catalog applications, image captions and reactivity).

Real IHC data Immunohistochemistry analysis of paraffin-embedded human brain tissue, using ADCY5/6 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-A Cyclase V/VI ADCY6 Antibody
Cat # A05655-1

A05655-1 has an IHC image from paraffin-embedded human brain tissue with a peptide-blocked comparison (catalog IHC image caption). The same SKU has an IF image from HeLa cells with a peptide-blocked comparison; human, mouse and rat are listed as reactive species (catalog IF image caption and reactivity).

Which to pick: For tissue IHC, choose A05655-1 on the strength of its paraffin-embedded human brain image; the caption does not report the fixative (catalog IHC image caption). For IF/ICC, A05655-1 has an IF image from HeLa cells, while ICC validation is unreported (catalog IF image caption and applications). For mouse or rat work, A05655-1 is a rabbit polyclonal with IHC and IF listed and both species in its reactivity list; the supplied images show human samples only (catalog host, dilution record, applications, reactivity and image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O43306 (ADCY6_HUMAN, Adenylate cyclase type 6).
  2. Human Protein Atlas. ADCY6 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. ADCY6 subcellular location (ICC-IF): Localized to the Golgi apparatus..
  4. Human Protein Atlas. ADCY6 antibody validation summary (1 antibodies).
  5. ADCY6 is a potential prognostic biomarker and suppresses OTSCC progression via Hippo signaling pathway. The Kaohsiung journal of medical sciences 2023 — PMC11895994.
  6. MiR-27a-3p binds to TET1 mediated DNA demethylation of ADCY6 regulates breast cancer progression via epithelial-mesenchymal transition. Frontiers in oncology 2022 — PMC9377375.
  7. Decreased microRNA-182-5p helps alendronate promote osteoblast proliferation and differentiation in osteoporosis via the Rap1/MAPK pathway. Bioscience reports 2018 — PMC6435538.
  8. PubMed PMID:10978539 — UniProt-cited evidence.
  9. PubMed PMID:9455477 — UniProt-cited evidence.
  10. PubMed PMID:12168954 — UniProt-cited evidence.