This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan ADPGK paraffin IHC around the observed cytoplasmic tissue pattern (HPA tissue IHC). Colon glandular cells and lung macrophages provide high-staining references (HPA tissue IHC); start the catalog antibody at 1:100–1:300 (datasheet A10813-1).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Widespread cytoplasmic staining across cell types (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A10813-1) | |
| Positive control | Colon+4 more · see all | |
| Negative control | Bone marrow+4 more · see all |
| Fixation | Keep fixation consistent across samples (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A10813-1) | |
| Caveat | Secreted annotation may complicate cytoplasmic scoring (UniProt) | |
| Regulation | Specific staining regulators are unreported (UniProt) | |
| Isoform / epitope | 6 isoforms; signal peptide 1–22 is removed; epitope unknown (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet A10813-1) with four published ADPGK IHC protocols (PMC11974013; PMC13266032; PMC7532211; PMC10714548).
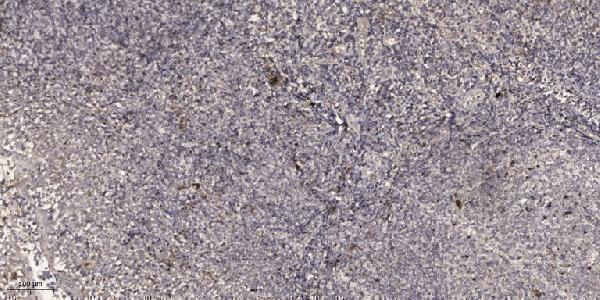
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet A10813-1) |
| Fixation | Image fixative and duration unreported (datasheet A10813-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A10813-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ADPGK, 1:100-1:300 (datasheet A10813-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ADPGK-positive staining in glandular cells of colon (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control. |
For paraffin-section IHC, expect predominantly cytoplasmic ADPGK staining across many cell types, with high staining in colon, rectum and small-intestinal glandular cells and lung macrophages (HPA: ubiquitous cytoplasmic expression; High in these cells). HPA rates its tissue IHC evidence Approved, with medium consistency against RNA expression (HPA: reliability summary). UniProt annotates ADPGK as secreted with no transmembrane segment, so interpret the observed cytoplasmic pattern in that context (UniProt Q9BRR6: subcellular location and topology).
| Cytoplasmic chromogen in glandular cells of colon, rectum or small intestine, or in lung macrophages. | These are useful positive-pattern checks: HPA reports High staining in each named cell population and describes the overall tissue profile as ubiquitous cytoplasmic expression (HPA: tissue IHC). Assess the named cells, since an impression of staining across the whole section does not establish which cell population is positive (standard IHC practice). |
| Predominantly nuclear or membrane-restricted signal, with little cytoplasmic staining in an expected positive cell population. | That compartment pattern diverges from the reported tissue IHC profile (HPA: ubiquitous cytoplasmic expression). UniProt reports no transmembrane segment but annotates the protein as secreted (UniProt Q9BRR6: topology; subcellular location). Treat the discrepancy as a reason to check staining specificity and slide controls, not as proof of a new ADPGK location (standard IHC practice). |
| Strong stain in bronchial respiratory epithelium, esophageal or oral squamous epithelium, or smooth muscle cells. | HPA lists ADPGK as Not detected in those specific cell populations (HPA: tissue IHC). Check whether the color follows the intended cellular compartment and persists with appropriate detection controls; antibody cross-reactivity or endogenous detection activity can mimic a positive result (standard IHC practice). A negative HPA entry does not make every cell in that tissue negative. |
| Widespread haze or chromogen over cells and surrounding tissue, obscuring cellular borders. | Diffuse background cannot establish ADPGK localization or a High-versus-Medium cellular pattern (standard IHC practice; HPA: tissue IHC levels). Inspect the no-primary control, blocking and wash performance, and compare a known positive cell population on the same run before assigning biological meaning (standard IHC practice). |
| No discernible cytoplasmic staining in the named cells of a colon, rectum or small-intestinal section. | That result conflicts with HPA's High glandular-cell staining in those tissues (HPA: tissue IHC). It warrants a run-level check of positive control, retrieval and detection before being interpreted as absence of ADPGK (standard IHC practice). HPA's Approved rating has medium RNA–staining consistency, so one image profile is a reference rather than an absolute cutoff (HPA: reliability summary). |
| Which observations anchor the tissue comparison? | HPA reports High staining in the named intestinal glandular cells and lung macrophages, Medium staining in several other glandular populations, and Low or Not detected staining in specified cells elsewhere (HPA: tissue IHC). Compare cell type as well as tissue name. |
| How strong is the IHC pattern evidence? | The tissue profile is Approved but has medium consistency between antibody staining and RNA expression; the listed IHC antibody HPA045194 is Approved, while HPA058525 is listed for ICC rather than IHC (HPA: reliability summary; antibody validation). |
| Does protein processing predict a different slide compartment? | UniProt annotates a signal peptide at residues 1–22, a chain at 23–497, secretion and no transmembrane segment (UniProt Q9BRR6: processing; topology; location). These annotations do not replace the cytoplasmic tissue IHC observation (HPA: tissue IHC). |
| Do isoforms explain a discrepant stain? | UniProt lists 6 isoforms (UniProt Q9BRR6: isoforms). The supplied record gives no antibody epitope or isoform-specific IHC pattern, so an unexpected positive or negative result cannot be assigned to a particular isoform from these sources. |
| What should an IF/ICC result look like? | On its separate guide page, compare IF/ICC images with the approved centrosome localization shown in SiHa, U-251MG and U2OS cells (HPA: subcellular ICC-IF). That ICC-IF observation answers the localization question; it does not redefine the cytoplasmic paraffin-section IHC reference (HPA: tissue IHC). |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive glandular cells are blank. | The result disagrees with HPA's High colon, rectum and small-intestinal glandular-cell staining; the supplied sources do not identify a target-specific fixation sensitivity (HPA: tissue IHC). | Verify the section contains the named cells and that a positive control stains; then check the established retrieval, primary-antibody dilution and detection steps for this IHC run (standard IHC practice). |
| Nuclei dominate while cytoplasm is weak. | Nuclear-dominant staining differs from the reported ubiquitous cytoplasmic IHC pattern (HPA: tissue IHC). The pattern alone cannot identify whether the cause is nonspecific binding or a preparation issue (standard IHC practice). | Compare the no-primary control and a known positive tissue, inspect localization at cellular resolution, and confirm that the IHC-validated antibody was used (standard IHC practice; HPA: HPA045194 IHC Approved). |
| Bronchial respiratory epithelium or smooth muscle appears strongly positive. | Those named cell populations are listed as Not detected, so strong staining requires a specificity check (HPA: tissue IHC). Endogenous detection activity and antibody cross-reactivity are possible explanations (standard IHC practice). | Review the no-primary and detection controls, then compare with a High positive population processed in the same run; score each cell type separately (standard IHC practice; HPA: tissue IHC). |
| Brown color is diffuse across the section. | Broad noncellular deposit prevents reliable assignment of the cytoplasmic pattern reported by HPA (HPA: tissue IHC; standard IHC practice). Inadequate blocking, washing or detection control can contribute to background (standard IHC practice). | Inspect the no-primary control and reagent background; repeat the established blocking and wash steps and assess the signal only where cell boundaries are clear (standard IHC practice). |
| A purported negative tissue contains scattered positive cells. | HPA's Not detected entries refer to specified populations, such as bone-marrow hematopoietic cells or bronchial respiratory epithelial cells, rather than every cell in a section (HPA: tissue IHC). | Identify the stained cell population before scoring, compare its compartment with HPA's cytoplasmic IHC profile, and use controls to evaluate unexpected staining (HPA: tissue IHC; standard IHC practice). |
| The IHC result is used to assess an IF/ICC image. | HPA reports cytoplasmic tissue IHC and approved centrosome localization by ICC-IF; these are distinct assay observations (HPA: tissue IHC; subcellular ICC-IF). | Evaluate paraffin-section IHC against the named tissue cell populations, and evaluate IF/ICC localization against the separate HPA centrosome observation (HPA: tissue IHC; subcellular ICC-IF). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Lung | Macrophages | High | Protein (IHC) | HPA → |
| Rectum | Glandular cells | High | Protein (IHC) | HPA → |
| Small intestine | Glandular cells | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot ADPGK staining in paraffin sections by checking retrieval, cell identity and compartment before comparing chromogenic signal across samples.
A10813-1 has a human tonsil paraffin-section IHC image (catalog image caption); IF is listed without a figure, and human, mouse, and rat reactivity is listed (catalog applications/reactivity).
A10813-1 is listed for IHC and IF in human, mouse, and rat (catalog applications/reactivity). Its IHC image shows paraffin-embedded human tonsil at 1:200 primary dilution with Tris-EDTA pH 9.0 retrieval; no IF image is supplied (A10813-1 image captions).
Which to pick: For tissue IHC, choose A10813-1: its own caption documents paraffin-embedded human tonsil, but does not report the fixative (A10813-1 IHC image caption). For IF, A10813-1 lists a 1:200–1:1000 range; ICC is unlisted and no IF figure is supplied (catalog applications/dilutions/image captions). For cross-species work, A10813-1 lists human, mouse, and rat reactivity; it has a rabbit host and no specified clone, while its tissue image documents human tonsil only (catalog reactivity/host/clone; A10813-1 IHC image caption).