AFAP1 / Actin filament-associated protein 1 · IHC design guide

Design Immunohistochemistry for AFAP1

Plan AFAP1 staining in paraffin sections using the catalog antibody’s 2–5 μg/ml IHC range (datasheet: A05258-3). Compare granular cytoplasmic staining across cell types, using appendix endocrine cells and gallbladder glandular cells as high-staining references (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for AFAP1 (IHC for AFAP1): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A05258-3, validated IHC image, and IHC protocol steps
Printable AFAP1 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A05258-3, controls and protocol steps. Open the full AFAP1 IHC guide →

AFAP1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Granular cytoplasmic staining in several tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A05258-3)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining varies by cell type, even within epithelia (HPA tissue IHC)
Regulation Overexpressed in prostate carcinoma (UniProt)
Isoform / epitope Two isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended AFAP1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A05258-3) with one published AFAP1 IHC protocol in human tissues (PMC3085893).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet A05258-3)
FixationImage fixative and duration unreported (datasheet A05258-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A05258-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05258-3)
Primary antibodyRabbit anti-AFAP1, 2-5μg/ml (datasheet A05258-3)
Primary incubationOvernight at 4 °C (datasheet A05258-3)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A05258-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultAFAP1-positive staining in endocrine cells of appendix (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression which a granular pattern in several tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A05258-3); the published F1 protocol used citrate pH 6.00 (PMC3085893).
Section 2

What Is the Expected AFAP1 Staining Pattern?

AFAP1 is a cytoplasmic, actin-associated protein with no transmembrane segment (UniProt Q8N556 topology and subcellular location). In paraffin-section IHC, expect cytoplasmic staining, sometimes granular, across several tissues (HPA tissue IHC). Appendix endocrine cells and gallbladder glandular cells are useful high-staining examples (HPA tissue IHC). HPA rates its tissue IHC evidence Enhanced, while reporting medium consistency between staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Clear cytoplasmic staining in appendix endocrine cells or gallbladder glandular cells, with little nuclear color.This matches the reported high staining in those cell populations (HPA tissue IHC) and AFAP1’s cytoplasmic, cytoskeletal location (UniProt Q8N556). A granular cytoplasmic appearance is compatible with the tissue profile (HPA tissue IHC).
Predominantly nuclear staining, or a crisp outline confined to the cell surface.These compartments do not match the expected cytoplasmic IHC pattern (HPA tissue IHC; UniProt Q8N556 subcellular location and topology). Check the matched negative control and the antibody’s IHC validation before assigning the color to AFAP1 (general IHC practice).
Strong color chiefly in cells expected to stain weakly, such as skeletal muscle myocytes.HPA reports low staining in skeletal muscle myocytes (HPA tissue IHC). Unexpected strong color can reflect cross-reactivity or endogenous detection activity; inspect cell morphology and controls before calling it AFAP1 (general IHC practice).
Similar diffuse color across tissue, stroma, and spaces between cells.A uniform haze obscures the cell-specific cytoplasmic pattern reported by HPA (HPA tissue IHC). Compare a section processed without primary antibody and review blocking, washing, and chromogen development (general IHC practice).
No staining in identifiable appendix endocrine cells or gallbladder glandular cells.Those populations are reported as high staining (HPA tissue IHC), so a blank result calls for a run-level check. Verify the positive-control tissue, antibody preparation, retrieval, and detection steps; no AFAP1-specific retrieval condition is supplied here (general IHC practice).
💡Expected AFAP1 appearanceCall the IHC result positive when cell-associated cytoplasmic color, potentially granular, is clear in appendix endocrine cells or gallbladder glandular cells, both reported High (HPA tissue IHC); predominantly nuclear color or uniform background is inconsistent with that pattern (HPA tissue IHC; UniProt Q8N556 subcellular location).
How each factor affects the staining
Tissue and cell populationAppendix endocrine and gallbladder glandular cells are High; adipocytes in adipose tissue and breast are Medium (HPA tissue IHC). Compare like cell populations when judging intensity, because whole-section color can conceal that distribution (general IHC practice).
Cytoplasmic architectureAFAP1 associates with the actin cytoskeleton and stress fibers (UniProt Q8N556); HPA describes granular cytoplasmic tissue staining (HPA tissue IHC). Fine filament detail may be difficult to resolve in chromogenic paraffin-section IHC (general IHC practice).
Strength of tissue evidenceHPA assigns Enhanced IHC reliability but describes only medium consistency between antibody staining and RNA expression (HPA tissue IHC). Use the reported pattern as a reference, and interpret unexpected staining with controls and morphology (general IHC practice).
AFAP1 processing and isoformsUniProt lists two isoforms and a full-length 1–730 chain without a signal peptide, propeptide, or transmembrane segment (UniProt Q8N556). The supplied record gives no antibody epitope, so it cannot establish which isoforms a particular IHC antibody detects.
Retrieval and fixation evidenceTarget-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive-control section is blank.The run may have failed at an antibody, retrieval, or detection step (general IHC practice).Use appendix endocrine cells or gallbladder glandular cells as reported High populations (HPA tissue IHC); confirm their presence, then check reagent preparation and each detection step (general IHC practice).
Only nuclei are strongly colored.Nuclear-dominant color conflicts with AFAP1’s cytoplasmic location (UniProt Q8N556) and the HPA tissue pattern (HPA tissue IHC).Review section morphology and the no-primary control; repeat with an IHC-validated antibody and appropriate controls if the discrepancy persists (general IHC practice).
Color appears broadly in low-staining cell populations.HPA reports low staining in thyroid glandular cells, bronchial respiratory epithelium, and skeletal muscle myocytes (HPA tissue IHC). Strong color there warrants a specificity or detection-background check (general IHC practice).Compare the same cell populations across sections and inspect the no-primary control for endogenous detection activity (general IHC practice).
Granular signal is hard to separate from diffuse background.Granular cytoplasmic staining is reported for AFAP1 (HPA tissue IHC), while widespread haze can arise during chromogenic detection (general IHC practice).Check whether color remains inside identifiable cells; review blocking, washes, and chromogen development alongside a no-primary control (general IHC practice).
One tissue stains less intensely than the positive control.AFAP1 staining differs by cell population: HPA reports both High and Medium examples and several Low examples (HPA tissue IHC).Score the named cell type and compartment before interpreting the difference; do not use the overall darkness of a section as the sole readout (general IHC practice).
What pattern should I expect if checking the result by IF/ICC?HPA places AFAP1 mainly on actin filaments, with additional focal adhesion localization and uncertain cytosolic localization (HPA subcellular ICC-IF).Use filament-associated signal as the main localization reference; treat cytosolic signal cautiously because HPA marks it uncertain (HPA subcellular ICC-IF).

Sample controls for AFAP1 IHC & IF

🧪Run appendix first and score its endocrine cells, which HPA rates High for AFAP1 (HPA: High in appendix endocrine cells). HPA detects AFAP1 in all 45 scored tissues, so no tissue is a validated negative; use the no-primary and isotype controls for background, and treat any unstained cells on the appendix slide as an internal background reference rather than a confirmed AFAP1-negative population (HPA: no negative tissue rows; standard IHC practice).
Positive control tissue: Appendix (Endocrine cells, HPA High)
Negative control tissue: None in HPA: AFAP1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show AFAP1 in A-431, U-251MG, U2OS, with annotated localisation: Actin filaments (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section; a rabbit IgG isotype control matched to the primary antibody’s clonality and concentration; and an AFAP1 knockout sample as a biological specificity control (caption: rabbit primary antibody; standard IHC practice). Block endogenous peroxidase and assess endogenous biotin background in appendix before interpreting DAB signal, because the reported detection uses a biotinylated secondary and streptavidin–biotin complex (caption: biotinylated secondary, SABC and DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A05258-3 paraffin-section caption does not state the fixative (caption: fixative unreported). That caption uses heat retrieval in EDTA at pH 8.0, but it does not establish whether retrieval is required; frozen-section performance is unreported (caption: EDTA retrieval; supplied evidence: no frozen-section comparison). IF offers an established way to assess the expected actin-filament pattern in the listed ICC-IF cell lines, although the evidence does not show that IF is easier than tissue IHC; in appendix IHC, endogenous peroxidase may create DAB background (HPA: actin filaments supported; HPA: ICC-IF images in A-431, U-251MG and U2OS; standard IHC practice).

HPA tissue IHC evidence for AFAP1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Endocrine cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: AFAP1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced AFAP1 IHC Tips

Troubleshoot AFAP1 staining in paraffin sections by checking retrieval, cell compartment, detection background and scoring against the documented tissue pattern.

Which retrieval conditions should I start with for AFAP1 paraffin sections?
Start with heat mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A05258-3). This is the condition documented for the catalog antibody’s human lung cancer tissue image; its caption gives no heating time or temperature, so establish those with the laboratory’s retrieval equipment (datasheet A05258-3; standard IHC practice). If staining is weak, vary heating duration on adjacent sections while keeping the buffer fixed, and compare signal with tissue preservation and background (standard IHC practice). Score cytoplasmic staining in intact cells rather than treating stronger staining at damaged section edges as successful retrieval (UniProt Q8N556 subcellular location; standard IHC practice).
How should I troubleshoot fixation when AFAP1 staining is weak or uneven?
The catalog image documents a paraffin section but does not state its fixative, so AFAP1 specific sensitivity to fixation remains unknown (datasheet A05258-3). Record the fixative and fixation duration for each specimen, then compare sections processed under documented conditions with the same retrieval and staining run (standard IHC practice). Uneven staining across a section warrants inspection of tissue preservation and processing before changing antibody concentration, because these can affect antigen access (standard IHC practice). Do not attribute a weak result to AFAP1 phosphorylation or its cytoskeletal location without a controlled fixation comparison (UniProt Q8N556 modified residues and subcellular location; standard IHC practice).
Where should convincing AFAP1 signal appear in an IHC section?
Expect cellular signal predominantly in the cytoplasm: AFAP1 is associated with cytoskeleton and stress fibers, while tissue IHC reports a ubiquitous granular cytoplasmic pattern (UniProt Q8N556 subcellular location; HPA tissue IHC). Use cell boundaries and a counterstain to distinguish cytoplasmic granules from pigment, debris or staining outside intact cells (standard IHC practice). Actin filaments are the supported main location in cellular imaging, with focal adhesion sites also reported; routine chromogenic sections may not resolve those structures individually (HPA subcellular; standard microscopy practice). A predominantly nuclear or extracellular pattern warrants comparison with an appropriate control and review of background before assigning it to AFAP1 (UniProt Q8N556 topology and subcellular location; standard IHC practice).
Can this IHC stain distinguish AFAP1 isoforms or phosphorylation states?
AFAP1 has 2 listed isoforms and several modified residues, including phosphoserines at positions 282, 283, 548 and 664 (UniProt Q8N556 isoforms and modified residues). The supplied catalog caption does not identify the antibody’s epitope or establish isoform or phosphosite selectivity (datasheet A05258-3). Treat a positive chromogenic stain as AFAP1 immunoreactivity under the tested conditions, without assigning it to a particular isoform or phosphorylation state (datasheet A05258-3; standard IHC interpretation). For that distinction, obtain epitope mapping and validation with suitable isoform or phosphosite controls before interpreting differences between specimens (standard antibody validation practice).
How can IF help investigate an ambiguous AFAP1 IHC pattern?
Use IF/ICC as a follow up to ambiguous chromogenic staining, since cellular imaging places AFAP1 mainly on actin filaments and also reports focal adhesion sites (HPA subcellular). Multiplex AFAP1 with a marker for the expected cell type in the specimen, and evaluate whether signal lies within those cells rather than relying on overlap with tissue autofluorescence (standard IF practice). Select spectrally separated fluorophores after checking unstained tissue, and favor a channel with low native fluorescence for the weaker target (standard IF practice). AFAP1 lacks a transmembrane segment and is intracellular, so permeabilise fixed cells sufficiently to expose its epitope while preserving cytoskeletal structure (UniProt Q8N556 topology and subcellular location; standard IF practice).
What should I check when AFAP1 DAB staining is diffuse?
First compare the primary antibody section with a matched section lacking primary antibody to identify detection system and tissue background (standard IHC practice). The documented workflow uses 10% goat serum blocking, 2 µg/ml primary antibody overnight at 4°C, a biotinylated secondary, and SABC with DAB (datasheet A05258-3). If background persists, check peroxidase blocking, wash stringency and the biotin based detection system before increasing primary dilution in a controlled series (standard chromogenic IHC practice). True AFAP1 staining should remain associated with intact cellular cytoplasm, whereas widespread extracellular deposit or uniform staining in the no primary control indicates background (UniProt Q8N556 subcellular location; standard IHC practice).
How should I quantify AFAP1 staining across tissue regions? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, because the tissue IHC profile varies by cell type despite low overall RNA tissue specificity (HPA tissue IHC). For chromogenic sections, record the percentage of positive cells and staining intensity, or use an H-score calculated from intensity categories and their cell percentages (standard IHC scoring practice). Normalize counts or positive area to viable cells or viable tissue area, and apply one threshold and imaging setup across compared sections (standard quantitative IHC practice). Report stromal and epithelial compartments separately when both are present, and exclude folds, necrosis and section edges from the denominator (standard quantitative IHC practice).
How can I separate true AFAP1 staining from artefact?
Give greatest weight to staining within intact cytoplasm, consistent with AFAP1’s cytoskeletal location and the reported granular cytoplasmic tissue pattern (UniProt Q8N556 subcellular location; HPA tissue IHC). Check that the stained cells match the annotated tissue compartment: the HPA reports high signal in appendix endocrine cells and gallbladder glandular cells, but low signal in bronchus respiratory epithelial cells (HPA tissue IHC). Discount signal confined to cut edges, necrotic areas or extracellular deposits, and compare a no primary control for endogenous enzyme or detection background (standard IHC practice). Interpret discrepancies cautiously because the HPA tissue stain has Enhanced reliability with medium consistency between staining and RNA data (HPA tissue IHC).
Boster reagents

Best AFAP1 / Actin filament-associated protein 1 IHC Antibodies

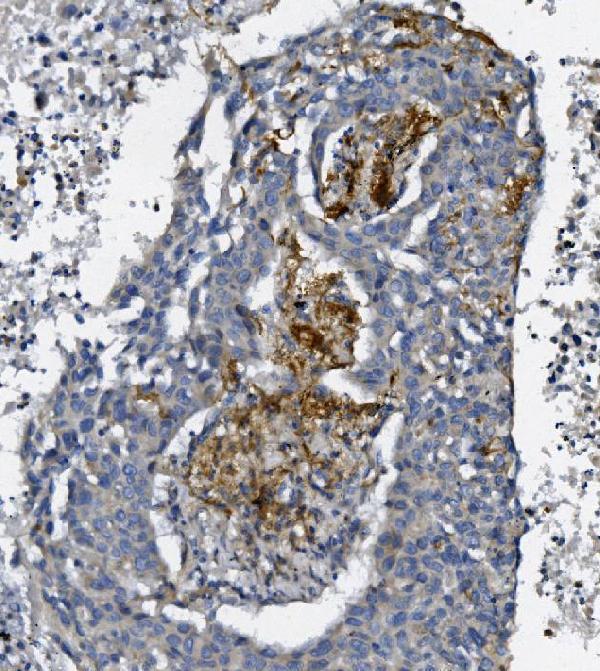
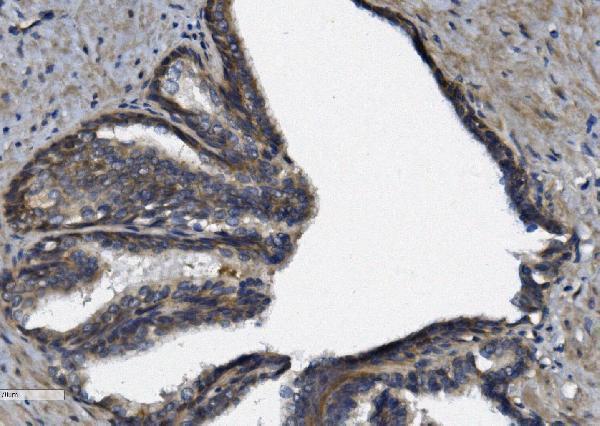
A05258-3 has IHC images from paraffin sections of human lung and prostatic cancer tissue (catalog image captions). No IF/ICC data are supplied (catalog applications; catalog image captions).

Real IHC data IHC analysis of AFAP/AFAP1 using anti-AFAP/AFAP1 antibody (A05258-3). AFAP/AFAP1 was detected in paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-AFAP/AFAP1 Antibody (A05258-3) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-AFAP/AFAP1 Antibody ®
Cat # A05258-3

A05258-3 will render with an IHC figure from a human lung cancer paraffin section; a second caption documents human prostatic cancer paraffin tissue (catalog image captions). Its listed applications include IHC, and its stated reactivity is human, mouse and rat; no IF/ICC application or image is listed (catalog applications; catalog reactivity; catalog image captions).

Which to pick: Choose A05258-3 for human paraffin-section IHC: its own captions document both tissues, while the fixative is unreported (catalog image captions). No SKU in this payload is validated for IF/ICC, so there is no supported IF/ICC pick (catalog applications; catalog image captions). A05258-3 lists mouse and rat reactivity, but the supplied IHC images show human tissue only; it is a rabbit antibody with no clone specified (catalog reactivity; catalog image captions; catalog host; catalog clone).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q8N556 (AFAP1_HUMAN, Actin filament-associated protein 1).
  2. Human Protein Atlas. AFAP1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. AFAP1 subcellular location (ICC-IF): Mainly localized to the actin filaments. In addition localized to the cytosol and focal adhesion sites..
  4. Human Protein Atlas. AFAP1 antibody validation summary (2 antibodies).
  5. Co-expression of AFAP1-AS1 and PD-1 predicts poor prognosis in nasopharyngeal carcinoma. Oncotarget 2017 — PMC5503590.
  6. AFAP1L1 is a novel adaptor protein of the AFAP family that interacts with cortactin and localizes to invadosomes. European journal of cell biology 2011 — PMC3085893.
  7. Long noncoding RNA actin filament-associated protein 1 antisense RNA 1 promotes malignant phenotype through binding with lysine-specific demethylase 1 and repressing HMG box-containing protein 1 in non-small-cell lung cancer. Cancer science 2019 — PMC6609801.
  8. Long non-coding RNA AFAP1-AS1 promotes alternative splicing of AXIN2 by facilitating SRSFs phase separation to induce drug resistance in lung adenocarcinoma. Molecular cancer 2025 — PMC12632050.
  9. PubMed PMID:15485829 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15815621 — UniProt-cited evidence.