This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic AHSA1 IHC in paraffin sections using fallopian tube glandular cells as a high-staining reference (HPA tissue IHC). Start the catalog antibody at 2–5 μg/ml and compare with salivary gland glandular cells, where staining was not detected (datasheet A05733-2; HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic signal across most tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A05733-2) | |
| Positive control | Fallopian tube+4 more · see all | |
| Negative control | Salivary gland+2 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Staining has medium consistency with RNA data (HPA tissue IHC) | |
| Regulation | Expression regulation unreported (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope differences unreported (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet A05733-2) and a published protocol for oral tissues (PMC12519801) provide starting points for AHSA1 staining.
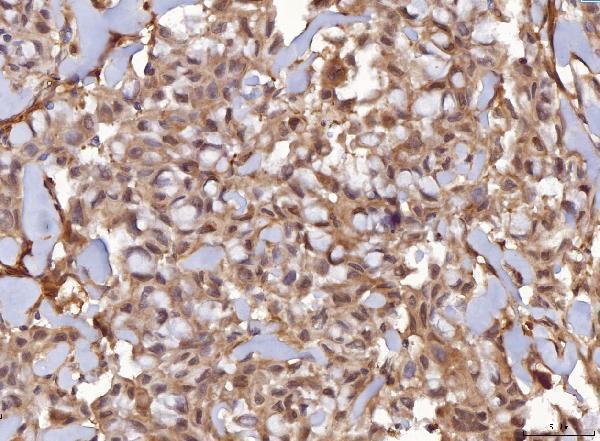
| Sample | Paraffin-embedded human breast infiltrating ductal carcinoma tissue; fixative not specified (datasheet A05733-2) |
| Fixation | Image fixative and duration unreported (datasheet A05733-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A05733-2); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A05733-2) |
| Primary antibody | Rabbit anti-AHSA1, 2-5 μg/ml (datasheet A05733-2) |
| Primary incubation | Overnight at 4 °C (datasheet A05733-2) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A05733-2) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | AHSA1-positive staining in glandular cells of fallopian tube (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
AHSA1 should stain mainly in the cytoplasm, consistent with its cytosolic localization and lack of a transmembrane segment (UniProt O95433; HPA: cytoplasmic expression in most tissues). Expect prominent staining in fallopian tube glandular cells, tonsil germinal center cells, and late spermatids (HPA: High). HPA rates its tissue IHC evidence Supported, with medium consistency between antibody staining and RNA expression (HPA).
| Clear cytoplasmic staining in fallopian tube glandular cells, tonsil germinal center cells, or late spermatids. | This matches the strongest listed tissue IHC patterns (HPA: High in each cell population). Assess the named cells within the section; neighboring cell types need not have the same intensity (HPA: cell-specific tissue IHC entries). |
| Predominantly nuclear staining, or a sharp plasma membrane outline, with little cytoplasmic signal. | Question specificity: AHSA1 is principally cytosolic (HPA: cytosol; UniProt O95433: cytosol). UniProt reports no transmembrane segment and only a possible transient ER interaction, which does not establish a dominant membrane pattern (UniProt O95433). |
| Strong staining in salivary glandular cells, skeletal myocytes, or smooth muscle cells while expected positive cells are weak. | These cells were not detected in the listed HPA tissue IHC observations (HPA: Not detected). Check cross-reactivity and chromogenic detection background before calling the signal AHSA1 (standard IHC practice); a single negative reference is not proof of biological absence. |
| Uniform color across cells, stroma, and empty spaces, with poor cell boundaries. | Treat diffuse staining as background until controls show a cell-associated pattern (standard IHC practice). AHSA1's reported tissue pattern is cytoplasmic and varies by cell type (HPA); uniform slide-wide color is not evidence of broader expression. |
| No staining in the named cells of a known-positive tissue. | A blank result conflicts with the listed high-staining references (HPA: fallopian tube glandular cells, tonsil germinal center cells, late spermatids). First verify that the expected cells are present and that the detection run worked (standard IHC practice); do not infer AHSA1 loss from one section. |
| Cell population and tissue | HPA reports High staining in three named populations, Medium in several others, and Not detected in selected glandular and muscle cells (HPA: tissue IHC). Score the relevant cells rather than assigning one intensity to an entire section (standard IHC practice). |
| Compartment | Cytosol is supported by ICC-IF, and cytoplasmic expression is reported across most tissues (HPA: subcellular; HPA: tissue IHC). UniProt allows transient ER interaction, so a minor reticular component alone cannot establish a separate, stable localization (UniProt O95433). |
| Antibody evidence | Both listed antibodies have Supported IHC status (HPA: HPA000903 and CAB006244). Overall tissue IHC reliability is Supported with medium staining–RNA consistency (HPA); interpret unexpected staining against tissue controls rather than treating validation status as proof for every section. |
| Isoforms and modifications | Two isoforms and several modified residues are annotated (UniProt O95433). The payload gives no epitope mapping or evidence that either feature changes IHC staining; do not assign an unusual pattern to an isoform or modification without separate validation. |
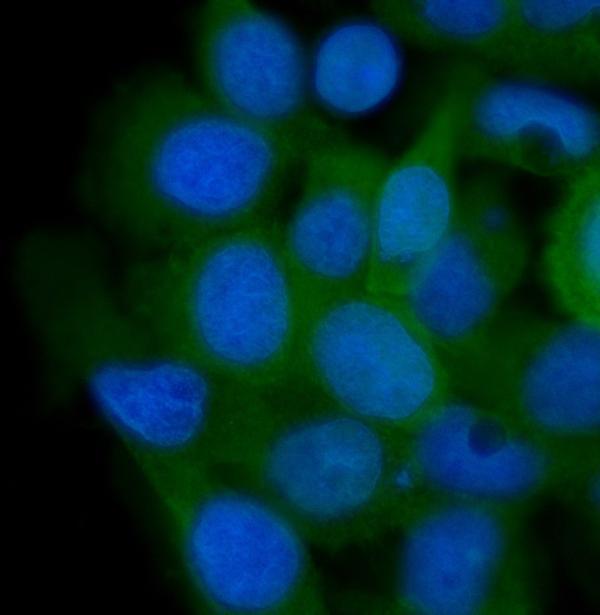
| What should ICC-IF show? | A cytosolic pattern is the supported reference, with images listed for A-431, U-251MG, and U2OS (HPA: subcellular ICC-IF). ICC-IF is a localization cross-check; this section provides no IF/ICC protocol option. |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive tissue appears blank. | The expected cell population may be absent from the section, or the IHC run may have failed (standard IHC practice). | Confirm the relevant cells are present; check run controls and the catalog antibody's IHC-P instructions before interpreting absence (standard IHC practice; HPA: named High populations). |
| Nuclei dominate the signal. | The compartment disagrees with supported cytosolic localization (HPA: cytosol; UniProt O95433: cytosol). | Compare with a known-positive section and reagent controls; score AHSA1 only where cell-associated cytoplasmic staining is credible (standard IHC practice; HPA: cytoplasmic tissue expression). |
| Muscle or salivary glandular cells stain strongly. | This conflicts with the listed Not detected observations and may reflect cross-reactivity or detection background (HPA: tissue IHC; standard IHC practice). | Check a no-primary control and compare the result with a high-staining reference population before accepting the unexpected signal (standard IHC practice; HPA: High populations). |
| Chromogen covers the section diffusely. | Nonspecific antibody binding or endogenous detection activity can obscure a cellular pattern (standard chromogenic IHC practice). | Review blocking, washes, detection controls, and counterstain; seek defined cytoplasmic staining in the named cells (standard IHC practice; HPA: cytoplasmic tissue expression). |
| Only faint staining appears in liver cholangiocytes or lung macrophages. | These are listed as Low, so weak signal there alone does not indicate assay failure (HPA: tissue IHC). | Judge run sensitivity using a named High population in an appropriate control section, while scoring the low-level cells separately (HPA: tissue IHC; standard IHC practice). |
| Two validated antibodies give different intensities. | Supported IHC status does not establish identical staining strength, and HPA reports only medium staining–RNA consistency overall (HPA: antibody validation; HPA: reliability). | Compare compartment and cell distribution against the same tissue controls; document disagreement without assigning an epitope or fixation cause that the supplied evidence does not establish. |
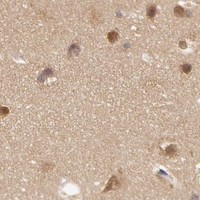


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Fallopian tube | Glandular cells | High | Protein (IHC) | HPA → |
| Testis | Elongated or late spermatids | High | Protein (IHC) | HPA → |
| Tonsil | Germinal center cells | High | Protein (IHC) | HPA → |
| Adipose tissue | Adipocytes | Medium | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
Use cytoplasmic staining as the main readout for AHSA1 in paraffin sections (HPA: cytoplasmic expression in most tissues; UniProt O95433: cytosol).
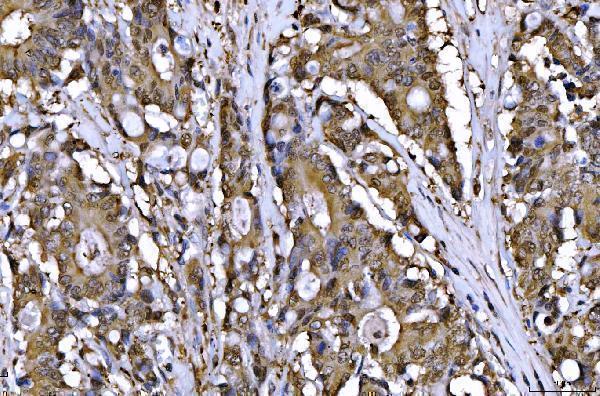
A05733-2 has IHC images from paraffin-embedded human carcinoma sections and an IF image from A431 cells (catalog image captions); listed reactivity covers human, mouse, and rat (catalog: reactivity).
A05733-2 is listed for IHC, ICC, and IF in human, mouse, and rat (catalog: applications and reactivity). Its IHC captions show human breast infiltrating ductal carcinoma, colorectal adenocarcinoma, endometrial cancer, and laryngeal squamous cell carcinoma sections; its IF caption shows A431 cells (A05733-2 image captions).
Which to pick: For tissue IHC, choose A05733-2: its captions document paraffin-embedded sections with EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody (A05733-2 IHC captions). For IF/ICC, the same SKU has an A431 cell IF image using 5 μg/ml primary antibody (A05733-2 IF caption). For cross-species work, A05733-2 lists human, mouse, and rat reactivity; clone identity and the IHC section fixative are unreported (catalog: reactivity and clone; A05733-2 IHC captions).