AKAP1 / A-kinase anchor protein 1, mitochondrial · IHC design guide

Design Immunohistochemistry for AKAP1

Plan AKAP1 staining in paraffin sections around the granular cytoplasmic pattern reported across tissues (HPA tissue IHC). The catalog antibody lists an IHC dilution of 1:50–1:200 (datasheet).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for AKAP1 (IHC for AKAP1): expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial outer membrane (UniProt), antibody A04451-1, validated IHC image, and IHC protocol steps
Printable AKAP1 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial outer membrane (UniProt), antibody A04451-1, controls and protocol steps. Open the full AKAP1 IHC guide →

AKAP1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial outer membrane (UniProt)
Staining pattern Granular cytoplasmic staining across tissues (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across compared paraffin sections. (selected-SKU IHC image A04451-1)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Isoform 2 is enriched in testis (UniProt)
Isoform / epitope 2 isoforms; N306 epitope coverage is unreported (UniProt; datasheet)
Section 1

Recommended AKAP1 IHC & IF Protocols

The catalog antibody protocol is followed by published AKAP1 IHC methods from three PMC articles (PMC5520900; PMC6006472; PMC12062205).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human brain tissue; fixative not specified (datasheet A04451-1)
FixationImage fixative and duration unreported (datasheet A04451-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-AKAP1, 1:50-1:200 (datasheet A04451-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultAKAP1-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Granular cytoplasmic expression in all tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 heat retrieval at 95–98 °C for 20 min (page retrieval rule); optimize against the published conditions for the chosen tissue.
Section 2

What Is the Expected AKAP1 Staining Pattern?

AKAP1 is anchored at the cytoplasmic face of the mitochondrial outer membrane, so paraffin-section IHC should show granular cytoplasmic staining rather than nuclear staining (UniProt Q92667 topology; HPA: granular cytoplasmic expression). HPA reports staining across tissues, including high staining in selected glandular, endothelial and neural cell populations; its tissue IHC reliability is Supported, with medium consistency between staining and RNA data (HPA tissue IHC).

What am I looking at on my slide?
Granular cytoplasmic staining in appendix or breast glandular cells, or colon endothelial cells.This fits the reported AKAP1 tissue pattern and mitochondrial location (HPA: High in those cells; HPA: granular cytoplasmic expression; UniProt Q92667 topology). Judge the named cell population, not the whole section: a tissue can contain cells with different staining levels (HPA tissue IHC).
Strong staining confined to nuclei, or a sharp cell-surface outline without cytoplasmic granules.That distribution conflicts with the expected mitochondrial outer-membrane pattern (UniProt Q92667 topology; HPA: granular cytoplasmic expression). Treat it as suspect and compare with a known-positive section and a no-primary control before assigning AKAP1 positivity (general IHC practice).
Strong staining in a cell population outside the reported high-staining populations.Check its identity before calling it nonspecific: HPA reports granular cytoplasmic expression across tissues, and its supplied list of high-staining cells is not an exhaustive negative-cell map (HPA tissue IHC). An inconsistent pattern may reflect cross-reactivity or endogenous chromogenic activity (general IHC practice).
Diffuse color covers cells and surrounding tissue, obscuring cytoplasmic granules.That distribution is difficult to interpret as AKAP1 because the reported tissue pattern is granular and cytoplasmic (HPA tissue IHC). Background may arise from detection chemistry, insufficient blocking or excessive antibody concentration; distinguish these with controls (general IHC practice).
No visible staining in a section expected to contain high-staining glandular or endothelial cells.An assay failure is possible when appendix glandular cells or colon endothelial cells lack their reported high signal (HPA: High in those cells). First confirm that the relevant cells are present, then assess the staining run; absence alone does not establish a true negative (general IHC practice).
💡Expected AKAP1 appearanceCall a positive result when the relevant cells show distinct granular cytoplasmic signal, potentially high in the specified HPA populations; nuclear-only or uniformly diffuse color is suspect (HPA tissue IHC; UniProt Q92667 topology; general IHC practice).
How each factor affects the staining
Subcellular locationAKAP1 anchors protein kinase A at the cytoplasmic face of the mitochondrial outer membrane, supporting a granular cytoplasmic IHC expectation (UniProt Q92667 topology and function; HPA tissue IHC). Chromogenic IHC cannot establish which membrane face carries the detected epitope (general IHC practice).
Tissue and cell populationHPA describes granular cytoplasmic expression in all tissues but identifies specific high-staining cells, including appendix and duodenal glandular cells, caudate glial cells and cerebral-cortex endothelial cells (HPA tissue IHC). Compare like cell populations when judging intensity (general IHC practice).
Isoform expressionUniProt reports two isoforms: isoform 1 in thymus, prostate, testis, ovary, colon and small intestine; isoform 2 is highly expressed in testis and detected at lower levels in several other tissues (UniProt Q92667 tissue specificity). Antibody recognition of each isoform is unspecified in the supplied record.
Antibody evidenceHPA lists IHC as Supported for HPA008691 and CAB019286; HPA008620 has ICC support but no listed IHC status (HPA antibody validation). The tissue profile has Supported reliability with medium staining–RNA consistency (HPA tissue IHC).
Antigen retrieval and fixationTarget-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive cells show no signal.The expected cells may be absent from the section, or the staining run may have failed (HPA: High in appendix glandular cells and colon endothelial cells; general IHC practice).Confirm cell identity on the counterstained section, check the positive control, and review the antibody dilution, retrieval and detection steps used in that run (general IHC practice).
Signal is weak or uneven within a known-positive cell population.HPA's High category identifies reported cell populations; it does not guarantee identical staining in every cell or section (HPA tissue IHC). Technical variation can also affect chromogenic intensity (general IHC practice).Compare equivalent cells in a concurrently stained positive section, then review section quality and the recorded retrieval, antibody and detection conditions (general IHC practice).
Nuclei dominate the staining.A nuclear-only pattern does not fit AKAP1's mitochondrial outer-membrane location or HPA's granular cytoplasmic tissue pattern (UniProt Q92667 topology; HPA tissue IHC).Check a no-primary control and a known-positive section; interpret nuclear color cautiously until a granular cytoplasmic pattern is demonstrated (general IHC practice).
Unreported cell populations stain strongly.The supplied HPA high-staining list is not a negative-cell list, although cross-reactivity or endogenous chromogenic activity can produce misleading color (HPA tissue IHC; general IHC practice).Verify cell identity and granular cytoplasmic location; use a no-primary control and the relevant detection-activity control to assess background (general IHC practice).
Color is diffuse throughout the section.Diffuse background obscures the reported granular cytoplasmic pattern (HPA tissue IHC). Excess antibody, inadequate blocking or detection background are possible general IHC causes (general IHC practice).Review the no-primary control, blocking and washing steps, and the antibody dilution used; score only cells whose granules remain distinguishable (general IHC practice).
What should IF/ICC show?HPA supports mitochondrial localization in ICC-IF and lists images from A-431, U-251MG, U2OS, CACO-2 and PC-3 cells (HPA subcellular ICC-IF).Expect mitochondrial localization in IF/ICC (HPA subcellular ICC-IF). Use the separate IF/ICC guide for assay setup; the IHC tissue pattern alone does not specify an IF/ICC protocol (HPA tissue IHC; HPA subcellular ICC-IF).

Sample controls for AKAP1 IHC & IF

🧪Run appendix first and score its glandular cells, which show High AKAP1 staining (HPA: appendix glandular cells, High). HPA detects AKAP1 in all 45 scored tissues, so there is no validated negative tissue; use no-primary and isotype controls, and treat any adjacent cells lacking chromogen as a background reference rather than a proven biological negative (HPA: no negative tissue rows; AKAP1 detected in all 45 scored tissues).
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: None in HPA: AKAP1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show AKAP1 in A-431, U-251MG, U2OS, CACO-2, PC-3, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide and an isotype control matched to the primary antibody’s host and immunoglobulin class; the caption identifies the catalog antibody as polyclonal but does not state its host species (catalog antibody A04451-1 caption: pAb). A validated AKAP1 knockout specimen can provide a biological negative; for chromogenic appendix IHC, block endogenous peroxidase and assess residual background in both control slides (standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected A04451-1 paraffin-section brain caption does not report a fixative (catalog antibody A04451-1 caption). An AKAP1-specific antigen retrieval requirement is also unreported, so optimize retrieval empirically for the chosen antibody; the supplied evidence does not establish whether frozen sections or IF are easier (supplied application evidence). IF offers a mitochondrial localization check (HPA: mitochondria, supported), while appendix chromogenic staining should be interpreted against endogenous peroxidase background (HPA: appendix glandular cells, High; standard IHC practice).

HPA tissue IHC evidence for AKAP1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Caudate Glial cells High Protein (IHC) HPA →
Cerebellum Cells in molecular layer High Protein (IHC) HPA →
Cerebral cortex Endothelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: AKAP1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced AKAP1 IHC Tips

Troubleshoot AKAP1 staining in paraffin section chromogenic IHC, with one question addressing IF multiplexing.

What should I change when AKAP1 staining is weak after retrieval?
Use citrate pH 6.0 HIER at 95–98 °C for 20 min on AKAP1 paraffin sections (page retrieval specification). Confirm that sections remained covered by buffer, then compare a known positive area with the same area on a no-primary control (standard IHC practice; HPA: granular cytoplasmic expression in all tissues). If staining remains weak, compare a small retrieval time series while keeping antibody concentration and detection constant (standard IHC practice). Check that the recovered signal is granular and cytoplasmic, consistent with AKAP1 at the mitochondrial outer membrane, before accepting a stronger signal as an improvement (HPA tissue IHC; UniProt Q92667 topology).
Could fixation explain weak AKAP1 staining in my paraffin sections?
AKAP1-specific fixation sensitivity is unknown from the supplied evidence; the selected antibody caption identifies paraffin-embedded human brain tissue but does not state its fixative (A04451-1 tissue-IHC caption). Record the actual fixative, time before fixation, and fixation duration for each specimen, then compare similarly processed sections in the same staining run (standard IHC practice). Test the page’s citrate pH 6.0 retrieval at 95–98 °C for 20 min before changing several variables together (page retrieval specification; standard IHC practice). Interpret any difference as a processing association until matched material and controls establish whether fixation itself caused it (standard IHC practice).
Where should convincing AKAP1 chromogenic staining appear?
Look for granular cytoplasmic staining, matching the reported tissue IHC pattern and mitochondrial localisation (HPA tissue IHC; HPA subcellular). AKAP1 anchors protein kinase A regulatory subunits at the cytoplasmic face of the mitochondrial outer membrane, so a diffuse nuclear-only pattern warrants scrutiny (UniProt Q92667 function and topology). Compare staining within the expected cell compartment against adjacent cells and a no-primary control under identical detection conditions (standard IHC practice). In brain sections, interpret the labeled cell population explicitly: high staining is reported in caudate glial cells, cerebellar molecular-layer cells, and cerebral cortex endothelial cells (HPA tissue IHC).
How can isoforms or epitope accessibility complicate AKAP1 IHC?
AKAP1 has 2 recorded isoforms, and the supplied evidence does not map this antibody’s epitope to either one (UniProt Q92667 isoforms; A04451-1 tissue-IHC caption). Isoform 1 is reported in thymus, prostate, testis, ovary, colon, and small intestine; isoform 2 is highly expressed in testis (UniProt Q92667 tissue specificity). Compare the immunogen sequence with isoform sequences when antibody documentation provides it, and avoid assigning an IHC signal to one isoform without that mapping (standard IHC interpretation). AKAP1 contains KH and Tudor domains and multiple modified residues, but their effects on this antibody’s paraffin-section epitope are untested here (UniProt Q92667 domains and modified residues; supplied antibody evidence).
How should I investigate AKAP1 by multiplex IF?
Treat IF as a separate assay and first establish that the antibody produces a reproducible mitochondrial pattern with appropriate negative controls (HPA subcellular; standard IF practice). Multiplex with a marker for the cell population being examined, such as a validated glial marker when assessing caudate glial cells, and check channels individually (HPA: High in caudate glial cells; standard IF practice). Choose fluorophores after measuring section autofluorescence and place the weaker signal in a cleaner channel (standard IF practice). Because AKAP1 faces the cytoplasm at the mitochondrial outer membrane, optimise permeabilisation for access to that side while preserving mitochondrial structure (UniProt Q92667 function and topology; standard IF practice).
What causes diffuse or widespread brown background in AKAP1 IHC?
Run a no-primary control and examine whether brown signal persists; persistent signal directs attention to detection chemistry or tissue background (standard chromogenic IHC practice). Block endogenous peroxidase before HRP and DAB detection, and compare blocking, wash conditions, and antibody concentration one variable at a time (standard chromogenic IHC practice). Do not assume every granular cytoplasmic signal is background, because that distribution is reported across tissues for AKAP1 (HPA tissue IHC). Conversely, strong staining confined to folds, damaged edges, or necrotic regions should be excluded from interpretation even when nearby cells show the expected mitochondrial-associated pattern (standard IHC practice; UniProt Q92667 localisation).
How should I score heterogeneous AKAP1 staining across cells? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and analysis region before scoring, then exclude folds, necrosis, and section edges consistently (standard IHC practice). For chromogenic sections, report an H-score from intensity categories 0–3 weighted by percent of cells, alongside percent positive cells when the threshold is reproducible (standard IHC scoring practice). If counting positive cells, report density per mm² and normalise to analyzed tissue area or the number of eligible cells in the specified compartment (standard IHC quantification practice). Keep exposure, detection, thresholds, and scoring rules matched across groups, and report cell types separately because AKAP1 staining varies by tissue compartment (standard IHC practice; HPA tissue IHC).
How can I distinguish genuine AKAP1 signal from staining artefact?
Favor granular cytoplasmic signal in intact cells over isolated nuclear or extracellular deposits, consistent with AKAP1’s mitochondrial outer-membrane location (HPA tissue IHC; UniProt Q92667 localisation). Check the identity of positive cells: reported examples include caudate glial cells and cerebral cortex endothelial cells, so a result in another population needs its own validation (HPA tissue IHC; standard IHC interpretation). Compare suspect staining with no-primary controls and inspect section edges and necrotic areas for artefact or residual endogenous enzyme activity (standard chromogenic IHC practice). HPA rates tissue staining as Supported with medium RNA–staining consistency, so use orthogonal evidence before making a strong cell-specific biological claim (HPA tissue IHC; standard IHC interpretation).
Boster reagents

Best AKAP1 / A-kinase anchor protein 1, mitochondrial IHC Antibodies

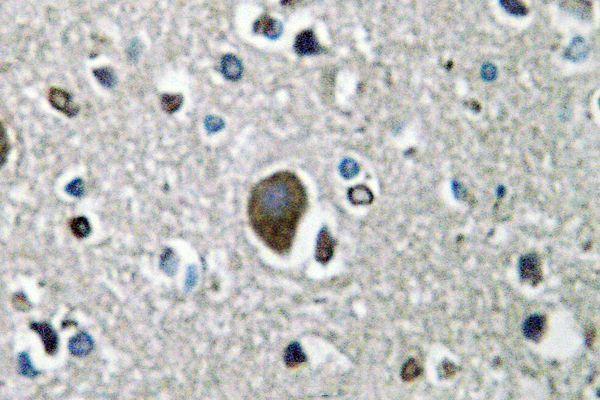
Anti-AKAP1 A04451-1 has an IHC image from paraffin-embedded human brain (IHC image caption); IF is listed, and reactivity covers Human, Mouse and Rat (catalog applications and reactivity).

Real IHC data Immunohistochemistry (IHC) analyzes of AKAP 1 (N306) pAb in paraffin-embedded human brain tissue.
Anti-AKAP 1 (N306) Antibody
Cat # A04451-1

A04451-1 renders with an IHC image of paraffin-embedded human brain (IHC image caption). Its listed applications include IHC and IF, with Human, Mouse and Rat reactivity (catalog applications and reactivity); no IF image is supplied (catalog image alts).

Which to pick: Choose A04451-1 for paraffin-section IHC because its own image caption documents staining in human brain tissue (IHC image caption); the fixative is unreported (IHC image caption). For IF, A04451-1 is listed, but ICC validation and an IF image are unreported (catalog applications and image alts). For Mouse or Rat samples, A04451-1 is the listed cross-species choice; its rabbit host and polyclonal designation come from the catalog and IHC image caption, respectively (catalog host and reactivity; IHC image caption: pAb).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q92667 (AKAP1_HUMAN, A-kinase anchor protein 1, mitochondrial).
  2. Human Protein Atlas. AKAP1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. AKAP1 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. AKAP1 antibody validation summary (3 antibodies).
  5. Mitochondrial AKAP1 supports mTOR pathway and tumor growth. Cell death & disease 2017 — PMC5520900.
  6. Higher expression of A-kinase anchoring-protein 1 predicts poor prognosis in human hepatocellular carcinoma. Oncology letters 2018 — PMC6006472.
  7. Mitochondrial PKA Is Neuroprotective in a Cell Culture Model of Alzheimer's Disease. Molecular neurobiology 2021 — PMC8260456.
  8. Hepatic AKAP1 deficiency exacerbates diet-induced MASLD by enhancing GPAT1-mediated lysophosphatidic acid synthesis. Nature communications 2025 — PMC12062205.
  9. PubMed PMID:8769136 — UniProt-cited evidence.
  10. PubMed PMID:7499250 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.