AKT1S1 / Proline-rich AKT1 substrate 1 · IHC design guide

Design Immunohistochemistry for AKT1S1

Plan chromogenic IHC-P for AKT1S1 using its reported cytoplasmic tissue pattern (HPA tissue IHC). Compare staining with the listed glandular positives and score cautiously because antibody staining and RNA show low consistency (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for AKT1S1 (IHC for AKT1S1): expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A03629, validated IHC image, and IHC protocol steps
Printable AKT1S1 IHC protocol sheet — expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A03629, controls and protocol steps. Open the full AKT1S1 IHC guide →

AKT1S1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining in glandular and other cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Heart muscle
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep formalin fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Antibody staining and RNA show low consistency (HPA tissue IHC)
Regulation Insulin alters mTORC1 association (UniProt)
Isoform / epitope 3 isoforms; verify antibody epitope coverage (UniProt)
Section 1

Recommended AKT1S1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with one published phospho-AKT1S1 IHC protocol (PMC4753445).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A03629); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-AKT1S1, 1:100–1:500 starting range (standard)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultAKT1S1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page retrieval rule); consider the published Tris-EDTA conditions for phospho-S202/203 staining (PMC4753445).
Section 2

What Is the Expected AKT1S1 Staining Pattern?

AKT1S1 is a cytosolic protein with no transmembrane segment (UniProt Q96B36: subcellular location and topology). In paraffin section IHC, expect predominantly cytoplasmic staining in the cell types where HPA reports expression, including glandular and respiratory epithelial cells (HPA tissue IHC: general cytoplasmic expression; medium staining). Treat tissue comparisons cautiously: HPA rates its IHC reliability Approved but reports low consistency between antibody staining and RNA expression (HPA tissue IHC: reliability description).

What am I looking at on my slide?
Cytoplasmic colour in glandular cells of appendix, duodenum or endometrium, with nuclei defined by the counterstain.This matches the reported medium staining in those cells and the general cytoplasmic pattern (HPA tissue IHC: medium; general cytoplasmic expression). Judge the distribution within cells before comparing overall darkness between sections (general IHC practice).
Predominantly nuclear, membranous or extracellular colour with little cytoplasmic signal.That distribution does not match the reported cytosolic location or lack of a transmembrane segment (UniProt Q96B36: location and topology; HPA subcellular: cytosol). Check whether the colour tracks tissue edges, counterstain or nonspecific deposits before assigning AKT1S1 positivity (general IHC practice).
Strong colour in an unexpected cell population, especially cardiomyocytes, while the expected cytoplasmic pattern is absent.HPA reports AKT1S1 as not detected in cardiomyocytes, although UniProt reports high expression in heart (HPA tissue IHC: heart muscle; UniProt Q96B36: tissue specificity). The discrepancy prevents a definitive call from that tissue alone; assess antibody specificity and detection background (general IHC practice).
Even colour across cells, stroma and empty areas, without discernible cytoplasmic boundaries.A uniform haze does not reproduce HPA's cell associated cytoplasmic staining (HPA tissue IHC: general cytoplasmic expression). It may reflect detection background or nonspecific binding; compare a no primary control and inspect wash and blocking steps (general IHC practice).
No cytoplasmic signal in an otherwise interpretable appendix or duodenum section.HPA reports medium staining in glandular cells of both tissues, so absence merits a technical check (HPA tissue IHC: appendix and duodenum). Expression varies among cells and assays; one negative section alone does not establish absence of AKT1S1 (HPA tissue IHC: low antibody and RNA consistency).
💡Expected AKT1S1 appearanceCall a convincing positive when glandular or respiratory epithelial cells show discernible cytoplasmic chromogen, around the medium level reported by HPA; isolated nuclear, stromal or uniform background colour is insufficient (HPA tissue IHC: medium; general cytoplasmic expression).
How each factor affects the staining
Compartment and topologyCytosolic localisation supports a cytoplasmic interpretation; no transmembrane segment supports scrutiny of membrane only staining (UniProt Q96B36: location and topology; HPA subcellular: cytosol).
Cell and tissue contextHPA reports medium staining in several glandular and epithelial populations, low staining in listed neuronal populations, and no detection in cardiomyocytes (HPA tissue IHC: positive, low and negative entries). Compare like cell types.
Evidence agreementHPA's Approved IHC reliability accompanies low antibody staining and RNA consistency; UniProt's high heart expression also differs from HPA's cardiomyocyte result (HPA tissue IHC: reliability and heart muscle; UniProt Q96B36: tissue specificity).
Antibody and molecular scopeHPA lists three antibodies with Approved IHC status and one with ICC support only (HPA antibodies: HPA064427, HPA075510, CAB021903, HPA043590). UniProt lists three isoforms and multiple modified residues; epitope coverage and modification sensitivity are unspecified here (UniProt Q96B36: isoforms and modified residues).
IF/ICC Q&A: where should signal appear?Cytosol is the supported location in HPA cell images, consistent with UniProt (HPA subcellular: cytosol; UniProt Q96B36: location). Use the separate IF/ICC guide for that application; this IHC pattern does not establish an IF protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Cytoplasmic staining is weak in an HPA medium staining cell type.The result may reflect run conditions or biological variation; HPA reports low consistency between staining and RNA data (HPA tissue IHC: reliability description).Confirm the cell identity and compare a same run positive section; review the selected IHC antibody's validated conditions, including retrieval and dilution (general IHC practice).
No signal appears in the test section or the same run positive section.A shared detection or staining step may have failed (general IHC practice).Check primary antibody application, detection reagents and chromogen development; repeat with a suitable positive section (general IHC practice).
Brown colour is diffuse or follows section edges.Background, drying or uneven reagent coverage can obscure cell boundaries (general IHC practice).Inspect a no primary control, section coverage, blocking and wash steps; interpret only reproducible cell associated colour (general IHC practice).
Colour persists in a no primary control.Primary antibody independent detection activity or nonspecific chromogen deposition may be present (general IHC practice).Address the detection system and its background controls before scoring AKT1S1 (general IHC practice).
Nuclei or membranes dominate the stain.The pattern conflicts with supported cytosolic localisation (HPA subcellular: cytosol; UniProt Q96B36: location and topology).Review morphology and controls, then assess antibody specificity; do not score compartment mismatched colour as a confirmed positive (general IHC practice).
Heart staining disagrees with an expected positive control result.UniProt reports high heart expression, while HPA reports no detection in cardiomyocytes (UniProt Q96B36: tissue specificity; HPA tissue IHC: heart muscle).Use an HPA medium staining cell type as a comparison and record the discordance rather than treating either heart result as decisive (HPA tissue IHC: positive entries and reliability description).

Sample controls for AKT1S1 IHC & IF

🧪Run adrenal gland first: glandular cells should stain at a medium level (HPA: adrenal gland, glandular cells, Medium). Use heart muscle as the negative tissue because cardiomyocytes are not detected (HPA: heart muscle, cardiomyocytes, Not detected); on the adrenal slide, cells outside the glandular compartment should show only background, assessed against the no-primary control.
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Heart muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show AKT1S1 in A-431, U-251MG, U2OS, HEK293, PC-3, NIH 3T3, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a concentration-matched isotype control matching the primary antibody’s host species and clonality, and a biological negative such as AKT1S1 knockout tissue or a validated immunizing-peptide block (standard IHC practice). For adrenal sections, quench endogenous peroxidase and check for pigment or other background before scoring chromogenic stain (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and retrieval dependence are unreported in the supplied evidence; the selected A03629 tissue-IHC caption gives 2.5 μg/ml for rat brain but does not report a fixative (selected A03629 caption: fixative not stated). Frozen sections cannot be ranked as easier from these data; IF/ICC can provide a cytosolic localization cross-check, but its relative ease is unreported (HPA subcellular: Cytosol, supported). In adrenal tissue, distinguish chromogenic signal from endogenous peroxidase activity and pigment (standard IHC practice).

HPA tissue IHC evidence for AKT1S1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Cervix Glandular cells Medium Protein (IHC) HPA →
Colon Endothelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Section 3

Advanced AKT1S1 IHC Tips

Troubleshoot AKT1S1 chromogenic IHC by checking retrieval, cytoplasmic staining, controls and cell-level scoring before interpreting changes in signal.

How should I retrieve AKT1S1 in paraffin sections if cytoplasmic staining is weak?
Start with citrate pH 6.0 heat-induced epitope retrieval at 95–98 °C for 20 min (page retrieval specification: cytoplasmic antigen). AKT1S1 is a cytosolic protein without a transmembrane segment, so assess staining within cell boundaries rather than treating membrane outlines as the expected pattern (UniProt Q96B36 subcellular location and topology). If signal remains weak, compare a slightly longer retrieval time on matched sections while holding antibody concentration, detection and development time constant (standard IHC practice). Include a tissue section with previously reproducible staining in each run, and reject retrieval changes that raise diffuse background along with apparent signal (standard IHC practice).
Could fixation explain inconsistent AKT1S1 staining between paraffin blocks?
Target-specific fixation sensitivity is unknown for AKT1S1, and the rat brain tissue IHC caption does not state a fixative (A03629 caption). Record each block’s fixative and fixation duration, then compare sections processed together so handling differences can be assessed (standard IHC practice). For new specimens, use a consistent buffered formalin workflow and avoid interpreting a between-block intensity difference until section thickness, retrieval and detection have been matched (standard IHC practice). If an archived block stains poorly, test another section with the same controls before changing retrieval conditions (standard IHC practice). Report the fixation history alongside any AKT1S1 scoring result so readers can judge comparability.
Which compartment should count as convincing AKT1S1 staining?
Prioritise cytoplasmic staining within identifiable cells: AKT1S1 is reported in the cytosol by UniProt, and HPA describes general cytoplasmic tissue expression (UniProt Q96B36 subcellular location; HPA tissue IHC). HPA also supports a cytosolic location in cell imaging, providing an independent compartment check (HPA subcellular: Cytosol, supported). Score nuclear-only or crisp membrane-only colour separately as unexpected staining rather than combining it with the cytoplasmic score (standard IHC interpretation). Inspect the counterstain and adjacent unstained structures at higher magnification to distinguish intracellular colour from precipitate or pigment (standard IHC practice). Compare the same cell type across sections before attributing a compartment shift to treatment.
Can this antibody distinguish AKT1S1 isoforms or phosphorylation states in tissue?
AKT1S1 has 3 annotated isoforms and multiple modified residues, including phosphoserines at positions 88, 92, 116 and 183 (UniProt Q96B36 isoforms and modified residues). The supplied IHC caption gives neither an epitope sequence nor phospho-selectivity, so its staining cannot be assigned to a particular isoform or phosphorylation state (A03629 caption). Check the antibody’s immunogen and cross-isoform sequence coverage before making an isoform claim, and use a separately validated site-specific reagent for a phosphorylation claim (standard antibody-validation practice). Keep retrieval and detection identical when comparing candidate reagents, because changes in staining alone cannot establish epitope specificity (standard IHC practice).
How can IF help check an ambiguous cytoplasmic IHC pattern?
Use IF/ICC as a separate localisation check and multiplex AKT1S1 with a marker for the cell type being scored in the IHC section (standard IF practice). Expect predominantly cytosolic signal, consistent with the supported HPA cell-imaging location and UniProt annotation (HPA subcellular: Cytosol, supported; UniProt Q96B36 subcellular location). Because AKT1S1 has no transmembrane segment, permeabilise fixed cells to expose the intracellular antigen, then compare permeabilised and matched control preparations (UniProt Q96B36 topology; standard IF practice). Choose fluorophores outside the tissue’s strongest autofluorescence range and inspect single-stain controls before judging colocalisation (standard IF practice). Keep IF findings distinct from evidence that a chromogenic tissue stain is specific.
What should I check when the AKT1S1 chromogen looks diffuse or widespread?
First compare the stained section with a no-primary control processed through the same secondary reagent and chromogen steps (standard IHC practice). Block endogenous peroxidase for enzyme-based detection, use an appropriate protein block, and shorten chromogen development if colour also appears in acellular areas (standard chromogenic IHC practice). Widespread cytoplasmic staining is plausible because HPA reports general cytoplasmic expression, but that pattern alone does not establish antibody specificity (HPA tissue IHC). Use the matched control to identify endogenous enzyme signal or nonspecific detection, and inspect folds, edges and precipitate at higher magnification (standard IHC practice). Retitrate the primary antibody only after these background sources are controlled.
How should I compare AKT1S1 IHC signal across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and cytoplasmic compartment before scoring, since AKT1S1 is annotated in the cytosol (UniProt Q96B36 subcellular location). For cellular staining, record the percentage of positive cells and an H-score using intensity grades 0–3, with a possible total of 0–300 (standard IHC scoring practice). If counting positive cells per mm², normalise to evaluable tissue area; for H-scores, compare the same cell type and exclude necrotic or folded regions (standard IHC practice). Use identical acquisition, counterstaining and scoring thresholds across groups, and report whether scoring was blinded (standard IHC practice). Treat run controls as a check on technical drift before comparing biological groups.
When does AKT1S1 staining support a biological conclusion?
A credible signal follows the expected cytoplasmic distribution within identifiable cells and exceeds matched no-primary background (UniProt Q96B36 subcellular location; standard IHC practice). Check whether colour is confined to tissue edges, folds or necrotic areas, or persists in the no-primary control; these patterns can indicate processing artefact or endogenous detection activity (standard IHC practice). Cell context matters: HPA reports medium staining in several glandular and epithelial populations, while its tissue IHC reliability note cites low consistency with RNA expression (HPA tissue IHC). Finally, total AKT1S1 staining does not by itself establish mTORC1 activity, because AKT1S1 function depends on phosphorylation and its interactions with mTORC1 and 14-3-3 (UniProt Q96B36 function and subunit).
Boster reagents

Best AKT1S1 / Proline-rich AKT1 substrate 1 IHC Antibodies

A03629 has rat-brain IHC and IF images (catalog image captions); Human, Mouse and Rat are listed as reactive species (catalog reactivity).

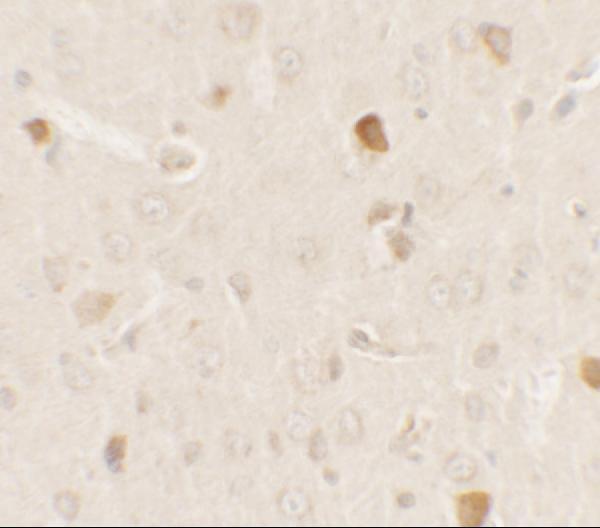
Real IHC data Immunohistochemistry of AKT1S1 in rat brain tissue with AKT1S1 antibody at 2.5 μg/ml.
Anti-Proline-rich AKT1 substrate 1 AKT1S1 Antibody
Cat # A03629

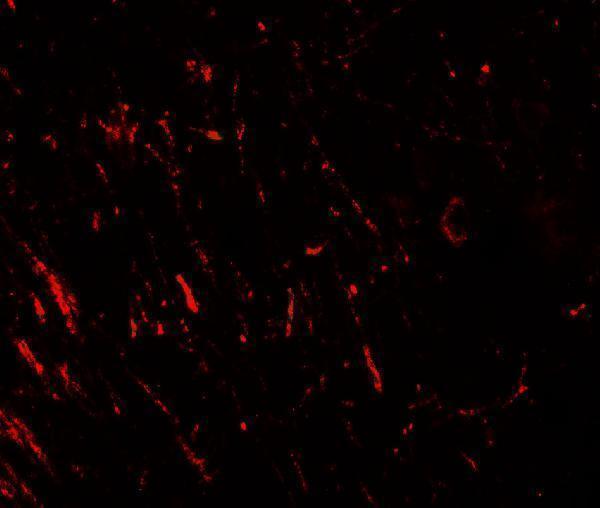
The rendered card is A03629, with IHC shown in rat brain tissue at 2.5 μg/ml (A03629 IHC image caption). Its IF image shows rat brain tissue at 20 μg/ml; Human and Mouse are listed as reactive, without IHC or IF image evidence here (A03629 IF image caption; catalog reactivity).

Which to pick: For paraffin-section IHC, choose A03629: IHC-P is listed and its IHC image shows rat brain tissue; the caption does not report the fixative (A03629 applications; A03629 IHC image caption). For tissue IF, A03629 has a rat-brain image; M03629-2 offers a rabbit monoclonal IF option without a supplied IF image, while ICC is not listed for either (A03629 IF image caption; M03629-2 catalog). For work across Human, Mouse and Rat, A03629 lists all three species for IHC-P and IF, but the supplied images document Rat only (A03629 applications; catalog reactivity; image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q96B36 (AKTS1_HUMAN, Proline-rich AKT1 substrate 1).
  2. Human Protein Atlas. AKT1S1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. AKT1S1 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. AKT1S1 antibody validation summary (4 antibodies).
  5. Pyruvate Kinase M2 Activates mTORC1 by Phosphorylating AKT1S1. Scientific reports 2016 — PMC4753445.
  6. METTL14-mediated m(6)A modification of circORC5 suppresses gastric cancer progression by regulating miR-30c-2-3p/AKT1S1 axis. Molecular cancer 2022 — PMC8842906.
  7. Comprehensive proteomic and pathological profiling identifies PRAS40 as a novel biomarker and mediator of primary immune checkpoint blockade resistance in non-small cell lung cancer. Cancer immunology, immunotherapy : CII 2025 — PMC12514079.
  8. PubMed PMID:14702039 — UniProt-cited evidence.
  9. PubMed PMID:15057824 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.