ALCAM / CD166 antigen · IHC design guide

Design Immunohistochemistry for ALCAM

Plan ALCAM IHC on paraffin sections using its predominantly membranous tissue pattern as a guide (HPA tissue IHC). Start with the catalog antibody’s 2–5 μg/mL IHC range (datasheet A01788-1), and compare bronchial respiratory epithelial cells reported as high with esophageal squamous epithelial cells reported as undetected (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ALCAM (IHC for ALCAM): expected localisation Predominantly cell membrane staining (HPA tissue IHC), antibody A01788-1, validated IHC image, and IHC protocol steps
Printable ALCAM IHC protocol sheet — expected localisation Predominantly cell membrane staining (HPA tissue IHC), antibody A01788-1, controls and protocol steps. Open the full ALCAM IHC guide →

ALCAM Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Predominantly cell membrane staining (HPA tissue IHC)
Staining pattern Membranous staining in most tissues, including parathyroid gland (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01788-1)
Positive control ⓘ Bronchus+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A01788-1)
Caveat A secreted variant may complicate protein–RNA comparisons (HPA tissue IHC)
Regulation Expressed by activated T and B cells (UniProt)
Isoform / epitope 4 isoforms; check whether the epitope is extracellular or cytoplasmic (UniProt)
Section 1

Recommended ALCAM IHC & IF Protocols

The catalog antibody’s IHC-P protocol uses EDTA pH 8.0 heat retrieval (datasheet A01788-1). The three published ALCAM IHC protocols below provide additional tissue-specific conditions (PMC8698607; PMC7714159; PMC4489046).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A01788-1)
FixationImage fixative and duration unreported (datasheet A01788-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01788-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01788-1)
Primary antibodyRabbit anti-ALCAM, 2-5μg/ml (datasheet A01788-1)
Primary incubationOvernight at 4 °C (datasheet A01788-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A01788-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultALCAM-positive staining in respiratory epithelial cells of bronchus (HPA tissue IHC: High). HPA tissue profile: Membranous expression in most tissues, including parathyroid gland. No signal in the no-primary control.
💡Decision noteFor the catalog antibody, start with EDTA pH 8.0 heat retrieval (datasheet A01788-1). Citrate pH 6.0 was reported with a different ALCAM antibody (PMC7714159).
Section 2

What Is the Expected ALCAM Staining Pattern?

ALCAM is a membrane protein with an extracellular region at residues 28–527 and a transmembrane segment at 528–549 (UniProt Q13740 topology). In paraffin section IHC, expect mainly membranous staining in selected epithelial and other cells, including respiratory epithelial cells, cholangiocytes and cells of Bowman’s capsule (HPA: tissue IHC). HPA rates the tissue pattern Enhanced, while noting medium consistency with RNA expression (HPA: reliability description).

What am I looking at on my slide?
Distinct staining outlines respiratory epithelial cells, cholangiocytes or cells of Bowman’s capsule.This fits the reported membranous pattern in these HPA high staining cell populations (HPA: tissue IHC). Judge the named cells and their borders; a positive tissue does not imply that every cell in its section should stain (HPA: cell specific tissue IHC).
Nuclei dominate the stain, with little convincing cell border signal.A dominant nuclear pattern is unsupported by the reported membrane topology and tissue IHC profile (UniProt Q13740 topology; HPA: membranous expression). Treat it as a possible staining artefact and check the counterstain and detection controls before assigning ALCAM positivity (general IHC practice).
Strong stain appears chiefly in adipocytes, cardiomyocytes or esophageal squamous epithelial cells.HPA reports ALCAM as not detected in those specific cell populations (HPA: tissue IHC). Unexpected staining warrants a cross reactivity or endogenous detection activity check (general IHC practice); the HPA result is a cell specific observation, not proof that every such specimen must be negative.
Color spreads across tissue and blank areas without resolving cell borders.Diffuse deposition does not reproduce the reported membranous profile (HPA: tissue IHC). Assess background against a reagent control, then review blocking, washes and chromogen development (general IHC practice). A diffuse field cannot establish which cells express ALCAM.
A bronchus section has no convincing respiratory epithelial signal.Respiratory epithelial cells are reported High in HPA tissue IHC (HPA: bronchus). First check that the expected cells are present and the detection run worked (general IHC practice). A single negative slide cannot establish absence of ALCAM; HPA reports only medium RNA to protein consistency (HPA: reliability description).
💡Expected ALCAM appearanceCall the section positive when identifiable respiratory epithelial cells, cholangiocytes or Bowman’s capsule cells show distinct, relatively strong cell border staining (HPA: High tissue IHC; HPA: membranous profile); nuclear dominant or diffuse color alone is an unsupported positive pattern (UniProt Q13740 topology; HPA: tissue IHC).
How each factor affects the staining
Antibody evidenceTwo listed antibodies, HPA010926 and CAB002148, have Enhanced IHC validation (HPA: antibodies). That supports the reported IHC pattern; it does not validate every antibody or every specimen.
Epitope positionALCAM spans the membrane once and has a large extracellular region (UniProt Q13740 topology). The supplied record gives no epitope for the catalog antibody, so topology alone cannot predict which retrieval condition will work.
Variants and extracellular processingUniProt lists 4 isoforms and a cleaved signal peptide at residues 1–27 (UniProt Q13740 isoforms; processing). HPA notes that at least one protein variant is secreted, complicating agreement between tissue RNA location and protein staining (HPA: reliability description).
GlycosylationNine glycosylation sites are listed in the extracellular region (UniProt Q13740 topology; glycosylation). Their presence does not establish an effect on this antibody’s IHC staining without its epitope and validation data.
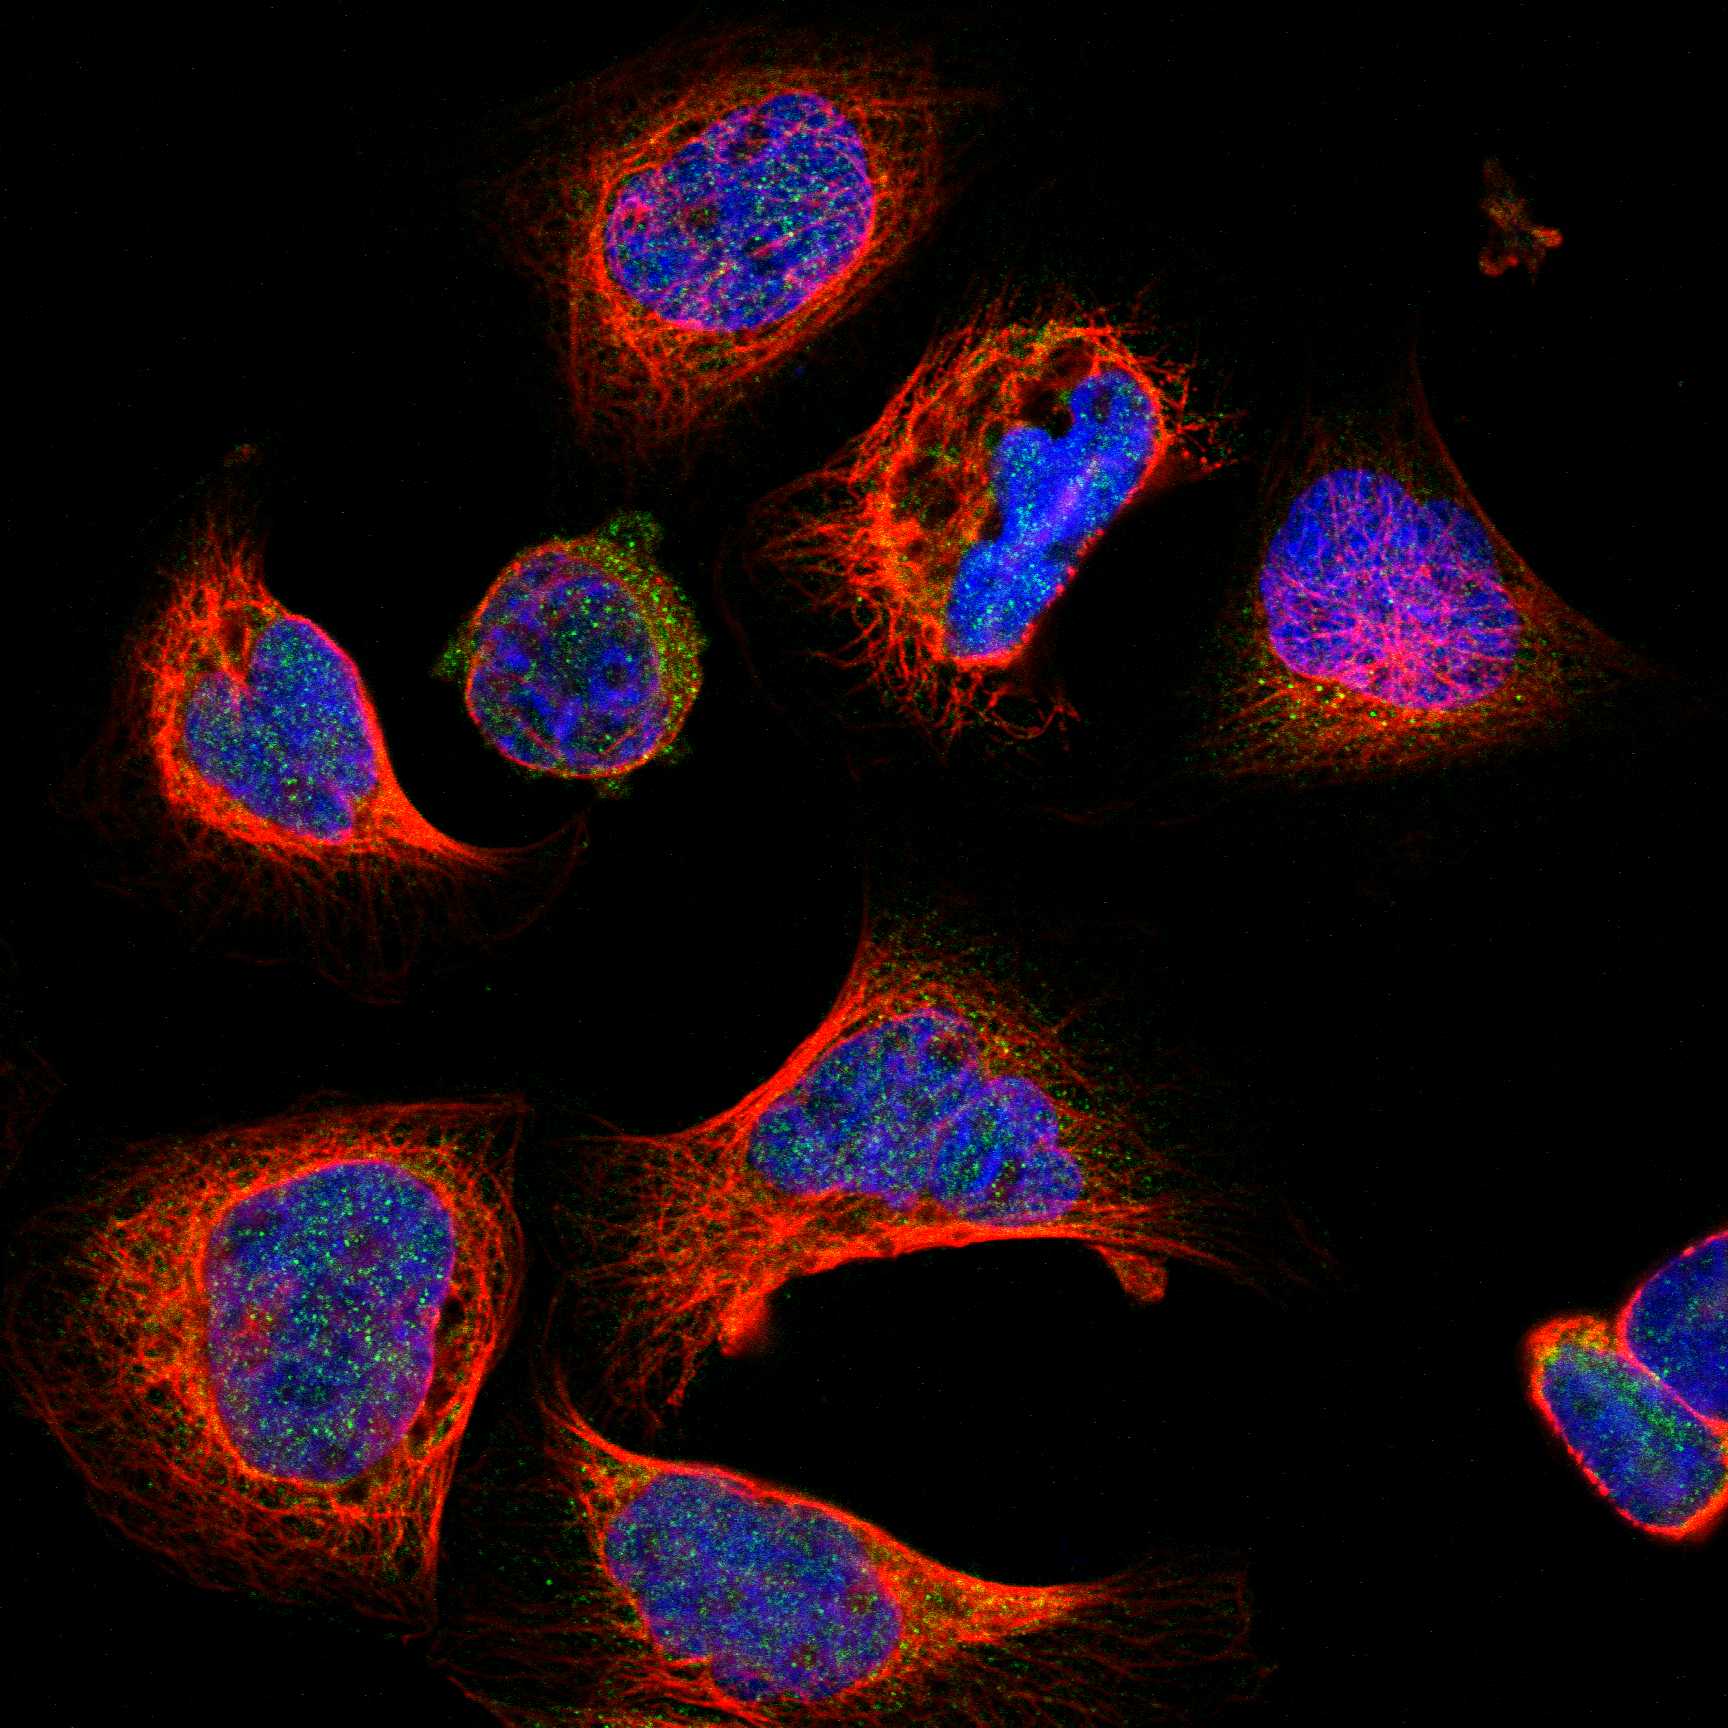
IF/ICC: should vesicles be the expected pattern?HPA lists vesicles as an uncertain ICC/IF location, and HPA010926 has Uncertain ICC validation (HPA: subcellular; antibodies). Use the separate IF/ICC guide for that application; the vesicle observation does not replace the membranous paraffin IHC expectation (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No stain in an expected positive cell population.The run may have failed, or the relevant cells may be absent from the section (general IHC practice). HPA reports High staining in bronchial respiratory epithelial cells (HPA: bronchus).Confirm the cells in the section, inspect the run control, and review the antibody dilution, retrieval and detection steps using the antibody’s IHC instructions (general IHC practice).
Nuclear signal overwhelms cell borders.Predominant nuclear localization conflicts with ALCAM membrane topology and HPA tissue staining (UniProt Q13740 topology; HPA: tissue IHC).Compare with a reagent control and check counterstain and detection settings; score only convincing cell associated staining in the expected compartment (general IHC practice).
Strong color appears in an HPA not detected cell type.Cross reactivity or endogenous detection activity is possible (general IHC practice); HPA reports adipocytes and cardiomyocytes as Not detected (HPA: tissue IHC).Identify the stained cells, compare a control without primary antibody, and check the detection system’s endogenous activity blocking step (general IHC practice).
The whole section has diffuse chromogen.Broad background can obscure the membranous profile reported by HPA (HPA: tissue IHC); insufficient washing or excessive development can contribute (general IHC practice).Inspect a reagent control, then review blocking, washing and development time before interpreting cellular signal (general IHC practice).
The signal is weak in a named High population.HPA’s High label describes observed staining in that cell population; it does not guarantee equal intensity across specimens or runs (HPA: tissue IHC).Check tissue morphology and the run control, then review the catalog antibody’s IHC dilution and retrieval instructions (general IHC practice).
Tissue RNA and the stained cell location disagree.HPA reports medium RNA to protein consistency and notes that a secreted variant can separate their tissue locations (HPA: reliability description).Interpret the observed cells and compartment directly; avoid using RNA enrichment alone to call a paraffin section positive or negative (HPA: reliability description; general IHC practice).

Sample controls for ALCAM IHC & IF

🧪Run bronchus first: respiratory epithelial cells should stain (HPA: High in bronchus respiratory epithelial cells). Use adipose tissue as the negative comparison (HPA: Not detected in adipocytes); on the bronchus slide, assess morphologically identified cells outside the respiratory epithelium for absent signal as an internal negative, without assuming every other cell type is ALCAM-negative (HPA: bronchus row specifies respiratory epithelial cells only).
Positive control tissue: Bronchus (Respiratory epithelial cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ALCAM in A-431, U-251MG, U2OS, with annotated localisation: Vesicles (uncertain) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a rabbit immunoglobulin control matched to the primary antibody’s clonality and concentration (selected-SKU caption: rabbit primary; standard IHC practice); use ALCAM knockout material as a biological negative if available (standard IHC practice). Quench endogenous peroxidase and check bronchial mucus for nonspecific DAB signal (selected-SKU caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: The selected-SKU paraffin-section caption reports heat retrieval in EDTA at pH 8.0, but its fixative is unreported (selected-SKU caption: EDTA retrieval; fixative not stated). No target-specific fixation window or fixation effect is reported in the supplied evidence, and the caption does not establish fixation; the relative ease of frozen-section IHC or IF also cannot be determined from it (selected-SKU caption: paraffin section only). In bronchus, distinguish epithelial staining from mucus-associated background (HPA: High in respiratory epithelial cells; standard IHC practice). The selected A01788-1 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image A01788-1).

HPA tissue IHC evidence for ALCAM

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cerebellum Processes in granular layer High Protein (IHC) HPA →
Cervix Glandular cells High Protein (IHC) HPA →
Endometrium Glandular cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Lymph node Germinal center cells Not detected Protein (IHC) HPA →
Section 3

Advanced ALCAM IHC Tips

Use matched controls and compartment-aware scoring to troubleshoot ALCAM staining in paraffin-section chromogenic IHC (UniProt Q13740; standard IHC practice).

How should I optimize retrieval when ALCAM staining is weak in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A01788-1). The selected tissue image used this condition before overnight incubation at 4°C with 2 μg/ml primary antibody (datasheet A01788-1). Keep heating and cooling conditions identical across test and control sections, then adjust retrieval duration on matched sections if staining remains weak (standard IHC practice). Treat another buffer or pH as a fallback, and reject conditions that damage morphology or raise diffuse DAB background (standard IHC practice). Look for clearer membrane staining, the principal tissue pattern reported for ALCAM (HPA: tissue IHC profile).
Could fixation explain inconsistent ALCAM staining across paraffin blocks?
The selected tissue-IHC caption identifies a paraffin section but does not state its fixative, so ALCAM-specific fixation sensitivity is unknown (datasheet A01788-1). Record each block's fixative, fixation duration, processing history, and section age before comparing staining between blocks (standard IHC practice). Compare a variable block with a consistently stained reference block using the same retrieval, antibody incubation, detection, and DAB development conditions (standard IHC practice). If staining differs, assess morphology and control staining before attributing the difference to fixation; tissue expression patterns cannot establish a fixation effect (standard IHC practice; HPA: tissue IHC profile).
Should ALCAM appear only at cell borders in chromogenic IHC?
Prioritize distinct membrane staining when assessing tissue sections, because the reported tissue-IHC profile is predominantly membranous (HPA: tissue IHC profile). ALCAM has an extracellular region at residues 28–527 and a membrane-spanning segment at 528–549, supporting a cell-surface pattern (UniProt Q13740 topology). Some protein can be secreted, and ALCAM is also annotated at axons and dendrites, so staining outside a simple cell-border outline needs anatomical context (UniProt Q13740 localisation). Do not classify diffuse cytoplasmic DAB as specific from appearance alone; compare expected cells, adjacent compartments, and omission controls (standard IHC practice).
How might epitope location and ALCAM isoforms affect staining interpretation?
ALCAM has 4 annotated isoforms, while the supplied evidence does not map this antibody's epitope or establish its isoform coverage (UniProt Q13740 isoforms; datasheet A01788-1). The reference protein places residues 28–527 outside the cell and 550–583 in the cytoplasm (UniProt Q13740 topology). Its extracellular region contains 9 annotated glycosylation sites, but these annotations do not establish whether this antibody recognizes a glycosylation-sensitive epitope (UniProt Q13740 glycosylation; datasheet A01788-1). If samples disagree, obtain the antibody's epitope information and compare matched sections before assigning the difference to an isoform (standard IHC practice).
How can IF help investigate an ambiguous ALCAM IHC pattern?
Use IF as a complementary localization check, pairing ALCAM with a marker for the expected cell type in the specimen and including single-label controls (standard IF practice). Choose a fluorophore channel with low tissue autofluorescence and inspect unstained tissue in each channel before calling faint signal positive (standard IF practice). Set permeabilization according to the antibody's mapped epitope: extracellular accessibility and cytoplasmic access require different handling, but this antibody's epitope is unspecified (UniProt Q13740 topology; datasheet A01788-1). Vesicular localization has been reported with uncertain confidence, so isolated puncta need controls and should not overturn a convincing membrane pattern in tissue IHC (HPA: subcellular localisation; HPA: tissue IHC profile).
What should I check when DAB obscures ALCAM cell borders?
Compare a no-primary section with the stained section to identify secondary-reagent binding or chromogen deposition unrelated to the primary antibody (standard IHC practice). Include an endogenous peroxidase block in the chromogenic workflow and check whether residual signal tracks enzyme-rich or damaged areas (standard IHC practice). The selected image used 10% goat serum blocking and a peroxidase-conjugated secondary incubated for 30 minutes at 37°C; those details describe that image's method (datasheet A01788-1). If background persists, titrate primary concentration and DAB development on matched sections while preserving a clear membrane signal in the positive control (standard IHC practice; HPA: tissue IHC profile).
How should I quantify heterogeneous ALCAM staining in tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable tissue area before scoring, then apply the same membrane-staining rule to every section (standard IHC practice; HPA: tissue IHC profile). Report the percentage of positive target cells and, when intensity matters, an H-score from 0–300 using intensity categories 0–3 (standard IHC practice). For dispersed positive cells, density per mm² can supplement the percentage; normalize counts to the scored viable area and percentages to the eligible target-cell denominator (standard IHC practice). Keep retrieval, detection, DAB development, and scoring thresholds consistent across slides, and report stromal or vascular staining separately if it could confound the target population (standard IHC practice).
How can I distinguish true ALCAM staining from a tissue artefact?
Look for reproducible cell-associated membrane staining in an anatomically plausible population, such as respiratory epithelial cells, rather than relying on DAB intensity alone (HPA: High in bronchus respiratory epithelial cells; HPA: tissue IHC profile). Treat staining confined to section edges, necrotic regions, or areas positive in a no-primary control as suspect (standard IHC practice). Diffuse signal in an unexpected compartment needs independent support because the predominant tissue pattern is membranous, although secreted protein complicates strict RNA-to-protein comparisons (HPA: tissue IHC profile; HPA: reliability description). Check endogenous peroxidase blocking when brown signal persists without primary antibody, and compare morphology plus matched controls before calling a specimen positive (standard IHC practice).
Boster reagents

Best ALCAM / CD166 antigen IHC Antibodies

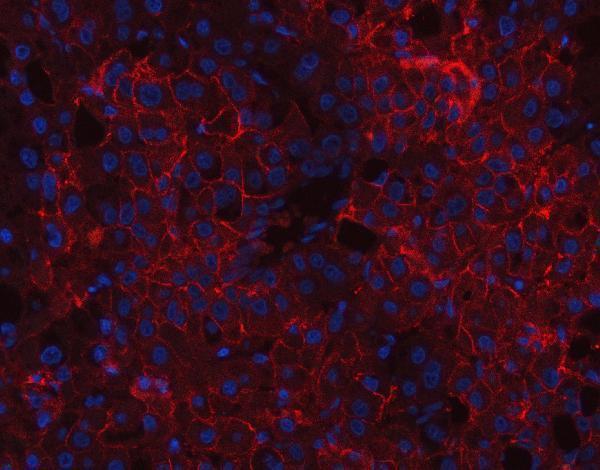
The catalog antibody has IHC images from human cancer and mouse lung paraffin sections, plus an IF image from human liver cancer paraffin sections (A01788-1 image captions).

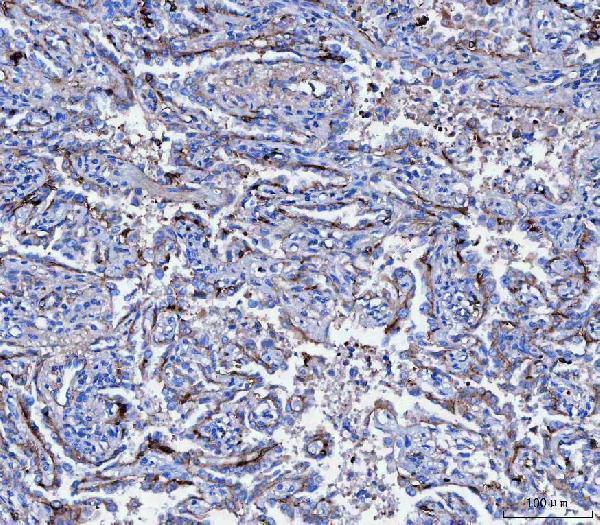
Real IHC data IHC analysis of CD166/ALCAM using anti-CD166/ALCAM antibody (A01788-1). CD166/ALCAM was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-CD166/ALCAM Antibody (A01788-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-CD166/ALCAM Antibody ®
Cat # A01788-1

A01788-1 will render with an IHC figure from a human breast cancer paraffin section; its other IHC captions show human lung cancer, human liver cancer, and mouse lung sections (A01788-1 IHC image captions). Its IF caption shows a human liver cancer paraffin section, and its application list includes IHC and IF (A01788-1 IF image caption; catalog applications).

Which to pick: For tissue IHC, choose A01788-1: its own caption documents EDTA retrieval at pH 8.0 and 2 μg/ml antibody on a paraffin section; the fixative is unreported (A01788-1 IHC image caption). For IF/ICC, A01788-1 has a tissue IF image, while M01788 is a rabbit monoclonal with ICC/IF listed but no image supplied (A01788-1 IF image caption; M01788 catalog applications, clone, and image alts). Both list human, mouse, and rat reactivity; A01788-1 additionally has a mouse lung IHC image, while the supplied captions show no rat sample (catalog reactivity; A01788-1 IHC image captions; M01788 image alts).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q13740 (CD166_HUMAN, CD166 antigen).
  2. Human Protein Atlas. ALCAM tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. ALCAM subcellular location (ICC-IF): Localized to vesicles..
  4. Human Protein Atlas. ALCAM antibody validation summary (2 antibodies).
  5. Comparative Proteomic Analysis of tPVAT during Ang II Infusion. Biomedicines 2021 — PMC8698607.
  6. Activated leukocyte cell adhesion molecule expression correlates with the WNT subgroup in medulloblastoma and is involved in regulating tumor cell proliferation and invasion. PloS one 2020 — PMC7714159.
  7. ALCAM (CD166) expression and serum levels in pancreatic cancer. PloS one 2012 — PMC3380038.
  8. Prognostic significance of ALCAM (CD166/MEMD) expression in cutaneous melanoma patients. Diagnostic pathology 2015 — PMC4489046.
  9. PubMed PMID:7760007 — UniProt-cited evidence.
  10. PubMed PMID:15496415 — UniProt-cited evidence.
  11. PubMed PMID:16641997 — UniProt-cited evidence.