This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Colon glandular cells and cerebral cortex neurons offer high-staining IHC references for ANKRD26 (HPA tissue IHC). This guide pairs those references with the catalog antibody’s 1:100–1:300 IHC dilution range (datasheet) and consistent paraffin-section fixation.

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic, often granular in tissue (HPA tissue IHC) | |
| Staining pattern | Glandular and neuronal cells: cytoplasmic, often granular (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep paraffin-section fixation consistent across samples (standard IHC practice; not target-specific) | |
| Caveat | Medium IHC–RNA concordance; external verification pending (HPA tissue IHC) | |
| Regulation | No expression induction annotated (UniProt) | |
| Isoform / epitope | 2 isoforms; check antibody epitope coverage (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by published ANKRD26 staining protocols for zebrafish paraffin sections (PMC12067082) and mouse brain and pituitary cryosections (PMC4601608).
| Sample | Paraffin-embedded human brain tissue; fixative not specified (datasheet A09289-1) |
| Fixation | Image fixative and duration unreported (datasheet A09289-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ANKRD26, 1:100-1:300 (datasheet A09289-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ANKRD26-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression, which often had a granular pattern. No signal in the no-primary control. |
ANKRD26 shows generally cytoplasmic, often granular staining in tissue IHC, with High staining reported in several glandular cell populations and cerebral cortex neuronal cells (HPA: tissue IHC). It has no annotated transmembrane segment (UniProt Q9UPS8 topology). Treat this as a reference pattern, not an absolute rule: HPA rates the tissue staining Approved, with medium consistency against RNA data and external verification pending (HPA: tissue IHC reliability).
| Granular cytoplasmic staining in appendix, colon or duodenum glandular cells. | This fits the reported tissue pattern; those cell populations are rated High (HPA: tissue IHC). Score the cells and compartment together, then compare intensity within the same staining run. Granularity can vary across cells, so an exact puncta count is not an established acceptance criterion (HPA: tissue IHC profile). |
| Strong staining confined to nuclei, cell borders or extracellular material. | These compartments do not match the reported general cytoplasmic pattern (HPA: tissue IHC). Review morphology, counterstain and detection controls before interpreting the signal as ANKRD26; HPA tissue IHC does not establish an expected nuclear or surface pattern. |
| Prominent staining of adipocytes or bone marrow hematopoietic cells. | Both are reported as Not detected (HPA: adipose tissue; bone marrow). Check whether the signal follows a cell population, tissue pigment or endogenous detection activity. Persistent staining may indicate cross-reactivity; a negative HPA observation alone cannot prove its cause. |
| Diffuse colour across cells and surrounding tissue, with little cellular contrast. | This is difficult to score as the reported granular cytoplasmic pattern (HPA: tissue IHC). Inspect a no-primary control and the distribution of precipitate; excess primary antibody, incomplete blocking or detection background are general IHC possibilities, not established ANKRD26-specific effects. |
| No interpretable signal in the glandular cells of an expected positive section. | Appendix, colon, duodenum and several other glandular populations are rated High (HPA: tissue IHC). First confirm that the expected cells are present and that the staining run worked. Then review antibody dilution, retrieval and detection as general IHC-P checks; HPA supplies no ANKRD26-specific retrieval condition here. |
| Tissue and cell selection | Use a reported High population as a positive reference and a reported Not detected population as a contrast (HPA: tissue IHC). Interpret each named cell type, rather than treating an entire organ as uniformly positive or negative. |
| Antibody evidence | HPA040654 and HPA041460 are IHC Approved (HPA: antibody validation). The tissue profile has medium agreement with RNA and awaits external verification (HPA: tissue IHC reliability), so unexpected staining merits an independent control. |
| Antigen retrieval | Retrieval can be optimised against positive and negative sections as general IHC-P practice. No target-specific retrieval condition or fixation sensitivity is supplied; neither the HPA staining levels nor UniProt topology establishes one. |
| IF/ICC expectation? | For the separate IF/ICC guide, HPA reports mainly Golgi localisation, with vesicles and cytosol also approved (HPA: subcellular ICC-IF). This supports an IF interpretation; it does not require organelle-level resolution in chromogenic tissue IHC. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive glandular cells have no visible stain. | The selected cells may be absent, or the staining run may have failed; the listed glandular populations are High in HPA tissue IHC. | Confirm cell identity on the counterstain and inspect a working positive control. Then review dilution, retrieval and detection as general IHC-P steps; do not infer a target-specific fixation effect. |
| Only nuclei appear strongly positive. | A nuclear-only result conflicts with the general cytoplasmic tissue profile (HPA: tissue IHC). | Check morphology and no-primary staining, then reassess with the IHC-validated antibody. Keep the result unassigned if the cytoplasmic reference pattern cannot be reproduced. |
| Reported negative cells stain prominently. | For example, adipocytes and bone marrow hematopoietic cells are Not detected (HPA: tissue IHC); cross-reactivity or endogenous detection activity is possible. | Compare matched positive tissue and a no-primary control. If the negative-cell signal persists, investigate specificity and endogenous enzyme activity before scoring it as ANKRD26. |
| Colour is widespread and masks cell boundaries. | Diffuse background prevents evaluation of the reported granular cytoplasmic pattern (HPA: tissue IHC). | Inspect no-primary and detection controls; adjust blocking, washes or antibody dilution using standard chromogenic IHC practice. Reassess only where cell morphology remains clear. |
| A section shows fewer positive cell types than expected. | HPA reports Low tissue specificity at RNA level but cell-specific IHC intensities (HPA: tissue IHC); whole-section appearance can obscure the relevant population. | Identify the named cell population before comparing results. Record its compartment and intensity separately from nearby cells, and use the HPA tissue observations as reference rather than a universal cutoff. |
| A Golgi-like IF image seems different from the tissue IHC slide. | Golgi, vesicle and cytosol assignments come from ICC-IF (HPA: subcellular); tissue IHC is described more broadly as cytoplasmic and often granular (HPA: tissue IHC). | Assess each application against its own reported pattern. Do not reject otherwise concordant chromogenic cytoplasmic staining solely because individual Golgi structures cannot be resolved. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
| Spleen | Cells in red pulp | Not detected | Protein (IHC) | HPA → |
Troubleshoot ANKRD26 staining in paraffin sections by checking retrieval, cellular pattern, controls and scoring before interpreting differences between samples.
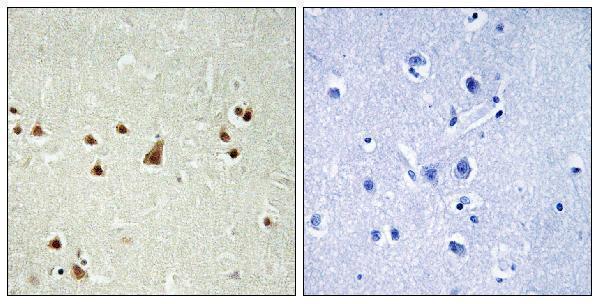
A09289-1 lists human and mouse reactivity and IHC/IF applications (catalog: applications/reactivity). Its IHC figure shows paraffin-embedded human brain (image caption); no IF figure is supplied (catalog: IF images).
A09289-1 will render with its own paraffin-embedded human brain IHC image and peptide-blocked comparison (image caption). It lists IHC, IF and ELISA applications and human and mouse reactivity (catalog: applications/reactivity).
Which to pick: For tissue IHC, choose A09289-1: its figure documents paraffin-embedded human brain (image caption), and the fixative is unreported (image caption). For IF, A09289-1 is listed at 1:50 (datasheet: IF dilution), but no IF image or ICC application is supplied (catalog: applications/IF images). For cross-species work, A09289-1 lists human and mouse reactivity (catalog: reactivity); its displayed IHC evidence is limited to human brain (image caption).