ANXA6 / Annexin A6 · IHC design guide

Design Immunohistochemistry for ANXA6

Plan paraffin-section ANXA6 IHC around cytoplasmic staining and cell-specific positive and negative controls (HPA tissue IHC). This guide covers fixation consistency, chromogenic detection, and scoring.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ANXA6 (IHC for ANXA6): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody M03735-1, validated IHC image, and IHC protocol steps
Printable ANXA6 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody M03735-1, controls and protocol steps. Open the full ANXA6 IHC guide →

ANXA6 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining across many tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M03735-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Esophagus+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet M03735-1); verify before use.
Caveat Some epithelial cell types are unstained (HPA tissue IHC)
Regulation Regulation not annotated (UniProt)
Isoform / epitope 2 isoforms; epitope consequences unreported (UniProt)
Section 1

Recommended ANXA6 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet M03735-1) with published ANXA6 staining in rat abdominal aorta (PMC9492406) and human breast cancer tissue (PMC8266800).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver tissue; fixative not specified (datasheet M03735-1)
FixationImage fixative and duration unreported (datasheet M03735-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M03735-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M03735-1)
Primary antibodyMouse monoclonal (clone 4C4) anti-ANXA6, 2 μg/ml (datasheet M03735-1)
Primary incubationOvernight at 4 °C (datasheet M03735-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet M03735-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultANXA6-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet M03735-1); neither published IHC excerpt specifies retrieval conditions (PMC9492406; PMC8266800).
Section 2

What Is the Expected ANXA6 Staining Pattern?

In paraffin-section IHC, expect mainly cytoplasmic ANXA6 staining, consistent with its cytoplasmic localization and lack of a transmembrane segment (UniProt P08133). HPA reports ubiquitous cytoplasmic expression, with high staining in selected cell populations rather than every cell in a tissue (HPA tissue IHC). Its tissue IHC reliability is Enhanced: staining agrees well with RNA expression data, pending external verification (HPA tissue IHC).

What am I looking at on my slide?
Clear cytoplasmic staining in adrenal glandular cells or pancreatic endocrine cells.This fits high staining in those specific populations (HPA tissue IHC: High). Score the identified cells and their cytoplasmic signal; an adjacent cell population need not have the same intensity.
Cytoplasmic staining in lung alveolar type II cells, placental endothelial cells, or smooth muscle cells.Each is a reported high-staining population (HPA tissue IHC: High). Cell identity matters when judging the result: a tissue-level label alone does not specify which cells should be strongly positive.
Predominantly nuclear staining, without a convincing cytoplasmic pattern.Treat this as discordant with the reported cytoplasmic IHC profile (HPA tissue IHC) and cytoplasmic localization (UniProt P08133). Review morphology and controls before interpreting it as ANXA6.
Strong signal in cells reported as not detected, such as esophageal squamous epithelial cells or bladder urothelial cells.The cell-level pattern conflicts with HPA tissue IHC. Consider nonspecific binding or endogenous detection activity, then compare with an appropriate negative detection control before assigning positivity.
Diffuse stain obscures cell borders, or no signal appears in a known high-staining population.Neither result permits a confident localization call. High-staining reference populations include adrenal glandular and pancreatic endocrine cells (HPA tissue IHC); assess controls and slide quality before scoring.
💡Expected ANXA6 appearanceCall a positive result when identifiable high-staining cells show clear cytoplasmic signal (HPA tissue IHC: High; UniProt P08133); strong nuclear-only signal or staining in an HPA not-detected cell population warrants review.
How each factor affects the staining
Cell population and tissue contextHPA describes ubiquitous cytoplasmic expression and low tissue RNA specificity, yet reports distinct high, low, and not-detected cell populations (HPA tissue IHC). Compare the same cell type, rather than treating an entire tissue as uniformly positive or negative.
IHC antibody evidenceHPA lists HPA002462 and HPA009650 as IHC Enhanced; CAB005077 is IHC Supported (HPA antibodies). These are validation summaries, not a claim that every antibody or preparation gives identical staining.
Topology and processingANXA6 has no annotated transmembrane segment or signal peptide; its annotated chain spans residues 2–673 (UniProt P08133). These facts support a cellular localization check but do not establish fixation sensitivity or an antigen-retrieval setting.
Isoforms and modificationsUniProt lists 2 isoforms and modified residues (UniProt P08133). The supplied record does not map an IHC antibody epitope to either isoform or a modified site, so staining differences cannot be assigned to either from these data.
IF/ICC Q: Where should signal appear?A: HPA reports mainly cytosolic staining, with an additional approved basal-body location (HPA subcellular ICC-IF). That additional IF observation does not make basal-body staining a requirement for chromogenic tissue IHC.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A reference section lacks cytoplasmic signal in adrenal glandular cells.The result conflicts with their reported high staining (HPA tissue IHC); this alone does not identify the failed IHC step.Confirm cell identity and tissue quality, then check the IHC-validated antibody, detection reagents, and run controls. Review retrieval and antibody dilution against the applicable IHC protocol as general workflow checks.
The slide has broad haze or precipitate instead of readable cell outlines.Diffuse background prevents assessment of the reported cytoplasmic pattern (HPA tissue IHC); nonspecific binding or detection deposits are possible general IHC causes.Inspect a negative detection control, reagent deposits, blocking, washing, and chromogen development. Adjust the implicated step, then reassess localization in a known high-staining cell population (HPA tissue IHC).
Only nuclei appear strongly stained.A nuclear-only result is discordant with ANXA6 cytoplasmic localization (UniProt P08133; HPA tissue IHC). The pattern alone cannot identify which reagent caused it.Check whether counterstain is being mistaken for chromogen, inspect a negative detection control, and repeat the localization assessment with an IHC-validated antibody.
Esophageal squamous epithelial cells stain strongly.HPA reports ANXA6 as not detected in those cells (HPA tissue IHC). Nonspecific primary binding or endogenous detection activity are possible general IHC explanations.Compare a control omitting the primary antibody and, where relevant, check endogenous enzyme blocking. Judge the cells separately from any neighboring positive population.
Some cells are intense while adjacent cells are faint or unstained.That can reflect cell-level variation: HPA reports high, low, and not-detected populations within its tissue survey (HPA tissue IHC). It is not by itself evidence of a processing failure.Identify and score each cell population separately; compare with the matching HPA cell-level entry before changing staining conditions.
Punctate cytoplasmic staining is interpreted as a required organelle pattern.UniProt reports ANXA6 in melanosome fractions, while HPA describes tissue IHC broadly as cytoplasmic (UniProt P08133; HPA tissue IHC). Neither source makes puncta a universal IHC criterion.First establish a specific cytoplasmic pattern in the relevant cells (HPA tissue IHC). Describe reproducible puncta separately, without assigning organelle identity from chromogenic staining alone.

Sample controls for ANXA6 IHC & IF

🧪Run lung first: alveolar type II cells should stain (HPA: High in lung alveolar type II cells). Use esophagus squamous epithelium as the negative tissue (HPA: Not detected in esophageal squamous epithelial cells); airspaces on the lung slide should show only background, while other lung cell types should not be assumed negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Esophagus (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ANXA6 in HAP1, Rh30, U2OS, ASC52telo, RPTEC/TERT1, hTERT-RPE1 (serum starved), with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched mouse IgG isotype controls, matching the primary’s subclass and clonality where known (selected-SKU caption: mouse primary antibody); use ANXA6 knockout material or peptide blocking, if available, as a biological specificity control. Block endogenous peroxidase for DAB detection and check lung pigment or autofluorescence when interpreting the positive tissue (selected-SKU caption: biotin-based DAB detection; standard IHC/IF practice).
⚠️Feasibility: The selected-SKU paraffin-section caption reports heat-mediated EDTA retrieval at pH 8.0, but does not establish that retrieval is required; its fixative is unreported (selected-SKU caption). A target-specific fixation window or fixation effect is unreported in the supplied evidence, and the caption does not establish fixation (selected-SKU caption). Paraffin IHC has a reported example, while the HPA cytosol ICC/IF images do not establish that IF or frozen sections are easier; assess lung pigment as a possible interpretation artefact (selected-SKU caption; HPA: cytosol approved; standard IHC/IF practice). The selected M03735-1 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image M03735-1).

HPA tissue IHC evidence for ANXA6

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Non-germinal center cells High Protein (IHC) HPA →
Lung Alveolar cells type II High Protein (IHC) HPA →
Lymph node Non-germinal center cells High Protein (IHC) HPA →
Pancreas Pancreatic endocrine cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Gallbladder Glandular cells Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Salivary gland Glandular cells Not detected Protein (IHC) HPA →
Small intestine Endocrine cells Not detected Protein (IHC) HPA →
Section 3

Advanced ANXA6 IHC Tips

Troubleshoot ANXA6 staining in paraffin-section IHC using the catalog antibody’s tissue image, reported localisation, and cell-specific expression as reference points.

How should I adjust retrieval when ANXA6 staining is weak in paraffin sections?
Start with heat-mediated retrieval in EDTA, pH 8.0, for paraffin sections (datasheet M03735-1). The catalog image used this retrieval before overnight incubation at 4°C with 2 μg/mL primary antibody, so check that the incubation and detection steps match before changing retrieval (datasheet M03735-1). If staining remains weak, compare a modestly longer heating interval with the original condition on adjacent sections, while keeping cooling and subsequent handling consistent (standard IHC practice). Judge any gain by clearer cytoplasmic staining in expected cells, rather than by stronger staining throughout the section (HPA: ubiquitous cytoplasmic expression; standard IHC practice).
Can fixation explain weak or uneven ANXA6 staining?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not report its fixative (datasheet M03735-1). Record the fixative, fixation duration, tissue thickness, and delay before fixation for each specimen, then compare sections processed under matched conditions (standard IHC practice). If staining varies across a section, inspect morphology and compare well-preserved central tissue with damaged or poorly preserved areas before changing antibody concentration (standard IHC practice). Keep retrieval at EDTA, pH 8.0 as the starting condition, and test any fixation-related hypothesis with matched specimens rather than inferring it from tissue expression or protein features (datasheet M03735-1; standard IHC practice).
What staining pattern should count as plausible ANXA6 in tissue?
Expect predominantly cytoplasmic signal: tissue IHC describes ubiquitous cytoplasmic expression, and subcellular imaging places ANXA6 mainly in the cytosol (HPA: tissue IHC profile; HPA: cytosol approved). An additional basal-body location is reported in subcellular imaging, but that observation alone does not establish a reliably resolvable punctum in chromogenic tissue sections (HPA: basal body approved; standard IHC practice). UniProt also lists cytoplasm and identification in melanosome fractions, without a transmembrane segment (UniProt P08133: subcellular location and topology). Score staining within intact cell boundaries alongside the counterstain; treat isolated nuclear, extracellular, or section-edge color as a reason to inspect specificity and tissue quality (standard IHC practice).
Could isoforms or epitope accessibility change the IHC pattern?
ANXA6 has 2 annotated isoforms, but the supplied antibody caption does not define its epitope or establish isoform selectivity (UniProt P08133: isoforms; datasheet M03735-1). The record also lists modified residues, including phosphoserine at position 13 and phosphotyrosine at position 30; their effect on this antibody cannot be inferred without epitope information (UniProt P08133: modified residues; datasheet M03735-1). Keep retrieval and primary incubation matched when comparing samples, so processing differences do not masquerade as biological variation (standard IHC practice). If an isoform-specific conclusion matters, obtain epitope or validation evidence before assigning a staining difference to either isoform (standard IHC practice).
How can IF help investigate an ambiguous IHC pattern?
Use IF/ICC as a separate localisation check, pairing ANXA6 with a marker for the cell population being examined; reported high-expression examples include alveolar type II cells and placental endothelial cells (HPA: high in lung alveolar type II cells and placental endothelial cells). Choose spectrally separated fluorophores and inspect unstained tissue for autofluorescence before interpreting overlap (standard IF practice). ANXA6 is mainly cytosolic and has no transmembrane segment, so permeabilisation should permit antibody access to an intracellular epitope, subject to the antibody’s unknown epitope position (HPA: cytosol approved; UniProt P08133: topology; standard IF practice). Compare localisation with the chromogenic section without transferring its retrieval, fixation, or antibody concentration to IF as a validated protocol (datasheet M03735-1; standard IF practice).
How do I reduce diffuse brown staining without losing ANXA6 signal?
First distinguish cellular cytoplasmic color from diffuse deposits, damaged tissue, and staining that persists in a no-primary control (HPA: ubiquitous cytoplasmic expression; standard IHC practice). The catalog tissue image used 10% goat serum blocking, 2 μg/mL primary antibody overnight at 4°C, a biotinylated secondary, and DAB development (datasheet M03735-1). Check peroxidase blocking and shorten DAB development if the no-primary control or tissue background is brown; these are general chromogenic controls, not ANXA6-specific findings (standard IHC practice). If background remains high, titrate the primary downward in matched sections and retain the lowest concentration that preserves interpretable cytoplasmic signal (standard IHC practice; HPA: tissue IHC profile).
How should I quantify ANXA6 IHC across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define cell populations and regions before scoring, then record the percentage of positive cells and staining intensity within intact cytoplasm (standard IHC practice; HPA: ubiquitous cytoplasmic expression). For an H-score, multiply each intensity category by its percentage of cells and sum the products, yielding a conventional 0–300 range (standard IHC practice). Normalise positive-cell counts to the number of evaluable cells in the same population, or report positive-cell density per mm² of evaluable tissue when area is the sampling unit (standard IHC practice). Keep section processing, imaging, threshold, and exclusion rules constant, and report cell-type scores separately when a sample mixes populations with different baseline expression (standard IHC practice; HPA: cell-specific tissue IHC levels).
What makes an apparent ANXA6-positive section convincing?
A convincing result places signal in intact cytoplasm and in an identifiable cell population, with limited staining in the no-primary control (HPA: ubiquitous cytoplasmic expression; standard IHC practice). High staining in pancreatic endocrine cells or smooth muscle cells is compatible with the tissue profile, whereas assigning strong signal to gallbladder glandular cells warrants closer review because that population is reported as not detected (HPA: high in pancreatic endocrine and smooth muscle cells; HPA: not detected in gallbladder glandular cells). Inspect section edges and necrotic areas for nonspecific color, and check endogenous peroxidase with the appropriate control (standard IHC practice). Interpret an unexpected nuclear-only or extracellular pattern cautiously against the mainly cytosolic localisation evidence (HPA: cytosol approved; standard IHC practice).
Boster reagents

Best ANXA6 / Annexin A6 IHC Antibodies

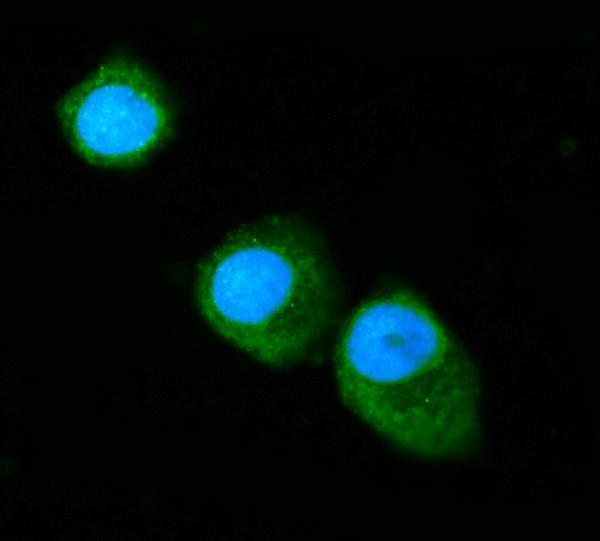
ANXA6 antibodies have IHC images from paraffin-embedded human, mouse, and rat tissues (catalog IHC captions); one also has IF/ICC data in T-47D cells (M03735-1 IF caption).

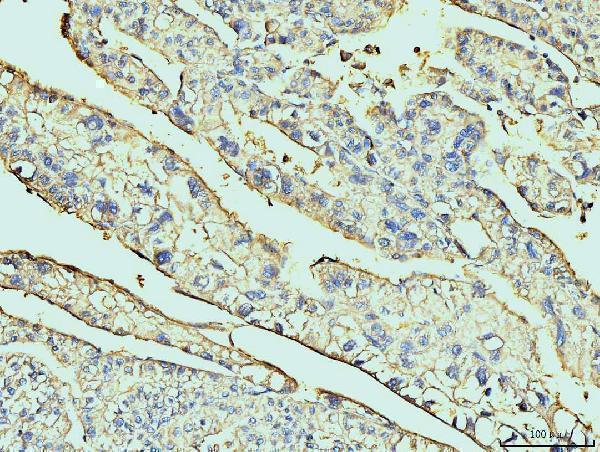
Real IHC data IHC analysis of Annexin VI using anti-Annexin VI antibody (M03735-1). Annexin VI was detected in a paraffin-embedded section of human liver tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml mouse anti-Annexin VI Antibody (M03735-1) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-Annexin VI Antibody ® (monoclonal, 4C4)
Cat # M03735-1
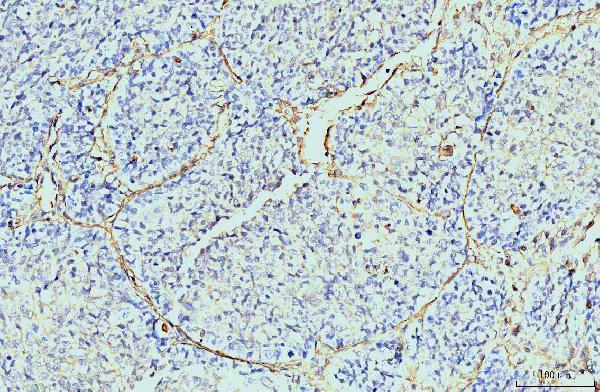
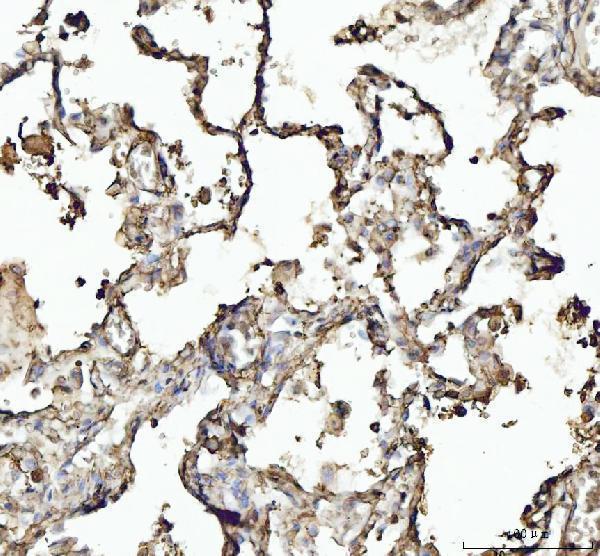
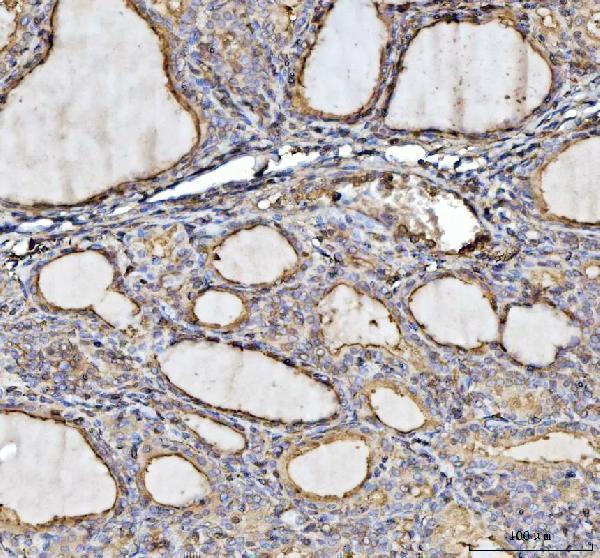
Real IHC data IHC analysis of Annexin VI/ANXA6 using anti-Annexin VI/ANXA6 antibody (A03735). Annexin VI/ANXA6 was detected in a paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Annexin VI/ANXA6 Antibody (A03735) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Annexin VI/ANXA6 Antibody ®
Cat # A03735

A03735 shows IHC staining in human lung and thyroid cancer, mouse tissue, and rat colon (A03735 IHC captions). M03735-1 shows IHC staining in human liver, lung cancer, renal clear cell carcinoma, and mouse pancreas, plus IF/ICC staining in T-47D cells (M03735-1 IHC and IF captions).

Which to pick: For tissue IHC, A03735 is a rabbit polyclonal with paraffin-section images from human, mouse, and rat; M03735-1 is a mouse monoclonal (4C4) with paraffin-section images from human and mouse (catalog host and clone; respective IHC captions). For IF/ICC, choose M03735-1: both applications are listed and its IF image shows staining in T-47D cells (catalog applications; M03735-1 IF caption). For cross-species IHC, A03735 has image evidence in all three listed species, while M03735-1 lists rat reactivity without a rat IHC image; the paraffin-section captions do not report the fixative (catalog reactivity; respective IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P08133 (ANXA6_HUMAN, Annexin A6).
  2. Human Protein Atlas. ANXA6 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. ANXA6 subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the basal body..
  4. Human Protein Atlas. ANXA6 antibody validation summary (4 antibodies).
  5. EZH2 Regulates ANXA6 Expression via H3K27me3 and Is Involved in Angiotensin II-Induced Vascular Smooth Muscle Cell Senescence. Oxidative medicine and cellular longevity 2022 — PMC9492406.
  6. SUMOylation of annexin A6 retards cell migration and tumor growth by suppressing RHOU/AKT1-involved EMT in hepatocellular carcinoma. Cell communication and signaling : CCS 2024 — PMC10986105.
  7. Breast Cancer Stem Cell-Derived ANXA6-Containing Exosomes Sustain Paclitaxel Resistance and Cancer Aggressiveness in Breast Cancer. Frontiers in cell and developmental biology 2021 — PMC8523856.
  8. Exosomal annexin A6 induces gemcitabine resistance by inhibiting ubiquitination and degradation of EGFR in triple-negative breast cancer. Cell death & disease 2021 — PMC8266800.
  9. PubMed PMID:3258820 — UniProt-cited evidence.
  10. PubMed PMID:2963335 — UniProt-cited evidence.
  11. PubMed PMID:2528541 — UniProt-cited evidence.