This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan APIP staining in paraffin sections using the reported nuclear and cytoplasmic tissue pattern (HPA tissue IHC). Use high-staining glandular cells as positive controls and score each cell type separately (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear and cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Variable nuclear and cytoplasmic staining across tissues (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Cerebellum+4 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining varies by tissue and cell type (HPA tissue IHC) | |
| Regulation | Isoform 2 is expressed at lower levels (UniProt) | |
| Isoform / epitope | Two isoforms; their epitope coverage is unknown (UniProt) |
The catalog antibody’s IHC-P protocol appears alongside a published APIP protocol for HCC paraffin sections (PMC12541992).
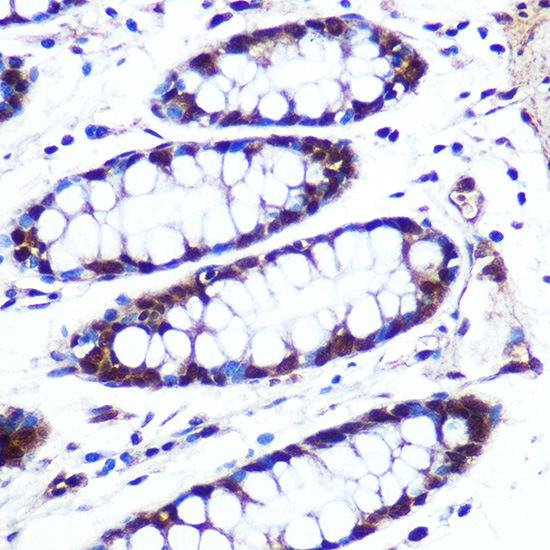
| Sample | Paraffin-embedded human colon tissue; fixative not specified (datasheet A09029) |
| Fixation | Image fixative and duration unreported (datasheet A09029); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-APIP, 1:50-1:200 (datasheet A09029) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | APIP-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Nuclear and cytoplasmic expression at variable levels in several different tissue types. No signal in the no-primary control. |
APIP should stain glandular cells in several tissues, with high IHC staining reported in colon, pancreas, stomach and other listed glands (HPA: tissue IHC). Nuclear and cytoplasmic staining is reported across tissues (HPA: Approved; medium consistency with RNA). Cytoplasmic localization is annotated by UniProt; APIP has no transmembrane segment or signal peptide (UniProt Q96GX9).
| Glandular cells show distinct nuclear and cytoplasmic chromogen in a positive tissue. | This fits the variable nuclear and cytoplasmic IHC profile (HPA: tissue IHC). Compare cells within the section: HPA reports High staining in colon glandular cells and pancreatic exocrine glandular cells (HPA: tissue IHC). |
| Staining is confined to cell borders or extracellular material, with no convincing intracellular signal. | Recheck specificity and section quality. The reported IHC pattern is nuclear and cytoplasmic (HPA: tissue IHC); UniProt lists cytoplasm and no transmembrane segment or signal peptide (UniProt Q96GX9). A border-only pattern is therefore unsupported. |
| Strong staining appears chiefly in cells outside the expected positive population. | Treat it as a possible specificity or detection problem, then compare morphology and a no-primary control. For example, HPA reports high staining in colon glandular cells but no detection in cerebellar granular-layer cells (HPA: tissue IHC). These observations are cell-specific. |
| Chromogen spreads uniformly across tissue, including spaces between cells. | Diffuse staining obscures the reported intracellular pattern (HPA: tissue IHC). Review background and detection controls before scoring APIP; broad color alone cannot establish expression in a particular cell type (general IHC interpretation). |
| No signal is seen in the expected positive glandular cells. | First verify the tissue and cell population: colon glandular cells and pancreatic exocrine glandular cells are reported High (HPA: tissue IHC). An absent result calls for checking antibody, detection and run controls; it does not alone establish absent APIP. |
| Tissue and cell selection | HPA reports High staining in glandular cells of adrenal gland, colon, gallbladder, prostate, salivary gland, small intestine and stomach, plus pancreatic exocrine cells (HPA: tissue IHC). Select and score the specified cells, rather than treating an entire organ as uniformly positive. |
| Interpretation of low or undetected cells | HPA lists low staining in thyroid glandular cells and no detection in cervix glandular cells (HPA: tissue IHC). These are observed cell-level results, not proof that every cell or section from those organs must be negative. |
| Compartment and topology | Tissue IHC describes variable nuclear and cytoplasmic expression (HPA: tissue IHC), while UniProt annotates cytoplasm and no transmembrane segment or signal peptide (UniProt Q96GX9). Use the tissue IHC observation for slide scoring; investigate a solely membranous pattern. |
| Isoforms and protein processing | Isoform 1 is ubiquitous; isoform 2 is lower and detected in selected tissues (UniProt Q96GX9). UniProt annotates a single 1–242 chain and no signal peptide or propeptide (UniProt Q96GX9). Antibody recognition of each isoform is unspecified here. |
| Validation and IF/ICC applicability | Q: Should IF/ICC match the tissue IHC result? A: HPA reports mainly nucleoplasm plus cytosol in ICC-IF (HPA: subcellular). Its tissue IHC rating is Approved with medium RNA consistency (HPA: tissue IHC); HPA021188 has Uncertain ICC validation (HPA: antibodies). |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive-control glandular cells have no chromogen. | The expected cell population may be missing, or an IHC reagent or detection step may have failed; absent color alone cannot identify which (general IHC practice). | Confirm the cells on the section, then review the antibody and detection run controls. Use a reported high-staining population such as colon glandular cells (HPA: tissue IHC). |
| All cells stain similarly, including a population expected to be undetected. | Nonspecific binding or detection background may mask cell-specific staining (general IHC practice). HPA reports no detection in cerebellar granular-layer cells (HPA: tissue IHC). | Compare a no-primary control and assess background before interpreting the section. Keep the HPA comparison tied to the named cell population, not the whole cerebellum (HPA: tissue IHC). |
| The signal appears only at plasma membranes. | A compartment mismatch raises concern for nonspecific staining or misidentified morphology (general IHC interpretation); APIP has no annotated transmembrane segment (UniProt Q96GX9). | Re-examine the counterstained cell boundaries and compare the positive control. Score nuclear and cytoplasmic intracellular signal against the reported IHC profile (HPA: tissue IHC). |
| A negative-looking area is interpreted as a failed APIP stain. | The sampled cells may normally have low or undetected IHC staining: HPA reports low signal in cerebral-cortex glia and no detection in ovarian stroma cells (HPA: tissue IHC). | Identify the exact cell type, then check a reported high-staining glandular population in the same run (HPA: tissue IHC). Do not infer assay failure from one low-staining population. |
| Nuclear staining is rejected because the UniProt location says cytoplasm. | The records describe different evidence: UniProt annotates cytoplasm (UniProt Q96GX9), and HPA observes variable nuclear and cytoplasmic staining in tissue IHC (HPA: tissue IHC). | Record nuclear and cytoplasmic compartments separately, and judge the pattern with tissue morphology and controls. Do not discard nuclear staining solely from the UniProt annotation. |
| An IF/ICC image is used to validate an IHC section directly. | ICC-IF localization and antibody validation do not automatically transfer to tissue IHC; HPA021188 is IHC Approved but ICC Uncertain (HPA: antibodies). | Interpret the paraffin-section result against HPA tissue IHC and its cell-level controls (HPA: tissue IHC). Use the ICC-IF nucleoplasm and cytosol result only as context (HPA: subcellular). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Pancreas | Exocrine glandular cells | High | Protein (IHC) | HPA → |
| Prostate | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot APIP staining by checking retrieval, compartment, cell type and controls before comparing signal across sections.
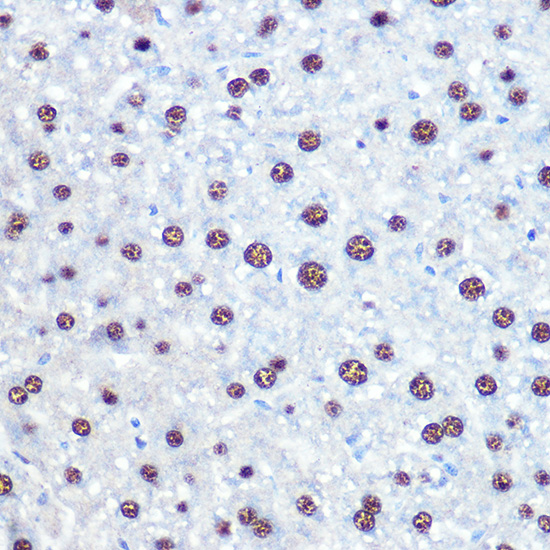
A09029 has IHC images from paraffin sections of human colon and mouse liver; no IF image is supplied (A09029 IHC image captions; catalog IF images).
A09029 is listed for IHC and has staining images from paraffin sections of human colon and mouse liver (A09029 catalog applications; IHC image captions). Its listed reactivity is Human, Mouse and Rat, while the supplied IHC images show human and mouse specimens (A09029 catalog reactivity; IHC image captions).
Which to pick: For tissue IHC, choose A09029, a rabbit polyclonal antibody whose captions show paraffin-section staining at 1:100 after microwave retrieval in 10 mM PBS at pH 7.2; the fixative is unreported (A09029 catalog host; IHC image captions). For IF/ICC, A09029 has no listed IF application or IF image (A09029 catalog applications; IF images). For cross-species work, A09029 lists Human, Mouse and Rat reactivity, with IHC images supplied for human and mouse specimens (A09029 catalog reactivity; IHC image captions).