APOBEC3C / DNA dC->dU-editing enzyme APOBEC-3C · IHC design guide

Design Immunohistochemistry for APOBEC3C

Plan chromogenic APOBEC3C IHC in paraffin sections using high-staining appendix lymphoid tissue and undetected adipocytes as reference controls (HPA tissue IHC). The guide covers the catalog antibody's IHC-P workflow and assessment of cytoplasmic and membranous staining (datasheet A07527-1; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for APOBEC3C (IHC for APOBEC3C): expected localisation Tissue staining: cytoplasmic/membranous (HPA tissue IHC); nucleus annotated (UniProt), antibody A07527-1, validated IHC image, and IHC protocol steps
Printable APOBEC3C IHC protocol sheet — expected localisation Tissue staining: cytoplasmic/membranous (HPA tissue IHC); nucleus annotated (UniProt), antibody A07527-1, controls and protocol steps. Open the full APOBEC3C IHC guide →

APOBEC3C Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Tissue staining: cytoplasmic/membranous (HPA tissue IHC); nucleus annotated (UniProt)
Staining pattern Cytoplasmic/membranous; high in appendix lymphoid tissue (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A07527-1)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining has medium concordance with RNA expression (HPA tissue IHC)
Regulation Expression regulation unspecified (UniProt)
Isoform / epitope No annotated isoforms or processing; one 1–190 chain (UniProt)
Section 1

Recommended APOBEC3C IHC & IF Protocols

The catalog antibody uses EDTA pH 8.0 heat-mediated retrieval (datasheet A07527-1). The published protocols below describe pancreatic and lung FFPE specimens (PMC9232547; PMC12780011).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A07527-1)
FixationImage fixative and duration unreported (datasheet A07527-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A07527-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A07527-1)
Primary antibodyRabbit anti-APOBEC3C, 2-5 μg/ml (datasheet A07527-1)
Primary incubationOvernight at 4 °C (datasheet A07527-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A07527-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultAPOBEC3C-positive staining in lymphoid tissue of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 retrieval (datasheet A07527-1); for optimization, compare Tris-EDTA pH 9.0 for 10 min (PMC9232547).
Section 2

What Is the Expected APOBEC3C Staining Pattern?

In paraffin-section IHC, expect mainly cytoplasmic staining, sometimes with a membranous appearance, in selected lymphoid, glandular, endothelial and other tissue-specific cells (HPA: cytoplasmic and membranous expression; HPA: tissue IHC). Nuclear localisation is also reported, but it is not the dominant HPA tissue-IHC profile (UniProt Q9NRW3: nucleus and cytoplasm; HPA: tissue IHC). APOBEC3C has no transmembrane segment (UniProt Q9NRW3: topology). HPA rates the tissue staining Approved, with medium consistency against RNA expression (HPA: tissue IHC).

What am I looking at on my slide?
Distinct cytoplasmic staining in appendix lymphoid tissue or lymph-node germinal-center cells (HPA: High in both).This fits an HPA-observed positive-cell pattern; compare the stained cells with adjacent cells rather than treating every cell in the section as an expected positive (HPA: tissue IHC).
Cytoplasmic staining with a membranous outline in selected cells (HPA: tissue-IHC profile).The outline can fit HPA's observed appearance, but it does not establish APOBEC3C as a membrane-spanning protein (UniProt Q9NRW3: no transmembrane segment).
Staining confined to an unexpected compartment, with no matching cytoplasmic pattern in expected positive cells (HPA: tissue IHC).Question specificity or detection artefact and compare a validated positive section; nuclear localisation alone cannot be dismissed because UniProt also lists the nucleus (UniProt Q9NRW3: subcellular location).
Strong signal in adipocytes or bronchial respiratory epithelium (HPA: Not detected in those cells).Check cell identity and controls; signal may reflect cross-reactivity or endogenous detection activity, rather than the HPA-observed APOBEC3C pattern (HPA: tissue IHC; standard IHC practice).
Broad, low-contrast colour across cells and tissue spaces (standard IHC practice).Diffuse background is hard to score as cell-specific staining; inspect the no-primary control and distinguish cellular signal from nonspecific chromogen deposition (standard IHC practice).
💡Expected APOBEC3C appearanceCall positive when defined cells show clear cytoplasmic staining, with possible membranous appearance, in an HPA High population such as epididymal glandular cells; indiscriminate staining of tissue spaces or HPA Not detected cells is suspect (HPA: tissue IHC; standard IHC practice).
How each factor affects the staining
Positive-cell selection (HPA: tissue IHC)HPA rates colon endothelial cells, kidney glomerular cells and placental trophoblastic cells High; select and score the named cell population within each tissue (HPA: High).
Negative-cell comparison (HPA: tissue IHC)Adipocytes, heart cardiomyocytes and fallopian-tube glandular cells are Not detected in the supplied HPA IHC record; use their cell-level pattern as a comparison, not a whole-organ claim (HPA: Not detected).
Compartment and topology (HPA: tissue IHC; UniProt Q9NRW3)HPA reports cytoplasmic and membranous tissue staining; UniProt lists nucleus and cytoplasm and no transmembrane segment. Interpret a membrane-like rim as an observed staining pattern, not proof of membrane insertion (HPA: tissue IHC; UniProt Q9NRW3).
IHC validation (HPA: antibody records; HPA: tissue IHC)The IHC record is Approved for CAB033048, while overall tissue staining has medium consistency with RNA expression; an Approved result still merits cell-specific controls when a slide disagrees with the reference pattern (HPA: antibody records; HPA: tissue IHC).
IF/ICC Q&A: should IF show the same pattern? (HPA: subcellular; HPA: antibody records)HPA reports approved intermediate-filament localisation in ICC-IF images from PC-3 and U2OS; its ICC-approved antibody is HPA071523, distinct from the IHC-approved CAB033048. Evaluate IF within its own assay context (HPA: subcellular; HPA: antibody records).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in appendix lymphoid tissue or lymph-node germinal-center cells (HPA: High).The expected cell population may be absent from the examined field, or an IHC step may have failed (HPA: tissue IHC; standard IHC practice).Locate the named cells first; then check the catalog antibody's IHC-P instructions, positive-control slide and detection reagents before changing conditions (HPA: tissue IHC; standard IHC practice).
Only a sharp surface rim appears, without cytoplasmic staining in expected positive cells (HPA: tissue IHC).HPA allows a membranous appearance, but APOBEC3C has no transmembrane segment; an isolated rim needs verification (HPA: tissue IHC; UniProt Q9NRW3).Compare the rim with internal positive cells and a no-primary control; assess whether staining follows cells or section edges (HPA: tissue IHC; standard IHC practice).
Adipocytes or bronchial respiratory epithelial cells stain strongly (HPA: Not detected).The pattern conflicts with the supplied HPA cell-level observations and may arise from nonspecific primary binding or detection background (HPA: tissue IHC; standard IHC practice).Confirm the cell type and review no-primary and other assay controls; reassess antibody and detection conditions if background persists (standard IHC practice).
Diffuse chromogen obscures individual cells (standard IHC practice).Excess detection signal, incomplete blocking or insufficient washing can reduce contrast in chromogenic IHC (standard IHC practice).Check the no-primary control, blocking and wash steps; adjust detection or primary-antibody conditions using the applicable IHC-P instructions (standard IHC practice).
A slide shows mainly nuclear staining (UniProt Q9NRW3: nucleus; HPA: tissue IHC).Nuclear APOBEC3C is plausible by UniProt, although HPA's supplied tissue-IHC profile emphasizes cytoplasmic and membranous expression (UniProt Q9NRW3; HPA: tissue IHC).Record the nuclear pattern separately, compare an HPA High tissue and review controls before assigning the result to APOBEC3C (HPA: tissue IHC; standard IHC practice).
An ICC-IF image shows filaments while paraffin IHC looks cytoplasmic (HPA: subcellular; HPA: tissue IHC).The supplied HPA observations come from different assays and antibodies: HPA071523 is ICC Approved; CAB033048 is IHC Approved (HPA: antibody records).Judge the paraffin section against the HPA tissue-IHC cell and compartment profile, and use the ICC-IF filament report only as assay-specific context (HPA: tissue IHC; HPA: subcellular).

Sample controls for APOBEC3C IHC & IF

🧪Run appendix first and expect staining in its lymphoid tissue (HPA: High in appendix lymphoid tissue). Use adipose tissue adipocytes as the negative comparison (HPA: Not detected in adipocytes); on the appendix slide, assess internal background in cells without specific staining without assuming every non-lymphoid cell is negative (HPA: High in appendix lymphoid tissue).
Positive control tissue: Appendix (Lymphoid tissue, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show APOBEC3C in PC-3, U2OS, with annotated localisation: Intermediate filaments (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and matched rabbit IgG isotype controls, plus APOBEC3C knockout material or validated immunizing-peptide competition if available (caption: rabbit primary antibody; standard IHC control practice). Quench endogenous peroxidase and check background before HRP/DAB detection in the appendix section (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A07527-1 paraffin-section caption does not state the fixative (caption: fixative not stated). The caption uses heat-mediated EDTA retrieval at pH 8.0, but does not establish whether retrieval is required (caption: EDTA retrieval at pH 8.0). The supplied evidence does not establish whether frozen sections or IF are easier; localization should be checked carefully because UniProt lists nucleus and cytoplasm, whereas HPA ICC-IF reports intermediate filaments (UniProt Q9NRW3 subcellular; HPA: intermediate filaments).

HPA tissue IHC evidence for APOBEC3C

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Lymphoid tissue High Protein (IHC) HPA →
Colon Endothelial cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Kidney Cells in glomeruli High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced APOBEC3C IHC Tips

Troubleshoot APOBEC3C chromogenic staining in paraffin sections using the catalog antibody’s tissue image and cell-specific reference patterns (datasheet A07527-1; HPA tissue IHC).

How should I adjust retrieval when APOBEC3C staining is weak?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A07527-1). Keep heating and cooling conditions consistent across slides, and record them before changing retrieval conditions (standard IHC practice). The catalog image used 2 μg/ml primary antibody overnight at 4°C, so compare your incubation conditions before attributing weak staining to retrieval (datasheet A07527-1). If staining remains weak, test an alternative retrieval buffer on matched sections as a fallback, while retaining the EDTA condition for comparison (standard IHC practice). Judge improvement in identifiable cells rather than diffuse staining across the section (standard IHC practice).
Can fixation explain variable APOBEC3C staining between paraffin blocks?
Target-specific fixation sensitivity is unknown: the catalog tissue caption identifies a paraffin section but does not state its fixative (datasheet A07527-1). Record each block’s fixative and fixation duration, then compare matched sections processed with the same retrieval and detection conditions (standard IHC practice). Use the documented EDTA pH 8.0 retrieval as a shared starting condition when comparing blocks (datasheet A07527-1). Evaluate whether variation follows block history or occurs among cells within the same section, using morphology and a counterstain to identify preserved tissue (standard IHC practice). Do not infer fixation tolerance from the reported tissue distribution or protein topology (HPA tissue IHC; UniProt Q9NRW3 topology).
What APOBEC3C staining pattern should I expect in tissue sections?
Assess cytoplasmic staining first, while documenting nuclear and apparent membranous signal separately: UniProt lists nucleus and cytoplasm, whereas tissue IHC reports cytoplasmic and membranous expression (UniProt Q9NRW3 subcellular; HPA tissue IHC). APOBEC3C has no transmembrane segment, so an apparent membrane rim needs careful evaluation against cell boundaries and neighboring cytoplasm (UniProt Q9NRW3 topology). Use a counterstain and matched brightfield settings to decide which cell contains each DAB deposit (standard IHC practice). The separate cell-based IF record places signal at intermediate filaments, which offers context but does not establish a required pattern in paraffin sections (HPA subcellular). Report compartment-specific results rather than pooling them (standard IHC practice).
How can I investigate an unexpected APOBEC3C epitope pattern?
The record lists a 190-amino-acid chain, a deaminase domain at residues 29–138, and no annotated isoforms (UniProt Q9NRW3 processing, domains and isoforms). It also lists no glycosylation sites or modified residues, so those annotations alone do not explain variable staining (UniProt Q9NRW3 glycosylation and modified residues). The supplied catalog caption does not map the antibody epitope; avoid assigning a particular domain to its tissue signal (datasheet A07527-1). Compare staining in distinct cell populations with an independently supported assay or antibody when specificity is in doubt (standard IHC practice). Keep the same retrieval and detection settings during that comparison so processing differences do not obscure it (standard IHC practice).
How should I investigate APOBEC3C localisation by multiplex IF?
For a separate IF experiment, pair APOBEC3C with a marker identifying the expected cell population, such as germinal center cells in lymph node, which show high tissue-IHC staining (HPA tissue IHC). Choose fluorophores in channels with low measured tissue autofluorescence and include single-stain controls to assess spectral bleed-through (standard IF practice). UniProt places APOBEC3C in nucleus and cytoplasm and reports no transmembrane segment, so plan permeabilisation for intracellular access rather than assuming a cell-surface epitope (UniProt Q9NRW3 subcellular and topology). Because the antibody’s epitope location is not supplied, titrate permeabilisation and assess morphology before interpreting absent signal (datasheet A07527-1; standard IF practice). Treat the intermediate-filament IF pattern as a comparison point, not proof of tissue localisation (HPA subcellular).
What should I check when DAB background obscures APOBEC3C staining?
Inspect a no-primary control to assess signal from detection reagents, and check whether background concentrates at tissue edges or damaged areas (standard IHC practice). The catalog image used 10% goat serum blocking, a peroxidase-conjugated secondary and DAB detection; it does not establish which step causes background in another section (datasheet A07527-1). Include a peroxidase-blocking step and compare sections developed for the same DAB duration when investigating diffuse color (standard chromogenic IHC practice). Check secondary-antibody specificity and wash conditions while keeping the primary concentration documented at 2 μg/ml as an initial reference (datasheet A07527-1; standard IHC practice). Judge background against cell morphology before changing the interpretation of a stained compartment (standard IHC practice).
How should I score APOBEC3C across different cell populations? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because tissue-IHC observations differ among cell types and include cytoplasmic and membranous patterns (HPA tissue IHC). For each population, report percent positive cells and an intensity score of 0–3, or combine them as an H-score from 0–300 (standard IHC practice). For spatial comparisons, report positive-cell density per mm² of evaluable tissue and specify how that area was selected (standard IHC practice). Normalize comparisons to the number of eligible cells or evaluable tissue area, rather than whole-slide area containing empty space or damaged tissue (standard IHC practice). Keep retrieval, imaging and positivity thresholds consistent across groups (standard IHC practice).
How do I distinguish APOBEC3C staining from artefact?
Look for reproducible signal in identifiable cells: lymph-node germinal center cells and appendix lymphoid tissue have high reported staining, while adipocytes are reported as not detected (HPA tissue IHC). Interpret cytoplasmic or nuclear signal alongside the stated locations, and scrutinize a sharp surface-only rim because APOBEC3C has no transmembrane segment (UniProt Q9NRW3 subcellular and topology). Discount isolated edge staining, necrotic areas and deposits that persist in a no-primary control; assess endogenous peroxidase with an appropriate control (standard chromogenic IHC practice). The tissue antibody has Approved reliability with medium consistency against RNA data, so retain cell-level and orthogonal evidence when making a specific assignment (HPA tissue IHC). Document discordant compartments or cell types explicitly (standard IHC practice).
Boster reagents

Best APOBEC3C / DNA dC->dU-editing enzyme APOBEC-3C IHC Antibodies

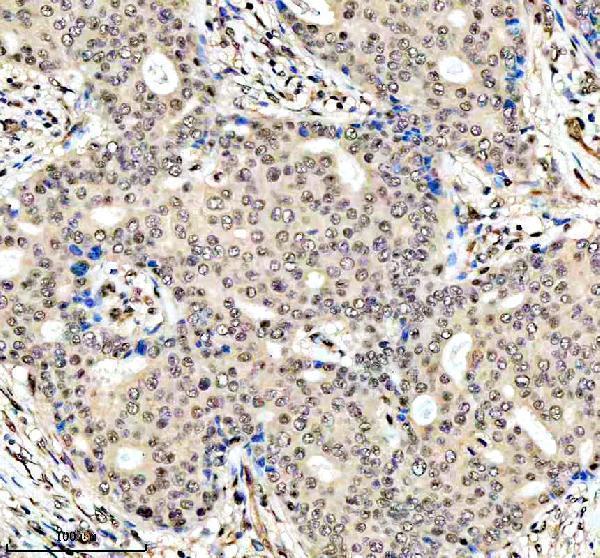
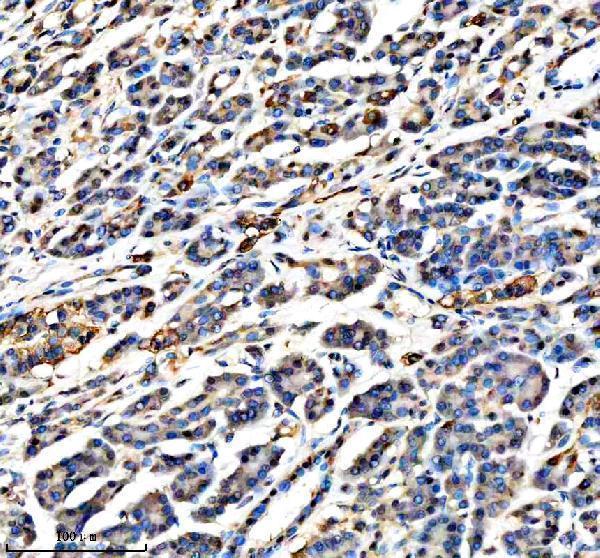
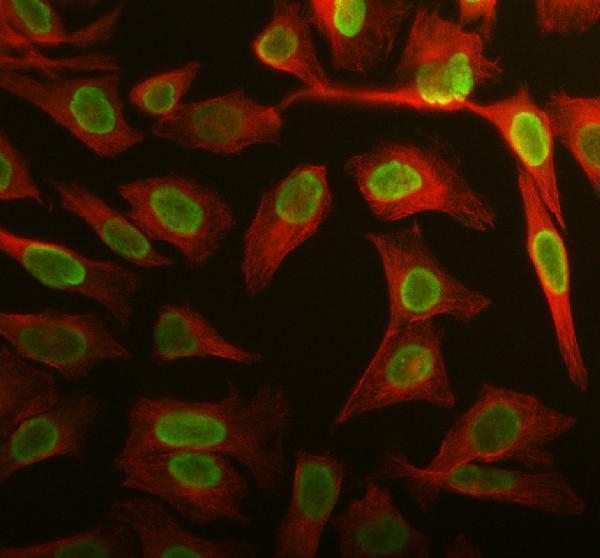
Anti-APOBEC3C A07527-1 has human paraffin-section IHC and HELA-cell IF images (IHC and IF captions); the catalog also lists Mouse and Rat reactivity (catalog reactivity).

Real IHC data IHC analysis of APOBEC3C using anti-APOBEC3C antibody (A07527-1). APOBEC3C was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-APOBEC3C Antibody (A07527-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-APOBEC3C Antibody ®
Cat # A07527-1

A07527-1 will render with IHC data from human breast cancer paraffin sections (IHC figure caption). The same SKU has IHC captions for human pancreas and stomach cancer sections and an IF caption for HELA cells (IHC and IF captions).

Which to pick: For tissue IHC, choose A07527-1: its caption documents paraffin sections, EDTA retrieval at pH 8.0, and 2 μg/ml primary antibody; the fixative is unreported (IHC figure caption). For IF/ICC, the same SKU has a HELA-cell example at 5 μg/ml (IF caption). For Mouse or Rat samples, A07527-1 lists reactivity with those species, but its supplied IHC and IF images show human material; clonality is unreported (catalog reactivity; IHC and IF captions; catalog clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NRW3 (ABC3C_HUMAN, DNA dC->dU-editing enzyme APOBEC-3C).
  2. Human Protein Atlas. APOBEC3C tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. APOBEC3C subcellular location (ICC-IF): Localized to the intermediate filaments..
  4. Human Protein Atlas. APOBEC3C antibody validation summary (2 antibodies).
  5. Aberrant APOBEC3C expression induces characteristic genomic instability in pancreatic ductal adenocarcinoma. Oncogenesis 2022 — PMC9232547.
  6. APOBEC3C coordinates DDX5 in R-loop resolution and dynamic control of Chk1-mediated stress-responsive circuitry as a prerequisite for gemcitabine resistance in p53-deficient cells. Cell death & disease 2026 — PMC12780011.
  7. An Integrated Immune-Related Bioinformatics Analysis in Glioma: Prognostic Signature's Identification and Multi-Omics Mechanisms' Exploration. Frontiers in genetics 2022 — PMC9114310.
  8. PubMed PMID:15461802 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:10591208 — UniProt-cited evidence.