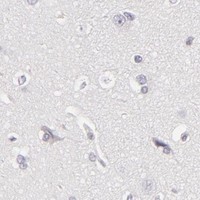
APOBEC3G / DNA dC->dU-editing enzyme APOBEC-3G · IHC design guide

Design Immunohistochemistry for APOBEC3G

Plan APOBEC3G paraffin IHC around cytoplasmic staining in tonsil and spleen (HPA tissue IHC). Start the IHC-validated antibody at 0.5–1 µg/mL (datasheet M00708) and interpret staining by cell type (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for APOBEC3G (IHC for APOBEC3G): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); a small nuclear pool is reported (UniProt), antibody M00708, validated IHC image, and IHC protocol steps
Printable APOBEC3G IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); a small nuclear pool is reported (UniProt), antibody M00708, controls and protocol steps. Open the full APOBEC3G IHC guide →

APOBEC3G Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); a small nuclear pool is reported (UniProt)
Staining pattern Cytoplasmic staining in several cell types, including immune cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M00708)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Positive cell types differ across lymphoid tissues (HPA tissue IHC)
Regulation Lymphoid tissue has enhanced RNA expression (HPA tissue RNA)
Isoform / epitope 2 isoforms (1, 3); epitope differences are unspecified (UniProt)
Section 1

Recommended APOBEC3G IHC & IF Protocols

The catalog antibody’s IHC-P protocol is complemented by published APOBEC3G IHC methods for ovarian carcinoma, cervical lesions, and rhesus macaque lymph node (PMC5026552; PMC9807366; PMC4418221).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human intestinal cancer tissue; fixative not specified (datasheet M00708)
FixationImage fixative and duration unreported (datasheet M00708); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M00708); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M00708)
Primary antibodyMouse monoclonal (clone 6C2) anti-APOBEC3G, 0.5-1μg/ml (datasheet M00708)
Primary incubationOvernight at 4 °C (datasheet M00708)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet M00708)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultAPOBEC3G-positive staining in lymphoid tissue of appendix (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in several tissues, including immune cells. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet: M00708); match each published retrieval method when reproducing its protocol (PMC5026552; PMC4418221).
Section 2

What Is the Expected APOBEC3G Staining Pattern?

APOBEC3G should stain mainly the cytoplasm, with a small nuclear fraction possible; it has no transmembrane segment (UniProt Q9HC16: subcellular location and topology). In paraffin sections, expect staining in selected lymphoid and other documented cell populations, rather than every cell in a positive tissue (HPA: cytoplasmic expression in several tissues, including immune cells; IHC reliability Enhanced, with medium consistency between staining and RNA data).

What am I looking at on my slide?
Cytoplasmic staining in lymph-node germinal-center cells or splenic red-pulp cells, with nearby cells differing in signal.This fits the reported medium staining in those specified populations (HPA: lymph node and spleen tissue IHC). Score the named cell population and compartment; a positive tissue need not stain uniformly (HPA: tissue IHC).
Predominantly nuclear staining, with little or no cytoplasmic signal.Review as a compartment mismatch: APOBEC3G is mainly cytoplasmic, although a small nuclear fraction is reported (UniProt Q9HC16: subcellular location). Check morphology and controls before calling nuclear-only staining specific.
Strong staining in adipocytes or bronchial respiratory epithelium.These specified cells were not detected by HPA tissue IHC (HPA: adipose tissue and bronchus). Unexpected signal raises concern for nonspecific antibody binding or endogenous chromogen activity; inspect the negative-reagent control (general IHC practice).
Diffuse color across cells, extracellular spaces, and tissue edges.A pattern that does not follow cell boundaries is difficult to score as APOBEC3G. Review background, washes, detection reagents, and tissue pigmentation with appropriate controls (general chromogenic IHC practice).
No signal in the expected cells of a positive-control section.A blank control section cannot establish a true negative in the test specimen. Recheck tissue identity, antibody and detection steps, and assay controls (general IHC practice); HPA reports medium staining in splenic red-pulp cells (HPA: spleen tissue IHC).
💡Expected APOBEC3G appearanceCall a section positive when the expected cells show discernible, mainly cytoplasmic staining—typically medium in the listed HPA-positive populations; diffuse field-wide color or strong signal in HPA-undetected cell types warrants control review (HPA: tissue IHC; UniProt Q9HC16: subcellular location).
How each factor affects the staining
Cell population and specimen choiceHPA reports medium staining in lymph-node germinal-center cells, tonsillar non-germinal-center cells, splenic red-pulp cells, testicular Sertoli cells, and selected glandular cells (HPA: tissue IHC). Compare like cell populations when selecting a positive reference; neighboring cells are not interchangeable controls (general IHC practice).
Compartment and topologyAPOBEC3G is mainly cytoplasmic, can occur in P-bodies, and has a small nuclear fraction; it has no transmembrane segment (UniProt Q9HC16: location and topology). Interpret staining by its intracellular distribution, without expecting a membrane-rim pattern.
Strength and validation of the tissue evidenceHPA calls the tissue-IHC reliability Enhanced but describes medium consistency between antibody staining and RNA expression; HPA001812 has Enhanced IHC validation (HPA: tissue IHC and antibody record). Use the observed cell-level pattern as a reference, with that consistency limit in mind.
IF/ICC Q&A: should its pattern match IHC?IF/ICC can show cytosol and nucleoplasm, but HPA marks both locations uncertain and cautions that the finding uses antibodies targeting proteins from multiple genes (HPA: subcellular ICC-IF). Treat it as qualified localization evidence; this IHC section supplies no IF/ICC protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive-control spleen section is blank.The assay may have failed, the sampled field may lack the relevant cells, or the tissue may be unsuitable for comparison (general IHC practice).Locate red-pulp cells and verify the antibody, detection reagents, and control run before interpreting test sections; HPA reports medium staining there (HPA: spleen tissue IHC).
Only nuclei stain in an otherwise expected population.A small nuclear fraction is possible, but a predominantly nuclear-only result differs from the mainly cytoplasmic reference (UniProt Q9HC16: subcellular location).Compare cytoplasm and nuclei in the same cells, then review negative-reagent controls and antibody specificity (general IHC practice). Avoid treating any nuclear signal alone as proof of an artefact.
Brown color is widespread or follows tissue edges.Diffuse deposition may reflect background from the detection workflow rather than a cell-restricted pattern (general chromogenic IHC practice).Check negative-reagent controls, endogenous detection activity, blocking, washes, and chromogen development (general IHC practice). Score only cellular signal that remains distinguishable from background.
Unexpectedly strong staining appears in adipocytes or bronchial respiratory epithelial cells.HPA reports these cell types as not detected; nonspecific binding or endogenous activity is possible (HPA: adipose tissue and bronchus; general IHC practice).Review cell identity and control sections; compare signal with an expected positive population before assigning it to APOBEC3G (HPA: tissue IHC; general IHC practice).
A glandular area looks negative despite a positive tissue label.HPA reports staining for particular glandular cells in fallopian tube, prostate, and seminal vesicle, while cervical glandular cells were not detected (HPA: tissue IHC). Tissue labels alone can conceal cell-level differences.Confirm the organ and cell population, then compare with the corresponding HPA cell-level observation. Record staining by cell type and compartment (HPA: tissue IHC; general IHC scoring practice).
An ICC-IF image seems more nuclear than the paraffin-section result.HPA's ICC-IF nucleoplasm and cytosol calls are uncertain and carry a multiple-gene antibody caution (HPA: subcellular ICC-IF). UniProt describes APOBEC3G as mainly cytoplasmic (UniProt Q9HC16: subcellular location).Interpret the IHC section against its own cell-level controls and the mainly cytoplasmic reference. Keep the qualified IF/ICC observation separate from the IHC scoring decision (HPA: tissue IHC and subcellular ICC-IF).

Sample controls for APOBEC3G IHC & IF

🧪Run lymph node first: germinal center cells should stain at the HPA Medium level (HPA: lymph node, germinal center cells, Medium). Use adipose tissue as the negative tissue; its adipocytes are listed as Not detected (HPA: adipose tissue, adipocytes, Not detected). On the positive slide, cells outside the germinal centers should show only counterstain or background in the negative-control sections; do not assume every such cell is APOBEC3G-negative (HPA: lymph node, germinal center cells, Medium; UniProt Q9HC16: expression in leukocytes).
Positive control tissue: Appendix (Lymphoid tissue, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show APOBEC3G in A-431, RT-4, U2OS, with annotated localisation: Nucleoplasm (uncertain), Cytosol (uncertain) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section and an isotype control matched to the mouse primary antibody’s IgG subclass and concentration (selected-SKU caption: mouse anti-APOBEC3G); use APOBEC3G-knockout material as a biological negative where available (standard IHC practice). Quench endogenous peroxidase in lymph node sections and check for endogenous biotin background if using the caption’s streptavidin–biotin detection system (selected-SKU caption: SABC with DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact M00708 tissue-IHC caption does not state the fixative (selected-SKU caption: fixative not stated). The caption uses heat retrieval in EDTA pH 8.0, but does not establish that retrieval is required; the supplied evidence does not establish that frozen sections or IF are easier (selected-SKU caption: EDTA pH 8.0; HPA subcellular: ICC-IF locations uncertain). In lymph node, endogenous peroxidase and biotin can produce background with chromogenic streptavidin–biotin detection, so interpret staining against the technical controls (selected-SKU caption: SABC with DAB; standard IHC practice).

HPA tissue IHC evidence for APOBEC3G

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Lymphoid tissue Medium Protein (IHC) HPA →
Fallopian tube Glandular cells Medium Protein (IHC) HPA →
Lymph node Germinal center cells Medium Protein (IHC) HPA →
Prostate Glandular cells Medium Protein (IHC) HPA →
Seminal vesicle Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced APOBEC3G IHC Tips

Troubleshoot APOBEC3G chromogenic staining in paraffin sections using the catalog antibody’s IHC conditions and cell type–specific controls.

How should I adjust retrieval when APOBEC3G staining is weak or uneven?
Start with heat-mediated EDTA pH 8.0 antigen retrieval for paraffin sections (datasheet M00708). The catalog image used this retrieval before overnight incubation at 4°C with 1 µg/mL primary antibody, so keep those conditions together for the first comparison (datasheet M00708). If staining remains weak, compare retrieval duration on adjacent sections while holding antibody concentration, detection and DAB development constant (standard IHC practice). Check tissue integrity and staining in the expected cell population before increasing retrieval intensity, because damaged sections and stronger background can make an apparent gain misleading (standard IHC practice; HPA: cytoplasmic expression in immune cells).
Can I attribute weak APOBEC3G staining to the tissue fixative?
The selected image identifies a paraffin-embedded section but does not report its fixative, so APOBEC3G-specific fixation sensitivity is unknown (datasheet M00708). Record the fixative and processing history for each specimen, then compare similarly processed sections before attributing a staining difference to biology (standard IHC practice). If preservation varies, assess morphology and staining in expected cells alongside the same EDTA pH 8.0 retrieval and 1 µg/mL primary condition (datasheet M00708; standard IHC practice). Do not infer a fixation effect from the tissue staining profile, phosphorylation sites or lack of a transmembrane segment; none establishes how this antibody’s epitope survives fixation (HPA: tissue IHC profile; UniProt Q9HC16: modified residues and topology).
Should nuclear or punctate staining count as APOBEC3G positivity?
Score cytoplasmic staining first: APOBEC3G is mainly cytoplasmic, with a smaller nuclear pool and reported P-body localisation (UniProt Q9HC16: subcellular location). Nuclear staining can be plausible, but the HPA nucleoplasm and cytosol assignments are uncertain because their antibody evidence may include proteins from multiple genes (HPA: subcellular). Compare each compartment with matched negative and secondary-only sections before assigning a separate nuclear score (standard IHC practice). For puncta, require a reproducible pattern within intact expected cells rather than isolated DAB deposits, and report punctate cytoplasmic signal separately from diffuse cytoplasm (UniProt Q9HC16: P-body; standard IHC practice).
Can this antibody distinguish APOBEC3G isoforms or phosphorylation states in sections?
APOBEC3G has two listed isoforms and two CMP/dCMP-type deaminase domains, but the supplied IHC caption does not map the antibody epitope (UniProt Q9HC16: isoforms and domains; datasheet M00708). It therefore cannot establish which isoform contributes to staining or whether an observed pattern is domain specific (datasheet M00708; standard IHC interpretation). Phosphothreonine is reported at residues 32 and 218, yet the caption supplies no evidence that this antibody distinguishes either modified state (UniProt Q9HC16: modified residues; datasheet M00708). Treat compartment and intensity scores as total antibody-reactive signal until epitope mapping and suitable orthogonal controls support a narrower claim (standard IHC practice).
How can IF help verify which cells carry the chromogenic APOBEC3G signal?
On a separately optimised IF section, pair APOBEC3G with a CD4 T-cell marker when examining lymphoid cells, or a macrophage marker when examining macrophages (UniProt Q9HC16: expression in CD4+ lymphocytes and monocytes; standard IF practice). Choose spectrally separated fluorophores and consider a far-red channel when tissue autofluorescence obscures shorter wavelengths (standard IF practice). APOBEC3G lacks a transmembrane segment and is mainly cytoplasmic, with a smaller nuclear pool, so use permeabilisation that allows antibody access to cytosol and, if assessed, nuclei (UniProt Q9HC16: topology and subcellular location; standard IF practice). Use unstained and single-label controls to distinguish autofluorescence and channel bleed-through from colocalisation; optimise IF independently of the chromogenic IHC conditions (standard IF practice).
What controls separate diffuse background from APOBEC3G staining?
The catalog image used 10% goat serum block, 1 µg/mL mouse primary overnight at 4°C, a biotinylated secondary and streptavidin-biotin detection with DAB (datasheet M00708). If brown signal is diffuse, compare a no-primary control and inspect whether signal tracks tissue structures or expected cells (standard IHC practice; HPA: cytoplasmic expression in immune cells). Include a peroxidase block and check endogenous biotin when using this detection format, since either can contribute to chromogenic background (standard IHC practice). Optimise washing, primary concentration and DAB development one variable at a time while preserving the EDTA pH 8.0 retrieval baseline (datasheet M00708; standard IHC practice).
How should I quantify APOBEC3G across sections with different immune-cell content? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and compartment before imaging; APOBEC3G staining is reported in immune cells and several other tissue cell types (HPA: tissue IHC profile; standard IHC practice). For cell-level intensity, report the percentage of positive cells and an H-score from 0–300 using consistent intensity thresholds (standard IHC practice). For spatial comparisons, report positive-cell density per mm² of viable tissue and state whether immune-rich and other regions were analysed separately (standard IHC practice). Normalise cell-based results to the number of evaluable cells of the same type, and compare sections processed and developed together to limit technical variation (standard IHC practice).
When is an APOBEC3G-positive focus more likely to be artefact?
A convincing focus contains intact cells with predominantly cytoplasmic staining in a plausible cell population, consistent with APOBEC3G localisation and the tissue IHC profile (UniProt Q9HC16: subcellular location; HPA: tissue IHC profile). Treat signal confined to section edges, necrotic areas or acellular deposits cautiously and review the matching no-primary control (standard IHC practice). Brown staining that persists without primary antibody warrants checks for endogenous peroxidase or, with the catalog’s streptavidin-biotin system, endogenous biotin (datasheet M00708; standard IHC practice). Nuclear staining alone deserves separate validation because the documented nuclear pool is small and HPA’s nucleoplasmic assignment is uncertain (UniProt Q9HC16: subcellular location; HPA: subcellular).
Boster reagents

Best APOBEC3G / DNA dC->dU-editing enzyme APOBEC-3G IHC Antibodies

Human paraffin-section IHC and cell IF images document APOBEC3G staining (catalog image captions); PB9985 also lists mouse and rat reactivity (catalog reactivity).

Real IHC data IHC analysis of APOBEC3G using anti-APOBEC3G antibody (M00708). APOBEC3G was detected in paraffin-embedded section of human intestinal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml mouse anti-APOBEC3G Antibody (M00708) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1021) with DAB as the chromogen.
Anti-APOBEC3G Antibody ® (monoclonal, 6C2)
Cat # M00708
Real IF data IF analysis of APOBEC3G using anti-APOBEC3G antibody (PB9985). APOBEC3G was detected in an immunocytochemical section of A431 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-APOBEC3G Antibody (PB9985) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) was used as secondary antibody at 1:500 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-APOBEC3G Antibody ®
Cat # PB9985

M00708 has IHC images from human paraffin sections of intestinal cancer, testis cancer, and tonsil, plus an IF image from MCF7 cells (M00708 image captions). PB9985 has an IF image from human A431 cells and lists human, mouse, and rat reactivity (PB9985 image caption; catalog reactivity).

Which to pick: Choose M00708 for human paraffin-section chromogenic IHC: it is a mouse monoclonal antibody, clone 6C2 (catalog), and its own IHC captions document EDTA retrieval at pH 8.0, 1 μg/mL primary antibody, and biotin–streptavidin/DAB detection; the fixative is unreported (M00708 IHC image captions). For IF/ICC, M00708 has an MCF7-cell IF image, while rabbit antibody PB9985 has an A431-cell IF image (catalog IF image captions; catalog host). PB9985 is the option with listed mouse and rat reactivity for IF/ICC, although its supplied IF image shows human cells and IHC is absent from its application list (PB9985 catalog reactivity, image caption, and applications).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9HC16 (ABC3G_HUMAN, DNA dC->dU-editing enzyme APOBEC-3G).
  2. Human Protein Atlas. APOBEC3G tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. APOBEC3G subcellular location (ICC-IF): Localized to the nucleoplasm and cytosol. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. APOBEC3G antibody validation summary (2 antibodies).
  5. APOBEC3G Expression Correlates with T-Cell Infiltration and Improved Clinical Outcomes in High-grade Serous Ovarian Carcinoma. Clinical cancer research : an official journal of the American Association for Cancer Research 2016 — PMC5026552.
  6. Evaluation of CD4(+) cells infiltration as a prognostic factor in cervical intraepithelial neoplasia 2. Journal of gynecologic oncology 2023 — PMC9807366.
  7. Type I interferon responses in rhesus macaques prevent SIV infection and slow disease progression. Nature 2014 — PMC4418221.
  8. Primary mucosal melanomas of the head and neck are characterised by overexpression of the DNA mutating enzyme APOBEC3B. Histopathology 2023 — PMC10107945.
  9. PubMed PMID:14557625 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15461802 — UniProt-cited evidence.