APOC4 / Apolipoprotein C-IV · IHC design guide

Design Immunohistochemistry for APOC4

Plan APOC4 paraffin IHC around strong plasma positivity and hepatocyte cytoplasmic staining (HPA tissue IHC). This guide covers fixation, antigen retrieval, antibody titration within 1:50–1:200 (datasheet), and interpretation of the cross-gene staining caution (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for APOC4 (IHC for APOC4): expected localisation Plasma and hepatocyte cytoplasm (HPA tissue IHC), antibody A08520, validated IHC image, and IHC protocol steps
Printable APOC4 IHC protocol sheet — expected localisation Plasma and hepatocyte cytoplasm (HPA tissue IHC), antibody A08520, controls and protocol steps. Open the full APOC4 IHC guide →

APOC4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Plasma and hepatocyte cytoplasm (HPA tissue IHC)
Staining pattern Strong plasma signal; hepatocyte cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Liver
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining may reflect protein from more than one gene (HPA tissue IHC)
Regulation Liver-enriched expression (HPA tissue RNA)
Isoform / epitope No annotated isoforms; mature chain starts at residue 28 (UniProt)
Section 1

Recommended APOC4 IHC & IF Protocols

Compare the catalog antibody's IHC-P protocol with a published APOC4 chromogenic IHC procedure (PMC11994977).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver carcinoma tissue; fixative not specified (datasheet A08520)
FixationImage fixative and duration unreported (datasheet A08520); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-APOC4, 1:50-1:200 (datasheet A08520)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultAPOC4-positive staining in hepatocytes of liver (HPA tissue IHC: Medium). HPA tissue profile: Strong positivity in plasma. Also cytoplasmic expression in liver. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page antigen-retrieval rule); the article excerpt does not specify retrieval (PMC11994977).
Section 2

What Is the Expected APOC4 Staining Pattern?

APOC4 is secreted, has no transmembrane segment, and is expressed by the liver and released into plasma (UniProt P55056). In tissue IHC, expect medium cytoplasmic staining in hepatocytes and strong plasma positivity (HPA tissue IHC: Supported). Interpret specificity cautiously: HPA notes that this tissue profile may detect protein from more than one gene (HPA tissue IHC: reliability description).

What am I looking at on my slide?
Hepatocyte cytoplasm stains at moderate intensity, with strong staining in plasma.This matches the reported liver and plasma pattern (HPA tissue IHC: medium hepatocytes; strong plasma). Read cellular and plasma signal separately: APOC4 is made in liver and secreted, so plasma positivity does not identify the cell that produced it (UniProt P55056).
Nuclei dominate the stain, or a crisp outline of hepatocyte membranes is the main cellular pattern.Neither is the expected tissue pattern: HPA reports hepatocyte cytoplasm and plasma, while UniProt describes a secreted protein with no transmembrane segment (HPA tissue IHC; UniProt P55056). Treat the compartment mismatch as a possible artefact and check controls before scoring it as APOC4.
A cell type reported as negative stains strongly, such as adipocytes in adipose tissue.HPA reports APOC4 as not detected in those adipocytes (HPA tissue IHC). Check for antibody cross-reactivity or endogenous chromogen activity (general IHC practice). Also inspect whether apparent cellular staining is adjacent plasma signal, since plasma itself is strongly positive (HPA tissue IHC).
Color appears broadly across tissue, including spaces and structures without a defined cellular pattern.Diffuse staining alone cannot establish APOC4 expression (general IHC practice). Compare the slide with a detection-only control, review blocking and washes, and ask whether the signal resolves into the reported hepatocyte cytoplasm and plasma pattern (HPA tissue IHC).
A liver section has no hepatocyte signal and no plasma signal.This conflicts with the reported medium hepatocyte and strong plasma staining (HPA tissue IHC). Confirm that the section contains evaluable hepatocytes and plasma, then review antibody identity, detection reagents, and retrieval conditions (general IHC practice); one blank section does not establish biological absence.
💡Expected APOC4 appearanceCall an IHC result pattern-consistent when hepatocyte cytoplasm is medium and plasma is strong (HPA tissue IHC); dominant nuclear staining or strong staining of HPA-negative adipocytes is suspect (HPA tissue IHC; general IHC practice).
How each factor affects the staining
Secretion and processingThe precursor has a signal peptide at residues 1–27; the annotated APOC4 chain is residues 28–127 (UniProt P55056). This supports interpreting plasma staining alongside hepatocyte cytoplasm, but the record does not identify the antibody epitope.
Antibody validation and specificityThe listed antibody HPA055877 has IHC status Supported, not Enhanced (HPA antibodies). HPA cautions that its tissue profile may detect protein from more than one gene (HPA tissue IHC), so a matching pattern supports interpretation without proving molecular specificity.
Subcellular evidenceHPA's subcellular summary says “Membrane,” yet lists no main location or ICC-IF image-bearing cell lines (HPA subcellular). For tissue interpretation, use the observed cytoplasmic hepatocyte and plasma pattern (HPA tissue IHC) together with secreted, non-transmembrane topology (UniProt P55056).
GlycosylationOne glycosylation site is annotated at residue 63 (UniProt P55056). The supplied record does not link this site to a staining compartment, retrieval setting, or staining intensity; do not infer those effects from the modification alone.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Liver positive control is blank.The reported positive compartments are absent from the readout, or the IHC workflow failed (HPA tissue IHC; general IHC practice).Verify section quality and control placement, then check antibody identity, dilution against its own instructions, retrieval, and detection controls (general IHC practice). No APOC4-specific dilution or retrieval condition is supplied here.
Brown signal is widespread despite a negative tissue control.Nonspecific antibody or detection signal, including endogenous enzyme activity, can mimic staining in chromogenic IHC (general IHC practice).Compare detection-only and appropriate tissue controls; review endogenous-activity blocking, antibody concentration, and washes (general IHC practice). Reassess only staining that has a credible cellular location.
Hepatocyte nuclei stain more than cytoplasm.The observed compartment differs from HPA's hepatocyte cytoplasmic pattern (HPA tissue IHC); the cause cannot be assigned from location alone.Check counterstain and detection-only controls, then repeat scoring with compartment boundaries in view (general IHC practice). Do not count isolated nuclear color as the expected APOC4 result.
Adipocytes stain strongly.Adipocytes in adipose tissue are reported as not detected (HPA tissue IHC); cross-reactivity, endogenous activity, or adjacent plasma signal are possibilities (general IHC practice; HPA tissue IHC: strong plasma).Compare the signal with a negative tissue and detection-only control, and determine whether color sits inside adipocytes or in nearby spaces (general IHC practice).
Plasma stains strongly but hepatocytes are hard to score.Strong plasma positivity can visually compete with medium hepatocyte cytoplasmic staining (HPA tissue IHC).Score hepatocyte cytoplasm separately from plasma and assess cells away from conspicuous plasma-rich areas (general IHC practice). Do not use plasma staining alone to assign a hepatocyte score.
IF/ICC Q&A: Does a membrane-like fluorescent signal establish APOC4 membrane localisation?HPA summarizes “Membrane” but provides no ICC-IF image-bearing cell lines or main location (HPA subcellular); UniProt calls APOC4 secreted and lists no transmembrane segment (UniProt P55056).No. Treat membrane-like IF/ICC signal as unresolved and consult the separate IF/ICC guide for that application; this IHC tissue pattern does not validate an IF/ICC compartment (HPA tissue IHC; HPA subcellular).

Sample controls for APOC4 IHC & IF

🧪Run liver first and score hepatocytes for APOC4 staining (HPA: Medium in hepatocytes). Use adipose tissue as a negative tissue, with adipocytes expected at control-level staining (HPA: Not detected in adipocytes); on the liver slide, assess nonhepatocyte cells against the no-primary background without assuming they are uniformly negative (UniProt P55056: secreted).
Positive control tissue: Liver (Hepatocytes, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for APOC4; derive a cell-line control from the positive tissue's cell type (Hepatocytes) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and matched nonimmune rabbit IgG for the polyclonal primary (selected IHC caption: pAb and goat anti-rabbit secondary), plus APOC4-knockout material or validated immunizing-peptide competition as a biological specificity control (standard IHC practice). Block endogenous peroxidase and check endogenous biotin in liver when using the caption’s avidin-peroxidase detection (selected IHC caption: avidin-peroxidase).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported; the selected 1:50 paraffin-section liver carcinoma caption does not state its fixative (selected IHC caption: fixative not stated). Antigen-retrieval dependence and whether frozen sections or IF are easier are unreported in the supplied evidence. Interpret extracellular or vascular signal cautiously because APOC4 is secreted into plasma (UniProt P55056: tissue specificity and subcellular location); endogenous biotin can complicate the caption’s avidin-based detection in liver (standard IHC practice; selected IHC caption: avidin-peroxidase).

HPA tissue IHC evidence for APOC4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Pending RNA-based expert annotation. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Liver Hepatocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced APOC4 IHC Tips

Troubleshoot APOC4 staining in paraffin sections by checking retrieval, controls, compartment, and scoring against its secreted protein biology (UniProt P55056).

What retrieval should I start with for weak APOC4 staining in paraffin sections?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 minutes (page retrieval setting: cytoplasmic / membrane antigen). Allow sections to cool in buffer, then compare retrieved and unretrieved serial sections using the same detection run (standard IHC practice). The selected antibody has a paraffin-section image at 1:50, but its caption does not report a retrieval method (A08520 tissue-IHC caption). If staining remains weak, optimise heating and cooling before testing another buffer as a fallback (standard IHC practice). Judge improvement in hepatocytes and plasma-associated signal alongside background, since APOC4 is liver-expressed and secreted (UniProt P55056; HPA tissue IHC).
How should I troubleshoot fixation-related loss of APOC4 signal?
APOC4-specific sensitivity to fixative type or fixation duration is unknown from the supplied evidence (A08520 tissue-IHC caption: fixative unreported). Record the fixative, fixation duration, tissue thickness, and processing history for each block before comparing staining (standard IHC practice). Run serial sections from differently processed blocks together with the same retrieval and detection conditions, using the liver signal as a reference (standard IHC practice; HPA tissue IHC: hepatocyte positivity). If signal varies, assess morphology and general antigen preservation before attributing the change to APOC4 (standard IHC practice). The paraffin-section caption reports 1:50 antibody use, but provides no basis for a target-specific fixation adjustment (A08520 tissue-IHC caption).
Which staining compartments are plausible for APOC4 in liver sections?
Interpret hepatocyte cytoplasmic staining and plasma-associated staining in light of liver expression and secretion (HPA tissue IHC: hepatocyte positivity and strong plasma positivity; UniProt P55056: secreted). APOC4 has a 1–27 signal peptide, a 28–127 mature chain, and no transmembrane segment (UniProt P55056 topology and processing). Thus, a sharp cell-surface outline alone needs independent validation before being called APOC4, even though the HPA subcellular summary says “Membrane” (UniProt P55056 topology; HPA subcellular summary). Compare cellular and extracellular staining on the same section and check whether signal follows vascular spaces or damaged tissue (standard IHC practice). Record these patterns separately, because staining outside hepatocytes need not represent local APOC4 production (UniProt P55056: liver expression and plasma secretion).
Could processing or glycosylation explain inconsistent APOC4 staining?
First check whether the antibody epitope is disclosed; the supplied caption identifies no epitope (A08520 tissue-IHC caption). APOC4 is reported as a 127-aa precursor with a 1–27 signal peptide and a 28–127 mature chain (UniProt P55056 processing). An epitope confined to the cleaved signal peptide would warrant different interpretation from one in the mature chain, but its location cannot be assigned here (UniProt P55056 processing; A08520 tissue-IHC caption). UniProt lists one glycosylation site at residue 63 and no annotated isoforms (UniProt P55056 PTMs and isoforms). Compare independent antibody epitopes or orthogonal evidence before blaming glycosylation for staining differences (standard IHC validation practice).
How can IF help resolve ambiguous APOC4 IHC localisation?
Use IF as a separate validation experiment and multiplex APOC4 with a hepatocyte marker to identify the expected producing cells (HPA tissue IHC: hepatocyte positivity; UniProt P55056: liver expression). Choose fluorophores after measuring tissue autofluorescence and include single-stain and no-primary controls to separate bleed-through and background (standard IF practice). For an intracellular epitope, test mild permeabilisation; for accessible extracellular antigen, compare a condition without detergent, because the epitope is unspecified and APOC4 is secreted without a transmembrane segment (A08520 tissue-IHC caption: epitope unspecified; UniProt P55056 topology). Score intracellular and extracellular fluorescence separately rather than treating overlap with a membrane marker as proof of membrane anchoring (UniProt P55056 topology; standard IF practice).
What controls distinguish APOC4 staining from chromogenic background?
Run a no-primary control beside each staining batch; the selected paraffin-section image used PBS in place of primary antibody (A08520 tissue-IHC caption). Its detection used a biotinylated secondary antibody followed by avidin-peroxidase, so inspect no-primary signal before interpreting brown deposits (A08520 tissue-IHC caption; standard IHC practice). Include an endogenous peroxidase block before DAB development and check whether residual colour follows tissue structures irrespective of primary antibody (standard chromogenic IHC practice). Titrate antibody and detection reagents while keeping retrieval constant; the caption reports 1:50 for its example, not a universal optimum (A08520 tissue-IHC caption; standard IHC practice). Compare hepatocytes with a low-signal reference such as adipocytes, reported as not detected (HPA tissue IHC: adipocytes not detected).
How should I score APOC4 when plasma signal accompanies hepatocyte staining? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scoring compartment before analysis: hepatocyte cytoplasm and extracellular or plasma-associated signal answer different questions (HPA tissue IHC: hepatocyte and plasma positivity; UniProt P55056: secreted). For hepatocytes, record the percentage of positive cells and an intensity-based H-score using consistent thresholds across sections (standard IHC scoring practice). Normalise cell counts to total evaluable hepatocytes, and report extracellular stained area or optical density per mm² of viable tissue separately (standard image-analysis practice). Exclude folds, necrosis, and edge artefacts using a prespecified mask, then compare slides processed in the same batch (standard IHC practice). Report both compartment scores because circulating APOC4 can contribute staining without indicating local synthesis (UniProt P55056: plasma secretion).
When should an apparent APOC4-positive focus be considered an artefact?
Prioritise hepatocyte cytoplasmic and plasma-associated patterns when judging plausibility, while retaining the caveat that HPA tissue staining may detect protein from more than one gene (HPA tissue IHC: profile and reliability caution). A discrete nuclear-only focus conflicts with APOC4 secretion and lacks support from the supplied localisation evidence (UniProt P55056: secreted; HPA tissue IHC). Check whether colour concentrates at section edges, folds, or necrosis, or persists in a no-primary control; these patterns warrant an artefact assessment (standard IHC practice; A08520 tissue-IHC caption: PBS control). Repeat questionable staining after reviewing endogenous peroxidase blocking and detection background (standard chromogenic IHC practice). Treat a convincing signal as antibody-reactive APOC4-like staining until specificity is supported independently (HPA tissue IHC: cross-gene caution).
Boster reagents

Best APOC4 / Apolipoprotein C-IV IHC Antibodies

The IHC-validated anti-APOC4 antibody A08520 has an image from paraffin-embedded human liver carcinoma tissue (A08520 image caption); human and mouse reactivity are listed (catalog: reactivity).

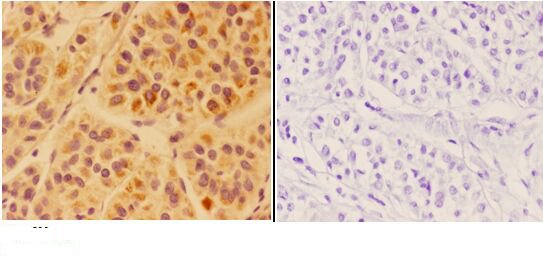
Real IHC data Immunohistochemistry (IHC) analyzes of APOC4 pAb in paraffin-embedded human liver carcinoma tissue at 1:50,showing secreted staining.Negative control (the right)Using PBS instead of primary antibody, secondary antibody is Goat Anti-Rabbit IgG-biotin followed by avidin-peroxidase.
Anti-Apolipoprotein C-IV APOC4 Antibody
Cat # A08520

A08520 is listed for IHC and for human and mouse reactivity (catalog: applications, reactivity). Its IHC image shows paraffin-embedded human liver carcinoma tissue at 1:50, with PBS replacing the primary antibody in the negative control (A08520 image caption).

Which to pick: Choose A08520 for tissue IHC: its image documents paraffin-embedded human liver carcinoma tissue, and its listed IHC dilution range is 1:50–1:200 (A08520 image caption; datasheet: IHC dilution). No IF/ICC application or IF image is listed for A08520, so the payload does not support an IF/ICC pick (catalog: applications, IF images). For cross-species planning, A08520 lists human and mouse reactivity, though the IHC image shows human tissue only; the fixative is unreported (catalog: reactivity; A08520 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.