This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic ARHGEF17 IHC in paraffin sections with the catalog antibody starting at 2.5 μg/mL (datasheet: IHC-P). Expect cytoplasmic staining, including high staining in heart cardiomyocytes, and use controls because tissue staining reliability is uncertain (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic in most tissues; high in cardiomyocytes (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Appendix+4 more · see all |
| Fixation | Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific) | |
| Caveat | Tissue staining reliability is uncertain (HPA tissue IHC) | |
| Regulation | Regulation not reported (UniProt) | |
| Isoform / epitope | No listed isoforms; one 1–2063 chain (UniProt) |
The catalog antibody’s IHC-P protocol is shown alongside published ARHGEF17 IHC methods for a ccRCC tissue array (PMC12008239) and colorectal tumor sections (PMC12775562).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A10510); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ARHGEF17, 2.5 μg/mL (datasheet A10510) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ARHGEF17-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
Expect predominantly cytoplasmic ARHGEF17 staining in many tissues (HPA tissue IHC: cytoplasmic expression in most tissues), including cardiomyocytes, glial cells and cholangiocytes scored High (HPA tissue IHC). A membrane accent is plausible from ICC-IF, which reports additional plasma membrane localization (HPA subcellular). ARHGEF17 has no transmembrane segment (UniProt Q96PE2 topology). Treat tissue IHC calls cautiously: HPA rates their reliability Uncertain, pending external verification (HPA tissue IHC).
| Cytoplasmic staining in heart cardiomyocytes, with recognizable cell boundaries. | This matches a High cell-level IHC call (HPA: heart cardiomyocytes) and UniProt's report of high heart expression (UniProt Q96PE2 tissue specificity). Score the cardiomyocytes separately from surrounding cells; the HPA IHC profile remains Uncertain (HPA tissue IHC). |
| Predominantly nuclear staining, without a discernible cytoplasmic component. | This differs from the tissue IHC cytoplasmic profile and approved ICC-IF cytosolic location (HPA tissue IHC; HPA subcellular). Check controls and detection conditions before assigning it to ARHGEF17; the supplied sources do not establish a nuclear pattern. |
| Strong staining in cells reported as Not detected, such as bone marrow hematopoietic cells. | This conflicts with that cell-level observation (HPA: bone marrow hematopoietic cells, Not detected). Consider cross-reactivity or endogenous detection activity and compare a no-primary control (general IHC practice). A single discordant field cannot establish the cause. |
| Diffuse color across cells, stroma and blank spaces, with little cell-level definition. | This is difficult to reconcile with the reported cellular cytoplasmic pattern (HPA tissue IHC). Check a no-primary control, blocking, washes and detection exposure for nonspecific background (general IHC practice) before scoring tissue expression. |
| No staining in heart cardiomyocytes while the slide's counterstain and morphology are readable. | This misses a High reference pattern (HPA: heart cardiomyocytes; UniProt Q96PE2: high heart expression). Review the IHC-validated antibody's working conditions and a positive control (general IHC practice); HPA's Uncertain reliability prevents treating absence alone as proof of assay failure (HPA tissue IHC). |
| Cell and tissue choice | Heart cardiomyocytes, liver cholangiocytes and cerebral cortex glial cells are High examples (HPA tissue IHC). Appendix glandular cells and bone marrow hematopoietic cells are reported Not detected (HPA tissue IHC). These are cell-level comparisons, not guarantees for every specimen. |
| Compartment and topology | Tissue staining is described as cytoplasmic (HPA tissue IHC). ICC-IF places ARHGEF17 mainly in cytosol, additionally at plasma membrane (HPA subcellular); UniProt lists no transmembrane segment (UniProt Q96PE2 topology). Do not require a membrane rim in chromogenic IHC. |
| Antibody evidence | HPA007991 is IHC Uncertain but ICC Approved; HPA074658 has no IHC status listed and is ICC Approved (HPA antibodies). HPA describes medium agreement between tissue staining and RNA and pending external verification (HPA tissue IHC). Interpret an isolated IHC signal with controls. |
| Antigen retrieval | No ARHGEF17-specific retrieval response is established in the supplied UniProt or HPA records. Compare retrieval conditions using the same positive tissue and controls if optimizing an IHC-P assay (general IHC practice); do not infer a target-specific fixation effect. |
| IF/ICC Q: Should an IF image look identical to chromogenic tissue IHC? | A: Expect chiefly cytosolic signal with possible plasma membrane signal in ICC-IF (HPA subcellular: approved locations). Tissue IHC is summarized as cytoplasmic and its reliability is Uncertain (HPA tissue IHC); compare compartments without assuming identical visual intensity. |
| Situation | Likely cause | Next action |
|---|---|---|
| Heart cardiomyocytes lack signal. | The result disagrees with a High HPA cell-level call and UniProt heart expression (HPA tissue IHC; UniProt Q96PE2). The cause cannot be assigned from those records alone. | Check section integrity, primary antibody conditions, retrieval and detection with a positive control (general IHC practice). Record the absent result rather than overriding it with the reference call. |
| Color appears in the no-primary control. | Background can arise from the detection system or endogenous activity (general IHC practice); this control does not implicate ARHGEF17. | Assess the detection reagent and, for enzyme-based chromogenic detection, the appropriate endogenous-enzyme block; repeat with the same tissue and exposure conditions (general IHC practice). |
| Most compartments show a uniform haze. | Poorly resolved background obscures the reported cytoplasmic cell pattern (HPA tissue IHC); excess reagent or insufficient washing are general IHC possibilities. | Compare no-primary background, adjust antibody concentration and blocking, and wash consistently (general IHC practice). Score only cells with distinguishable staining. |
| A predominantly nuclear pattern persists. | It conflicts with HPA's cytoplasmic tissue profile and approved cytosolic ICC-IF assignment (HPA tissue IHC; HPA subcellular); its identity is unresolved. | Recheck focus, counterstain and no-primary control, then compare another independently validated reagent if available (general IHC practice). Report the compartment discrepancy. |
| Bone marrow hematopoietic cells stain as strongly as the chosen positive cells. | HPA reports those hematopoietic cells as Not detected (HPA tissue IHC). Cross-reactivity or endogenous detection activity is possible (general IHC practice). | Compare matched no-primary sections and cell-level morphology; inspect whether color follows the same compartments in each control (general IHC practice). Do not call the signal specific from intensity alone. |
| ICC-IF shows a membrane rim, but IHC-P shows mainly cytoplasm. | An additional plasma membrane location is approved for ICC-IF, whereas tissue IHC is summarized as cytoplasmic (HPA subcellular; HPA tissue IHC). | Score each application against its reported compartment pattern and its own controls (general IHC practice). Do not require a visible membrane rim to accept otherwise supported cytoplasmic IHC staining. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Caudate | Glial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | High | Protein (IHC) | HPA → |
| Cerebral cortex | Glial cells | High | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Rectum | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Salivary gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot ARHGEF17 staining in chromogenic tissue IHC, with one section on adapting the experiment to IF.
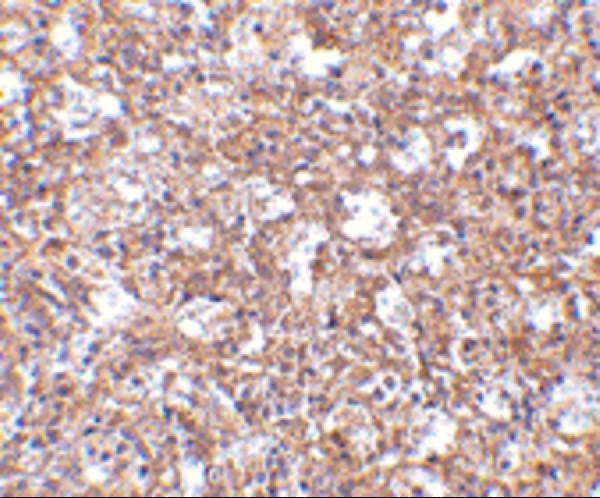
A10510 is listed for human IHC-P and has a human spleen IHC image (catalog: applications, reactivity and image caption). No IF image is supplied (catalog: IF image list).
A10510 is listed for human IHC-P (catalog: applications and reactivity). Its IHC image shows human spleen tissue at 2.5 μg/mL (catalog: IHC image caption).
Which to pick: Choose A10510 for human paraffin-section IHC; its application list includes IHC-P, and its image caption documents staining in human spleen tissue (catalog: applications and IHC image caption). For IF/ICC, A10510 has a suggested starting concentration of 20 μg/mL, but IF/ICC is absent from its application list and no IF image is supplied (catalog: dilution text, applications and IF image list). No cross-species option is listed because A10510 is the only supplied SKU and lists human reactivity; its IHC image caption does not report the fixative (catalog: reactivity and IHC image caption).