ARL2 / ADP-ribosylation factor-like protein 2 · IHC design guide

Design Immunohistochemistry for ARL2

Plan ARL2 staining in paraffin sections using the observed nuclear and cytoplasmic tissue pattern (HPA tissue IHC). Use high staining in colon glandular cells as a positive reference and assess cell types separately (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ARL2 (IHC for ARL2): expected localisation General nuclear and cytoplasmic staining (HPA tissue IHC), antibody A04155-1, validated IHC image, and IHC protocol steps
Printable ARL2 IHC protocol sheet — expected localisation General nuclear and cytoplasmic staining (HPA tissue IHC), antibody A04155-1, controls and protocol steps. Open the full ARL2 IHC guide →

ARL2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General nuclear and cytoplasmic staining (HPA tissue IHC)
Staining pattern Glandular cells show nuclear and cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04155-1)
Positive control ⓘ Colon+4 more · see all
Negative control ⓘ Liver
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Liver cholangiocytes may show no staining (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope 2 isoforms; intracellular epitope map unspecified (UniProt)
Section 1

Recommended ARL2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: A04155-1) is complemented by one published ARL2 colorectal tissue protocol (PMC7816291).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human cervical cancer tissue; fixative not specified (datasheet A04155-1)
FixationImage fixative and duration unreported (datasheet A04155-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04155-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04155-1)
Primary antibodyRabbit anti-ARL2, 2-5 μg/ml (datasheet A04155-1)
Primary incubationOvernight at 4 °C (datasheet A04155-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A04155-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultARL2-positive staining in glandular cells of colon (HPA tissue IHC: High). HPA tissue profile: General nuclear and cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet: A04155-1); the published protocol specifies microwave retrieval without naming a buffer (PMC7816291).
Section 2

What Is the Expected ARL2 Staining Pattern?

In paraffin IHC, expect ARL2 staining in cytoplasm and nuclei across several tissues, with strong staining in selected cell populations (HPA: Supported tissue IHC; general nuclear and cytoplasmic expression). ARL2 is also associated with mitochondria and centrosomes, but those structures require more specific localization evidence than routine chromogenic IHC provides (UniProt P36404: subcellular locations). ARL2 has no annotated transmembrane segment (UniProt P36404: topology).

What am I looking at on my slide?
Distinct nuclear and cytoplasmic staining in colon glandular cells.This fits a documented strong positive population and the broad tissue IHC pattern (HPA: High in colon glandular cells; general nuclear and cytoplasmic expression). Judge whether staining follows the glandular cells, rather than interpreting color throughout the section as an ARL2 pattern.
A punctate or perinuclear signal appears to mark a specific organelle.Treat the organelle assignment as provisional. HPA tissue IHC reports a general nuclear and cytoplasmic pattern, while UniProt lists mitochondria and centrosomes (HPA: tissue IHC profile; UniProt P36404: subcellular locations). Chromogenic appearance alone does not identify which structure contains the signal.
Strong staining is confined to a compartment inconsistent with the expected nuclear and cytoplasmic pattern.Consider localization artefact or nonspecific detection before assigning a new ARL2 location (HPA: general nuclear and cytoplasmic tissue IHC profile). Compare a known positive population on the same run; HPA ICC-IF locations are observations from a different assay and cannot settle an IHC compartment call.
Cholangiocytes stain strongly, while expected positive cells show little or no signal.Investigate cross-reactivity or endogenous detection activity rather than treating this reversal as expected expression (HPA: ARL2 not detected in liver cholangiocytes; High in colon glandular cells). The cholangiocyte observation is cell-specific: it does not make every cell in liver an ARL2-negative control.
Color is diffuse across cells and surrounding tissue, or a known positive population is blank.Diffuse color obscures cell and compartment boundaries; assess background controls and detection conditions before scoring it as ARL2. A blank result in colon glandular cells warrants a check of the IHC workflow and antibody performance (HPA: High in colon glandular cells), without assuming that one failed section disproves expression.
💡Expected ARL2 appearanceA convincing positive shows High staining in documented populations such as colon glandular cells, with an interpretable nuclear and cytoplasmic pattern; uniform haze or strong cholangiocyte staining is suspect (HPA: colon High, cholangiocytes not detected; general nuclear and cytoplasmic tissue IHC profile).
How each factor affects the staining
Choice of positive and comparison cellsColon glandular cells, pancreatic exocrine cells and fallopian tube ciliated cells are documented High populations (HPA: tissue IHC). Liver cholangiocytes are reported not detected; compare identified cell types rather than whole-organ averages (HPA: liver cholangiocytes).
Compartment evidence differs by assayTissue IHC reports general nuclear and cytoplasmic expression (HPA: tissue IHC). ICC-IF additionally places ARL2 mainly in nucleoplasm, basal body and flagellar centriole (HPA: subcellular ICC-IF). Those fine locations are useful context, but are not directly validated as resolvable chromogenic IHC patterns.
Conflicting nuclear annotationsUniProt lists the nucleus among ARL2 locations but also says ARL2 was not detected there in its location note (UniProt P36404: subcellular annotation). HPA reports nuclear tissue staining and supported nucleoplasmic ICC-IF localization (HPA: tissue IHC; subcellular ICC-IF). Report the observed assay pattern without claiming this discrepancy is resolved.
Antibody validation and isoformsHPA044610 has Supported IHC status, and HPA rates the tissue staining Supported for consistency with RNA expression (HPA: antibody validation; tissue reliability). UniProt lists 2 ARL2 isoforms (UniProt P36404: isoforms); the supplied records do not establish which isoforms an antibody detects.
Epitope and preparation informationUniProt annotates a chain spanning residues 2–184 and no transmembrane segment (UniProt P36404: processing and topology). Neither annotation identifies the antibody epitope or establishes a retrieval condition. Target-specific fixation sensitivity and an optimal antigen retrieval method are unreported in the supplied sources.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in a documented High population.The result conflicts with the expected staining in that cell population, but the image alone cannot identify the failed step (HPA: High in colon glandular cells).Confirm the cell identity and section quality, then review the assay's antibody dilution, retrieval, detection and counterstain settings as general IHC workflow checks. Run an appropriate positive section alongside it; do not infer ARL2-specific retrieval requirements from HPA.
Strong signal appears in liver cholangiocytes.This differs from the reported not-detected result and may reflect nonspecific antibody binding or endogenous detection activity (HPA: liver cholangiocytes not detected).Verify cholangiocyte identity, inspect a no-primary control, and assess the detection system's endogenous-activity block where applicable. Compare staining with a documented High population (HPA: tissue IHC); a negative-control result alone cannot prove antibody specificity.
Diffuse brown background masks cell boundaries.Section-wide deposition can arise from general chromogenic IHC background; it does not establish diffuse ARL2 expression.Inspect a no-primary control and review blocking, washes, detection time and counterstain as general IHC checks. Score ARL2 only where cells and compartments remain distinguishable (HPA: general nuclear and cytoplasmic tissue IHC profile).
A bright spot is scored as centrosomal or mitochondrial ARL2.UniProt lists both locations, but a chromogenic spot does not identify an organelle (UniProt P36404: subcellular locations).Describe the observed spot without assigning an organelle from IHC alone. For a localization question, consult the separate IF/ICC guide; HPA reports basal body, flagellar centriole and mitochondrial localization in ICC-IF (HPA: subcellular ICC-IF).
Nuclear staining is automatically rejected as artefact.The records contain mixed nuclear annotations: HPA reports nuclear tissue staining, while a UniProt location note says ARL2 was not detected in the nucleus (HPA: tissue IHC; UniProt P36404: subcellular annotation).Keep the nuclear observation in the record, compare it with the documented cell-type pattern and controls, and state the source discrepancy. HPA's Supported nucleoplasmic ICC-IF result supplies context, not a substitute IHC validation (HPA: subcellular ICC-IF).
A low-staining population is called negative.Low and not detected are different HPA categories: hippocampal neuronal cells, smooth muscle cells and bone marrow hematopoietic cells are Low, whereas liver cholangiocytes are not detected (HPA: tissue IHC).Record the identified cell type and staining intensity separately. Compare it with a High population in the same run before deciding whether the assay has lost sensitivity (HPA: tissue IHC).

Sample controls for ARL2 IHC & IF

🧪Run colon first: glandular cells should stain for ARL2 (HPA: High in colon glandular cells). Use liver cholangiocytes as the negative tissue and assess non-glandular cells on the colon slide as internal contrast only where they lack specific staining; HPA does not designate those cells as negative (HPA: Not detected in liver cholangiocytes; colon row reports glandular cells only).
Positive control tissue: Colon (Glandular cells, HPA High)
Negative control tissue: Liver (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ARL2 in U2OS, ASC52telo, RPTEC/TERT1, hTERT-RPE1 (serum starved), Sperm, with annotated localisation: Nucleoplasm (supported), Basal body (approved), Flagellar centriole (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a host-matched rabbit isotype control, and ARL2 knockout material or an appropriate peptide-block control to assess specificity (caption: rabbit anti-ARL2; standard IHC practice). Quench endogenous peroxidase and check the colon section for background before interpreting DAB staining (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A04155-1 paraffin-section caption does not state a fixative (caption: fixative unreported). The caption uses heat retrieval in EDTA at pH 8.0, but whether retrieval is required for ARL2 is unreported (caption: heat-mediated EDTA retrieval). The supplied evidence does not establish whether frozen sections or IF/ICC are easier, or identify a colon-specific artefact; assess tissue background with the controls above (HPA: ICC-IF images available; standard IHC practice).

HPA tissue IHC evidence for ARL2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Colon Glandular cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Fallopian tube Ciliated cells (ciliary rootlets) High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Lung Alveolar cells type I High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Section 3

Advanced ARL2 IHC Tips

Troubleshoot ARL2 staining in paraffin sections by checking retrieval, cell type, subcellular pattern and controls before interpreting signal intensity.

What retrieval should I try first when ARL2 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A04155-1). The selected paraffin-section image used this retrieval before incubation with 2 μg/ml antibody overnight at 4°C (datasheet A04155-1). If staining remains weak, compare a modestly longer heating interval with the original interval on adjacent sections, recording temperature and cooling time (standard IHC practice). Keep antibody concentration, detection and development conditions matched so retrieval is the variable under test (standard IHC practice). Examine tissue morphology alongside signal, because excessive heating can damage sections and complicate localisation calls (standard IHC practice).
Can I choose a fixative based on the reported ARL2 tissue pattern?
The selected image documents a paraffin-embedded section but does not state its fixative, so ARL2-specific fixation sensitivity is unknown (datasheet A04155-1). Treat fixation history as an experimental variable and record fixative, duration and processing conditions for every comparison (standard IHC practice). Begin evaluation with the documented EDTA pH 8.0 retrieval and 2 μg/ml primary incubation overnight at 4°C (datasheet A04155-1). Compare sections with known, matched processing before attributing weaker staining to biological expression differences (standard IHC practice). General nuclear and cytoplasmic tissue staining does not establish which fixation conditions preserve this antibody's epitope (HPA: tissue IHC profile).
Should ARL2 staining be nuclear, cytoplasmic or concentrated near centrioles?
Expect potentially mixed nuclear and cytoplasmic staining in tissue sections (HPA: tissue IHC profile). In cell imaging, nucleoplasm, basal body and flagellar centriole are principal reported locations, with additional mitochondrial localisation (HPA: subcellular). UniProt also lists mitochondrial intermembrane space and centrosome association, while its annotation notes no detection in the nucleus (UniProt P36404 localisation). Resolve this discrepancy by scoring nuclear, diffuse cytoplasmic and focal perinuclear patterns separately within identified cell types (standard IHC practice). A small centrosomal focus may be difficult to resolve with chromogenic brightfield imaging; assess it cautiously against morphology and controls (standard IHC practice).
Could isoform choice or epitope access explain discordant ARL2 staining?
ARL2 has 2 annotated isoforms and no annotated transmembrane segment (UniProt P36404 isoforms and topology). The supplied antibody evidence does not specify its epitope or establish equal recognition of both isoforms (datasheet A04155-1: selected image caption). Consequently, do not assign an absent nuclear or cytoplasmic signal to a particular isoform from chromogenic staining alone (standard IHC interpretation). UniProt annotates phosphoserine at residue 45, but the supplied evidence does not show that this modification changes antibody binding (UniProt P36404 modified residues; datasheet A04155-1: selected image caption). If an epitope map becomes available, check its sequence against both isoforms before interpreting compartment differences (standard antibody-validation practice).
How can IF help assess ARL2 localisation alongside a cell-type marker?
For a separate IF experiment, pair ARL2 with a cilia marker such as acetylated tubulin when examining ciliated cells; high ciliary-rootlet staining is reported in fallopian tube (HPA: tissue IHC). Assign spectrally distinct fluorophores and favour a far-red ARL2 channel if tissue autofluorescence obscures shorter wavelengths (standard IF practice). ARL2 lacks an annotated transmembrane segment, while mitochondrial intermembrane-space localisation is reported (UniProt P36404 topology and localisation). After fixation, assess detergent permeabilisation against signal and morphology, since access to intracellular compartments depends on membrane disruption (standard IF practice). Include single-colour and secondary-only controls when evaluating overlap or bleed-through (standard IF practice).
How do I distinguish diffuse ARL2 signal from chromogenic background?
The selected paraffin-section workflow used 10% goat serum, a peroxidase-conjugated secondary incubated for 30 minutes at 37°C, and DAB development (datasheet A04155-1). Add an endogenous peroxidase block and inspect a no-primary control before treating brown deposit as ARL2 signal (standard chromogenic IHC practice). Titrate development while keeping exposure conditions consistent across comparison sections, because excess DAB can obscure cellular boundaries (standard IHC practice). Examine whether signal follows identifiable cells and compartments rather than folds, tissue edges or precipitate (standard IHC interpretation). General nuclear and cytoplasmic expression makes diffuse cellular staining plausible, but it does not validate staining present in negative controls (HPA: tissue IHC profile; standard IHC interpretation).
How should I quantify ARL2 across paraffin sections with mixed staining patterns? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because ARL2 tissue staining includes nuclear and cytoplasmic expression (HPA: tissue IHC profile). For each compartment, report the percentage of positive viable cells and an H-score from 0–300, calculated from percentages at intensity grades 0–3 (standard IHC scoring practice). If measuring focal signal, report positive profiles per mm² of evaluable tissue and state the identification rule (standard image-analysis practice). Normalise cell counts to viable cells of the same annotated type, or area-based counts to evaluable area, excluding necrosis and folds (standard IHC scoring practice). Apply identical staining, imaging and scoring settings to comparison sections (standard IHC scoring practice).
What would make an apparent ARL2-positive cell or compartment unconvincing?
Judge staining against cell identity: glandular cells in colon and ciliated cells in fallopian tube have reported high signal, whereas liver cholangiocytes are reported undetected (HPA: tissue IHC). Nuclear and cytoplasmic staining is documented, while centrosomal and mitochondrial locations provide additional context for focal patterns (HPA: tissue IHC and subcellular; UniProt P36404 localisation). A pattern confined to an unexpected compartment or cell population needs corroboration rather than automatic rejection, given the reported localisation differences (HPA: subcellular; UniProt P36404 localisation; standard IHC interpretation). Discount staining concentrated at edges, folds or necrosis, and inspect no-primary controls for endogenous enzyme signal (standard IHC interpretation). Reproducibility across well-preserved sections strengthens an interpretation (standard IHC practice).
Boster reagents

Best ARL2 / ADP-ribosylation factor-like protein 2 IHC Antibodies

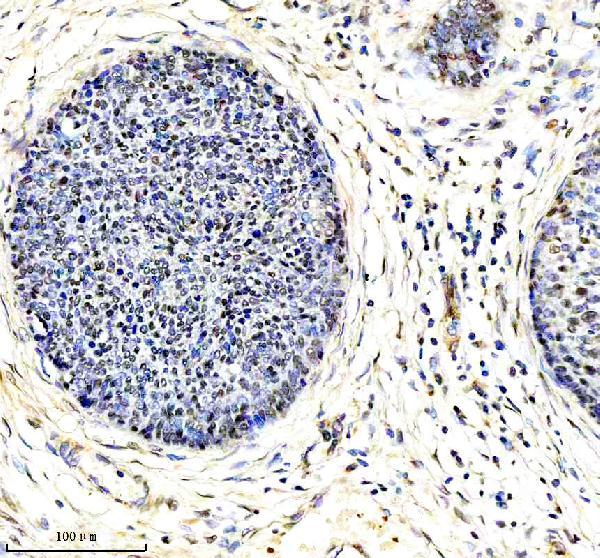
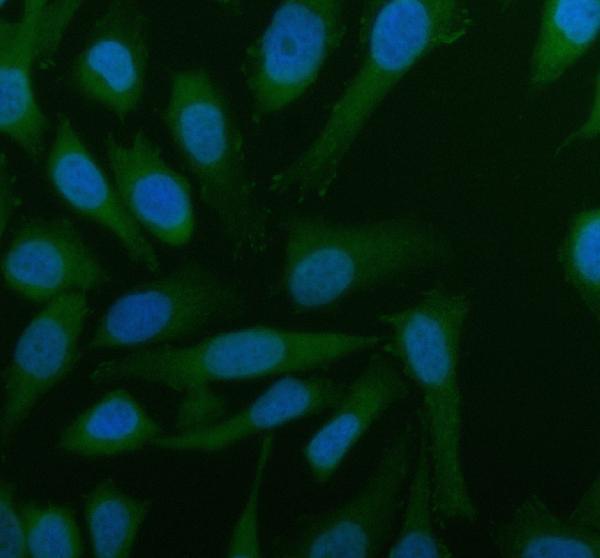
The IHC-validated antibody has real paraffin-section IHC data from human cervical cancer tissue and IF/ICC data from HELA cells (A04155-1 image captions). Human, Mouse and Rat reactivity is listed (catalog reactivity).

Real IHC data IHC analysis of ARL2 using anti-ARL2 antibody (A04155-1). ARL2 was detected in a paraffin-embedded section of human cervical cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ARL2 Antibody (A04155-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-ARL2 Antibody ®
Cat # A04155-1

A04155-1 will render with IHC data from a paraffin-embedded human cervical cancer section (A04155-1 IHC caption). Its IF/ICC data show ARL2 detection in HELA cells (A04155-1 IF caption).

Which to pick: Choose A04155-1 for paraffin-section IHC; its IHC caption documents a human cervical cancer section, while the fixative is unreported (A04155-1 IHC caption). Choose the same SKU for IF/ICC in HELA cells (A04155-1 IF caption). For cross-species work, the catalog lists Human, Mouse and Rat reactivity, but the supplied IHC and IF images document human samples only; clonality is unreported (catalog reactivity; A04155-1 image captions; catalog clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P36404 (ARL2_HUMAN, ADP-ribosylation factor-like protein 2).
  2. Human Protein Atlas. ARL2 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. ARL2 subcellular location (ICC-IF): Mainly localized to the nucleoplasm, basal body and flagellar centriole. In addition localized to the nucleoli, mitochondria, equatorial segment and mid piece..
  4. Human Protein Atlas. ARL2 antibody validation summary (1 antibodies).
  5. Regulation of ARL2 in colorectal cancer cell proliferation and tumorigenicity, and its negative association with AXL. Oncology letters 2021 — PMC7816291.
  6. ARL2 overexpression inhibits glioma proliferation and tumorigenicity via down-regulating AXL. BMC cancer 2018 — PMC5975491.
  7. ARL2 is required for homologous recombination repair and colon cancer stem cell survival. FEBS open bio 2022 — PMC9340879.
  8. ADP-Ribosylation Factor-Like 2 (ARL2) regulates cilia stability and development of outer segments in rod photoreceptor neurons. Scientific reports 2018 — PMC6240099.
  9. PubMed PMID:8415637 — UniProt-cited evidence.
  10. PubMed PMID:15146197 — UniProt-cited evidence.
  11. PubMed PMID:16554811 — UniProt-cited evidence.