ASCL1 / Achaete-scute homolog 1 · IHC design guide

Design Immunohistochemistry for ASCL1

Plan chromogenic ASCL1 IHC in paraffin sections with the catalog antibody at 2–5 μg/ml (datasheet A03023-2). Assess cytoplasmic CNS staining (HPA tissue IHC) while accounting for the nuclear molecular annotation (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ASCL1 (IHC for ASCL1): expected localisation Cytoplasmic in CNS (HPA tissue IHC); nuclear (UniProt), antibody A03023-2, validated IHC image, and IHC protocol steps
Printable ASCL1 IHC protocol sheet — expected localisation Cytoplasmic in CNS (HPA tissue IHC); nuclear (UniProt), antibody A03023-2, controls and protocol steps. Open the full ASCL1 IHC guide →

ASCL1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic in CNS (HPA tissue IHC); nuclear (UniProt)
Staining pattern Cytoplasmic staining in CNS glia and cerebellar processes (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03023-2)
Positive control ⓘ Cerebellum+3 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat CNS cytoplasmic staining contrasts with nuclear annotation (HPA tissue IHC; UniProt)
Regulation Early neural lineage development (UniProt)
Isoform / epitope No isoforms annotated; one 1–236 chain (UniProt)
Section 1

Recommended ASCL1 IHC & IF Protocols

Start with the catalog antibody’s IHC-P protocol (datasheet: A03023-2), then compare published staining of rat paraffin-embedded tissue (PMC10855250) and human small cell lung cancer tissue microarrays (PMC7779202).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet A03023-2)
FixationImage fixative and duration unreported (datasheet A03023-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03023-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03023-2)
Primary antibodyRabbit anti-ASCL1, 2-5 μg/ml (datasheet A03023-2)
Primary incubationOvernight at 4 °C (datasheet A03023-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03023-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
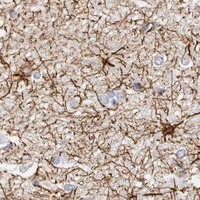
Expected resultASCL1-positive staining in processes in granular layer of cerebellum (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in CNS. No signal in the no-primary control.
💡Decision noteTry EDTA pH 8.0 heat retrieval first (datasheet: A03023-2); sodium citrate pH 6.0 is a published alternative for rat tissue (PMC10855250).
Section 2

What Is the Expected ASCL1 Staining Pattern?

ASCL1 is a nuclear transcription factor without a transmembrane segment (UniProt P50553: location and topology). In tissue IHC, HPA reports cytoplasmic staining in the CNS, including glial cells and cerebellar granular-layer processes (HPA: tissue IHC). That observed pattern has Enhanced reliability, reflecting consistency with RNA expression data (HPA: tissue IHC). Interpret nuclear and cytoplasmic signal in the context of the assay and cell type.

What am I looking at on my slide?
CNS glial staining, with signal in cerebellar granular-layer processes.This matches the reported tissue IHC pattern: High in cortical and hippocampal glial cells and cerebellar processes; Medium in caudate glial cells (HPA: tissue IHC). Record the stained cell type and compartment separately. The tissue result should not be described as exclusively nuclear, even though ASCL1 is annotated as nuclear (UniProt P50553: location).
Prominent staining in an unexpected compartment, especially when it differs from the CNS reference pattern.Treat this as a possible localisation artefact and review morphology and controls before calling it ASCL1. UniProt places ASCL1 in the nucleus; HPA reports cytoplasmic CNS tissue staining and approved nucleoplasmic plus cytosolic ICC-IF localisation (UniProt P50553: location; HPA: tissue IHC and subcellular). Cytoplasmic signal alone therefore cannot be dismissed automatically.
Strong staining in cell types reported as undetected, such as adipocytes or adrenal glandular cells.This conflicts with those HPA tissue observations (HPA: adipose tissue and adrenal gland, Not detected). Consider cross-reactivity or endogenous detection activity, particularly if staining is widespread or unrelated to cell morphology. A negative reference limits interpretation of that preparation; it does not prove every specimen of the tissue must be negative.
Diffuse chromogen across cells and surrounding tissue, with little cellular distinction.This is difficult to score as ASCL1 because the reported tissue signal is assigned to specific CNS cells or processes (HPA: tissue IHC). In general IHC practice, inspect the negative control and background before changing the biological interpretation. Document whether signal follows nuclei, cytoplasm, processes, or extracellular spaces.
No staining in a chosen HPA positive CNS reference.First assess the assay and reference section: HPA reports High staining in cortical and hippocampal glial cells and cerebellar granular-layer processes, but only Medium in caudate glial cells (HPA: tissue IHC). Check morphology, detection controls, and the antibody's IHC validation before concluding that ASCL1 is absent. HPA staining levels are observations, not guaranteed signal in every section.
💡Expected ASCL1 appearanceFor tissue IHC, a convincing positive follows identifiable CNS glial cells or cerebellar granular-layer processes, with High reported staining in those settings (HPA: tissue IHC); broad, structureless staining in unrelated cells warrants control review.
How each factor affects the staining
Assay-dependent compartmentNuclear localisation reflects the annotated transcription-factor role (UniProt P50553: location and function). HPA tissue IHC describes cytoplasmic CNS staining, while ICC-IF identifies approved nucleoplasmic and additional cytosolic localisation (HPA: tissue IHC and subcellular). Keep those observations distinct when scoring a paraffin section.
Reference tissue and cell selectionCortex and hippocampus provide reported High glial staining; cerebellum provides High staining in granular-layer processes; caudate glial staining is Medium (HPA: tissue IHC). Adipocytes and adrenal glandular cells are reported Not detected (HPA: tissue IHC). Choose controls by the named cell type, not by tissue name alone.
Molecular context and antibody evidenceASCL1 is a 236-residue chain with no signal peptide, propeptide, transmembrane segment, or annotated isoforms (UniProt P50553: processing and topology). These facts do not predict retrieval needs or fixation sensitivity. HPA029217 has Enhanced IHC validation (HPA: antibodies); that status does not validate every antibody or staining run.
IF/ICC Q: Where should signal appear?A: Mainly in the nucleoplasm, with additional cytosolic localisation reported as approved (HPA: subcellular ICC-IF). This is an IF/ICC interpretation point, not an IHC protocol choice. Apply the tissue IHC observations separately when reading chromogenic paraffin sections (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A reported High CNS reference is blank.The assay or reference section may have failed; the listed High level is an HPA observation, not a guarantee (HPA: tissue IHC).Check section morphology and positive and detection controls. Review the antibody's IHC validation, then reassess the reference cell type (general IHC practice; HPA: antibodies and tissue IHC).
Cytoplasmic signal is labelled automatically as nonspecific.HPA describes cytoplasmic CNS tissue staining, despite UniProt's nuclear annotation (HPA: tissue IHC; UniProt P50553: location).Score cell identity and compartment separately; compare with the reported CNS pattern and controls before rejecting the signal.
Many unrelated cell types stain strongly.Cross-reactivity or endogenous detection activity is possible, especially where HPA reports cells as Not detected (HPA: tissue IHC).Compare a matched negative control and inspect whether chromogen follows cellular structures (general IHC practice).
The whole section has diffuse background.Nonspecific reagent binding or detection background can obscure the cell-restricted HPA pattern (general IHC practice; HPA: tissue IHC).Review blocking, washes, detection controls, and chromogen development using the validated IHC workflow (general IHC practice).
Only caudate appears weaker than cortex.HPA reports Medium staining in caudate glial cells and High staining in cortical glial cells (HPA: tissue IHC).Compare like cell types and score intensity by site before treating the difference as assay failure (HPA: tissue IHC).
An IF/ICC image appears mainly nuclear while tissue IHC appears cytoplasmic.These are the reported patterns for different assays (HPA: subcellular ICC-IF and tissue IHC).Interpret each against its own HPA reference and controls; do not transfer an IF/ICC localisation call directly to a paraffin IHC score.

Sample controls for ASCL1 IHC & IF

🧪Run cerebral cortex first and score nuclear staining in glial cells, which HPA rates High (HPA: cerebral cortex, glial cells High; UniProt P50553: nucleus). Use adipose tissue as the negative tissue, focusing on adipocytes rated Not detected; on the cortex slide, cells without nuclear signal can serve as internal background references, but their identity should be checked before calling them biological negatives (HPA: adipose adipocytes Not detected; standard IHC practice).
Positive control tissue: Cerebellum (Processes in granular layer, HPA High)
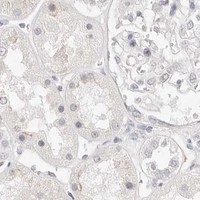
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ASCL1 in HAP1, SH-SY5Y, U2OS, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched rabbit IgG isotype controls for the rabbit catalog antibody, plus an ASCL1-knockout specimen if available as a biological negative (selected-SKU IHC caption: rabbit primary; standard IHC practice). Quench endogenous peroxidase and inspect cortical pigment that could be mistaken for DAB signal; for IF/ICC, assess tissue autofluorescence separately (standard IHC/IF practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected-SKU paraffin-section caption does not state a fixative (selected-SKU IHC caption). The caption reports heat retrieval in EDTA at pH 8.0 before IHC staining, but does not establish that this retrieval condition is required for cerebral cortex (selected-SKU IHC caption: lung cancer section; HPA: cerebral cortex glial cells High). The evidence does not establish whether frozen sections or IF/ICC are easier; HPA reports mainly nucleoplasmic and additional cytosolic IF localization, while cortical pigment or autofluorescence can complicate interpretation (HPA: subcellular localization; standard IHC/IF practice).

HPA tissue IHC evidence for ASCL1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Processes in granular layer High Protein (IHC) HPA →
Cerebral cortex Glial cells High Protein (IHC) HPA →
Hippocampus Glial cells High Protein (IHC) HPA →
Caudate Glial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced ASCL1 IHC Tips

Troubleshoot ASCL1 staining by checking retrieval, compartment, cell identity and matched controls before changing how paraffin sections are scored.

What should I adjust when ASCL1 staining is weak after antigen retrieval?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for this paraffin-section IHC assay (datasheet A03023-2). The selected tissue image used that retrieval before an overnight incubation at 4°C with 2 μg/ml catalog antibody (datasheet A03023-2). If staining is weak, verify that the section remained covered by retrieval solution and compare a longer or shorter heating interval on matched sections while keeping the buffer constant (standard IHC practice). Judge any gain by nuclear signal and preserved morphology, since ASCL1 is a nuclear transcription factor and excessive retrieval can impair tissue interpretation (UniProt P50553; standard IHC practice).
Could fixation explain weak or uneven ASCL1 staining in my paraffin sections?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative, so its staining cannot establish an optimal fixation method for ASCL1 (datasheet A03023-2). Record the fixative, fixation duration and processing history for each specimen before comparing staining across sections (standard IHC practice). Keep retrieval at EDTA pH 8.0 and the primary concentration at 2 μg/ml during an initial comparison so those variables do not obscure a fixation effect (datasheet A03023-2; standard IHC practice). Check morphology and staining in similarly processed control sections, then adjust one preparation variable at a time (standard IHC practice).
How should I evaluate cytoplasmic staining when ASCL1 is expected in nuclei?
Prioritize interpretable nuclear staining when evaluating ASCL1 as a transcription factor, because UniProt places it in the nucleus and describes its DNA-binding role (UniProt P50553). Cytoplasmic signal deserves separate reporting: HPA describes cytoplasmic expression in CNS tissue and an additional cytosolic location in its subcellular data (HPA tissue IHC; HPA subcellular). Compare nuclear and cytoplasmic patterns against cell morphology, a matched control section and the no-primary control before assigning either pattern to ASCL1 (standard IHC practice). Do not combine both compartments into one positive-cell score; record their separate percentages so a change in background cannot masquerade as altered nuclear expression (standard IHC practice).
Could an isoform or epitope difference explain inconsistent ASCL1 IHC staining?
The supplied UniProt record lists 0 isoforms and one 1–236 chain, so an annotated isoform switch does not explain discordant sections here (UniProt P50553). It identifies a bHLH domain at residues 118–170 and an example acetylated residue at 156, but the antibody’s binding epitope is not supplied (UniProt P50553; datasheet A03023-2). Consequently, do not attribute weak staining to that modification or to masking of a particular domain without epitope evidence (UniProt P50553; standard IHC interpretation). First compare matched sections under the documented EDTA pH 8.0 retrieval and 2 μg/ml primary conditions, then assess control staining and morphology (datasheet A03023-2; standard IHC practice).
How can IF help check an ambiguous ASCL1 IHC pattern?
Use IF/ICC as a separate comparison of compartment and cell identity, since HPA reports ASCL1 mainly in the nucleoplasm with an additional cytosolic location in its subcellular data (HPA subcellular). Multiplex ASCL1 with a marker of the expected neuronal or neuroendocrine cell type, chosen for the specimen, and inspect colocalization at the single-cell level (UniProt P50553 function; standard IF practice). Select fluorophores in channels with low measured tissue autofluorescence and include unstained and single-stain controls before interpreting overlap (standard IF practice). ASCL1 has no transmembrane segment, so use permeabilisation that permits antibody access to a nuclear epitope; the antibody’s precise epitope remains unspecified (UniProt P50553 topology; datasheet A03023-2; standard IF practice).
What should I check when DAB background obscures ASCL1-positive nuclei?
Run a no-primary section and inspect where brown signal appears before changing the ASCL1 antibody concentration; widespread signal in that control points to detection or tissue background (standard IHC practice). The selected assay used 10% goat serum, 2 μg/ml primary antibody overnight at 4°C, a peroxidase-conjugated secondary for 30 minutes at 37°C, and DAB development (datasheet A03023-2). Include a peroxidase-blocking step and control DAB development time as general chromogenic IHC measures, rather than treating them as ASCL1-specific validation (standard IHC practice). Compare background in intact tissue with section edges and damaged areas, then adjust blocking, washing or antibody exposure one variable at a time (standard IHC practice).
How should I score ASCL1 staining across heterogeneous paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and nuclear positivity threshold before scoring, and apply the same rules to every section in the comparison (standard IHC practice). Report % positive cells or a nuclear H-score using staining-intensity categories and the percentage of eligible cells in each category (standard IHC practice). If spatial distribution matters, report positive-cell density per mm² of viable, annotated tissue and exclude folds, necrosis and section edges consistently (standard IHC practice). Normalize counts to eligible cells or viable tissue area, record cytoplasmic staining separately, and retain identical detection and counterstain settings across compared slides (standard IHC practice; HPA tissue IHC).
What evidence distinguishes genuine ASCL1 staining from an IHC artefact?
A convincing result shows reproducible staining in the relevant cells, with nuclear signal assessed against ASCL1’s transcription-factor role and reported nuclear location (UniProt P50553). Cytoplasmic staining alone requires caution rather than automatic dismissal, because HPA reports cytoplasmic CNS tissue staining and an additional cytosolic location (HPA tissue IHC; HPA subcellular). Compare the candidate cells with their morphology and a matched no-primary section; signal concentrated at section edges, in necrotic areas or where endogenous peroxidase persists is suspect (standard IHC practice). Use the documented EDTA pH 8.0 assay conditions as a reference, and report compartment-specific observations without inferring expression from DAB color alone (datasheet A03023-2; standard IHC practice).
Boster reagents

Best ASCL1 / Achaete-scute homolog 1 IHC Antibodies

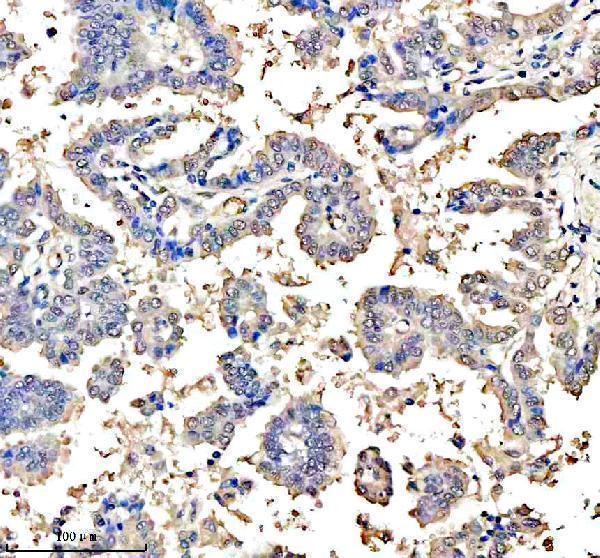
A03023-2 has IHC data from a human lung cancer paraffin section (image caption: A03023-2). Its listed reactivity includes human, mouse, and rat (catalog: A03023-2 reactivity).

Real IHC data IHC analysis of ASCL1 using anti-ASCL1 antibody (A03023-2). ASCL1 was detected in a paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ASCL1 Antibody (A03023-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-ASCL1 Antibody ®
Cat # A03023-2

A03023-2 is listed for IHC and reacts with human, mouse, and rat (catalog: A03023-2 applications/reactivity). Its IHC image shows a human lung cancer paraffin section with EDTA pH 8 retrieval and DAB detection; the fixative is unreported (image caption: A03023-2).

Which to pick: For tissue IHC, choose A03023-2: this rabbit antibody has a human paraffin-section IHC example, with fixation unreported (catalog: A03023-2 host/applications; image caption: A03023-2). No IF/ICC-validated option or IF image is supplied (catalog: A03023-2 applications/IF images). For cross-species work, A03023-2 lists mouse and rat reactivity, but its IHC dilution and tissue image document human samples only (catalog: A03023-2 reactivity/dilution; image caption: A03023-2).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P50553 (ASCL1_HUMAN, Achaete-scute homolog 1).
  2. Human Protein Atlas. ASCL1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. ASCL1 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. ASCL1 antibody validation summary (2 antibodies).
  5. A comparison of adult rhabdomyosarcoma and high-grade neuroendocrine carcinoma of the urinary bladder reveals novel PPP1R12A fusions in rhabdomyosarcoma. Human pathology 2019 — PMC8078053.
  6. Postnatal Exposure to the Endocrine Disruptor Dichlorodiphenyltrichloroethane Affects Adrenomedullary Chromaffin Cell Physiology and Alters the Balance of Mechanisms Underlying Cell Renewal. International journal of molecular sciences 2024 — PMC10855250.
  7. Clinicopathological features and prognostic implications of ASCL1 expression in surgically resected small cell lung cancer. Thoracic cancer 2021 — PMC7779202.
  8. Pulmonary Neuroendocrine Cells and Small Cell Lung Carcinoma: Immunohistochemical Study Focusing on Mechanisms of Neuroendocrine Differentiation. Acta histochemica et cytochemica 2022 — PMC9253501.
  9. PubMed PMID:8390674 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.