This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan ATG4B IHC-P around cytoplasmic staining in most tissues (HPA tissue IHC). This guide covers consistent section fixation (standard IHC practice), a 5 μg/mL antibody starting concentration (datasheet), and interpretation of nuclear staining flagged as off target (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Staining pattern | Glandular-cell cytoplasmic staining; texture unreported (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Nuclear staining was deemed off target (HPA tissue IHC) | |
| Regulation | Expression regulation unreported (UniProt) | |
| Isoform / epitope | 5 isoforms; epitope coverage unknown (UniProt) |
Compare the catalog antibody’s IHC-P protocol with four published ATG4B chromogenic IHC protocols (PMC13313432; PMC9388977; PMC11416411; PMC6966594).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A02885); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ATG4B, 5 μg/mL (datasheet A02885) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ATG4B-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in a majority of tissues. No signal in the no-primary control. |
ATG4B is mainly cytosolic, with smaller pools associated with autophagosomes, endoplasmic reticulum and mitochondria; it has no transmembrane segment (UniProt Q9Y4P1 localization and topology). In tissue IHC, expect cytoplasmic staining in many cell types, especially appendix, colon and duodenal glandular cells (HPA tissue IHC: High). HPA rates its tissue staining Approved, while reporting medium agreement with RNA data and disregarded off-target staining (HPA tissue IHC reliability).
| Cytoplasmic staining in appendix, colon or duodenal glandular cells, with little nuclear signal. | This fits the strongest listed tissue examples: glandular cells are High, and the overall IHC profile is cytoplasmic (HPA tissue IHC). Score the relevant cells and compartment, since a strongly stained area alone does not establish the expected pattern (general IHC practice). |
| Prominent nuclear staining, especially if cytoplasmic staining is weak or absent. | Treat nuclear tissue-IHC signal cautiously: HPA explicitly considered nuclear staining off target and disregarded it (HPA tissue IHC reliability). HPA separately approves nucleoplasmic signal in ICC-IF; that finding does not validate a nuclear pattern on paraffin tissue sections (HPA subcellular ICC-IF; HPA tissue IHC). |
| Strong signal in a cell population listed as Not detected, such as adipocytes or cardiomyocytes. | That conflicts with the listed cell-specific tissue-IHC observations (HPA tissue IHC: adipocytes and cardiomyocytes Not detected). Check cell identification, antibody specificity and detection controls before calling it ATG4B; staining in another cell population within the same tissue needs its own assessment (general IHC practice). |
| Diffuse color covers tissue and empty areas, obscuring cell boundaries. | A non-cellular haze cannot be read as the reported cytoplasmic pattern (HPA tissue IHC profile; general IHC practice). Examine a no-primary control and review blocking, washes and chromogen development to distinguish background from signal in identifiable cells (general IHC practice). |
| No cytoplasmic signal in glandular cells of an otherwise interpretable appendix, colon or duodenum section. | This misses HPA's High cell-specific examples (HPA tissue IHC). Confirm that the intended cells are present and assess the IHC assay with controls before concluding that the specimen lacks ATG4B (general IHC practice). |
| Cell type and tissue | HPA reports cytoplasmic expression in a majority of tissues but different cell-specific levels: glandular cells in appendix, colon and duodenum are High, while lung macrophages and pancreatic exocrine glandular cells are Medium (HPA tissue IHC). Compare like cell types when judging intensity. |
| Compartment and topology | The predominant cytosolic location supports a cytoplasmic IHC readout; UniProt also lists autophagosomes, endoplasmic reticulum and mitochondria and reports no transmembrane segment (UniProt Q9Y4P1 localization and topology). These annotations do not require resolvable organelle staining in chromogenic tissue IHC. |
| IHC antibody evidence | The listed IHC antibody CAB037195 is Approved, while HPA reports only medium agreement between tissue staining and RNA and says presumed off-target binding was disregarded (HPA antibody validation; HPA tissue IHC reliability). Interpret unexpected compartments or cells with that qualification in mind. |
| IF/ICC Q: Is nuclear fluorescence an expected tissue-IHC result? | HPA approves nucleoplasm and cytosol in ICC-IF images from MCF-7 and RT-4, but disregards nuclear staining in tissue IHC (HPA subcellular ICC-IF; HPA tissue IHC reliability). Interpret each assay against its own evidence; this section gives no IF/ICC protocol option. |
| Mitochondrial subset | UniProt describes a small mitochondrial portion and reports that Ser-34 phosphorylation promotes mitochondrial localization (UniProt Q9Y4P1 localization). Its presence does not make mitochondrial enrichment a routine tissue-IHC acceptance criterion; HPA's reported tissue pattern remains cytoplasmic (HPA tissue IHC). |
| Situation | Likely cause | Next action |
|---|---|---|
| High nuclear signal in paraffin tissue sections. | HPA considered nuclear tissue-IHC staining off target, even though nucleoplasmic ICC-IF localization is Approved (HPA tissue IHC reliability; HPA subcellular ICC-IF). | Assess the cytoplasmic pattern separately, include a no-primary control, and avoid scoring nuclei as positive tissue-IHC evidence without independent specificity support (general IHC practice; HPA tissue IHC reliability). |
| No signal in expected positive glandular cells. | Appendix, colon and duodenal glandular cells are High in HPA tissue IHC; an absent result may reflect assay performance or the sampled cell population (HPA tissue IHC; general IHC practice). | Confirm the cells on a counterstained section, then review antigen retrieval, primary-antibody conditions and detection-system controls as general IHC checks; no ATG4B-specific retrieval condition is supplied (general IHC practice). |
| Strong staining in an HPA Not detected cell population. | Unexpected color may represent nonspecific antibody binding or endogenous detection activity; HPA itself notes disregarded presumed off-target staining (general IHC practice; HPA tissue IHC reliability). | Verify cell identity and compare no-primary and detection controls before assigning ATG4B positivity (general IHC practice). |
| Uniform haze or color outside cells. | Background can obscure the cell-bound cytoplasmic profile reported by HPA (general IHC practice; HPA tissue IHC profile). | Check no-primary controls, blocking, washing and chromogen development; judge the result only where cell boundaries and compartment are interpretable (general IHC practice). |
| Weak staining in a tissue expected to be positive. | HPA levels are cell-specific: lung macrophages and pancreatic exocrine glandular cells are Medium, and several other listed cell types are Low (HPA tissue IHC). | Identify the exact cell population and compare it with its HPA level before adjusting assay conditions; use a High glandular-cell example as a positive reference when available (HPA tissue IHC; general IHC practice). |
| Puncta or apparent organelle enrichment dominate the slide. | UniProt lists autophagosome, endoplasmic reticulum and mitochondrial locations, but HPA summarizes tissue IHC as cytoplasmic; organelle identity cannot be assigned from chromogenic appearance alone (UniProt Q9Y4P1 localization; HPA tissue IHC; general IHC practice). | Record the compartment and cell type, check specificity controls, and require independent compartment evidence before naming an organelle (general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded. Nuclear staining was considered off target and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Hippocampus | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Lung | Macrophages | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Cervix | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Endometrium | Cells in endometrial stroma | Not detected | Protein (IHC) | HPA → |
Troubleshoot ATG4B staining in paraffin sections by checking retrieval, cytoplasmic localisation and tissue controls before interpreting chromogenic signal (UniProt Q9Y4P1; HPA tissue IHC).
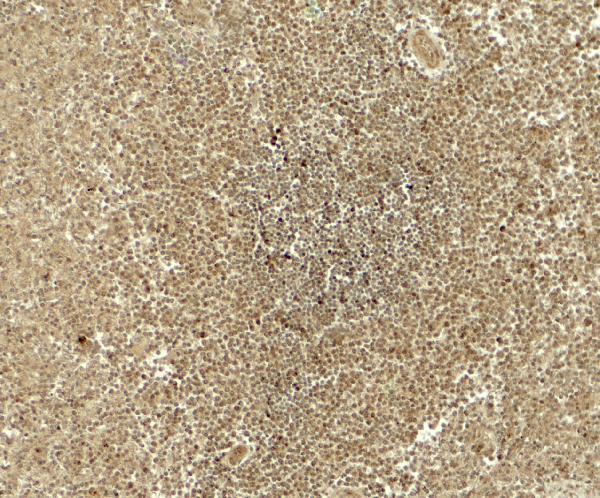
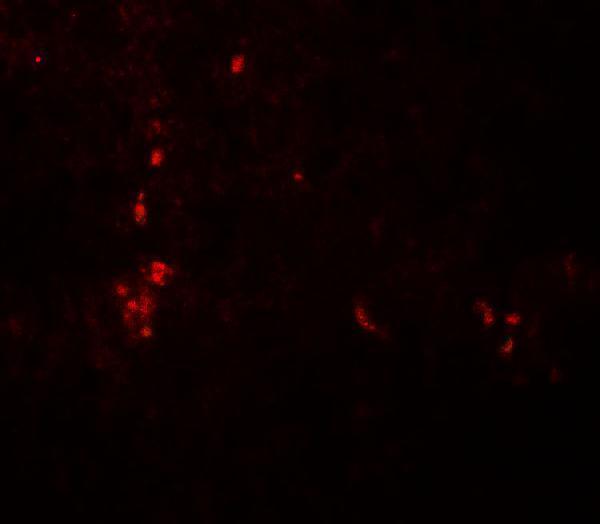
ATG4B antibody A02885 has human spleen IHC and IF images (catalog image captions); its listed reactivity covers human, mouse, and rat (catalog: reactivity).
A02885 has an IHC image of human spleen tissue at 5 μg/mL (catalog: IHC image caption). The same SKU has an IF image of human spleen tissue at 20 μg/mL (catalog: IF image caption).
Which to pick: Choose A02885 for paraffin section IHC (catalog: IHC-P application); its IHC image shows human spleen tissue, but the caption does not report the fixative (catalog: IHC image caption). Choose A02885 for IF (catalog: IF application and IF image caption); ICC is not listed as a tested application (catalog: applications). For mouse or rat work, A02885 lists both species as reactive, although its supplied IHC and IF images show human tissue; the host is rabbit and clonality is unreported (catalog: reactivity, image captions, host, clone).