This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
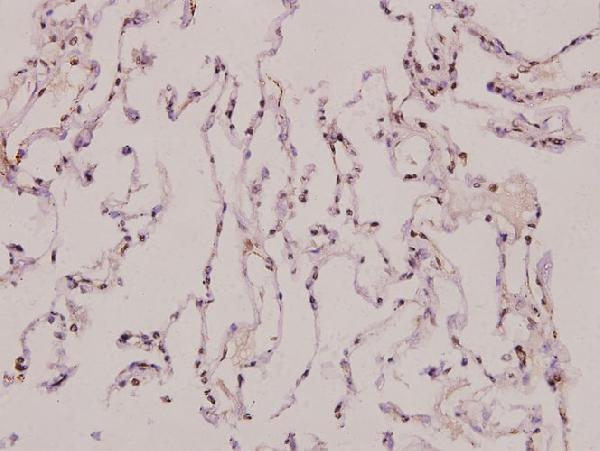
Plan ATP5MF paraffin IHC around cytoplasmic staining in most tissues (HPA tissue IHC). The catalog antibody is shown staining paraffin-embedded human lung carcinoma at 1:100 (catalog IHC image caption).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining (HPA tissue IHC); inner mitochondrial membrane (UniProt) | |
| Staining pattern | Cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A32262) | |
| Caveat | Some cell types lack staining despite the broad tissue profile (HPA tissue IHC) | |
| Regulation | No specific expression regulator reported (UniProt) | |
| Isoform / epitope | 4 isoforms; epitope coverage is not given in the record (UniProt) |
The catalog antibody IHC-P protocol (datasheet) is accompanied by a published ATP5MF IHC protocol using clinical breast cancer tissue sections (PMC11472516).
| Sample | Paraffin-embedded human lung carcinoma tissue; fixative not specified (datasheet A32262) |
| Fixation | Image fixative and duration unreported (datasheet A32262); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ATP5MF, 1:50-1:200 (datasheet A32262) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ATP5MF-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
ATP5MF is a mitochondrial inner-membrane subunit with 1 transmembrane segment at residues 68–85 (UniProt P56134 topology). In paraffin-section IHC, expect cytoplasmic staining in many tissues, especially kidney tubule cells and glandular cells of the adrenal, breast, parathyroid, rectum, salivary gland and stomach, where HPA reports High staining (HPA tissue IHC). HPA rates its tissue profile Approved, with medium consistency against RNA data and external verification pending (HPA tissue IHC).
| Cytoplasmic staining in kidney tubule cells or one of the listed high-staining glandular cell populations (HPA tissue IHC). | This matches the reported IHC distribution (HPA tissue IHC). A granular cytoplasmic appearance is compatible with mitochondrial localisation (UniProt P56134; HPA subcellular), but staining alone does not prove organelle identity (standard IHC practice). |
| Predominantly nuclear or cell-surface chromogen in an otherwise positive tissue (HPA tissue IHC). | This conflicts with the expected mitochondrial inner-membrane location (UniProt P56134). Assess specificity and detection background before interpreting it as ATP5MF (standard IHC practice). HPA's additional nuclear-membrane IF location is uncertain and does not establish a nuclear IHC pattern (HPA subcellular). |
| Strong staining of a cell population reported as Not detected, such as adipocytes or lymph-node germinal-center cells (HPA tissue IHC). | The discrepancy warrants checking cross-reactivity and endogenous detection activity (standard IHC practice). HPA's Not detected category describes its observed specimens; it does not prove that every specimen of that cell type must be negative (HPA tissue IHC). |
| Diffuse chromogen across tissue and surrounding spaces, without a clear cellular pattern (standard IHC practice). | This is difficult to score as ATP5MF: the reported tissue signal is cytoplasmic and the protein is mitochondrial (HPA tissue IHC; UniProt P56134). Review blocking, washing and detection controls for nonspecific background (standard IHC practice). |
| No discernible staining in kidney tubules or the listed high-staining glandular cells (HPA tissue IHC). | An absent signal in these reference-positive populations calls for an assay check, including section quality, retrieval, primary-antibody conditions and detection controls (standard IHC practice). HPA's Approved rating has only medium RNA concordance and awaits external verification (HPA tissue IHC). |
| Compartment and topology | ATP5MF resides in the mitochondrial inner membrane and has 1 transmembrane segment at residues 68–85 (UniProt P56134). This supports cytoplasmic, mitochondrial-compatible interpretation; the supplied record does not locate the antibody epitope or establish a retrieval condition. |
| Tissue and cell context | HPA reports cytoplasmic expression in most tissues, but levels differ by cell population (HPA tissue IHC). Its High kidney-tubule and listed glandular observations are useful comparators; its Not detected calls are observed results, not universal exclusions (HPA tissue IHC). |
| Antibody evidence | HPA070412 has Approved IHC status; HPA067267 has no supplied IHC status (HPA antibodies). The tissue profile itself has medium antibody–RNA consistency and pending external verification (HPA tissue IHC). Interpret unexpected staining with that evidence limit in mind. |
| IF/ICC Q: What localisation should a separate IF/ICC guide expect? | A: Mainly mitochondria; HPA marks this location supported (HPA subcellular). Its additional nuclear-membrane location is uncertain, so treat that signal cautiously (HPA subcellular). Both listed antibodies have Supported ICC status (HPA antibodies). |
| Protein forms | UniProt lists 4 isoforms and a chain spanning residues 2–94 (UniProt P56134). These annotations do not identify which forms a given IHC antibody detects; avoid assigning cell-level intensity differences to isoforms without antibody-specific evidence. |
| Situation | Likely cause | Next action |
|---|---|---|
| A high-staining reference population gives little or no chromogen (HPA tissue IHC). | Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation. | Check section integrity, retrieval, primary-antibody conditions and detection with appropriate controls, then reassess the reference population (standard IHC practice). |
| Nuclear staining dominates the section (standard IHC practice). | Nuclear staining conflicts with the mitochondrial inner-membrane assignment (UniProt P56134). HPA labels its additional nuclear-membrane IF finding uncertain (HPA subcellular). | Compare the same run with positive tissue and detection controls; score nuclear-only chromogen separately from the expected cytoplasmic signal (HPA tissue IHC; standard IHC practice). |
| Chromogen appears in HPA Not detected cells, such as adipocytes (HPA tissue IHC). | Cross-reactivity or endogenous detection activity may contribute (standard IHC practice); HPA's category is specimen-based evidence (HPA tissue IHC). | Review the primary-omission and detection controls, then compare cell identity and staining distribution with HPA's observed pattern (standard IHC practice; HPA tissue IHC). |
| Background obscures cell boundaries or intracellular detail (standard IHC practice). | Nonspecific antibody binding or detection background can impair interpretation (standard IHC practice). | Review blocking, washing and primary-antibody conditions using matched controls; interpret ATP5MF only when cellular signal separates from background (standard IHC practice). |
| Signal is present, but mostly on cell surfaces (standard IHC practice). | A surface-dominant pattern does not fit an inner-mitochondrial-membrane protein (UniProt P56134). | Check detection controls and antibody specificity, and compare with the cytoplasmic pattern reported in tissue IHC (standard IHC practice; HPA tissue IHC). |
| Two samples differ markedly in staining intensity (standard IHC practice). | HPA reports variable cell-population levels, from High to Not detected, while its tissue profile has medium RNA concordance (HPA tissue IHC). | Compare like cell populations under matched staining and scoring conditions; document any departure from HPA's observations without treating them as absolute expression limits (standard IHC practice; HPA tissue IHC). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Parathyroid gland | Glandular cells | High | Protein (IHC) | HPA → |
| Rectum | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Lymph node | Germinal center cells | Not detected | Protein (IHC) | HPA → |
| Oral mucosa | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Placenta | Decidual cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot ATP5MF chromogenic staining in paraffin sections using mitochondrial localisation, tissue IHC patterns, and the selected antibody’s caption as reference points (UniProt P56134; HPA tissue IHC; A32262 caption).
The IHC-validated ATP5MF antibody A32262 has a paraffin-embedded human lung carcinoma image (A32262 image caption) and lists Human, Mouse, and Rat reactivity (A32262 catalog).
A32262 is listed for IHC (A32262 catalog). Its IHC image shows paraffin-embedded human lung carcinoma tissue at 1:100 (A32262 image caption).
Which to pick: For tissue IHC, choose A32262, a rabbit antibody with a listed IHC dilution of 1:50–1:200 (A32262 catalog); its image supports use on paraffin-embedded human lung carcinoma tissue (A32262 image caption). The caption does not report the fixative (A32262 image caption). For cross-species work, A32262 lists Human, Mouse, and Rat reactivity, but its catalog lists no IF/ICC application or image, so there is no supported IF/ICC pick (A32262 catalog).