BCKDHA / 2-oxoisovalerate dehydrogenase subunit alpha, mitochondrial · IHC design guide

Design Immunohistochemistry for BCKDHA

Plan paraffin-section BCKDHA IHC around the granular cytoplasmic pattern observed across tissues (HPA tissue IHC). Use the catalog antibody’s IHC conditions and assess staining with the reported off-target binding caution in mind (datasheet A04561-1; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for BCKDHA (IHC for BCKDHA): expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial matrix expected (UniProt), antibody A04561-1, validated IHC image, and IHC protocol steps
Printable BCKDHA IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial matrix expected (UniProt), antibody A04561-1, controls and protocol steps. Open the full BCKDHA IHC guide →

BCKDHA Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial matrix expected (UniProt)
Staining pattern Many cell types show granular cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04561-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Presumed off-target binding may mimic staining (HPA tissue IHC)
Regulation Expression regulator not specified (UniProt)
Isoform / epitope 2 isoforms; chain 46–445; epitope impact unknown (UniProt)
Section 1

Recommended BCKDHA IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by one published BCKDHA protocol using a colorectal cancer tissue microarray (PMC13324575).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A04561-1)
FixationImage fixative and duration unreported (datasheet A04561-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04561-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04561-1)
Primary antibodyRabbit anti-BCKDHA, 2-5 μg/ml (datasheet A04561-1)
Primary incubationOvernight at 4 °C (datasheet A04561-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A04561-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultBCKDHA-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression with a granular, mitochondrial pattern. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A04561-1); the published protocol does not specify retrieval (PMC13324575).
Section 2

What Is the Expected BCKDHA Staining Pattern?

BCKDHA is a mitochondrial matrix protein without a transmembrane segment (UniProt P12694: location and topology). In paraffin-section IHC, expect granular cytoplasmic staining across many tissues, including strong staining in selected glandular, epithelial, hematopoietic and adipocyte populations (HPA: ubiquitous granular mitochondrial profile; listed cell types High). HPA rates the tissue pattern Supported but cautions that presumed off-target binding was observed and disregarded (HPA: reliability summary).

What am I looking at on my slide?
Granular cytoplasmic signal in adrenal glandular cells or bronchial respiratory epithelial cells.This matches the reported mitochondrial pattern in cell populations scored High (HPA: tissue IHC). Evaluate granularity and cell identity together; chromogenic signal alone does not prove mitochondrial identity or antibody specificity (standard IHC interpretation).
Predominantly nuclear, surface-membrane or other sharply noncytoplasmic staining.This conflicts with matrix localization and the reported granular cytoplasmic profile (UniProt P12694: location and topology; HPA: tissue IHC). Review controls and staining conditions before assigning it to BCKDHA (standard IHC practice).
Strong staining confined to a cell population different from the one expected in the chosen section.Compare the population with that tissue’s HPA entry before calling it unexpected; BCKDHA staining is broadly distributed (HPA: tissue IHC). If the distribution remains discordant, consider cross-reactivity or endogenous detection activity, especially given HPA’s off-target caution (HPA: reliability summary; standard IHC practice).
Uniform brown haze over cells and surrounding section, obscuring granules.This is difficult to interpret as the reported granular cytoplasmic pattern (HPA: tissue IHC). Background from detection reagents or insufficient blocking is a general IHC possibility; assess reagent controls before scoring cells (standard IHC practice).
No discernible signal in a section containing an HPA-listed High cell population.Check that the expected cells are present: examples include breast adipocytes and bone-marrow hematopoietic cells (HPA: tissue IHC). An absent signal warrants review of the antibody and IHC workflow; the record does not establish BCKDHA-specific fixation sensitivity.
💡Expected BCKDHA appearanceCall a result consistent with BCKDHA when staining is granular and cytoplasmic in an HPA-listed High cell population; predominantly nuclear signal or uniform haze is discordant (HPA: tissue IHC; UniProt P12694: location).
How each factor affects the staining
Compartment and processingThe annotated mature chain spans residues 46–445 and localizes to the mitochondrial matrix; no transmembrane segment is annotated (UniProt P12694). The supplied record does not locate the antibody epitope, so it cannot predict epitope accessibility.
Isoforms and modified residuesTwo isoforms and several modified residues are annotated (UniProt P12694). Without an antibody epitope or isoform-specific validation, the record cannot establish which forms contribute to IHC staining or whether modifications change it.
Antibody validationThe listed antibody HPA036640 has Supported IHC status; HPA also cautions that presumed off-target binding was observed and disregarded (HPA: antibody record and reliability summary). Interpret an atypical pattern with controls rather than treating validation as proof for every cell.
Tissue selectionHPA lists High staining in several specified populations and no negative or low examples in this payload (HPA: tissue IHC). Select a listed High population as a reference; the supplied data do not justify labeling another tissue a true negative.
Can IF/ICC resolve the pattern?The HPA subcellular entry supplies no main location or ICC-IF images, so it offers no image-based IF confirmation here (HPA: subcellular record). IF/ICC has its own guide; this IHC section makes no IF protocol recommendation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A listed High population is unstained.The section may lack the intended cells, or an IHC workflow step may have failed (HPA: listed High populations; standard IHC practice).Confirm cell identity and tissue preservation, then review retrieval, antibody application and chromogenic detection with appropriate controls (standard IHC practice). No BCKDHA-specific retrieval or fixation effect is established.
Brown signal is mainly nuclear or along the cell surface.That distribution disagrees with the annotated matrix location and HPA granular cytoplasmic profile (UniProt P12694; HPA: tissue IHC).Compare a listed High population and reagent controls; reassess specificity before scoring the discordant compartment as BCKDHA (HPA: tissue IHC; standard IHC practice).
The whole section has diffuse brown background.Nonspecific reagent binding or endogenous detection activity can obscure localized signal (standard IHC practice).Inspect no-primary and detection controls, then optimize blocking, washing or detection according to the assay chemistry (standard IHC practice); look again for discrete cytoplasmic granules (HPA: tissue IHC).
An unexpected cell population stains more strongly than the expected one.Broad expression complicates a simple positive-versus-negative call, and the HPA reliability note flags presumed off-target binding (HPA: tissue IHC and reliability summary).Check that tissue’s recorded cell-level pattern and examine controls before assigning the signal to BCKDHA; avoid declaring an unlisted population negative (HPA: tissue IHC; standard IHC practice).
Granular staining varies among otherwise comparable sections.Section quality or IHC processing can vary (standard IHC practice); the supplied sources do not attribute such variation to BCKDHA fixation sensitivity.Compare tissue morphology, control staining and processing records across sections before interpreting intensity differences as biology (standard IHC practice).
An IF/ICC image is sought to verify a chromogenic result.The supplied HPA subcellular record has no ICC-IF images or reported main location (HPA: subcellular record).Use the UniProt matrix annotation and HPA tissue IHC profile to frame the IHC interpretation; consult the separate IF/ICC guide for that application (UniProt P12694; HPA: tissue IHC).

Sample controls for BCKDHA IHC & IF

🧪Run breast first: adipocytes are scored High for BCKDHA (HPA: High in breast adipocytes). HPA detects BCKDHA in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and treat unstained cells outside the adipocyte compartment as background comparators rather than confirmed BCKDHA-negative cells (HPA: no negative tissue rows).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: BCKDHA is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for BCKDHA; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only slide, a concentration-matched rabbit IgG isotype control matched to the primary antibody’s clonality, and a BCKDHA-knockout sample or validated peptide-block control (selected-SKU caption: rabbit primary antibody; standard IHC controls). Quench endogenous peroxidase and check for endogenous biotin in breast tissue before interpreting the biotin-based DAB signal (selected-SKU caption: SABC/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the fixative in the selected-SKU paraffin-section caption is unreported (selected-SKU caption: fixative not stated). The caption demonstrates heat retrieval in EDTA pH 8.0, but does not establish that this retrieval condition is required; the supplied evidence does not establish whether frozen sections or IF are easier (selected-SKU caption: EDTA retrieval; HPA: no ICC-IF images). In breast adipocytes, lipid vacuoles leave a thin cytoplasmic rim, so score cytoplasmic staining rather than empty vacuoles (HPA: High in breast adipocytes; standard tissue morphology).

HPA tissue IHC evidence for BCKDHA

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Caution, targets protein from more than one gene. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: BCKDHA is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced BCKDHA IHC Tips

Troubleshoot BCKDHA staining in paraffin sections by checking retrieval, mitochondrial localisation, assay controls and scoring before interpreting differences between samples.

Which retrieval condition should I start with for BCKDHA in paraffin sections?
Start with heat mediated retrieval in EDTA pH 8.0 for paraffin sections (datasheet A04561-1). The selected antibody produced tissue staining after this treatment, followed by 2 μg/ml primary antibody overnight at 4°C (datasheet A04561-1). If staining is weak, first check that sections received consistent heating and cooling, then compare retrieval durations on adjacent sections while holding antibody concentration and detection constant (general IHC practice). Judge the result by granular cytoplasmic signal, the reported tissue pattern, while watching for diffuse background or damaged morphology (HPA: tissue IHC profile; general IHC practice).
How should I troubleshoot weak BCKDHA staining when fixation conditions vary?
Target specific sensitivity to fixation is unknown: the selected tissue image identifies a paraffin section but does not state its fixative (datasheet A04561-1 caption). Record each specimen’s fixative and fixation duration, and compare adjacent sections processed with the same retrieval and detection conditions (general IHC practice). Begin with EDTA pH 8.0 heat retrieval and 2 μg/ml primary antibody overnight at 4°C, matching the selected image conditions (datasheet A04561-1). If staining differs between specimens, evaluate morphology and a consistently processed positive control before attributing the difference to BCKDHA abundance (general IHC practice).
What staining pattern is plausible for BCKDHA, and how should I assess diffuse signal?
BCKDHA resides in the mitochondrial matrix and has no annotated transmembrane segment (UniProt P12694: localisation and topology). In tissue IHC, expect granular cytoplasmic staining, consistent with the reported ubiquitous mitochondrial pattern; nuclear only staining deserves scrutiny (HPA: tissue IHC profile; UniProt P12694: localisation). Compare suspect regions with intact neighbouring cells and a matched control section, keeping counterstain and development consistent (general IHC practice). If granules disappear while the entire section becomes uniformly brown, review retrieval, antibody concentration and detection background before scoring the signal as BCKDHA (general IHC practice).
Can this IHC stain distinguish BCKDHA isoforms or phosphorylation states?
Two BCKDHA isoforms are listed, but the supplied antibody caption does not identify an epitope or establish isoform discrimination (UniProt P12694: isoforms; datasheet A04561-1 caption). BCKDHA also has annotated phosphorylation near residues 337–347 and an alternate acetylation annotation at 356 (UniProt P12694: modified residues). Treat the chromogenic result as antibody dependent total immunoreactivity until epitope mapping or an appropriate modified residue specific validation supports a narrower claim (general IHC interpretation). Compare a second antibody with a documented distinct epitope, or a suitable loss of target control, if isoform or modification specificity is central to the experiment (general IHC practice).
How can I use IF to investigate the BCKDHA pattern seen by IHC?
Use a separate IF validation series; the selected antibody evidence describes chromogenic staining of a paraffin section, with its fixative unreported (datasheet A04561-1 caption). Pair BCKDHA with a mitochondrial marker and a marker identifying the expected cell population, then inspect single channel images before interpreting overlap (UniProt P12694: mitochondrial matrix; general IF practice). Choose spectrally separated fluorophores and place the weaker signal away from channels dominated by tissue autofluorescence, using unstained controls to assess that background (general IF practice). Because BCKDHA is matrix localised, optimise permeabilisation to allow antibody access across mitochondrial membranes while preserving mitochondrial structure (UniProt P12694: localisation; general IF practice).
How do I separate genuine BCKDHA signal from brown background?
The selected chromogenic workflow used 10% goat serum block, a biotinylated secondary antibody, streptavidin biotin complex and DAB (datasheet A04561-1 caption). Run a no primary control and inspect pigment, section folds and exposed edges before changing the BCKDHA antibody concentration (general IHC practice). Include appropriate peroxidase blocking, and assess whether endogenous biotin contributes to signal when using this detection system (general IHC practice; datasheet A04561-1 caption). Prefer crisp granular cytoplasmic staining over uniform haze, but confirm doubtful patterns with controls because the HPA tissue profile notes presumed off target binding (HPA: tissue IHC profile and reliability).
How should I score BCKDHA staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the eligible cell population and compartment before scoring: the reported tissue pattern is granular cytoplasmic, consistent with mitochondrial BCKDHA (HPA: tissue IHC profile; UniProt P12694: localisation). For cell based comparisons, record the percentage of positive eligible cells and an H-score using a consistent intensity scale; for spatial questions, report positive cell density per mm² of viable tissue (general IHC practice). Normalise each result to the eligible cell count or viable tissue area, and keep staining, imaging and thresholds consistent across samples (general IHC practice). Exclude folds, necrosis and edges using criteria set before reviewing group labels (general IHC practice).
When is BCKDHA staining convincing rather than an artefact?
Convincing staining is granular and cytoplasmic in intact cells, matching the reported tissue pattern and BCKDHA mitochondrial matrix localisation (HPA: tissue IHC profile; UniProt P12694: localisation). A signal confined to nuclei, necrotic debris or section edges warrants investigation with morphology and a no primary control (UniProt P12694: localisation; general IHC practice). Check endogenous peroxidase and, for the selected streptavidin biotin workflow, endogenous biotin before treating brown precipitate as antigen signal (general IHC practice; datasheet A04561-1 caption). Interpret apparent differences cautiously because the HPA assessment reports presumed off target binding, and confirm consequential findings with an independent specificity control (HPA: tissue IHC reliability; general IHC practice).
Boster reagents

Best BCKDHA / 2-oxoisovalerate dehydrogenase subunit alpha, mitochondrial IHC Antibodies

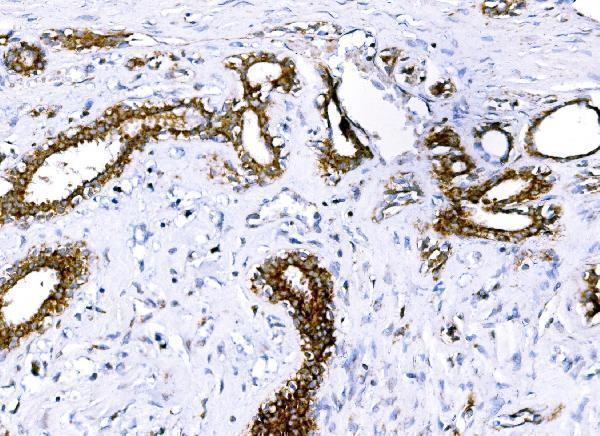
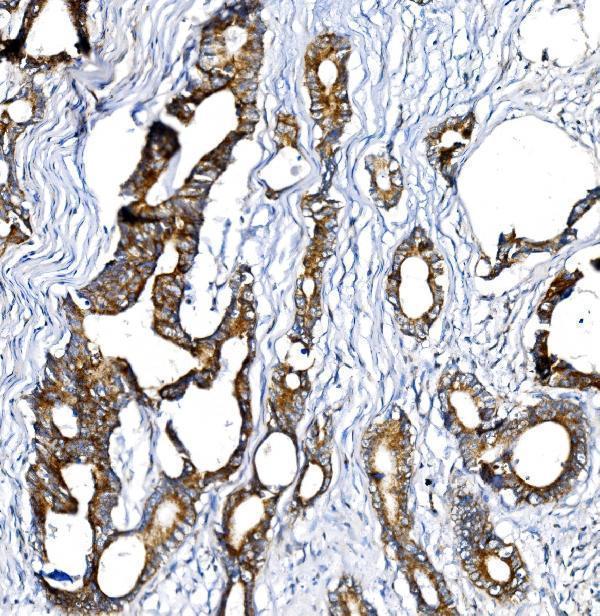
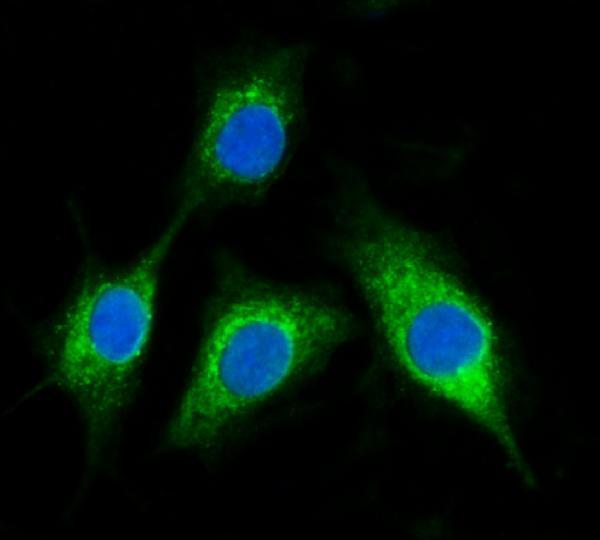
A04561-1 has IHC images from paraffin-embedded human breast, colon and liver cancer sections and an IF/ICC image from A549 cells (catalog IHC/IF captions); listed reactivity includes human, mouse and rat (catalog).

Real IHC data IHC analysis of BCKDHA using anti-BCKDHA antibody (A04561-1). BCKDHA was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-BCKDHA Antibody (A04561-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-BCKDHA Antibody ®
Cat # A04561-1

A04561-1 will render with its human breast cancer paraffin-section IHC figure; the catalog also shows human colon and liver cancer paraffin-section IHC images (catalog IHC captions). It is listed for IHC, ICC and IF in human, mouse and rat, with an IF/ICC image from A549 cells (catalog applications/reactivity; catalog IF caption).

Which to pick: Choose A04561-1 for paraffin-section IHC: its IHC caption documents EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody overnight at 4°C (catalog IHC caption); the fixative is unreported (catalog IHC caption). Choose the same SKU for IF/ICC based on its A549 cell image and 5 μg/ml listed IF dilution (catalog IF caption; datasheet: 5 μg/ml). For mouse or rat work, A04561-1 lists reactivity with both species, while the supplied IHC images show human tissue only; its host is rabbit and clonality is unreported (catalog reactivity/host; catalog IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P12694 (ODBA_HUMAN, 2-oxoisovalerate dehydrogenase subunit alpha, mitochondrial).
  2. Human Protein Atlas. BCKDHA tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. BCKDHA subcellular location (ICC-IF): Highest expression in HEL: 69.8 nTPM.
  4. Human Protein Atlas. BCKDHA antibody validation summary (1 antibodies).
  5. Identification of neoadjuvant chemoradiotherapy resistance-associated proteins in locally advanced rectal cancer: A pilot study. Oncology letters 2026 — PMC13324575.
  6. PPM1K mediates metabolic disorder of branched-chain amino acid and regulates cerebral ischemia-reperfusion injury by activating ferroptosis in neurons. Cell death & disease 2023 — PMC10522625.
  7. Loss of BCAA catabolism enhances Rab1A-mTORC1 signaling activity and promotes tumor proliferation in NSCLC. Translational oncology 2023 — PMC10209880.
  8. PubMed PMID:1420356 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:15057824 — UniProt-cited evidence.