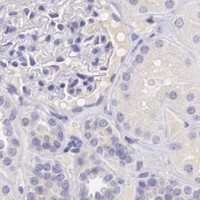
BCL6 / B-cell lymphoma 6 protein · IHC design guide

Design Immunohistochemistry for BCL6

Plan BCL6 IHC around nuclear staining in germinal center cells of tonsil and lymph node (HPA tissue IHC). This guide covers fixation, staining controls and interpretation for paraffin sections.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for BCL6 (IHC for BCL6): expected localisation Nuclear staining in several tissues (HPA tissue IHC), antibody M00142, validated IHC image, and IHC protocol steps
Printable BCL6 IHC protocol sheet — expected localisation Nuclear staining in several tissues (HPA tissue IHC), antibody M00142, controls and protocol steps. Open the full BCL6 IHC guide →

BCL6 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in several tissues (HPA tissue IHC)
Staining pattern Nuclear staining in lymphoid germinal center cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet M00142)
Positive control ⓘ Cerebellum+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat Germinal center T cells also express BCL6 (UniProt)
Regulation Expressed in germinal center T and B cells (UniProt)
Isoform / epitope 2 isoforms; epitope impact is unspecified (UniProt)
Section 1

Recommended BCL6 IHC & IF Protocols

Compare the catalog antibody’s citrate pH 6 protocol (datasheet: M00142) with four published BCL6 IHC workflows (PMC2676553; PMC5219810; PMC9346488; PMC5680041).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleFormaldehyde-fixed, paraffin-embedded Human tonsil tissue (datasheet M00142)
FixationImage formalin-fixed; duration unreported (datasheet M00142); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6 (datasheet M00142); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-BCL6, 1:25 (datasheet M00142)
Primary incubation1 hours at 37°C (datasheet M00142)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultBCL6-positive staining in gLUC cells - nucleus of cerebellum (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in several tissues, including lymphoid tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6 heat retrieval (datasheet: M00142); the published alternatives include Tris–EDTA pH 9 (PMC9346488) and CC1 conditioning (PMC5680041).
Section 2

What Is the Expected BCL6 Staining Pattern?

BCL6 should stain nuclei, especially germinal center cells in tonsil and lymph node, where HPA reports high staining (HPA: tissue IHC; UniProt P41182: nucleus). It has no transmembrane segment or signal peptide, supporting a nuclear interpretation rather than a surface pattern (UniProt P41182: topology and processing). HPA rates the tissue profile Enhanced, while describing medium consistency between staining and RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Strong, discrete nuclear staining in germinal center cells, with less staining outside those areas.This matches the clearest tissue positive controls: HPA reports high staining in germinal center cells of tonsil and lymph node (HPA: tissue IHC). Score the fraction and intensity of stained nuclei in the relevant cells, rather than treating every unstained cell on the section as a failed assay (general IHC practice).
Predominantly membranous or broad cytoplasmic staining, without convincing stained nuclei.That distribution conflicts with the expected nuclear signal (UniProt P41182: nucleus; HPA: nuclear tissue expression). Consider nonspecific antibody binding or detection artefact. Review a known-positive control on the same run and inspect the nuclear compartment before calling the sample BCL6 positive (general IHC practice).
Strong staining in a cell population expected to be negative, such as adipocytes.HPA reports BCL6 as not detected in adipocytes of adipose tissue (HPA: tissue IHC). Unexpected staining warrants a cross-reactivity or endogenous detection-activity check; it does not alone establish either cause. Compare morphology and a no-primary control under the same detection conditions (general IHC practice).
Uniform chromogen haze across cells or tissue spaces obscures nuclear boundaries.A diffuse field is difficult to score as BCL6 because the supported signal is nuclear (HPA: tissue IHC; UniProt P41182: nucleus). Check the no-primary control, blocking and washes, then reassess whether individual nuclei remain distinguishable (general IHC practice).
No nuclear staining in tonsil or lymph node germinal center cells.This contradicts the high staining reported for those cells (HPA: tissue IHC). Treat the run as unresolved before interpreting a negative test section. Check control tissue preservation, primary-antibody application and the detection workflow; the supplied sources do not establish BCL6-specific fixation sensitivity (general IHC practice; HPA: tissue IHC).
💡Expected BCL6 appearanceA convincing positive is distinct, often high-intensity nuclear staining in tonsil or lymph node germinal center cells; diffuse haze or isolated cytoplasmic colour without nuclear definition is suspect (HPA: tissue IHC; UniProt P41182: nucleus).
How each factor affects the staining
Tissue and cell selectionTonsil or lymph node germinal center cells provide documented high IHC signal; adipocytes in adipose tissue provide a reported not-detected comparison (HPA: tissue IHC). These observations guide control selection but do not guarantee every specimen will match.
Antibody validation and tissue-profile reliabilityTwo listed antibodies have Enhanced IHC validation, while the overall HPA tissue profile reports medium agreement between staining and RNA data (HPA: antibody validation; HPA: tissue IHC reliability). Interpret a discordant sample with morphology and controls, rather than using validation status as proof of specificity in that sample.
Protein form and epitope informationUniProt lists 2 isoforms and one chain spanning residues 1–706, with no signal peptide or propeptide (UniProt P41182: isoforms and processing). The supplied record gives no antibody epitope location, so it cannot establish isoform-specific staining or predict an antigen-retrieval condition.
IF/ICC Q: Which compartment should show BCL6 fluorescence?A: Primarily the nucleoplasm (HPA: ICC-IF, supported). HPA also lists Golgi localization as uncertain, so Golgi-only fluorescence needs caution (HPA: ICC-IF). This localization guidance supplies no IF/ICC protocol; the application here is paraffin-section chromogenic IHC.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive germinal center cells have no signal.A run or detection failure is possible because these cells show high HPA IHC staining (HPA: tissue IHC).Confirm that the positive-control area is present, then review primary incubation, antigen retrieval and detection steps against the IHC-validated antibody's instructions (general IHC practice). No BCL6-specific retrieval or fixation effect is established here.
Colour is mainly cytoplasmic or membranous.The pattern conflicts with nuclear BCL6 localization (UniProt P41182: nucleus; HPA: tissue IHC).Compare a known-positive nuclear control and a no-primary control. Recheck morphology and detection background before scoring; if the pattern persists, treat its specificity as unresolved (general IHC practice).
Adipocytes stain strongly.Adipocytes are reported as not detected in adipose tissue (HPA: tissue IHC); cross-reactivity or endogenous detection activity is possible.Run a no-primary control and inspect whether the same cells retain colour. If needed, review blocking and detection chemistry using general IHC controls (general IHC practice).
Diffuse background hides nuclear detail.Background staining may prevent separation of true nuclear signal from nonspecific colour (general IHC practice; UniProt P41182: nucleus).Check the no-primary slide, washes and blocking. Adjust workflow settings only against a positive control so loss of background is not mistaken for loss of BCL6 (general IHC practice).
A low or negative specimen is being called assay failure.Expression varies by cell type: HPA reports low staining in several cell populations and not-detected staining in others (HPA: tissue IHC).Judge run validity using a separate documented positive, such as tonsil germinal center cells, then report the tested cell population's observed nuclear staining (HPA: tissue IHC; general IHC practice).
ICC-IF shows a Golgi-like signal but little nucleoplasmic signal.HPA supports nucleoplasmic localization and marks its additional Golgi localization uncertain (HPA: ICC-IF).Treat the Golgi-only result as inconclusive; review nuclear counterstain alignment and fluorescence controls within the separate IF/ICC guide (general IF practice).

Sample controls for BCL6 IHC & IF

🧪Run tonsil first: germinal center cells should show BCL6 nuclear staining (HPA: High in tonsil germinal center cells; UniProt P41182: nucleus). Use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes); on the tonsil slide, assess cells outside germinal centers as internal low-signal comparators, without assuming every such cell is BCL6-negative (HPA: High in tonsil germinal center cells).
Positive control tissue: Cerebellum (GLUC cells - nucleus, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show BCL6 in A-549, U-251MG, U2OS, RT-4, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an isotype control matched to the primary antibody’s host species and clonality; and a BCL6 knockout sample or validated peptide-block control (standard IHC practice). For chromogenic tonsil IHC, block endogenous peroxidase and check background from the biotin-based detection system (M00142 tissue-IHC caption: biotinylated secondary; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact M00142 tissue-IHC caption does not establish the specimen fixative (M00142 tissue-IHC caption: fixative unreported). Heat-mediated citrate retrieval at pH 6 was used in the tonsil example; optimize retrieval for the specimens being tested (M00142 tissue-IHC caption). The supplied evidence does not establish whether frozen sections or IF are easier than paraffin IHC for BCL6; the tonsil chromogenic workflow should account for endogenous peroxidase and possible biotin-related background (M00142 tissue-IHC caption: biotinylated secondary; standard IHC practice).

HPA tissue IHC evidence for BCL6

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum GLUC cells - nucleus High Protein (IHC) HPA →
Lymph node Germinal center cells High Protein (IHC) HPA →
Testis Pachytene spermatocytes High Protein (IHC) HPA →
Tonsil Germinal center cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebral cortex Endothelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced BCL6 IHC Tips

Troubleshoot BCL6 staining by checking nuclear localisation, germinal center cell context, and matched controls before changing detection conditions (UniProt P41182; HPA tissue IHC).

What retrieval should I try when BCL6 nuclear staining is weak in paraffin sections?
Start with heat-mediated citrate retrieval at pH 6 for paraffin sections (datasheet M00142). If staining remains weak, adjust heating duration on matched sections while keeping the buffer and detection system constant, and inspect morphology after each change (standard IHC practice). Include tonsil germinal center cells as a positive reference and score nuclear staining separately from diffuse background (HPA tissue IHC: High in tonsil germinal center cells; UniProt P41182: nucleus). If retrieval damages morphology or raises background, return to the gentler condition and check antibody incubation and detection controls before changing buffer (standard IHC practice).
How should I troubleshoot weak BCL6 staining across differently fixed specimens?
BCL6-specific sensitivity to fixation is unknown from the supplied evidence, so assess it experimentally rather than assigning a target-specific effect (supplied fixation evidence: none). Compare matched sections with documented fixation histories under the same pH 6 citrate retrieval and detection conditions, recording nuclear intensity alongside tissue preservation (datasheet M00142; standard IHC practice). Use a tonsil germinal center reference in each run to distinguish a specimen-wide technical failure from variation within the specimen (HPA tissue IHC: High in tonsil germinal center cells; standard IHC practice). Do not infer fixation tolerance from BCL6 localisation or modified residues; neither establishes how its antibody epitope survives processing (UniProt P41182: nucleus and modified residues).
Should I count cytoplasmic or Golgi-like staining as BCL6 positive?
Prioritise nuclear chromogen when evaluating BCL6, because the protein is annotated as nuclear and tissue staining includes nuclear expression in lymphoid tissues (UniProt P41182: nucleus; HPA tissue IHC: nuclear expression). Mainly nucleoplasmic localisation is supported in cell imaging, whereas an additional Golgi location is uncertain, so Golgi-like staining alone needs independent validation before scoring (HPA subcellular). Examine a tonsil germinal center reference and a reagent control at the same detection settings to separate a reproducible nuclear pattern from nonspecific cytoplasmic deposit (HPA tissue IHC: High in tonsil germinal center cells; standard IHC practice). Document nuclear and nonnuclear signal separately rather than merging them into one positive category (standard IHC practice).
Could isoforms or modifications explain inconsistent BCL6 staining?
BCL6 has 2 annotated isoforms, but the supplied evidence does not locate this antibody's epitope within either one (UniProt P41182: isoforms 1 and 2; supplied epitope evidence: none). The protein also has a BTB domain at residues 32–99 and annotated phosphorylation and acetylation sites, which cannot by themselves establish antibody recognition (UniProt P41182: domains and modified residues). Compare matched sections under identical retrieval and detection conditions before attributing differences to an isoform or modification (standard IHC practice). Seek epitope mapping or an independently validated antibody if an isoform-specific conclusion is essential, and report the original stain as BCL6 immunoreactivity meanwhile (standard IHC practice).
How can I check a multiplex IF result against the BCL6 IHC pattern?
Use the chromogenic IHC result as a spatial reference, then assess BCL6 in the IF experiment with a marker identifying the expected germinal center cell population (HPA tissue IHC: High in germinal center cells; standard IF practice). Choose a fluorophore in a spectral region with low measured tissue autofluorescence and include single-color and unstained controls before interpreting colocalisation (standard IF practice). BCL6 is nuclear and has no transmembrane segment, so permeabilisation must permit antibody access to an intracellular epitope; optimise it for the IF specimen and antibody (UniProt P41182: nucleus and topology; standard IF practice). Compare nuclear signal within marker-defined cells rather than treating diffuse fluorescence as agreement with IHC (standard IF practice).
What should I adjust when BCL6 chromogen covers nuclei and surrounding tissue?
First compare the stained section with a no-primary control, then inspect whether deposit follows nuclei, tissue edges, or damaged regions (standard IHC practice; UniProt P41182: nucleus). The selected M00142 tonsil example used 3% BSA for 0.5 hour and a 1:25 primary incubation for 1 hour at 37°C; these are example conditions, not universal settings (M00142 tissue-IHC caption). Check wash quality and secondary-only signal, and apply an appropriate endogenous peroxidase block when using peroxidase detection (standard chromogenic IHC practice). Titrate antibody and detection on adjacent sections while retaining a tonsil germinal center reference, seeking distinct nuclear signal with acceptable background (HPA tissue IHC; standard IHC practice).
How should I quantify BCL6-positive nuclei across tissue regions? ⚠ ANSWER MARKED FOR VERIFICATION
Define the region and eligible nucleated cell population before scoring, then report the percentage of nuclei above a prespecified chromogen threshold (standard IHC quantification practice; UniProt P41182: nucleus). An H-score can combine intensity categories 0–3 with their percentages to give 0–300, provided every specimen uses the same scoring rule (standard IHC quantification practice). Alternatively, report positive nuclei per mm² together with total eligible nuclei per mm², so changes in cellularity are visible (standard IHC quantification practice). Normalise percentages to eligible cells within the annotated region, and analyse germinal centers separately when they are the biological focus (HPA tissue IHC: High in germinal center cells; standard IHC quantification practice).
How do I distinguish true BCL6 positivity from staining artefacts?
Treat crisp nuclear signal in an appropriate cell population as the strongest BCL6 pattern, using germinal center cells as a reference (UniProt P41182: nucleus; HPA tissue IHC: High in germinal center cells). Diffuse cytoplasmic-only deposit or strong staining restricted to section edges and necrotic areas should trigger review of morphology and controls before a positive call (standard IHC practice; HPA subcellular: Golgi location uncertain). Compare no-primary and, for enzyme detection, endogenous-enzyme controls where relevant to identify signal unrelated to primary antibody binding (standard chromogenic IHC practice). BCL6 expression also occurs outside germinal centers, so interpret any convincing nuclear signal in its tissue and cell context rather than assuming exclusivity (HPA tissue IHC: nuclear expression in several tissues).
Boster reagents

Best BCL6 / B-cell lymphoma 6 protein IHC Antibodies

The catalog includes BCL6 IHC images from human tonsil sections for both antibodies (M00142 image caption; M00142-1 image caption) and an IF image from Ramos cells for M00142-1 (M00142-1 IF image caption).

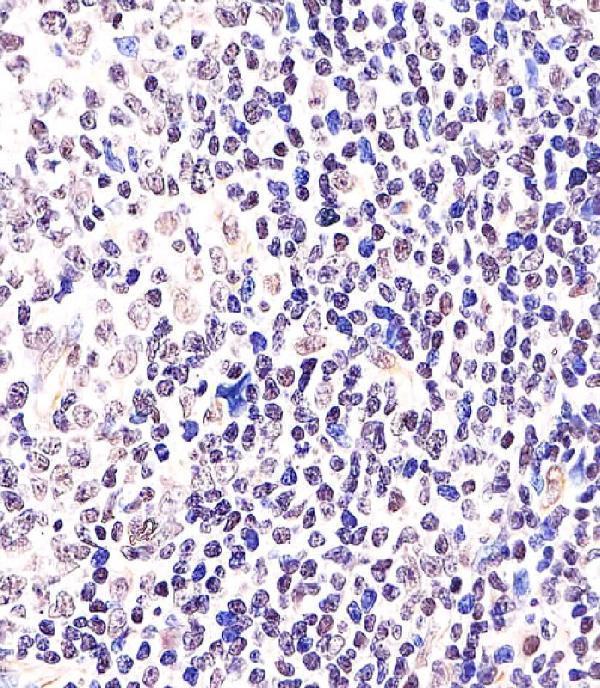
Real IHC data M00142 staining BCL6 in Human tonsil tissue sections by Immunohistochemistry (IHC-P -paraformaldehyde-fixed, paraffin-embedded sections). Tissue was fixed with formaldehyde and blocked with 3% BSA for 0. 5 hour at room temperature; antigen retrieval was by heat mediation with a citrate buffer (pH6). Samples were incubated with primary antibody (1/25) for 1 hours at 37°C. A undiluted biotinylated goat polyvalent antibody was used as the secondary antibody.
Anti-BCL6 Antibody (Center)
Cat # M00142
Real IHC data Immunohistochemical analysis of paraffin-embedded human tonsil, using Bcl-6 Antibody.
Anti-Bcl-6 Rabbit Monoclonal Antibody
Cat # M00142-1

M00142 shows IHC staining in formaldehyde-fixed, paraffin-embedded human tonsil; its listed reactivity is Human and Mouse (M00142 image caption; M00142 catalog). M00142-1 shows IHC staining in paraffin-embedded human tonsil and IF staining in Ramos cells (M00142-1 IHC image caption; M00142-1 IF image caption).

Which to pick: For tissue IHC with a documented fixation and retrieval example, choose M00142: its tonsil image reports formaldehyde fixation and heat retrieval in citrate buffer at pH 6 (M00142 image caption). For IF/ICC, choose the rabbit monoclonal M00142-1, which lists both applications and has a Ramos-cell IF image; its paraffin tonsil IHC caption does not report a fixative (M00142-1 catalog; M00142-1 IF image caption; M00142-1 IHC image caption). For Human/Mouse reactivity, choose M00142, while noting that its supplied IHC image shows human tonsil only (M00142 catalog; M00142 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P41182 (BCL6_HUMAN, B-cell lymphoma 6 protein).
  2. Human Protein Atlas. BCL6 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. BCL6 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the Golgi apparatus..
  4. Human Protein Atlas. BCL6 antibody validation summary (3 antibodies).
  5. BCL6 degradation caused by the interaction with the C-terminus of pro-HB-EGF induces cyclin D2 expression in gastric cancers. British journal of cancer 2009 — PMC2676553.
  6. Double-hit lymphomas: clinical, morphological, immunohistochemical and cytogenetic study in a series of Brazilian patients with high-grade non-Hodgkin lymphoma. Diagnostic pathology 2017 — PMC5219810.
  7. Developmental cell death of cortical projection neurons is controlled by a Bcl11a/Bcl6-dependent pathway. EMBO reports 2022 — PMC9346488.
  8. Recurrent BCOR internal tandem duplication and BCOR or BCL6 expression distinguish primitive myxoid mesenchymal tumor of infancy from congenital infantile fibrosarcoma. Modern pathology : an official journal of the United States and Canadian Academy of Pathology, Inc 2017 — PMC5680041.
  9. PubMed PMID:8220427 — UniProt-cited evidence.
  10. PubMed PMID:8235596 — UniProt-cited evidence.
  11. PubMed PMID:8274740 — UniProt-cited evidence.