This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan BCS1L paraffin-section IHC around the catalog antibody’s 1:50–1:200 dilution range (datasheet) and the reported cytoplasmic tissue pattern (HPA tissue IHC). Liver hepatocytes offer a high-staining control, while adipocytes were reported as unstained (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining (HPA tissue IHC); inner membrane molecular site (UniProt) | |
| Staining pattern | Widespread cytoplasmic staining across cell types (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue |
| Fixation | Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific) | |
| Caveat | Adipocytes may be unstained despite broad expression (HPA tissue IHC) | |
| Regulation | Ubiquitous expression; no regulator specified (UniProt) | |
| Isoform / epitope | No annotated isoforms; chain spans residues 2–419 (UniProt) |
Compare the catalog antibody’s IHC-P protocol with the published BCS1L protocol for formalin-fixed, paraffin-embedded FT and SOC tissues (PMC13039997).
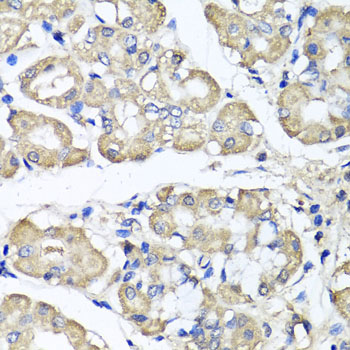
| Sample | Paraffin-embedded human stomach tissue; fixative not specified (datasheet A04885) |
| Fixation | Image fixative and duration unreported (datasheet A04885); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-BCS1L, 1:50-1:200 (datasheet A04885) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | BCS1L-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control. |
BCS1L is an inner mitochondrial membrane protein with residues 33–419 facing the matrix (UniProt Q9Y276 topology). In paraffin section IHC, expect cytoplasmic staining in many cell types (HPA: ubiquitous cytoplasmic expression), including strong staining in hepatocytes and several glandular epithelia (HPA: High). HPA rates the tissue IHC pattern Supported, with medium consistency between staining and RNA expression (HPA: reliability description).
| Strong cytoplasmic staining in hepatocytes or colon glandular cells, with cellular detail preserved. | This agrees with the reported High staining in those cells (HPA: liver and colon). A granular cytoplasmic appearance is compatible with mitochondrial residence (UniProt Q9Y276 subcellular location), although HPA tissue IHC describes the pattern only as cytoplasmic. Judge the compartment and cell identity together; intensity alone cannot establish specificity. |
| Predominantly nuclear or surface staining, with little discernible cytoplasmic signal. | That compartment conflicts with the reported cytoplasmic tissue pattern (HPA: tissue IHC) and inner mitochondrial membrane location (UniProt Q9Y276 topology). Treat it as a possible artefact until staining conditions and controls are reviewed. The supplied sources do not establish nuclear or surface BCS1L staining as an expected IHC result. |
| Strong staining in adipocytes, especially if the known-positive cells show little signal. | HPA reports BCS1L as Not detected in adipocytes (HPA: adipose tissue). Such a reversal raises concern for cross-reactivity or endogenous detection activity (general IHC practice). It is a comparison with the supplied HPA pattern, not proof that every adipocyte in every specimen must be negative. |
| Diffuse color across cells and tissue spaces, with no clear cytoplasmic boundaries. | This is difficult to score as BCS1L because HPA reports a cellular cytoplasmic pattern (HPA: tissue IHC). Excess antibody, incomplete blocking, or inadequate washing can produce diffuse background (general IHC practice). Compare a control without primary antibody and inspect whether the color follows tissue structure. |
| No staining in hepatocytes or another supplied High-staining cell population. | Absence in an expected positive population calls the run into question (HPA: High in hepatocytes and listed glandular cells). Review section integrity, retrieval, antibody application, and detection controls as general IHC practice. HPA's Supported rating has medium consistency with RNA data, so one negative specimen alone cannot settle biological absence (HPA: reliability description). |
| Where should the signal be assessed? | BCS1L spans the inner mitochondrial membrane once at residues 16–32, with residues 33–419 on the matrix side (UniProt Q9Y276 topology). This supports a cytoplasmic, mitochondria-compatible interpretation of IHC staining; tissue IHC does not resolve the membrane or establish an epitope position (HPA: cytoplasmic expression). |
| Which cells make useful pattern comparisons? | Hepatocytes and the supplied glandular and squamous epithelial populations are reported High, while adipocytes are Not detected and bone marrow hematopoietic cells are Low (HPA: tissue IHC). Use cell identity when comparing slides; ubiquitous expression and low RNA tissue specificity do not imply equal staining in every cell (UniProt Q9Y276 tissue specificity; HPA: RNA specificity). |
| How strong is the tissue IHC evidence? | Both listed antibodies, HPA037700 and HPA037701, have Supported IHC status (HPA: antibody validation). The overall tissue pattern is Supported with medium consistency between staining and RNA expression (HPA: reliability description). These labels support a reference pattern but do not independently prove the identity of every stained structure. |
| Does IF/ICC confirm the same compartment? | HPA's ICC-IF summary says mainly vesicles, with an additional mid-piece location; the vesicle assignment is Uncertain and the mid-piece assignment is Approved (HPA: subcellular ICC-IF). HPA037701 has Uncertain ICC status, while no ICC status is supplied for HPA037700 (HPA: antibody validation). Assess IF/ICC on its own guide page rather than treating these images as confirmation of mitochondrial IHC. |
| Do annotated variants or processing change the expected slide pattern? | The supplied UniProt record annotates no isoforms, signal peptide, propeptide, or glycosylation sites, and lists a chain from residues 2–419 (UniProt Q9Y276 processing). It therefore supplies no basis for predicting a separate secreted or cleaved staining compartment. These annotations also provide no target-specific fixation-sensitivity claim. |
| Situation | Likely cause | Next action |
|---|---|---|
| The positive tissue is blank, including hepatocytes. | The result disagrees with High hepatocyte staining (HPA: liver); a failed IHC run remains possible (general IHC practice). | Check the positive-control section, primary antibody application, detection reagents, and counterstain. Review retrieval as a general IHC variable; no BCS1L-specific retrieval or fixation response is supplied. |
| Adipocytes stain as strongly as neighboring expected-positive cells. | HPA reports adipocytes as Not detected (HPA: adipose tissue). Cross-reactivity or endogenous detection activity is possible (general IHC practice). | Compare matched tissue morphology and a control without primary antibody. If color persists without primary, investigate the detection system and its blocking steps (general IHC practice). |
| The slide has mainly nuclear staining. | Nuclear dominance disagrees with cytoplasmic tissue IHC (HPA: tissue IHC) and mitochondrial inner membrane residence (UniProt Q9Y276). | Recheck cell boundaries and the counterstain, then compare a known-positive cytoplasmic control. Review antibody concentration and detection background as general IHC practice before interpreting the nuclear signal. |
| Brown color is widespread but lacks a recognizable cell pattern. | Diffuse background can follow excessive antibody, insufficient blocking, or incomplete washing (general IHC practice); it cannot establish the HPA cytoplasmic pattern. | Inspect the control without primary antibody, then optimize blocking, antibody concentration, and washes under the assay's general IHC workflow. Score only interpretable cellular staining. |
| Only weak staining appears in bone marrow hematopoietic cells. | Low staining is compatible with the supplied HPA observation for those cells (HPA: bone marrow). | Check hepatocytes or a supplied High-staining epithelial population in the same run (HPA: tissue IHC). Do not classify a run as failed solely because the bone marrow signal is weak. |
| An IF/ICC image looks vesicular while paraffin IHC looks cytoplasmic. | HPA reports vesicles as an Uncertain main ICC-IF location and cytoplasmic tissue IHC as Supported (HPA: subcellular and tissue IHC). | Keep the assay-specific observations distinct. Use the IF/ICC guide for its controls and interpretation; do not change the IHC compartment call on the basis of the uncertain vesicle assignment alone (HPA: ICC-IF location status). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot BCS1L staining in paraffin sections by checking retrieval, compartmental pattern, controls, and scoring before interpreting differences in chromogenic signal.
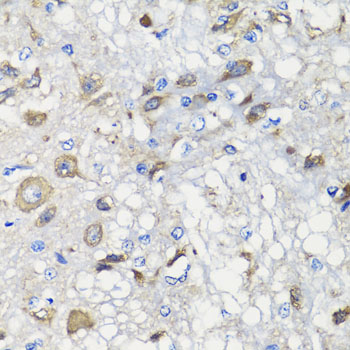
The anti-BCS1L antibody A04885 has IHC images from paraffin-embedded human stomach and rat brain; IF/ICC is listed for human, mouse, and rat without an IF image (catalog: A04885).
A04885 has IHC images from paraffin-embedded human stomach and rat brain, each stained at 1:100 (A04885 IHC captions). IF/ICC is listed for A04885, but no IF image is supplied; mouse is listed as reactive without a supplied IHC image (catalog: A04885 applications, reactivity, image alts).
Which to pick: For tissue IHC, choose A04885: its own captions document paraffin sections and microwave antigen retrieval in 10 mM PBS at pH 7.2; the fixative is unreported (A04885 IHC captions). For IF/ICC, A04885 is the listed option at 1:50–1:200, though no IF image is supplied; its host is rabbit and clonality is unreported (catalog: A04885 applications, IF dilution, host, clone, IF image alts). For cross-species work, A04885 lists human, mouse, and rat reactivity, with supplied IHC images for human and rat samples (catalog: A04885 reactivity; A04885 IHC captions).