This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section C1QC IHC with catalog antibody A05666-1 at 1:100–1:300 (datasheet: IHC 1:100–1:300). Interpret mainly plasma positivity (HPA tissue IHC) alongside C1QC secretion and cell-surface association (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Mainly plasma staining (HPA tissue IHC); secreted/cell surface (UniProt) | |
| Staining pattern | Mainly plasma; medium glandular and stromal staining (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Colon+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Secretion can separate tissue RNA from protein staining (HPA tissue IHC) | |
| Regulation | Lymphoid tissue-enhanced RNA (HPA tissue RNA) | |
| Isoform / epitope | No annotated isoforms; mature chain starts at aa 29 (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by published C1QC IHC methods for colon tissue and vascular tissue (PMC9589315; PMC11880100).
| Sample | Paraffin-embedded human lung carcinoma tissue; fixative not specified (datasheet A05666-1) |
| Fixation | Image fixative and duration unreported (datasheet A05666-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-C1QC, 1:100 - 1:300 (datasheet A05666-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | C1QC-positive staining in glandular cells of colon (HPA tissue IHC: Medium). HPA tissue profile: Mainly plasma positivity. No signal in the no-primary control. |
C1QC is secreted and can associate with antigen–antibody complexes on pathogen surfaces; it has no transmembrane segment (UniProt P02747 subcellular location; topology). In tissue sections, expect mainly plasma positivity, with medium staining reported in selected glandular cells and endometrial stromal cells (HPA: tissue IHC). Interpret cell-associated staining cautiously: HPA rates the tissue pattern Supported but reports low consistency between staining and RNA expression (HPA: reliability).
| Chromogen is mainly in plasma-associated spaces, with some staining along nearby tissue structures. | This fits the reported mainly plasma-positive pattern (HPA: tissue IHC) and the secreted location of C1QC (UniProt P02747 subcellular location). Location alone cannot identify the cell that produced the protein; HPA notes that RNA and protein locations can differ for a secreted variant (HPA: reliability description). |
| Medium staining appears in colon, fallopian tube, gallbladder, or prostate glandular cells, or in endometrial stromal cells. | These are reported positive cell and tissue combinations (HPA: tissue IHC). Assess each alongside its local plasma signal and a negative detection control (general IHC practice). Medium staining supports the reported pattern but does not, by itself, establish local C1QC synthesis (HPA: reliability description). |
| Strong, sharply nuclear staining dominates the section. | A dominant nuclear pattern conflicts with the secreted and cell-surface annotations (UniProt P02747 subcellular location). Treat it as suspect and check the negative detection control, counterstain, and antibody-specific staining pattern (general IHC practice). |
| Adipocytes or cardiomyocytes stain strongly, or caudate glial cells show a strong cell-body signal. | Those cell types were reported as not detected in the named tissues (HPA: tissue IHC). Consider cross-reactivity or endogenous detection activity, especially if the signal also appears in a negative detection control (general IHC practice). A result in one specimen is not proof of either cause. |
| Most structures acquire a uniform haze, or no signal appears in a section expected to be positive. | Diffuse haze makes the reported plasma-focused pattern difficult to judge (HPA: tissue IHC); inspect negative controls for background (general IHC practice). For absent signal, first verify the chosen positive tissue and cell type against the HPA record, then check the staining run (HPA: tissue IHC; general IHC practice). |
| Secretion and surface association | C1QC is annotated as secreted and cell-surface-associated, with no transmembrane segment (UniProt P02747 subcellular location; topology). Interpret extracellular signal as potentially meaningful, while avoiding an inference that the nearest stained cell produced it. |
| Protein processing | The annotated signal peptide spans residues 1–28 and the mature chain spans 29–245 (UniProt P02747 processing). An epitope in the signal peptide and one in the mature chain would warrant different interpretation; this payload does not locate either antibody's epitope. |
| Tissue pattern and confidence | HPA reports mainly plasma positivity and rates tissue IHC Supported, while noting low agreement with RNA expression for this secreted protein (HPA: tissue IHC; reliability). Use the tissue staining record to assess appearance, not RNA location as a strict map of protein. |
| Antibody validation | HPA lists HPA001471 and CAB009828 as IHC Supported; neither has an ICC status in the supplied antibody record (HPA: antibodies). Supported is the reported status here; the payload does not report IHC Enhanced for either antibody. |
| IF/ICC interpretation? | HPA lists C1QC as secreted but provides no main ICC-IF location or cell-line images in this record (HPA: subcellular ICC-IF). There is therefore no image-backed intracellular IF pattern to recommend here; consult the separate IF/ICC guide for that application. |
| Situation | Likely cause | Next action |
|---|---|---|
| No chromogen appears in the selected positive tissue. | The field may lack the reported positive compartment, or the IHC detection run may have failed (HPA: tissue IHC; general IHC practice). | Inspect plasma-containing areas and the named HPA-positive cell type in the same tissue; confirm that the run's positive detection control stained (HPA: tissue IHC; general IHC practice). If both are blank, check reagent preparation, incubation, and detection steps (general IHC practice). |
| The section is broadly brown, including regions expected to be unstained. | Background from detection chemistry or nonspecific antibody binding can obscure the mainly plasma-positive pattern (general IHC practice; HPA: tissue IHC). | Compare a negative detection control and review blocking, washing, antibody concentration, and chromogen development (general IHC practice). Score C1QC only after the compartment pattern is distinguishable (HPA: tissue IHC). |
| Strong staining appears in adipocytes, cardiomyocytes, or caudate glial cells. | These named cell types were not detected in HPA tissue IHC; cross-reactivity or endogenous detection activity is possible (HPA: tissue IHC; general IHC practice). | Verify cell identity on the counterstained section, inspect a negative detection control, and compare with the HPA-positive pattern before assigning the signal to C1QC (HPA: tissue IHC; general IHC practice). |
| Only glandular or stromal cells stain, with little evident plasma signal. | Medium glandular and endometrial stromal staining is reported, but HPA describes the overall pattern as mainly plasma-positive (HPA: tissue IHC). | Review nearby plasma-containing areas and a matching HPA tissue entry. Record the cell type and compartment separately; do not infer local synthesis from cell staining alone because protein and RNA locations may differ (HPA: tissue IHC; reliability description). |
| A bright nuclear pattern is the principal finding. | Nuclear localisation is unsupported by the supplied secreted and cell-surface annotations (UniProt P02747 subcellular location). | Check whether the counterstain was mistaken for chromogen, then compare negative detection controls and the expected plasma-associated distribution (general IHC practice; HPA: tissue IHC). |
| An IF/ICC image shows puncta or an intracellular pattern that seems inconsistent with IHC. | The supplied HPA ICC-IF record has no main location or cell-line images for C1QC; IHC tissue distribution cannot establish an intracellular IF pattern (HPA: subcellular ICC-IF; tissue IHC). | Describe the observed IF compartments without assigning a validated C1QC location from this record; use the separate IF/ICC guide for application-specific evaluation (HPA: subcellular ICC-IF). |
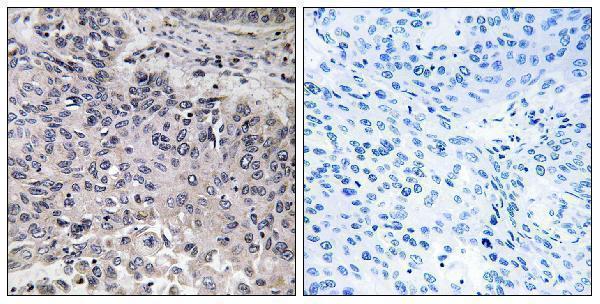
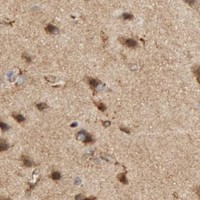


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Low consistency between antibody staining and RNA expression data. At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Colon | Glandular cells | Medium | Protein (IHC) | HPA → |
| Endometrium | Cells in endometrial stroma | Medium | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | Medium | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | Medium | Protein (IHC) | HPA → |
| Prostate | Glandular cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot C1QC staining by checking retrieval, compartment, controls and scoring in paraffin section chromogenic IHC; use the IF guidance for multiplex experiments.
A05666-1 has a C1QC IHC image from a human lung carcinoma paraffin section (catalog image caption); the catalog lists IHC and IF applications and Human, Mouse and Rat reactivity (catalog applications and reactivity).
A05666-1 has a peptide-blocked IHC comparison in paraffin-embedded human lung carcinoma tissue (catalog image caption). The catalog lists IHC, IF and ICC applications and Human, Mouse and Rat reactivity for A05666-1; no IF image is supplied (catalog applications, reactivity and image listings).
Which to pick: Choose A05666-1 for tissue IHC: its own image shows staining of a paraffin-embedded human lung carcinoma section with a peptide-blocked comparison; the fixative is unreported (catalog image caption). For IF/ICC, A05666-1 is catalog-listed for both applications at 1:50 for IF, but no IF image is supplied (catalog applications, IF dilution and image listings). For work across species, A05666-1 is the listed rabbit polyclonal with Human, Mouse and Rat reactivity; the supplied IHC image shows human tissue only (catalog host, dilution_raw, reactivity and image caption).