This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic CARD6 IHC on paraffin sections using the catalog antibody A13067 at 1:50–1:200 (datasheet). Compare staining with HPA high-staining glandular cells and assess cytoplasmic, nuclear and membrane signal (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic, nuclear and membrane staining (HPA tissue IHC) | |
| Staining pattern | Glandular cells show cytoplasmic, nuclear and membrane staining (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet A13067); verify before use. | |
| Caveat | Staining and RNA show medium consistency; verify specificity (HPA tissue IHC) | |
| Regulation | Low tissue specificity; stimulus regulation unreported (HPA tissue IHC; UniProt) | |
| Isoform / epitope | No isoforms or transmembrane segment annotated (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet) with a published CARD6 method using paraffin sections (PMC4792137).
| Sample | Paraffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A13067) |
| Fixation | Image fixative and duration unreported (datasheet A13067); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-CARD6, 1:50-1:200 (datasheet A13067) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | CARD6-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic, nuclear and membrane expression. No signal in the no-primary control. |
In paraffin-section IHC, expect CARD6 staining in cytoplasm, nuclei, or at cell membranes; HPA reports a broad pattern and does not assign a single required compartment (HPA tissue IHC). High staining is reported in specified glandular, hematopoietic, respiratory epithelial, and endothelial cells (HPA: High). Interpret this as an expected pattern, not definitive target verification: HPA rates the IHC evidence Approved, with medium staining–RNA consistency and external verification pending (HPA tissue IHC). CARD6 has no annotated transmembrane segment (UniProt Q9BX69 topology).
| Cell-associated chromogen appears in cytoplasm, nuclei, or at membranes of HPA-listed cell types. | This fits the reported broad CARD6 pattern (HPA tissue IHC). Compare staining within identified cells; compartment alone cannot establish antibody specificity. High staining in those cells is an HPA observation, not a required score for every section (HPA: High). |
| Signal is confined to luminal material, extracellular matrix, debris, or a sharp tissue edge. | These sites fall outside HPA's reported cell-associated cytoplasmic, nuclear, and membrane pattern (HPA tissue IHC). Suspect deposition or another staining artefact; inspect morphology and controls before scoring cells. Nuclear or membrane staining alone is not a wrong-compartment finding here (HPA tissue IHC). |
| Strong staining appears mainly in cells other than those identified as High by HPA. | Check cell identity and the detection controls before attributing it to CARD6. Cross-reactivity or endogenous detection activity are possible explanations (general IHC practice). HPA reports low tissue RNA specificity, so staining in another cell type cannot by itself prove cross-reactivity (HPA tissue IHC). |
| A uniform haze covers several cell types, stroma, or the whole section. | A field-wide signal obscures the cell-associated pattern needed for interpretation (HPA tissue IHC). Nonspecific binding, residual reagent, or chromogen development may contribute (general IHC practice). Treat intensity scores as unreliable until background is controlled. |
| There is no detectable signal in a section expected to contain HPA-listed High cells. | First verify that the relevant cells are present and preserved; examples include adrenal glandular cells and bone-marrow hematopoietic cells (HPA: High). A blank result then warrants a check of antibody, retrieval, and detection conditions (general IHC practice). It does not establish absence of CARD6. |
| Compartment and topology | HPA reports cytoplasmic, nuclear, and membrane staining (HPA tissue IHC). CARD6 lacks an annotated transmembrane segment (UniProt Q9BX69 topology); membrane-associated staining should therefore be described as an observed pattern, not evidence that CARD6 spans the membrane. |
| Choice of positive tissue and cell type | HPA lists High staining in glandular cells of adrenal gland, appendix, cervix, and duodenum; hematopoietic cells of bone marrow; respiratory epithelial cells of bronchus; and endothelial cells of cerebral cortex and colon (HPA: High). Select a listed cell population that can be identified on the section. |
| Strength of antibody evidence | HPA lists antibody HPA041933 as a rabbit polyclonal with IHC Approved status, and describes medium staining–RNA consistency with external verification pending (HPA antibodies; HPA tissue IHC). The supplied record does not report IHC Enhanced validation (HPA antibodies). Interpret agreement with the pattern as supportive rather than conclusive. |
| Can this IHC pattern be used as an IF/ICC expectation? | HPA provides no main ICC-IF location and lists no cell lines with ICC-IF images for CARD6 (HPA subcellular). The tissue IHC pattern can guide what to inspect, but it does not establish an IF/ICC localisation result. This section supplies no IF/ICC protocol option. |
| Target-specific retrieval or processing effect | Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation. |
| Situation | Likely cause | Next action |
|---|---|---|
| An HPA-listed High cell population is present, but the section is blank. | The primary antibody, retrieval, or detection sequence may have failed (general IHC practice); a blank section alone does not identify which step failed. | Confirm cell identity, then check a concurrent positive section, reagent application, retrieval conditions, and detection steps (general IHC practice). Use an HPA-listed High cell population as the expected reference (HPA: High). |
| Most of the section shows weak, diffuse brown haze. | Nonspecific binding or excess chromogen development can obscure cell boundaries (general IHC practice). | Review blocking, antibody dilution, wash steps, and development time; score only interpretable cell-associated signal (general IHC practice; HPA tissue IHC pattern). No CARD6-specific working dilution is supplied. |
| Brown signal persists in a control run without primary antibody. | Endogenous detection activity or a detection-system artefact may be present (general IHC practice). | Investigate the detection reagents and, where relevant, endogenous enzyme blocking before assigning the signal to CARD6 (general IHC practice). |
| Signal concentrates at cut edges, folds, debris, or luminal material. | Section geometry or precipitated detection product can mimic a positive cell pattern (general IHC practice). | Inspect an intact area and compare with the control section; exclude deposits outside identifiable cells from scoring (general IHC practice; HPA tissue IHC pattern). |
| Strong staining occurs in an unexpected cell population. | Cell identification, cross-reactivity, or endogenous activity may explain the result (general IHC practice). HPA's low tissue RNA specificity does not make an unlisted population definitively negative (HPA tissue IHC). | Recheck morphology and detection controls, then report the observed cell type and compartment without claiming CARD6 specificity from staining alone (general IHC practice; HPA tissue IHC). |
| A reader expects only cytoplasmic staining or treats all membrane staining as invalid. | That rule conflicts with HPA's general cytoplasmic, nuclear, and membrane profile (HPA tissue IHC). The absence of a transmembrane segment does not resolve the observed membrane pattern (UniProt Q9BX69 topology). | Record compartment and cell type separately, compare with HPA-listed High cells, and qualify uncertain localisation rather than discarding it by compartment alone (HPA tissue IHC; general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cerebral cortex | Endothelial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: CARD6 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Use compartment, cell type, and section controls to interpret CARD6 staining in paraffin sections; its tissue IHC evidence does not establish a target-specific fixation response.
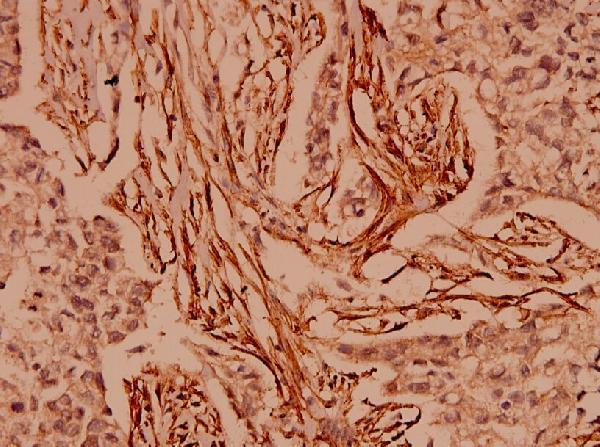
The catalog lists two human-reactive CARD6 antibodies for IHC and IF (catalog: applications and reactivity). A13067 has an IHC image from a paraffin-embedded human breast carcinoma section (catalog image caption).
A13067 is the only SKU with a rendered card; its image shows IHC on paraffin-embedded human breast carcinoma at 1:100 (catalog image caption). It also lists IF and human reactivity, but has no IF image (catalog: applications, reactivity, image alts).
Which to pick: Choose A13067 for tissue IHC because its own image documents a paraffin-embedded human section; the fixative is unreported (catalog image caption). For IF, both A13067 and A13067-1 list the application, but neither provides an IF image or lists ICC, so there is no documented basis to prefer one for IF/ICC (catalog: applications and image alts). Neither has documented cross-species reactivity: both list Human only, and neither reports a clone (catalog: reactivity and clone).